
Facial Nerve Paralysis Dr Vishal Sharma Gabriel Fallopius

Facial Nerve Paralysis Dr. Vishal Sharma

Gabriel Fallopius (1523 -62)

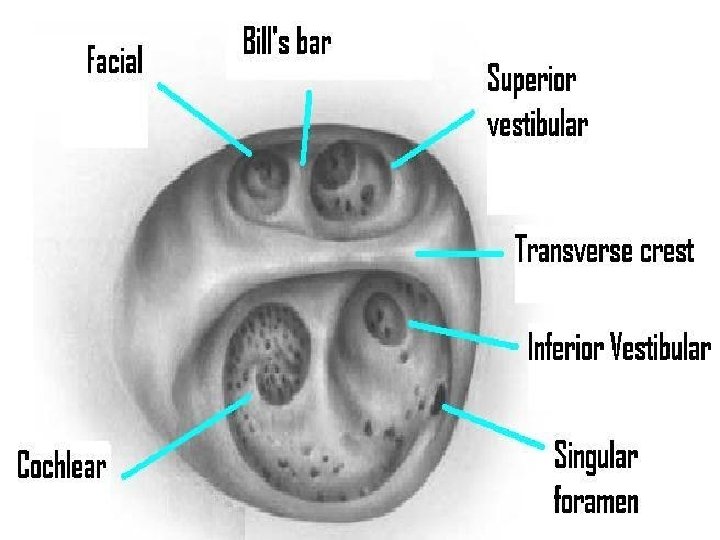
Anatomy of Facial Nerve l Motor root: 7000 axons l Sensory root (Nervus intermedius / Wrisberg): 3000 axons. Joins motor root at fundus of I. A. C. l Motor: predominantly to facial muscles l Secretomotor: lacrimal, submandibular, sublingual l Taste: anterior 2/3 rd of tongue l Sensory: Post-aural / concha / ext. auditory canal

Course of facial nerve
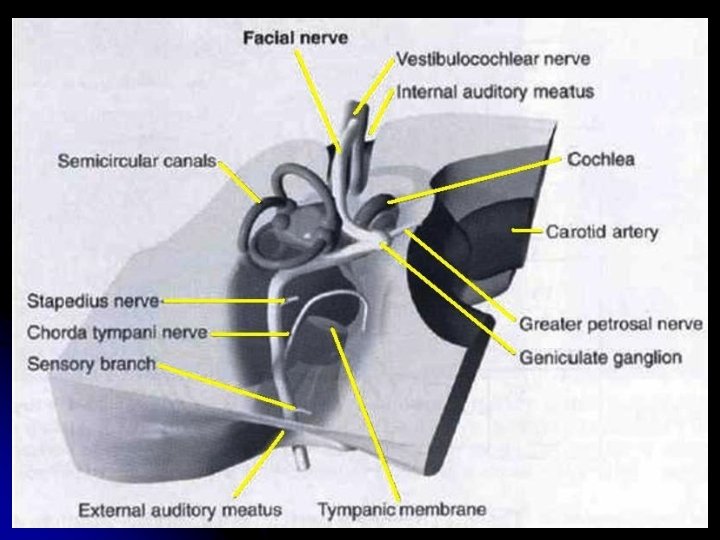
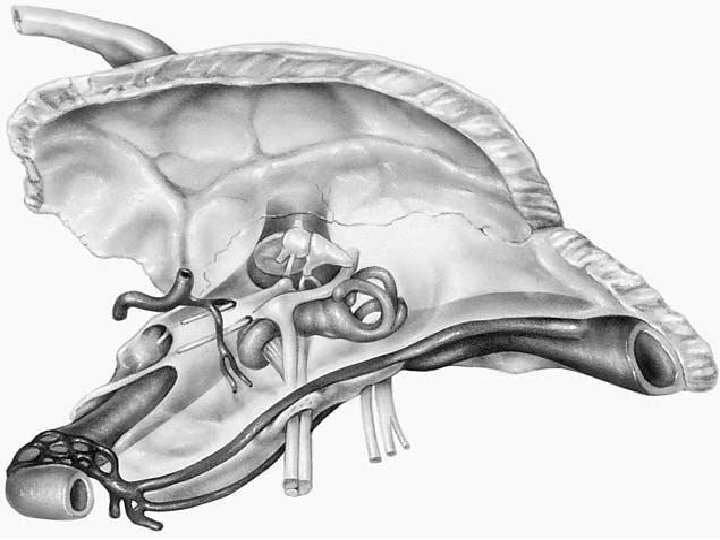
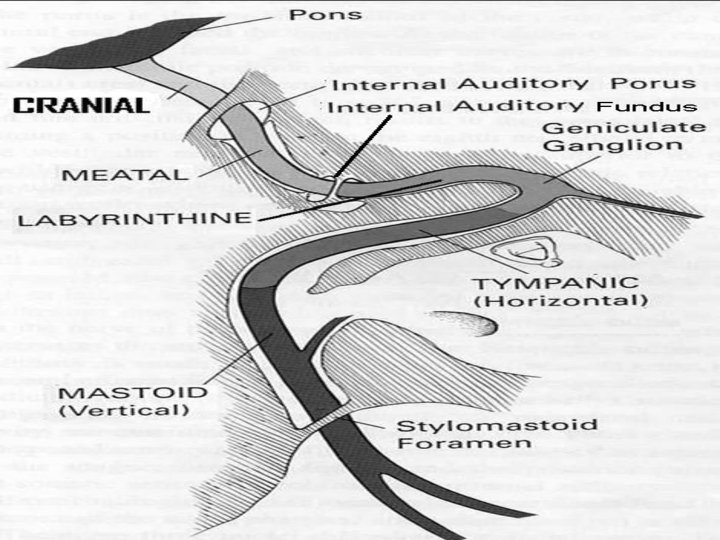
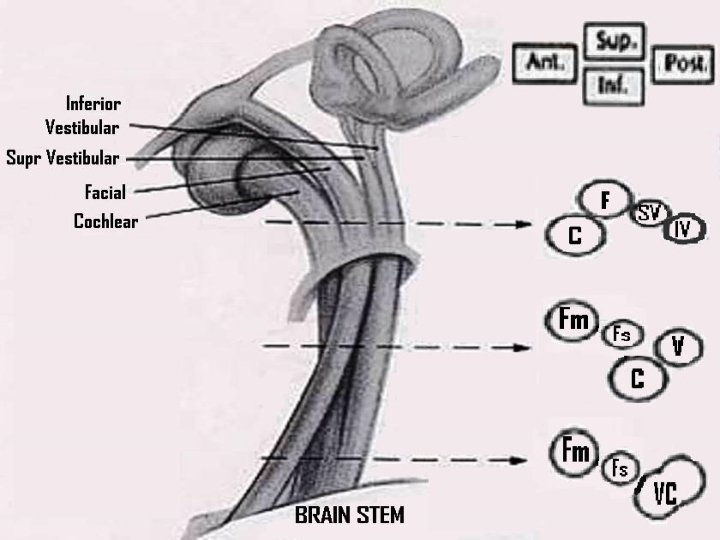
Parts of facial nerve Intracranial: within cerebello-pontine angle Intra-temporal Meatal segment Labyrinthine segment Tympanic segment Mastoid segment Extra-cranial Extra-parotid Intra-parotid (terminal)
Segments of Facial Nerve 1. Supranuclear: Fibers in cerebral cortex to brain stem 2. Brain stem: Motor nucleus of facial nerve (pons) 3. Intra-cranial (12 mm): Brain stem to entry into IAC 4. Meatal (10 mm): Within Internal Auditory Canal 5. Labyrinthine (4 mm): Fundus of I. A. C. to Geniculate gangl. 6. Tympanic (11 mm): Geniculate ganglion to pyramid 7. Mastoid (13 mm): Pyramid to stylomastoid foramen 8. Extra-temporal (15 mm): S. M. foramen to pes anserinus

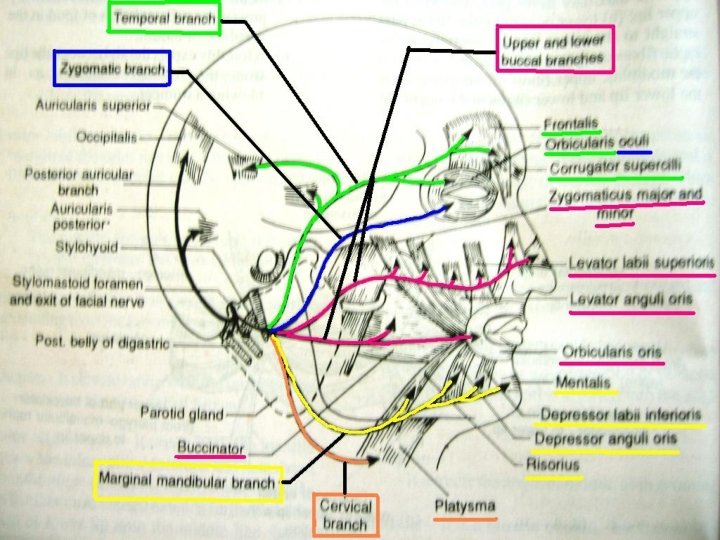
Primary branches of facial nerve Intra-temporal: greater superficial petrosal, stapedius, chorda tympani Extra-parotid: post-auricular, stylohyoid, posterior belly of digastric Intra-parotid: temporal, zygomatic, buccal, marginal mandibular, descending cervical
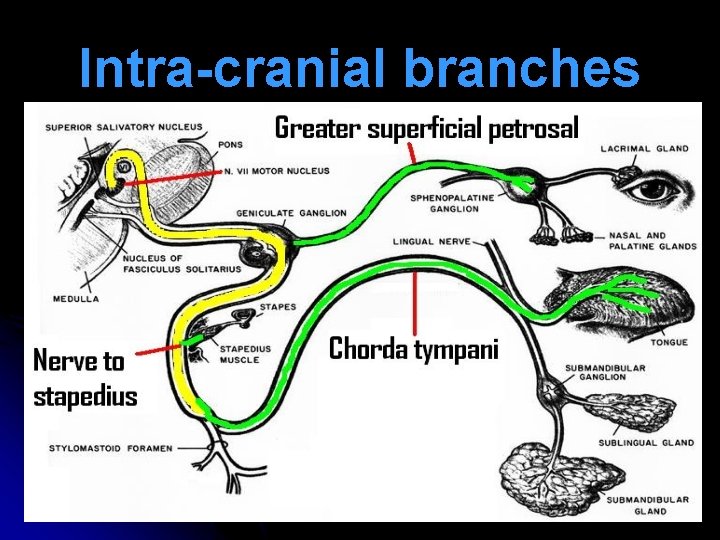
Intra-cranial branches
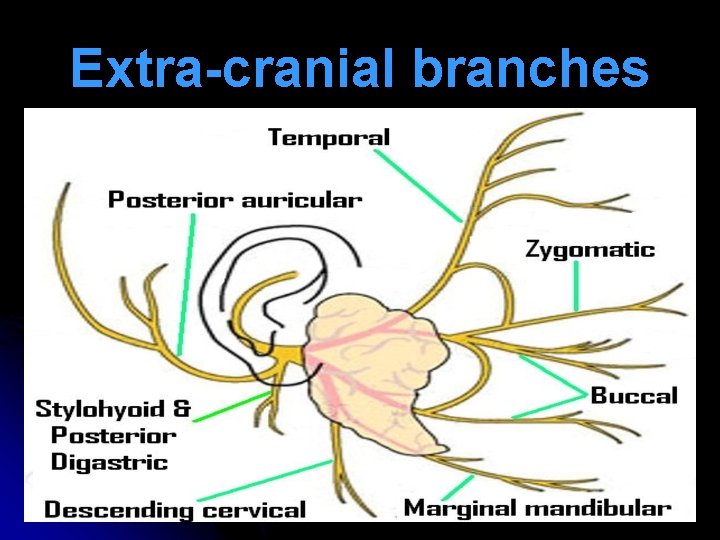
Extra-cranial branches

Communicating branches to: Meatal: vestibulo-cochlear Tympanic: lesser petrosal otic ganglion Mastoid: auricular branch of vagus Extra-parotid: glossopharyngeal, auriculotemporal, vagus, greater auricular, lesser occipital Terminal: branches of trigeminal

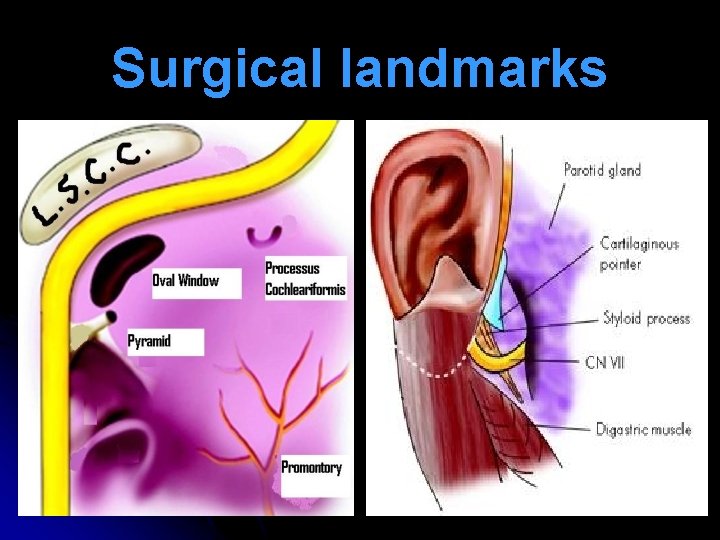
Surgical landmarks

Cochleariform process: small bony protuberance (from which tensor tympani muscle turns 900 to insert into malleus) lies 1 mm inferior to geniculate ganglion at anterior end of tympanic segment. Cog: bony ridge hanging from tegmen tympani lies 1 mm above & posterior to cochleariform process. Incus short process: 2 mm below lies external genu Lateral Semicircular Canal: 2 mm Antero-Infero. Medial lies external genu Oval window: 1 mm above lies external genu
Inferior edge of Posterior S. C. C. : 2 mm anterior & lateral lies mastoid segment of facial nerve Tympano-mastoid suture in posterior canal wall: 58 mm medial lies mastoid segment of facial nerve Digastric ridge in mastoid tip: leads antero-medially to mastoid segment of facial nerve Groove between mastoid & bony E. A. C. meatus: bisected by facial nerve Tragal pointer: 1 cm antero-infero-medial is facial nv Root of styloid process: lateral lies facial nerve Superior border of posterior belly of digastric: superior & parallel lies facial nerve
Surgical landmarks
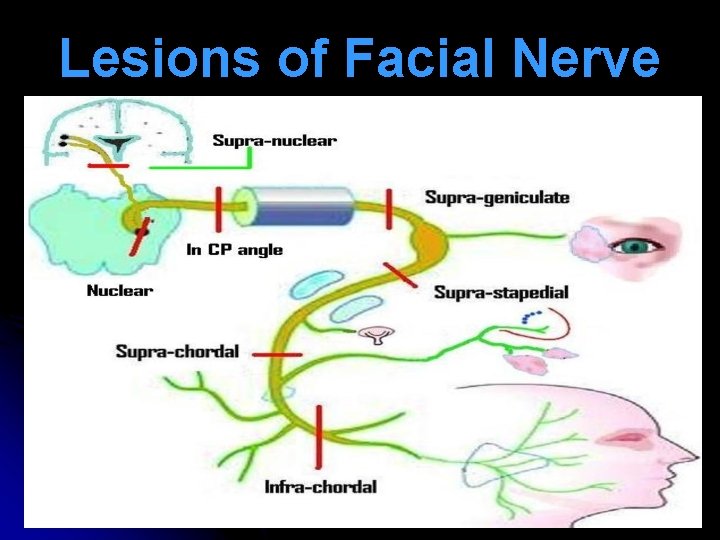
Lesions of Facial Nerve
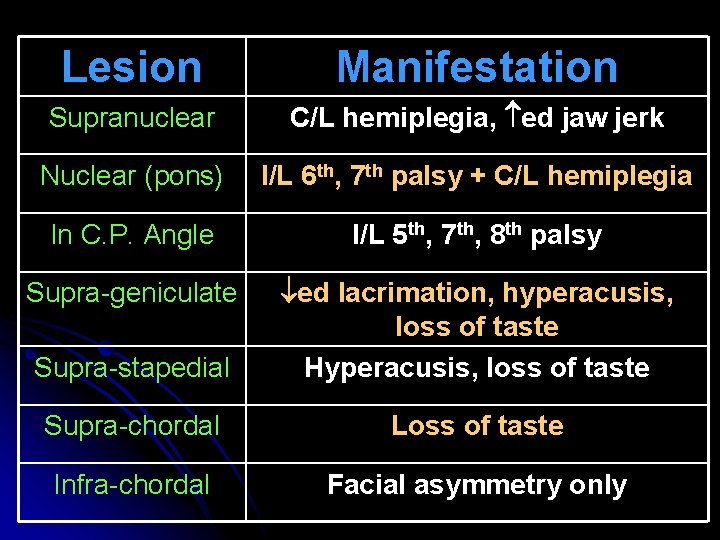
Lesion Manifestation Supranuclear C/L hemiplegia, ed jaw jerk Nuclear (pons) I/L 6 th, 7 th palsy + C/L hemiplegia In C. P. Angle I/L 5 th, 7 th, 8 th palsy Supra-geniculate Supra-stapedial ed lacrimation, hyperacusis, loss of taste Hyperacusis, loss of taste Supra-chordal Loss of taste Infra-chordal Facial asymmetry only
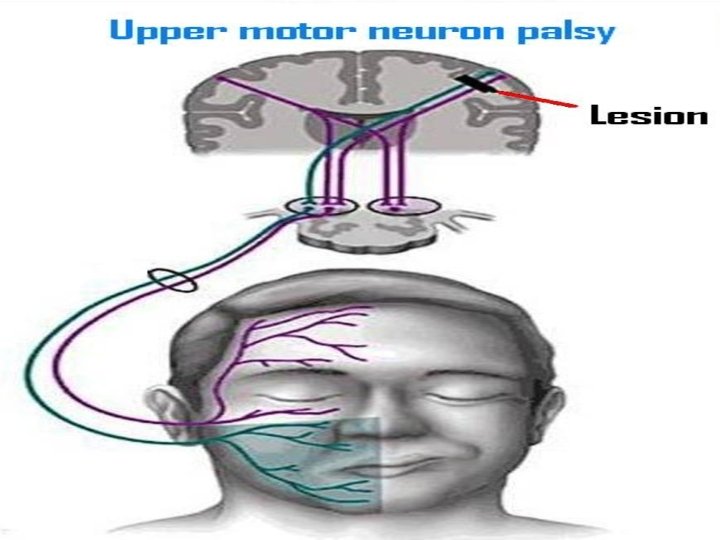
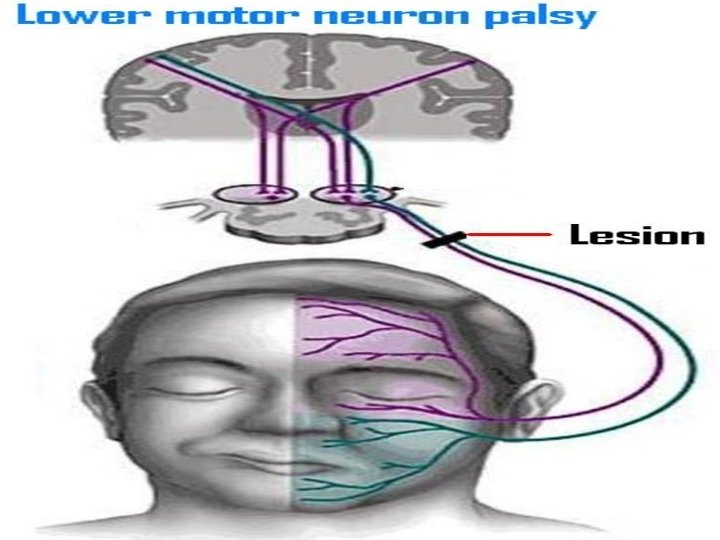
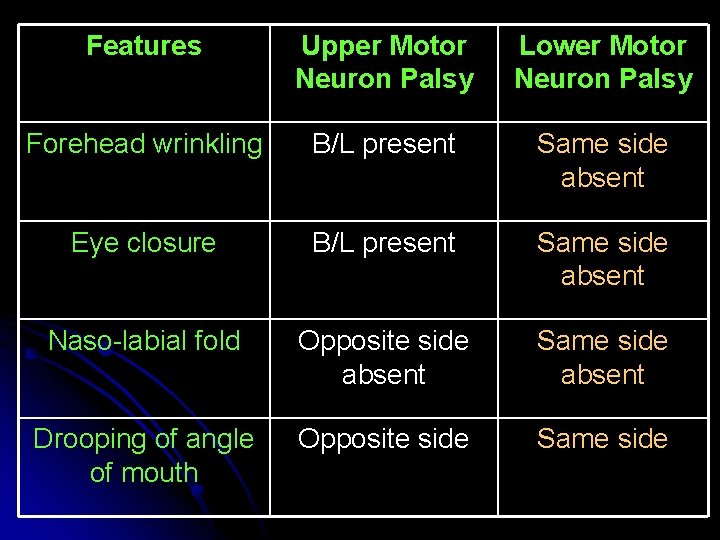
Features Upper Motor Neuron Palsy Lower Motor Neuron Palsy Forehead wrinkling B/L present Same side absent Eye closure B/L present Same side absent Naso-labial fold Opposite side absent Same side absent Drooping of angle of mouth Opposite side Same side

Etiology of Facial Nerve Palsy
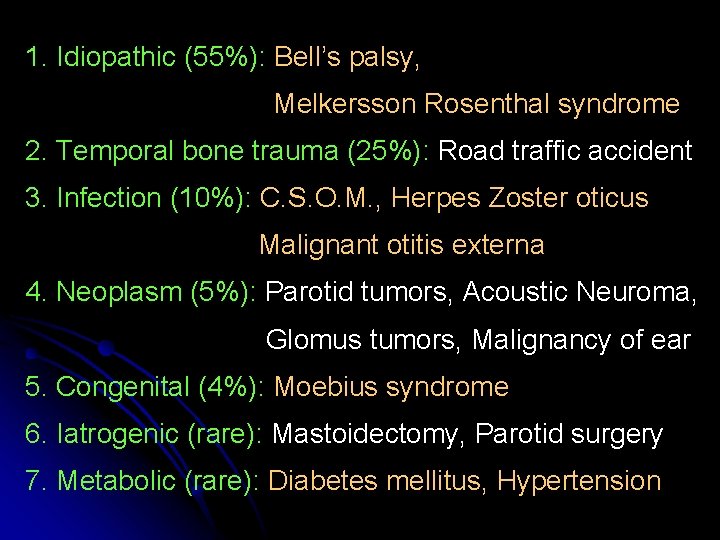
1. Idiopathic (55%): Bell’s palsy, Melkersson Rosenthal syndrome 2. Temporal bone trauma (25%): Road traffic accident 3. Infection (10%): C. S. O. M. , Herpes Zoster oticus Malignant otitis externa 4. Neoplasm (5%): Parotid tumors, Acoustic Neuroma, Glomus tumors, Malignancy of ear 5. Congenital (4%): Moebius syndrome 6. Iatrogenic (rare): Mastoidectomy, Parotid surgery 7. Metabolic (rare): Diabetes mellitus, Hypertension

Sunderland’s Classification (1951)
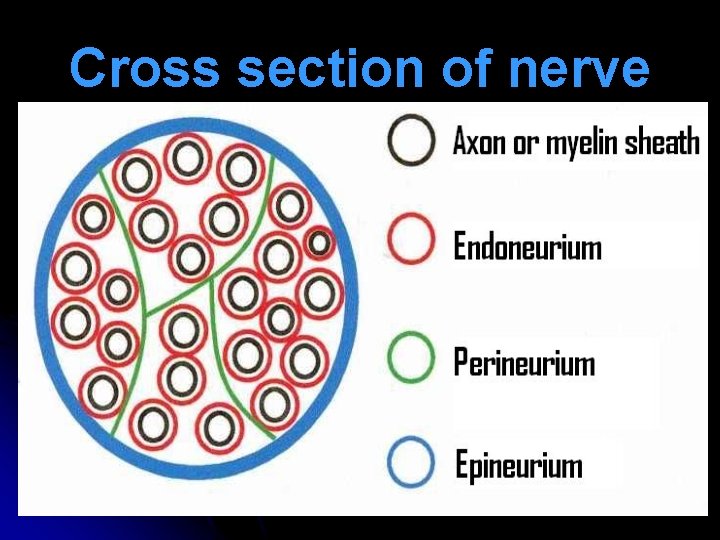
Cross section of nerve
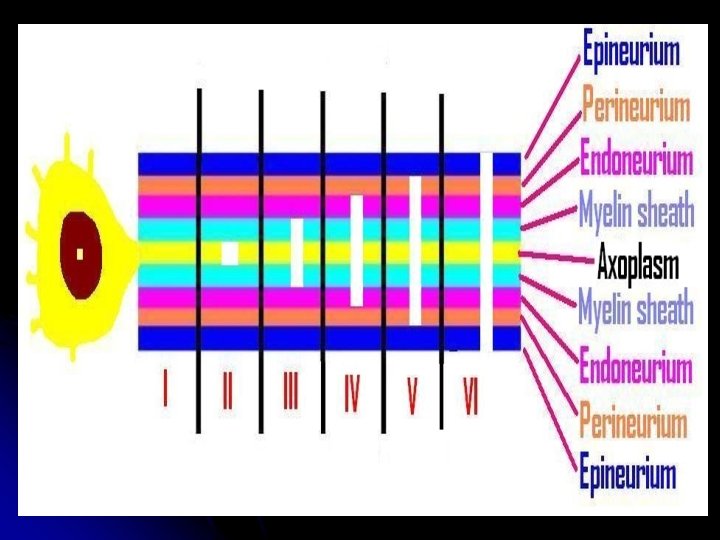
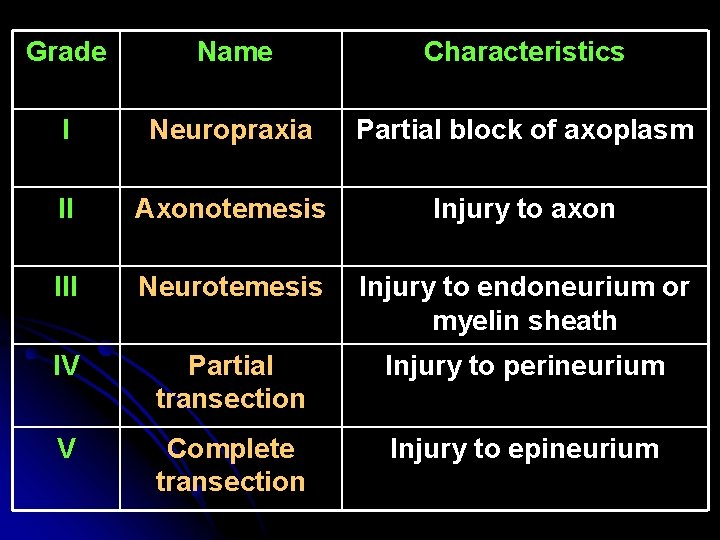
Grade Name Characteristics I Neuropraxia Partial block of axoplasm II Axonotemesis Injury to axon III Neurotemesis Injury to endoneurium or myelin sheath IV Partial transection Injury to perineurium V Complete transection Injury to epineurium

House Brackmann Classification (1 year post -injury)
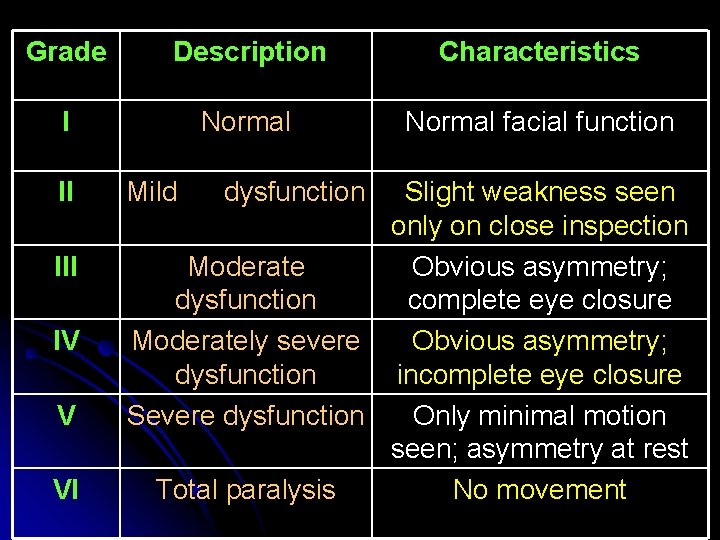
Grade Description Characteristics I Normal facial function II IV V VI Mild dysfunction Slight weakness seen only on close inspection Moderate Obvious asymmetry; dysfunction complete eye closure Moderately severe Obvious asymmetry; dysfunction incomplete eye closure Severe dysfunction Only minimal motion seen; asymmetry at rest Total paralysis No movement
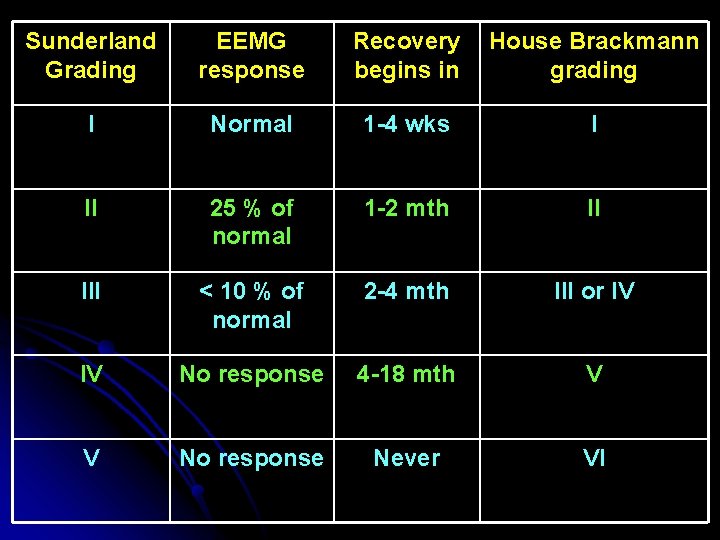
Sunderland Grading EEMG response Recovery begins in House Brackmann grading I Normal 1 -4 wks I II 25 % of normal 1 -2 mth II III < 10 % of normal 2 -4 mth III or IV IV No response 4 -18 mth V V No response Never VI
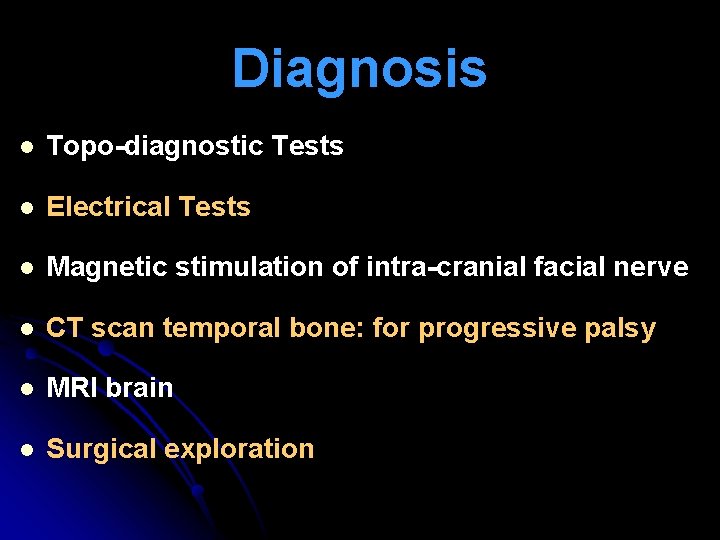
Diagnosis l Topo-diagnostic Tests l Electrical Tests l Magnetic stimulation of intra-cranial facial nerve l CT scan temporal bone: for progressive palsy l MRI brain l Surgical exploration
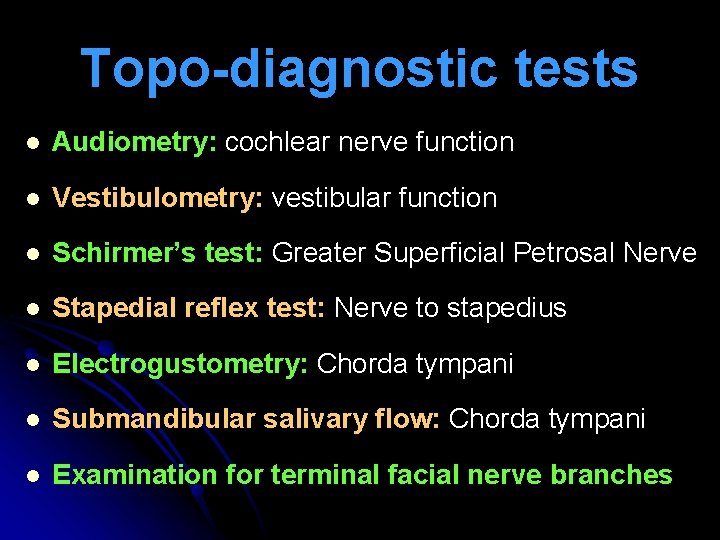
Topo-diagnostic tests l Audiometry: cochlear nerve function l Vestibulometry: vestibular function l Schirmer’s test: Greater Superficial Petrosal Nerve l Stapedial reflex test: Nerve to stapedius l Electrogustometry: Chorda tympani l Submandibular salivary flow: Chorda tympani l Examination for terminal facial nerve branches
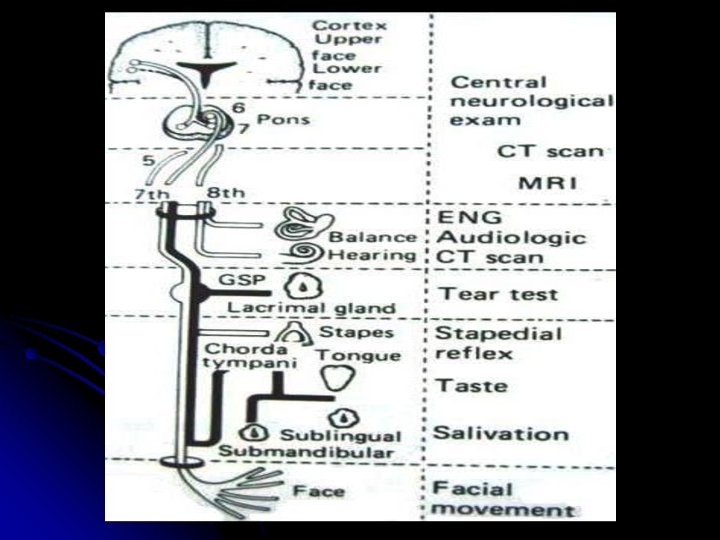

Schirmer’s Test Unilateral wetness ed by >30% of total amount of both eyes after 5 minutes = Schirmer test positive lesion at or proximal to geniculate ganglion
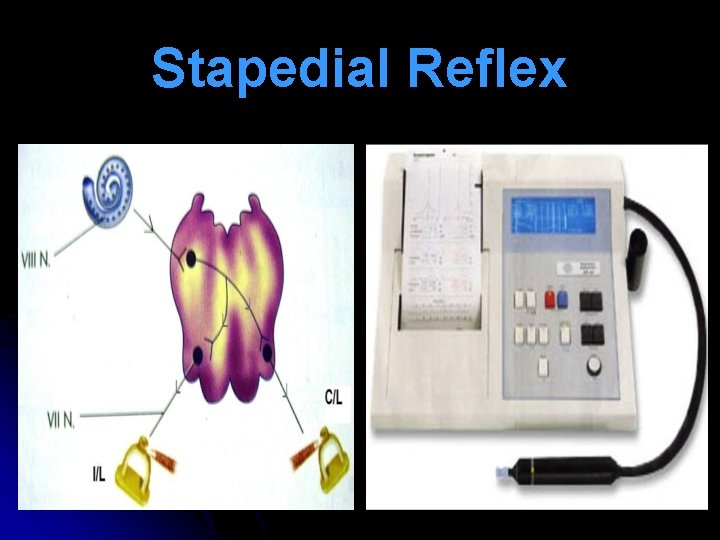
Stapedial Reflex

Electrogustometry Measures minimum amount of current required to excite sensation of taste
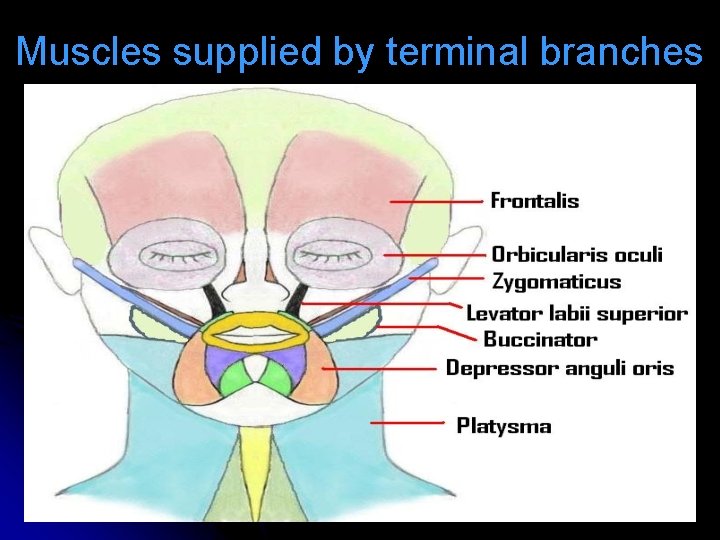
Muscles supplied by terminal branches

Electrical tests
Nerve Excitability Test l Stimulating electrode used over terminal branches of facial nerve l Minimum current intensity required to produce minimal muscle movement is calculated l Normal side compared to paralyzed side l Difference > 3. 5 m. Amp = unfavorable prognosis
Maximal stimulation test l Stimulating electrode used over terminal branches of facial nerve l Minimum current intensity required to produce maximal muscle movement is calculated l Normal side compared to paralyzed side l Difference > 3. 5 m. Amp = unfavorable prognosis
Electro-neuronography l Terminal branch of facial nerve stimulated & action potential recorded in appropriate muscle l Paralyzed side compared to normal side (which is taken as 100%) l Response > 10% = 85 -95 % chance of recovery l Response < 10% = 25 % chance of recovery
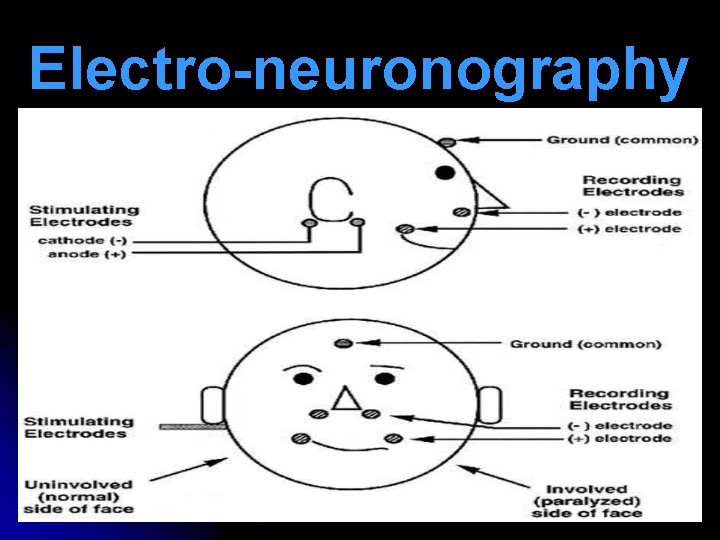
Electro-neuronography
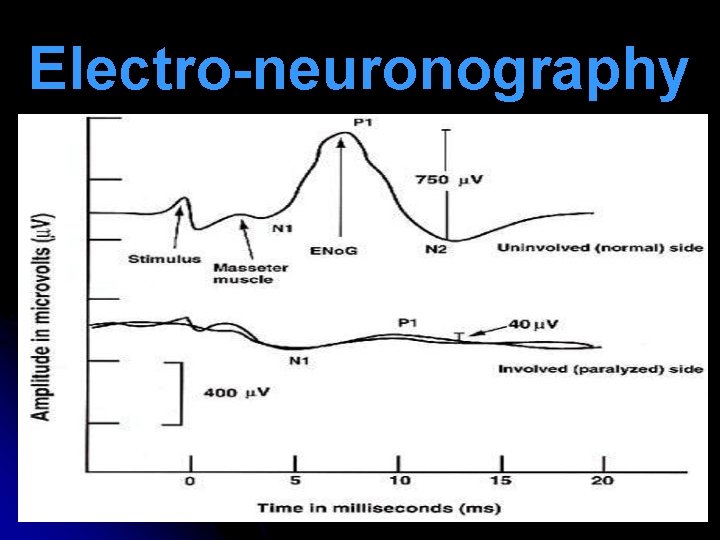
Electro-neuronography
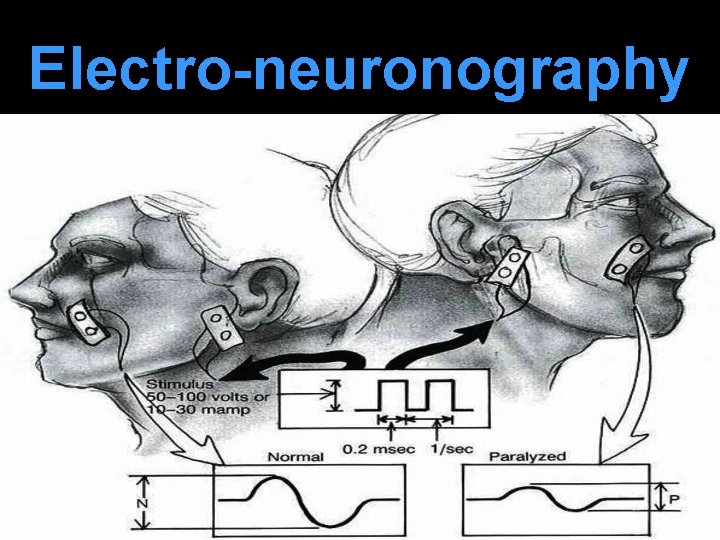
Electro-neuronography

Electromyography Records spontaneous activity of facial muscles
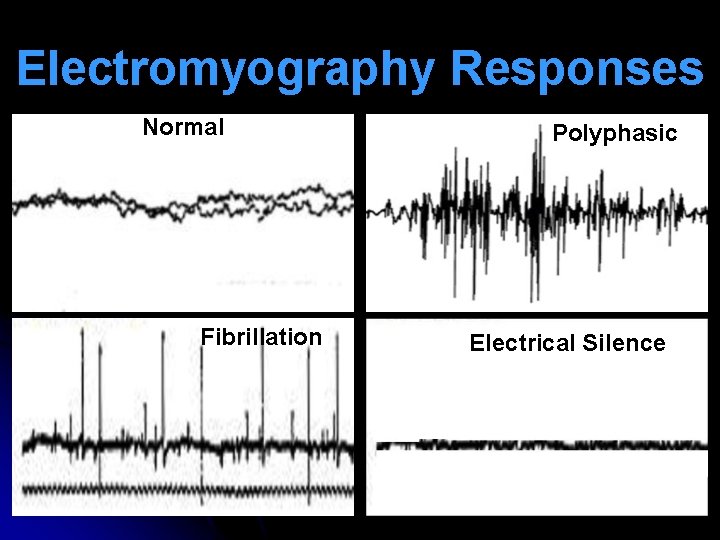
Electromyography Responses Normal Fibrillation Polyphasic Electrical Silence
Response Interpretation l Normal Motor Unit Action Potentials: Incomplete transection of facial nerve l Poly-phasic Motor Unit Action Potentials: Re-innervation of facial muscles l Fibrillation potentials: Denervation of muscles (2 -3 weeks after trauma) l Electrical silence: Atrophy / absence of muscle
Bell’s Palsy l Acute onset, idiopathic, unilateral, self-limiting, non-progressive, peripheral facial nerve palsy l 85% start recovering within 3 weeks l Etiology: 1. Viral: Herpes simplex, Herpes Zoster 2. Ischemia of facial nerve: exposure to cold, emotional stress, nerve compression 3. Hereditary 4. Autoimmune

Sir Charles Bell
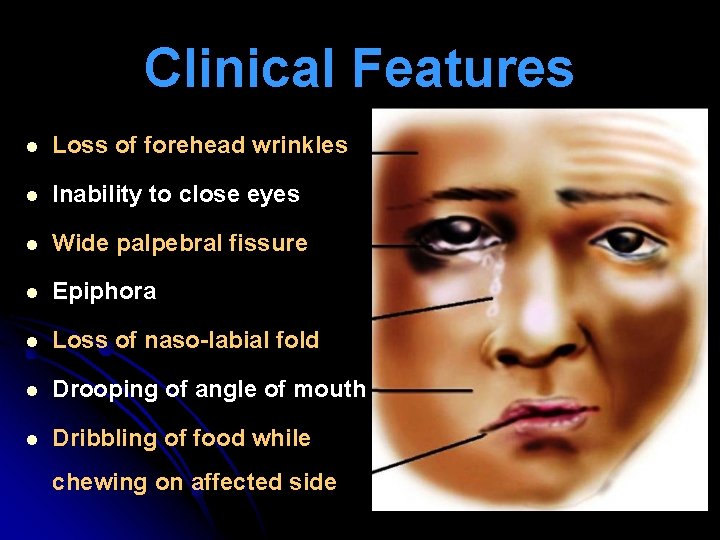
Clinical Features l Loss of forehead wrinkles l Inability to close eyes l Wide palpebral fissure l Epiphora l Loss of naso-labial fold l Drooping of angle of mouth l Dribbling of food while chewing on affected side
Medical treatment l Prednisolone (1 mg/kg in 2 doses): for 2 - 3 weeks l Acyclovir: 200 -400 mg 5 times per day X 7 days l Eye care: Voluntary closure @ 2 / min. Ciplox eye drops 2 hourly & ointment H. S. Eye cover at night. l Physiotherapy: moist heat + facial massage + facial muscle exercise l Electrical stimulation of facial nerve & muscle l Facial nerve decompression: Controversial

Moebius syndrome

Melkersson Rosenthal Syndrome l Recurrent alternating facial palsy l Fissured tongue l Facio-labial edema l Familial history
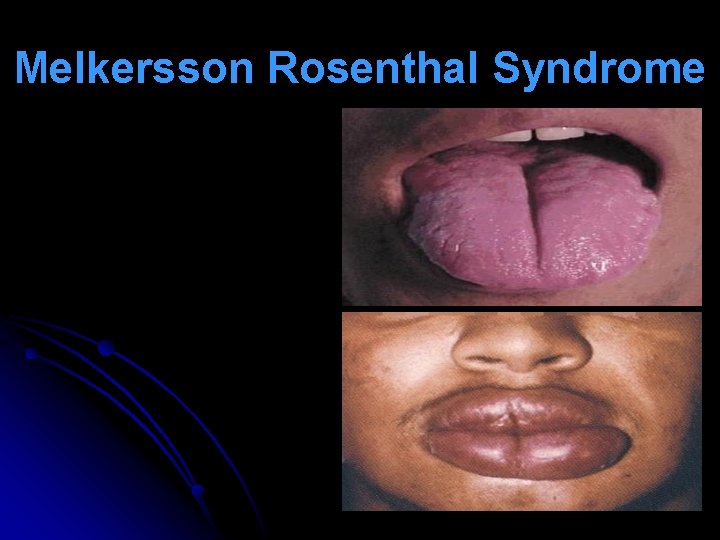
Melkersson Rosenthal Syndrome

Surgical Treatment for Facial Nerve Injury
A. Facial nerve decompression: till meatal foramen B. Neurorrhaphy (Nerve repair) 1. Direct end to end anastomosis 2. Interposition Cable grafting: sural, greater auricular C. Nerve Transposition: hypoglossal-facial D. Muscle Transposition: temporalis, masseter E. Micro-neuro-vascular muscle flaps F. Static Procedures: eyelid implant, fascial sling
Treatment Protocol Up to 3 weeks: Nerve decompression or Nerve repair 3 weeks – 2 year: Nerve Repair or Nerve Transposition > 2 year with fibrillation in Electromyography: Nerve Repair or Nerve Transposition > 2 yr with electrical silence in Electromyography: Muscle transposition / Eyelid implant / Fascial sling
Facial Nerve Decompression l Cortical mastoidectomy done l Facial nerve canal bone thinned in barber pole fashion with diamond burr. Drilling done: l Posteriorly at mastoid segment, Laterally at external genu & Inferiorly at tympanic segment l Avoids injury to chorda tympani & lateral S. C. C. l Labyrinthine segment decompressed by middle cranial fossa approach
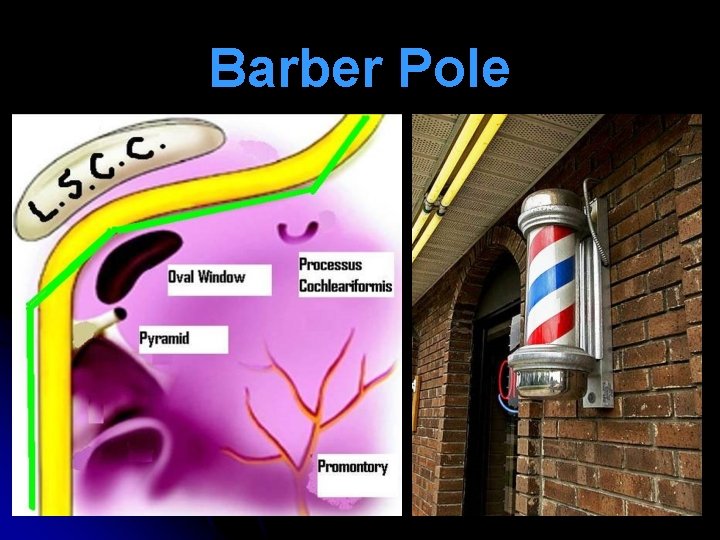
Barber Pole
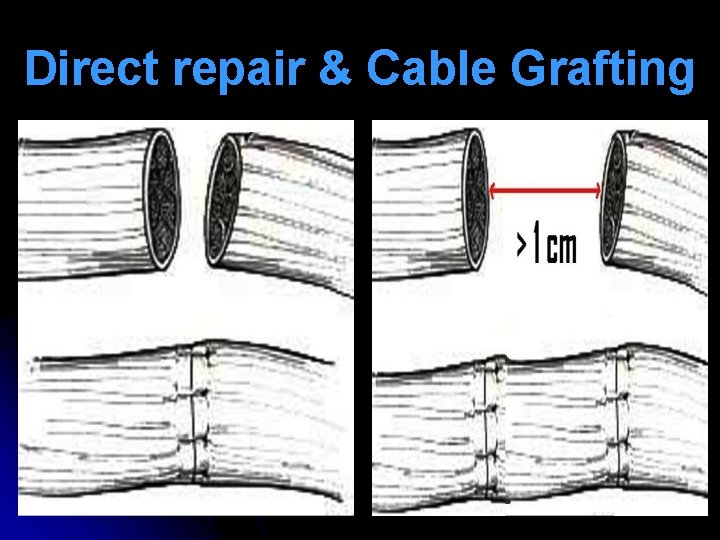
Direct repair & Cable Grafting
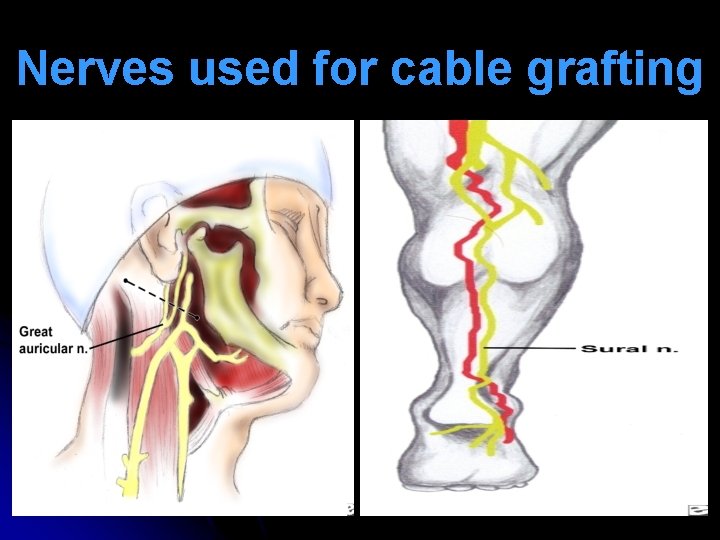
Nerves used for cable grafting
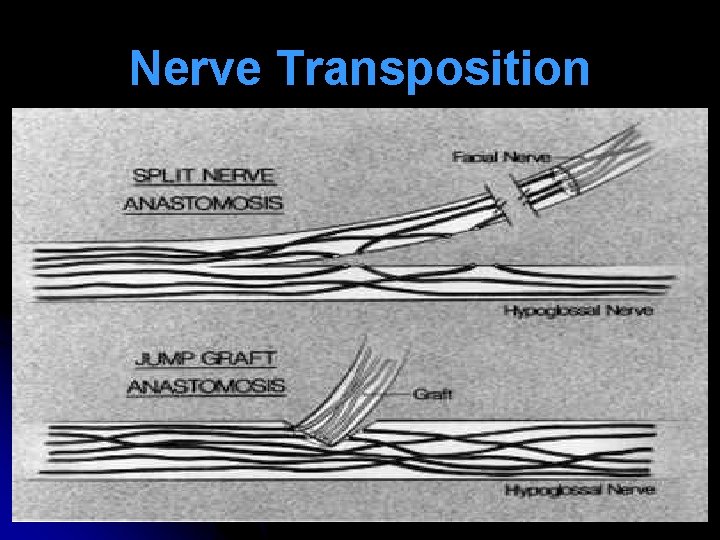
Nerve Transposition
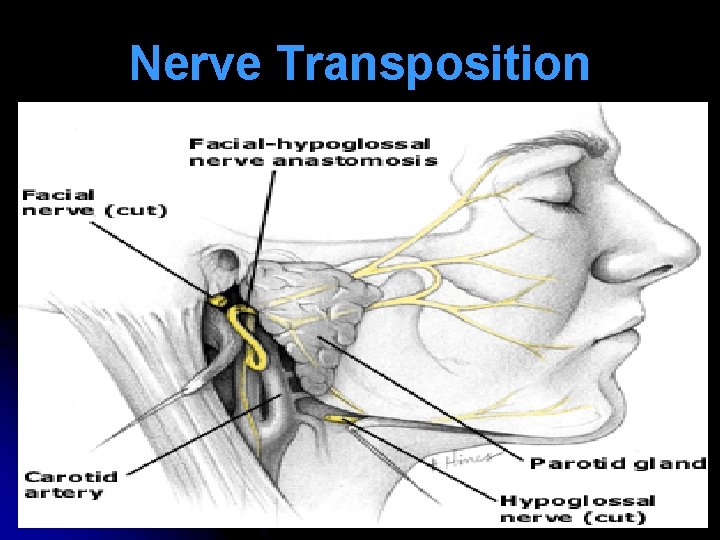
Nerve Transposition
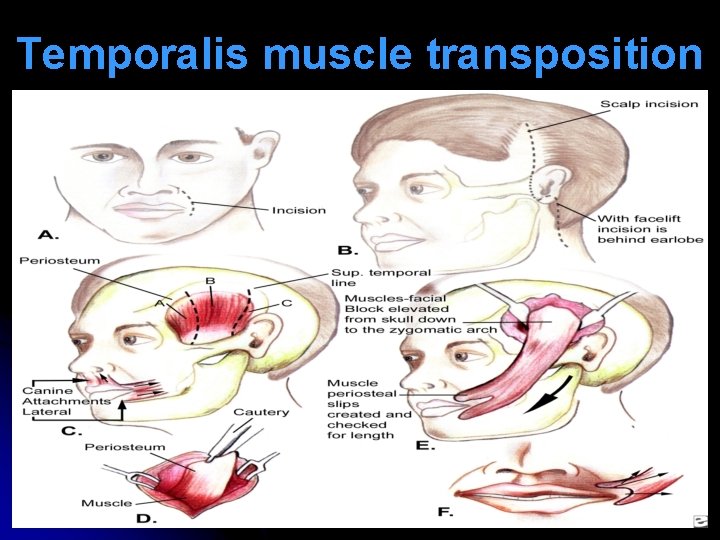
Temporalis muscle transposition
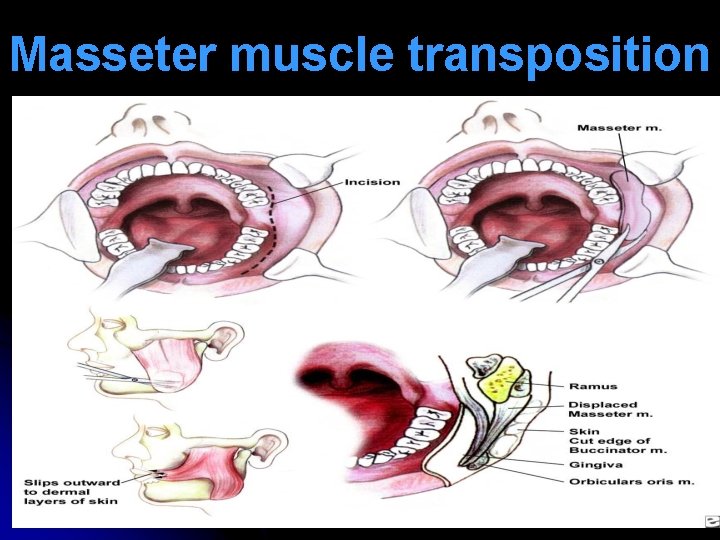
Masseter muscle transposition
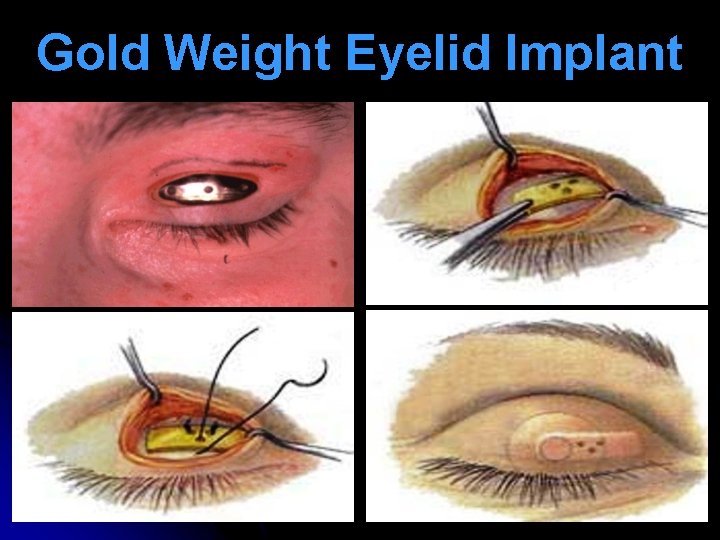
Gold Weight Eyelid Implant
Complications of facial nerve injury 1. Incomplete recovery 2. Exposure keratitis 3. Facial tics & spasms 4. Faulty regeneration of facial nerve a. Synkinesis: Mass movement of facial muscles b. Crocodile tear syndrome: gustatory lacrimation v Salivary to lacrimal gland cross over c. Frey’s syndrome: gustatory sweating v Secreto-motor to sympathetic cross over

Thank You
- Slides: 72