
Entamoebae Amoebae are free living few of them

Entamoebae Ø Amoebae are free living, few of them may act as human pathogens 1. Entamoeba : E. histolytica, E. hartmanni, E. coli, E. gingivalis. 2. Endolimax : E. nana 3. Iodamoeba : I. butschlii 4. Diantamoeba : D. fragilis

Entamoebae histolytica Ø It was discovered in 1875 by Losch in Russia. Ø Commonly seen in tropical countries, common in places where sanitation is poor. Morphology: It is seen in three forms, The trophozoite, precyctic and cystic stages.
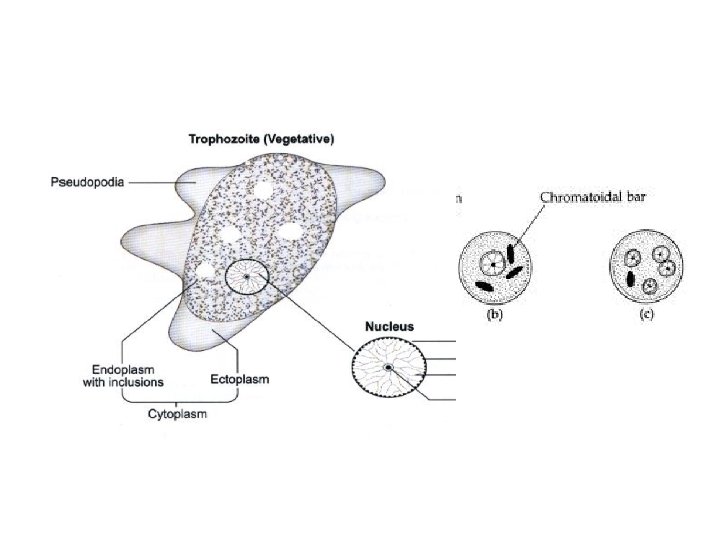
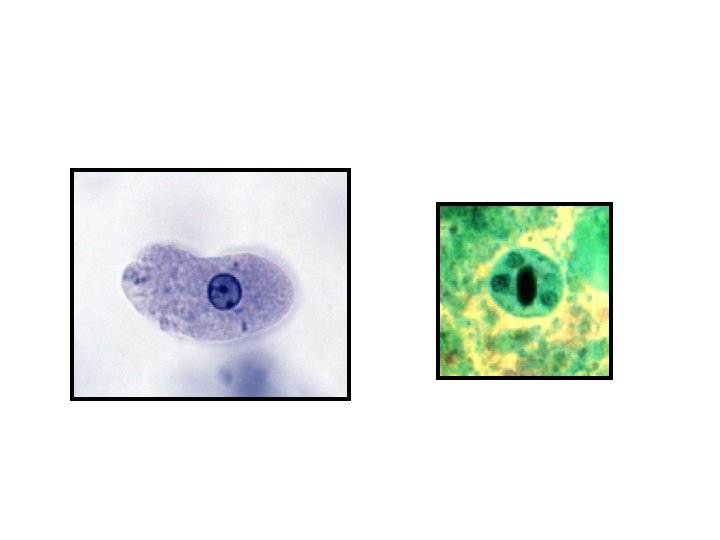
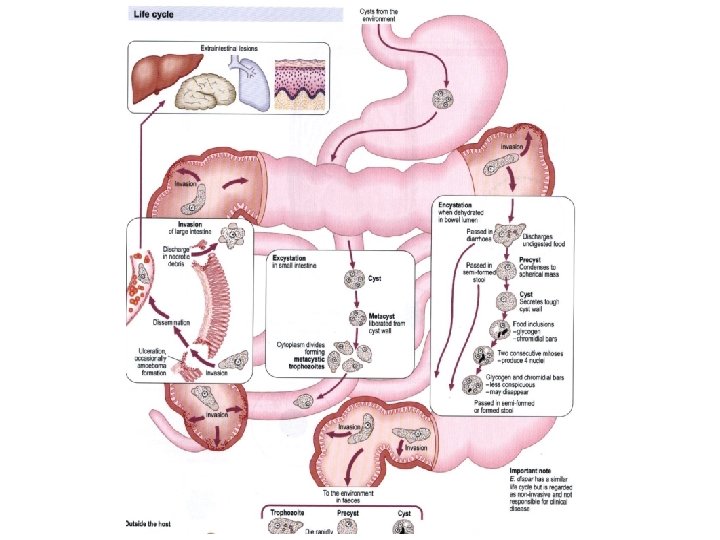
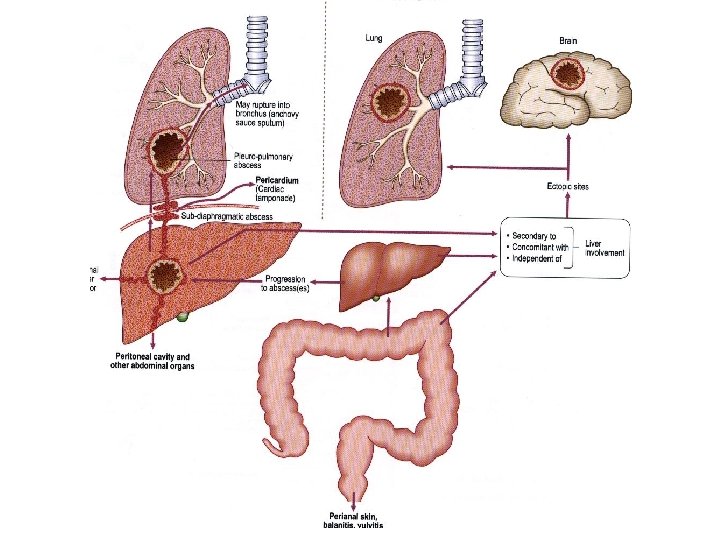
Pathogenicity Pathogenic lesions – two types: – Primary or intestinal lesions – confined to large intestine – Secondary or metastatic lesions (extraintestinal) – due to migration of trophozoites to liver, lungs & brain.
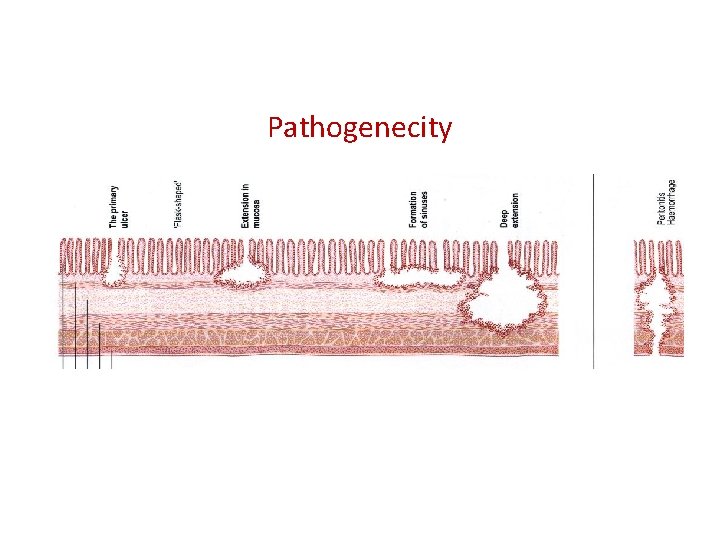
Pathogenecity

Amoebic v/s bacillary dysentery Macroscopic: Frequency Amoebic dysentery Bacillary dysentery 6 to 8 motions per day Over 10 per day Amoun Relatively copious Small Odour Offensive Normal Colour Dark red Bright red Nature Blood & mucus mixed with feces Blood & mucus, no feces Reacti Acid Alkaline In clumps Discrete Scanty Many ts on Microscopic: RBCs Pus cells Eosinop Present - many hils Very few
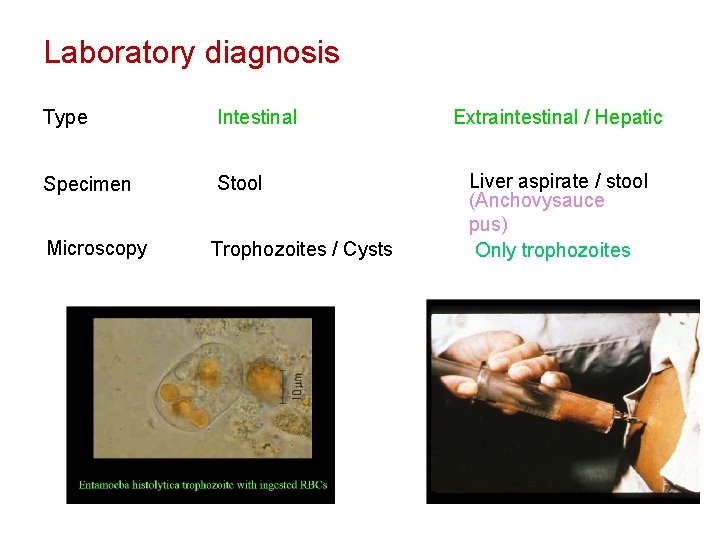
Laboratory diagnosis Type Intestinal Specimen Stool Microscopy Trophozoites / Cysts Extraintestinal / Hepatic Liver aspirate / stool (Anchovysauce pus) Only trophozoites

Treatment & Prevention : • Treatment – – Tissue & luminal - Metronidazole / Tinidazole • Prevention – Personal hygiene. – Prevention of drinking water contamination. – Thorough washing of raw vegetables & fruits.
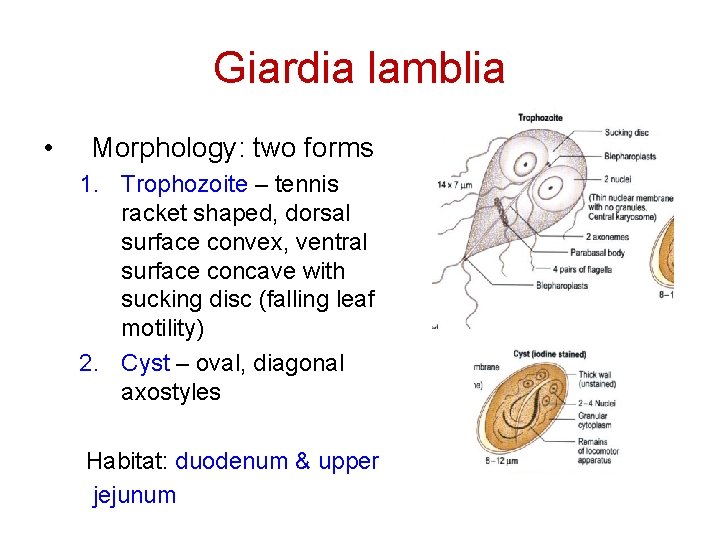
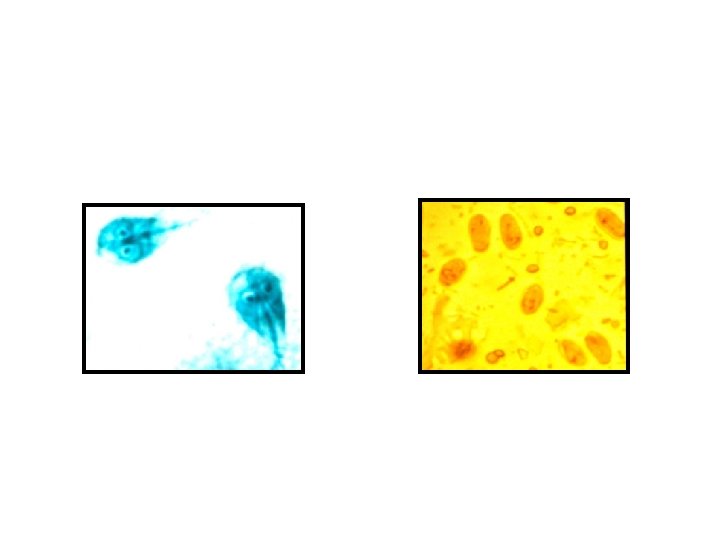
Giardia lamblia • Morphology: two forms 1. Trophozoite – tennis racket shaped, dorsal surface convex, ventral surface concave with sucking disc (falling leaf motility) 2. Cyst – oval, diagonal axostyles Habitat: duodenum & upper jejunum
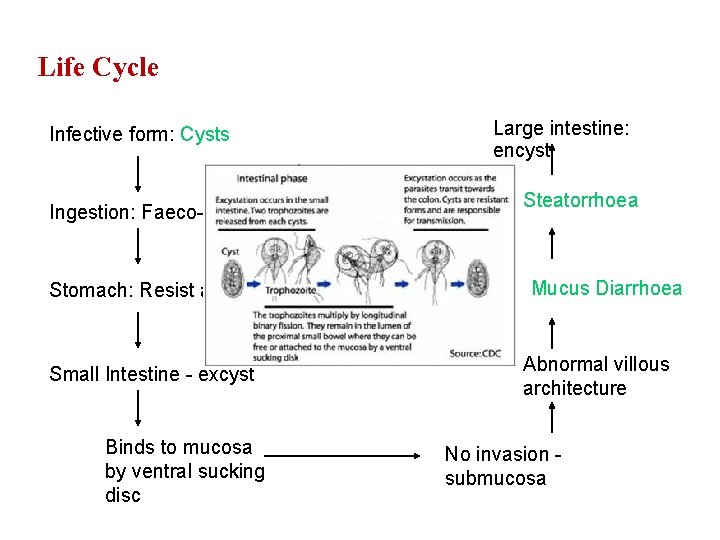
Life Cycle Infective form: Cysts Ingestion: Faeco-oral Stomach: Resist acid Small Intestine - excyst Binds to mucosa by ventral sucking disc Large intestine: encyst Steatorrhoea Mucus Diarrhoea Abnormal villous architecture No invasion submucosa

Laboratory diagnosis - Giardiasis Specime Stool, duodenal ns: aspiration Enterotest : Gelatin capsules Microscop Trophozoites / y: cysts Treatme nt: Preventio n: Metronidazole / Tinidazole Personal hygiene, avoid food & water contamination, drink safe water
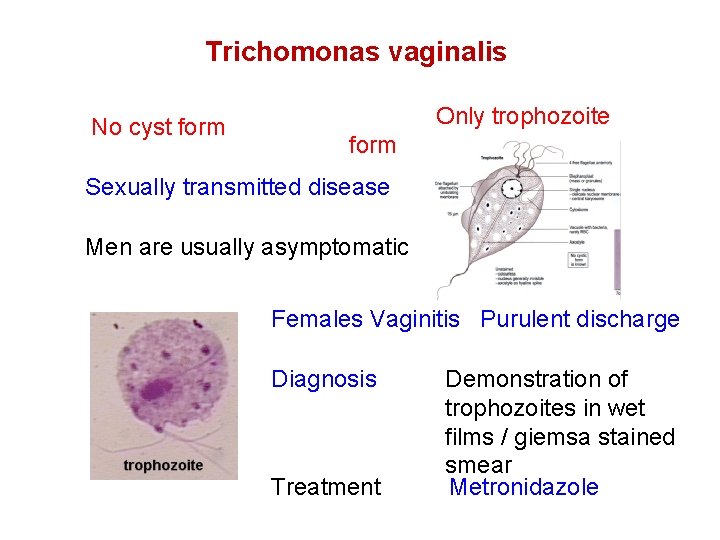
Trichomonas vaginalis No cyst form Only trophozoite form Sexually transmitted disease Men are usually asymptomatic Females Vaginitis Purulent discharge Diagnosis Treatment Demonstration of trophozoites in wet films / giemsa stained smear Metronidazole

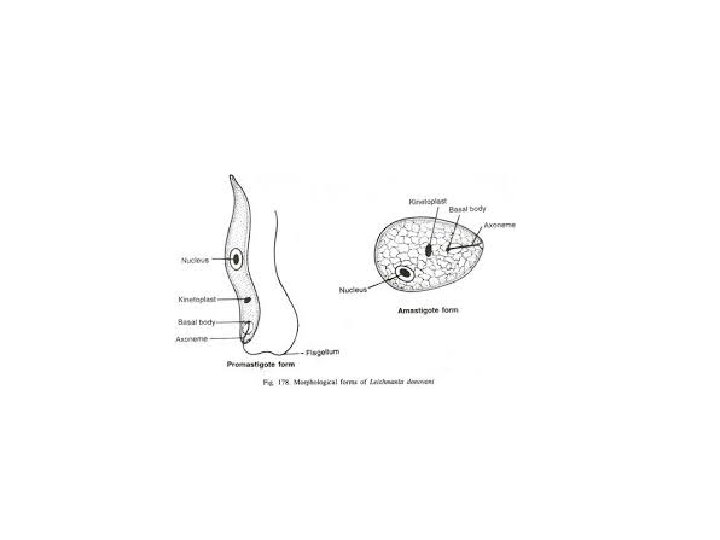
Haemoflagellates • Infecting man belongs to two genera in the family Trypanosomatidae – Trypanosoma Leishmania • Medically important haemoflagellates require two hosts to complete life cycle. Man and insect vector. • Exists in two or more of morphological forms 1. Amastigote form - Round or ovoid without external flagellum. 2. Promastigote form - Lanceolate, Flagellate.

Leishmania • Named after Sir William Leishman who discovered in spleen of a soldier who had died of Dum fever, Calcutta. • Leishmania are obligate intracellular parasites that pass their life cycle in two hosts, the mammalian host and the insect vector female sand fly. Classification : A. Causing Visceral Leishmaniasis (VL) B. Causing cutaneous Leishmaniasis (CL) Leishmania donovani History : Isolated in 1900 from Dum, Calcutta, Donovan also reporter same findings from Madras therefore called as Leishmania donovani.
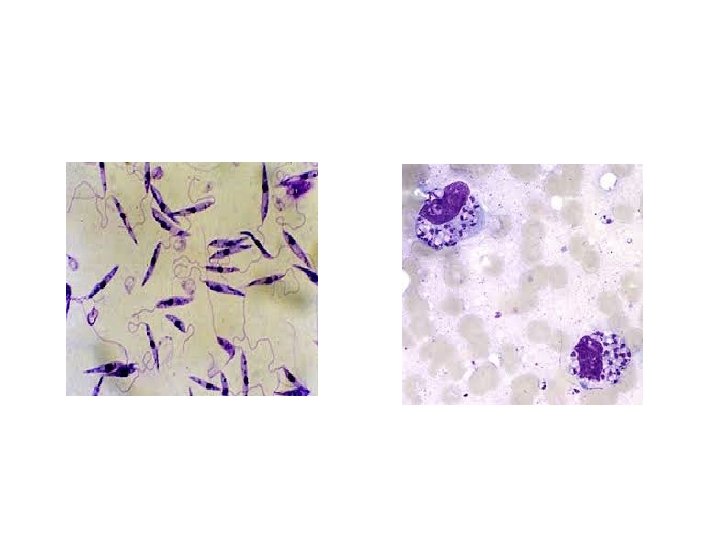
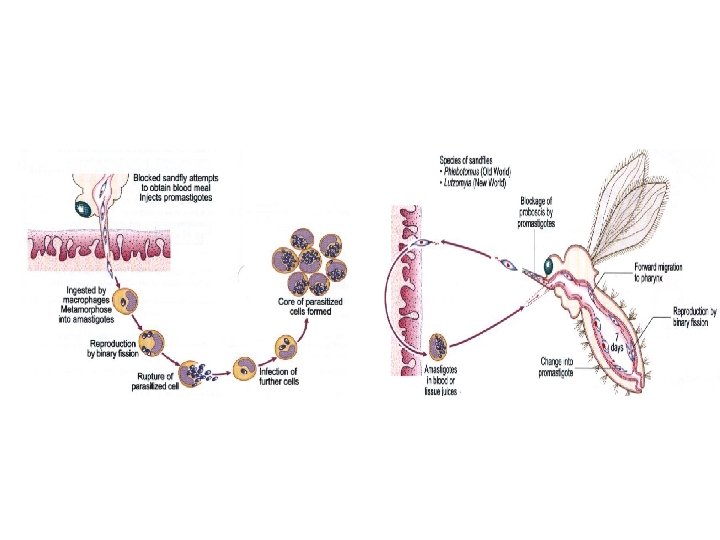

PATHOGENISITY • It causes disease Kala Azar also known as Dum fever or Tropical splenomegaly. • Transmitted mainly by the bite of the sand fly also possible by blood transfusion, sexual, inoculation and congenital. • Most of the cases unapparent or sub clinical and only about 3% develop the typical Kala azar syndrome. • Incubation period is about 2 to 6 months, it may be short as 10 days or as long as 2 years. • Onset is typically insidious. Illness begins with fever which may be remittent or irregular. • Splenomegaly starts early and is progressive and massive. Hepatomegaly and lymphadenopathy not very prominent. • The disease progresses for several months with periods of no fever followed again fever. • Emaciation and anaemia develops. Skin becomes dry, rough and hair becomes thin and brittle. • Most untreated will die in about 2 years due to dysentery or Tuberculosis.

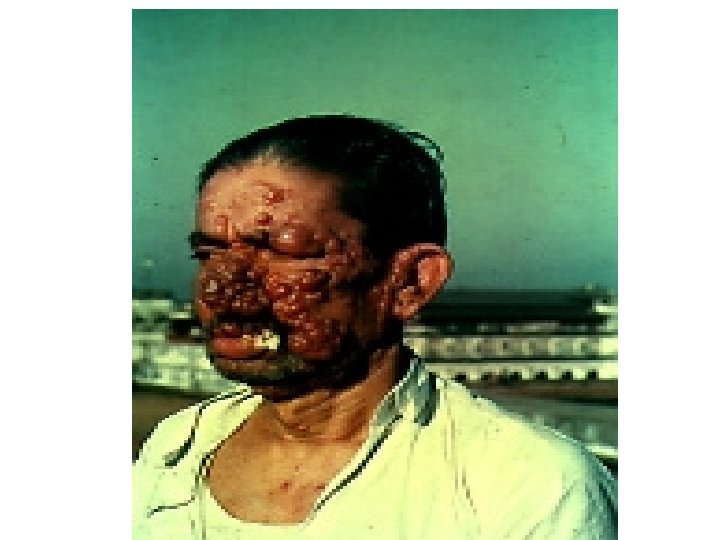
POST KALA AZAR DERMAL LEISHMANIASIS ( PKDL ) • • 10 to 20 % of the patients recovered from Kala azar develop PKDL. The PKDL lesion develops about a year of two after recovery from the systemic illness. Seen mainly in India. There are three types 1. Depigmented macules. 2. Erythematous patches ( Butterfly patches on face ) 3. Granulamatous nodules.

LABORATORY DIAGNOSIS 1. Demonstration of parasite : A. Microscopy : From. I. Peripheral blood. II. Bone marrow. III. Slpenic aspiration. ( If BM examination is inconclusive. ) B. Culture : Can be cultured on Novy-Mc. Neal-Nicolle media.

2. Serology : Demonstration of specific antibodies. 3. Skin test (Montenegro test) : It is a delayed hypersensitivity test done by using killed promastigote antigen. It is positive in PKDL.

Treatment : 1. Sodium stibogluconate. 2. Aminosidine 3. Pentamidine. Prevention : Treat all cases, eradication of vector. Personal measures.

Thank you
- Slides: 28