
Does Less Lung More Heart Nathaniel Marchetti DO






- Slides: 44
Does Less Lung = More Heart? Nathaniel Marchetti, DO Temple University Philadelphia, PA
Cardiac Effects of COPD n Why do we care about the heart in COPD? n What does hyperinflation do to the heart? n Effect of LVRS on cardiac function
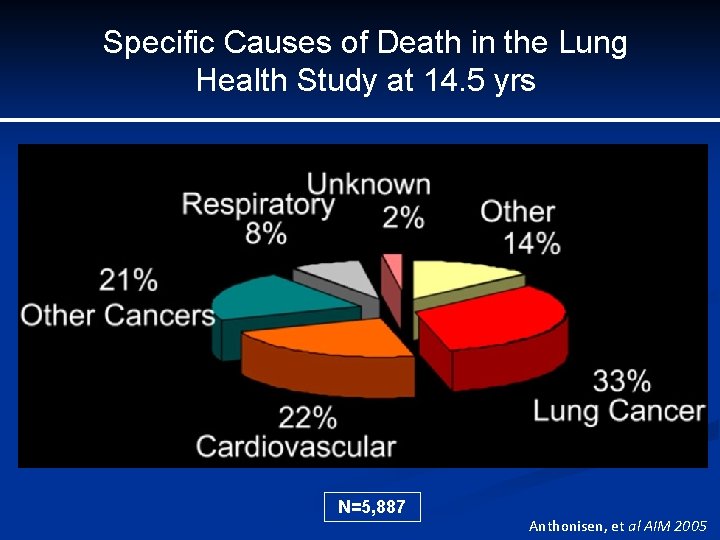
Specific Causes of Death in the Lung Health Study at 14. 5 yrs N=5, 887 Anthonisen, et al AIM 2005
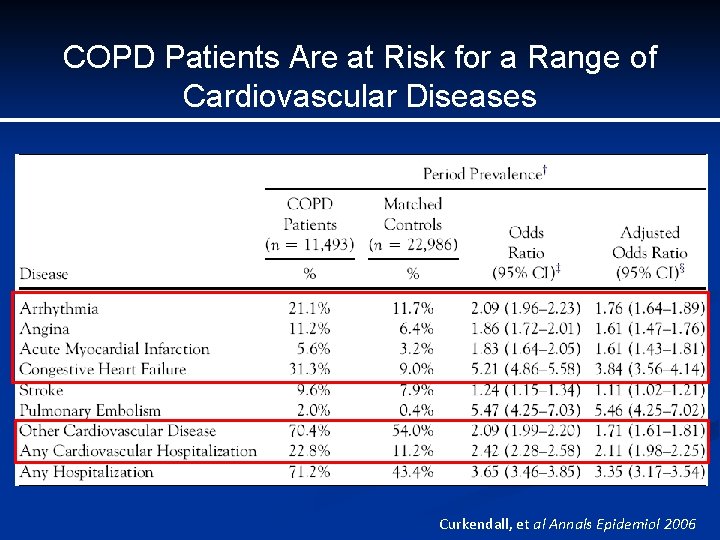
COPD Patients Are at Risk for a Range of Cardiovascular Diseases Curkendall, et al Annals Epidemiol 2006
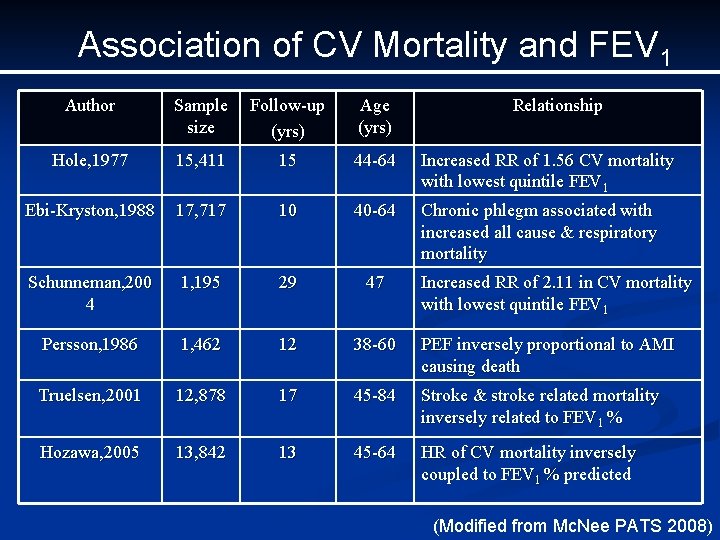
Association of CV Mortality and FEV 1 Author Sample size Follow-up (yrs) Age (yrs) Relationship Hole, 1977 15, 411 15 44 -64 Increased RR of 1. 56 CV mortality with lowest quintile FEV 1 Ebi-Kryston, 1988 17, 717 10 40 -64 Chronic phlegm associated with increased all cause & respiratory mortality Schunneman, 200 4 1, 195 29 47 Persson, 1986 1, 462 12 38 -60 PEF inversely proportional to AMI causing death Truelsen, 2001 12, 878 17 45 -84 Stroke & stroke related mortality inversely related to FEV 1 % Hozawa, 2005 13, 842 13 45 -64 HR of CV mortality inversely coupled to FEV 1 % predicted Increased RR of 2. 11 in CV mortality with lowest quintile FEV 1 (Modified from Mc. Nee PATS 2008)
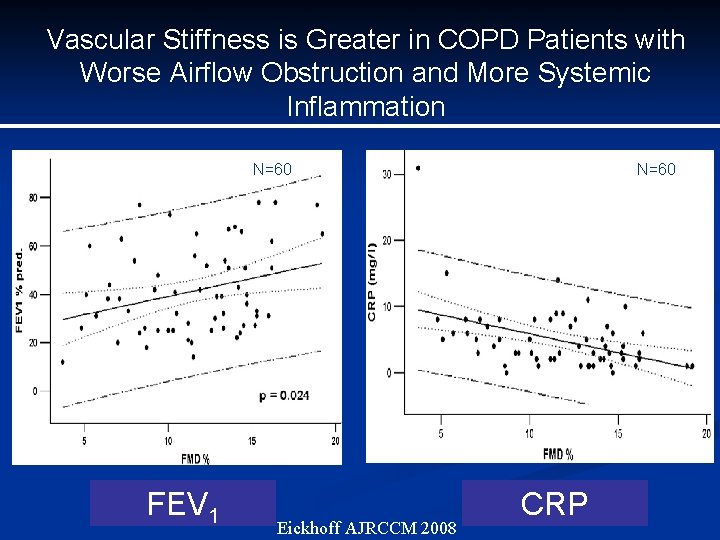
Vascular Stiffness is Greater in COPD Patients with Worse Airflow Obstruction and More Systemic Inflammation N=60 FEV 1 Eickhoff AJRCCM 2008 N=60 CRP
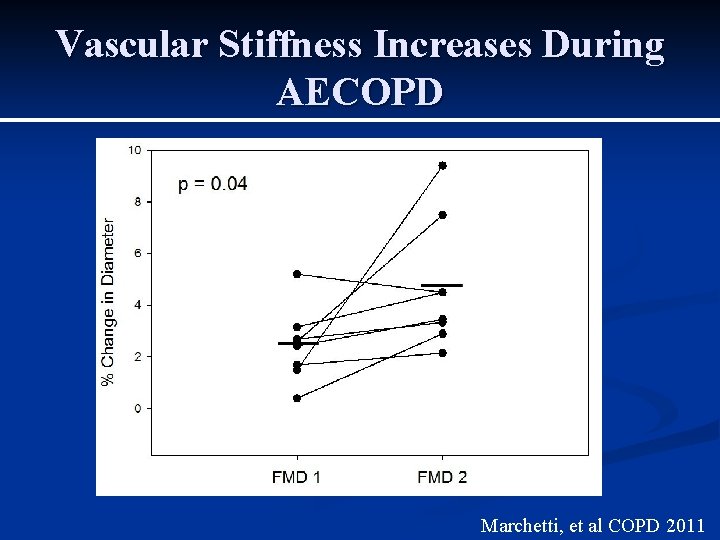
Vascular Stiffness Increases During AECOPD Marchetti, et al COPD 2011
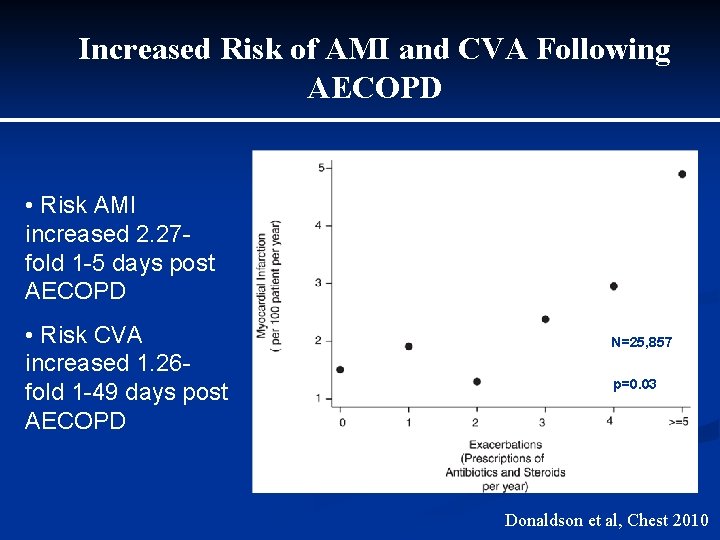
Increased Risk of AMI and CVA Following AECOPD • Risk AMI increased 2. 27 fold 1 -5 days post AECOPD • Risk CVA increased 1. 26 fold 1 -49 days post AECOPD N=25, 857 p=0. 03 Donaldson et al, Chest 2010
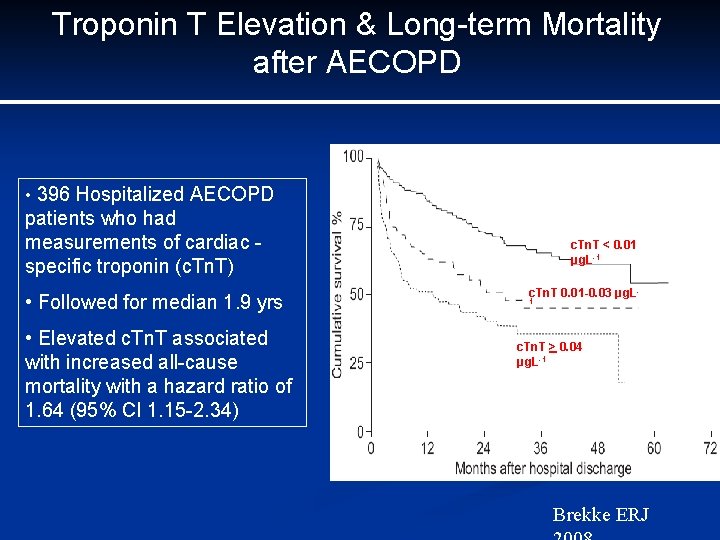
Troponin T Elevation & Long-term Mortality after AECOPD • 396 Hospitalized AECOPD patients who had measurements of cardiac specific troponin (c. Tn. T) • Followed for median 1. 9 yrs • Elevated c. Tn. T associated with increased all-cause mortality with a hazard ratio of 1. 64 (95% CI 1. 15 -2. 34) c. Tn. T < 0. 01 μg. L-1 c. Tn. T 0. 01 -0. 03 μg. L 1 c. Tn. T > 0. 04 μg. L-1 Brekke ERJ
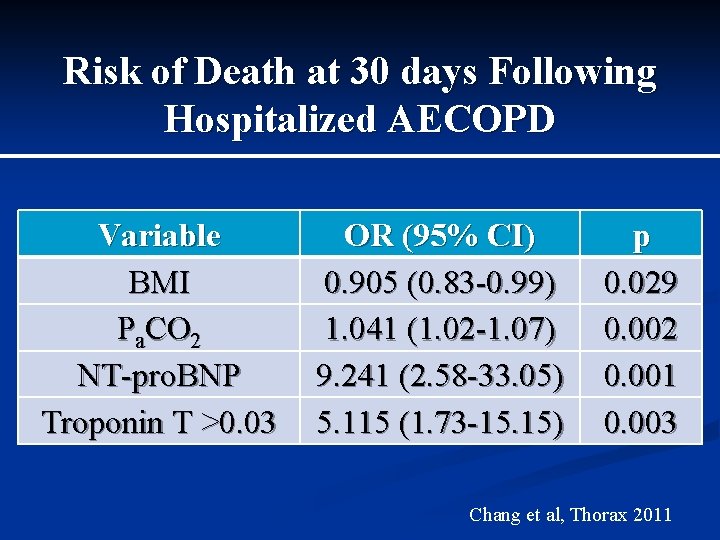
Risk of Death at 30 days Following Hospitalized AECOPD Variable BMI Pa. CO 2 NT-pro. BNP Troponin T >0. 03 OR (95% CI) 0. 905 (0. 83 -0. 99) 1. 041 (1. 02 -1. 07) 9. 241 (2. 58 -33. 05) 5. 115 (1. 73 -15. 15) p 0. 029 0. 002 0. 001 0. 003 Chang et al, Thorax 2011
Effect of Hyperinflation on the Heart
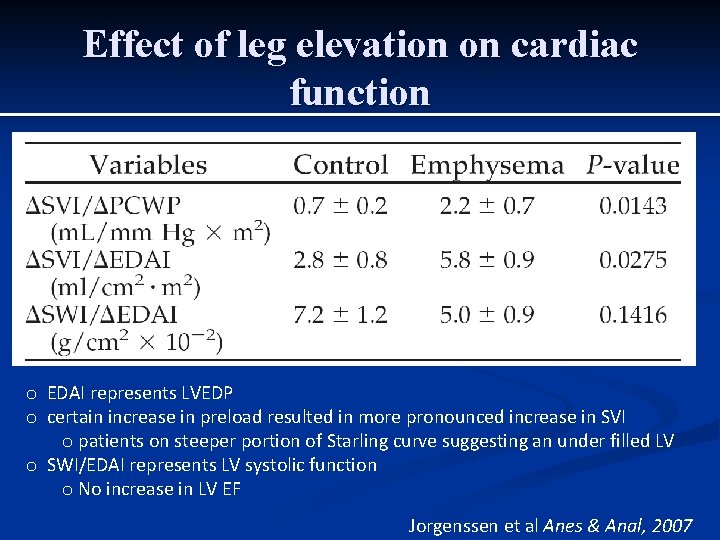
Effect of leg elevation on cardiac function o EDAI represents LVEDP o certain increase in preload resulted in more pronounced increase in SVI o patients on steeper portion of Starling curve suggesting an under filled LV o SWI/EDAI represents LV systolic function o No increase in LV EF Jorgenssen et al Anes & Anal, 2007
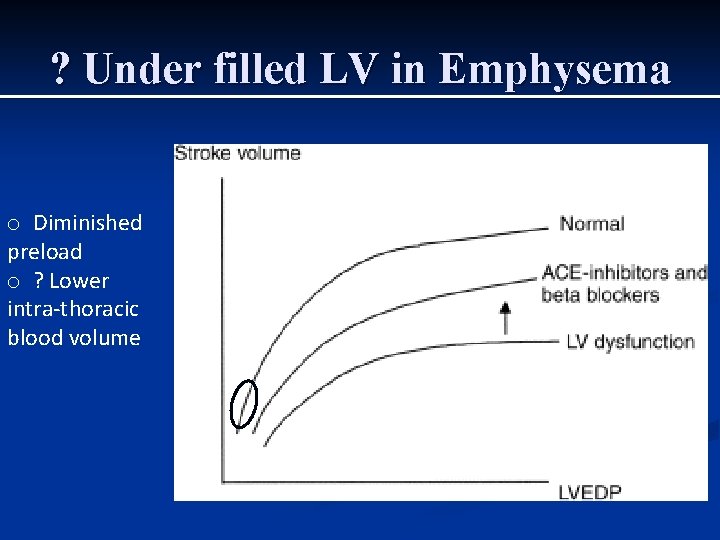
? Under filled LV in Emphysema o Diminished preload o ? Lower intra-thoracic blood volume
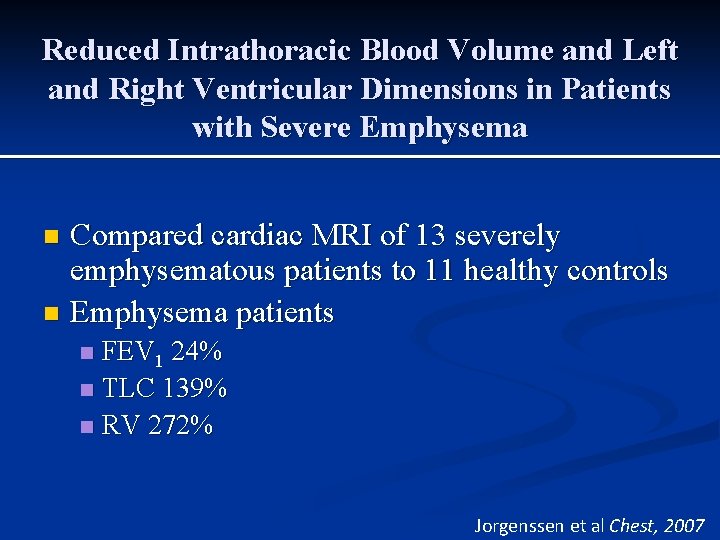
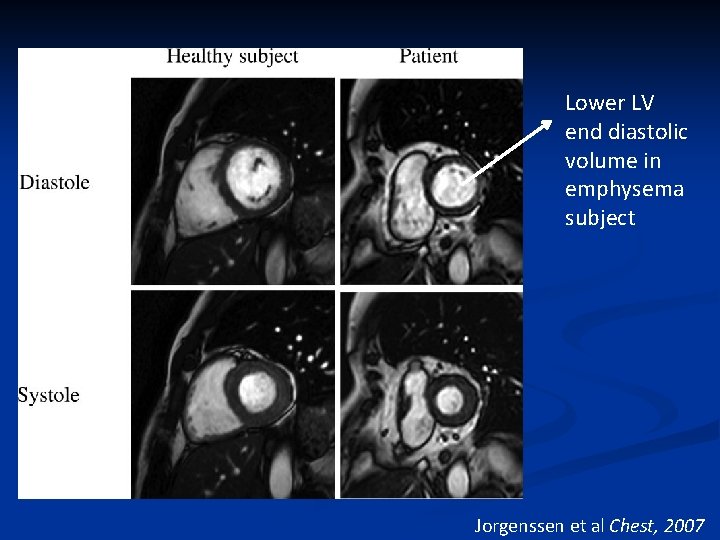
Reduced Intrathoracic Blood Volume and Left and Right Ventricular Dimensions in Patients with Severe Emphysema Compared cardiac MRI of 13 severely emphysematous patients to 11 healthy controls n Emphysema patients n FEV 1 24% n TLC 139% n RV 272% n Jorgenssen et al Chest, 2007
Lower LV end diastolic volume in emphysema subject Jorgenssen et al Chest, 2007
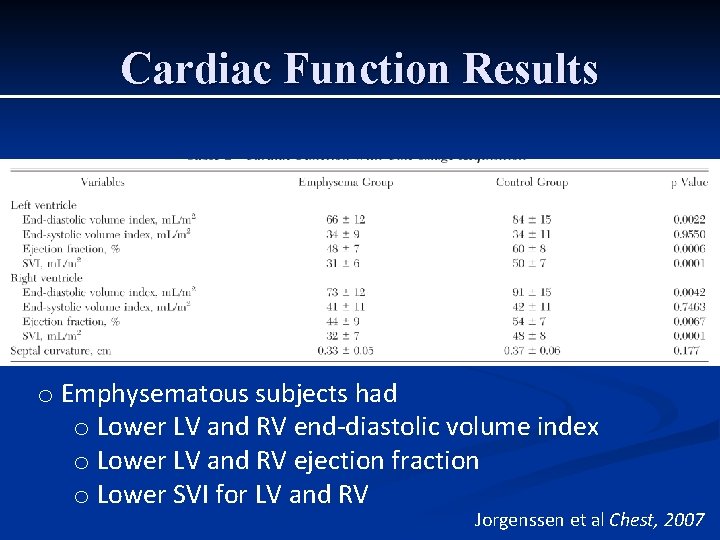
Cardiac Function Results o Emphysematous subjects had o Lower LV and RV end-diastolic volume index o Lower LV and RV ejection fraction o Lower SVI for LV and RV Jorgenssen et al Chest, 2007
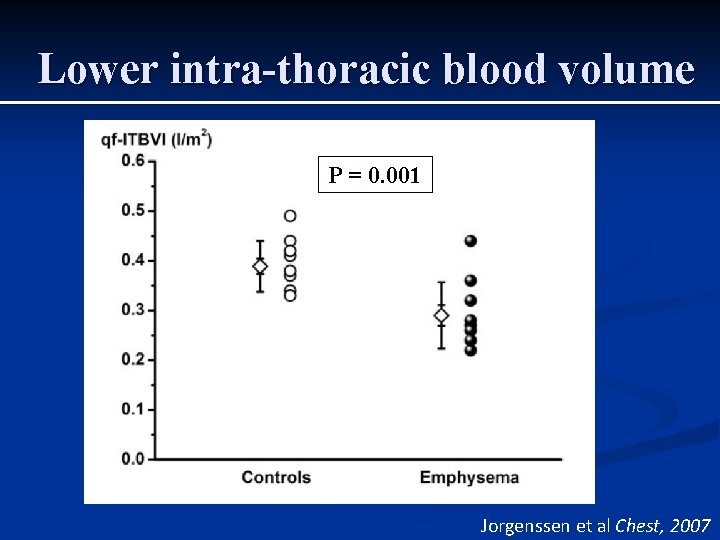
Lower intra-thoracic blood volume P = 0. 001 p = 0. 001 Jorgenssen et al Chest, 2007
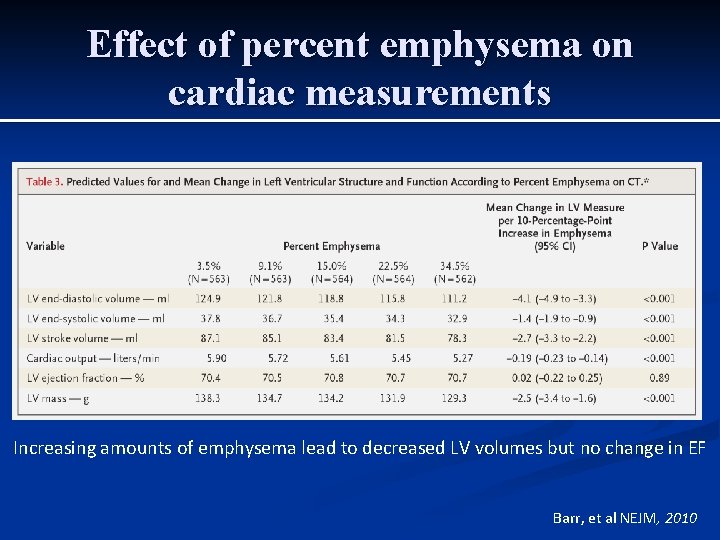
Percent Emphysema, Airflow Obstruction, and Impaired Left Ventricular Filling Sub study of Multi-Ethnic Study of Atherosclerosis (MESA) n Measured LV structure and function with MRI in 2, 816 patients n Measured extent of emphysema on CT (HU < -910) n n n Included 70% of lung since they were cardiac CTs Spirometry Barr, et al NEJM, 2010
Effect of percent emphysema on cardiac measurements Increasing amounts of emphysema lead to decreased LV volumes but no change in EF Barr, et al NEJM, 2010
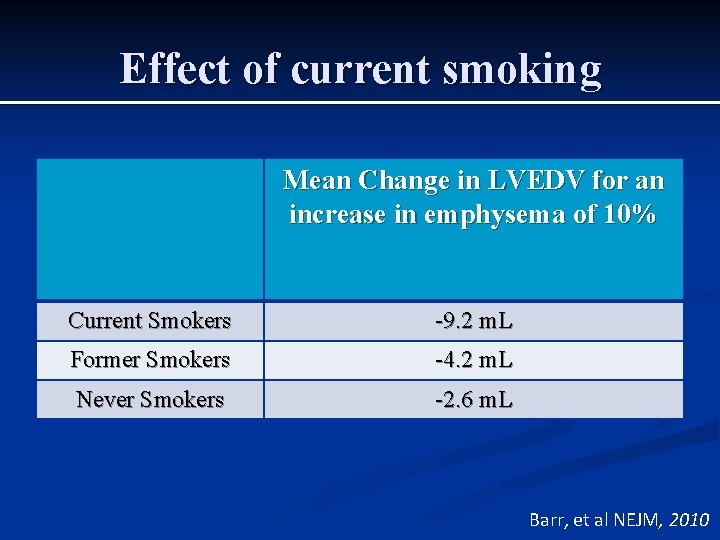
Effect of current smoking Mean Change in LVEDV for an increase in emphysema of 10% Current Smokers -9. 2 m. L Former Smokers -4. 2 m. L Never Smokers -2. 6 m. L Barr, et al NEJM, 2010
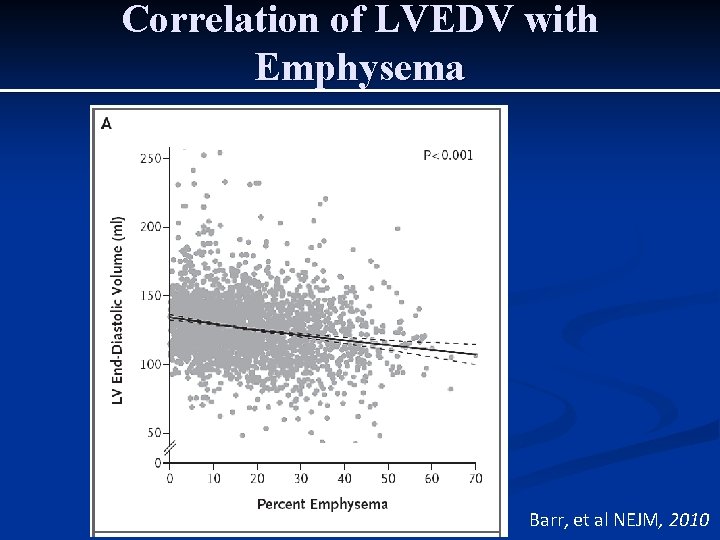
Correlation of LVEDV with Emphysema Barr, et al NEJM, 2010
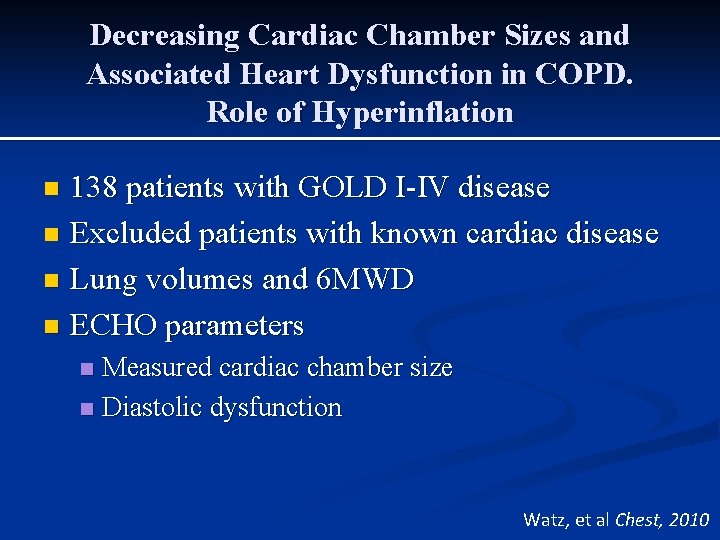
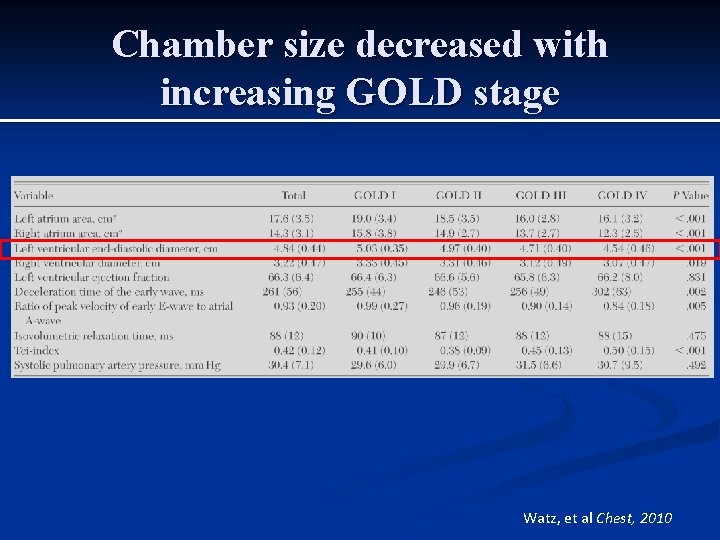
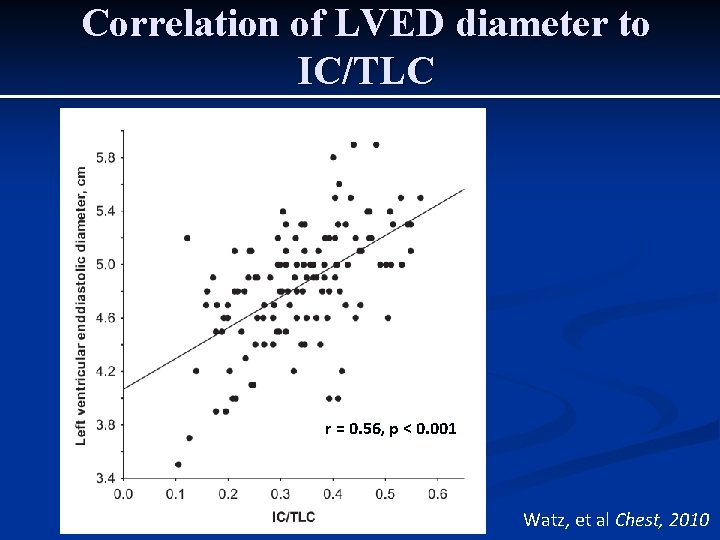
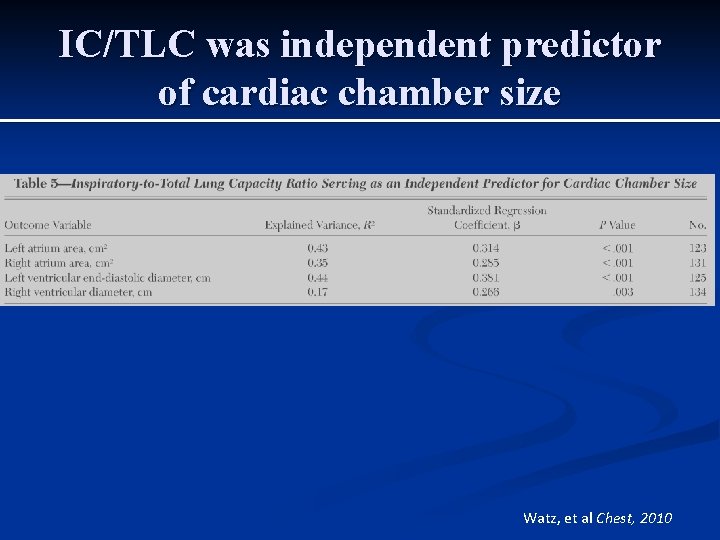
Decreasing Cardiac Chamber Sizes and Associated Heart Dysfunction in COPD. Role of Hyperinflation 138 patients with GOLD I-IV disease n Excluded patients with known cardiac disease n Lung volumes and 6 MWD n ECHO parameters n Measured cardiac chamber size n Diastolic dysfunction n Watz, et al Chest, 2010
Chamber size decreased with increasing GOLD stage Watz, et al Chest, 2010
Correlation of LVED diameter to IC/TLC r = 0. 56, p < 0. 001 Watz, et al Chest, 2010
IC/TLC was independent predictor of cardiac chamber size Watz, et al Chest, 2010
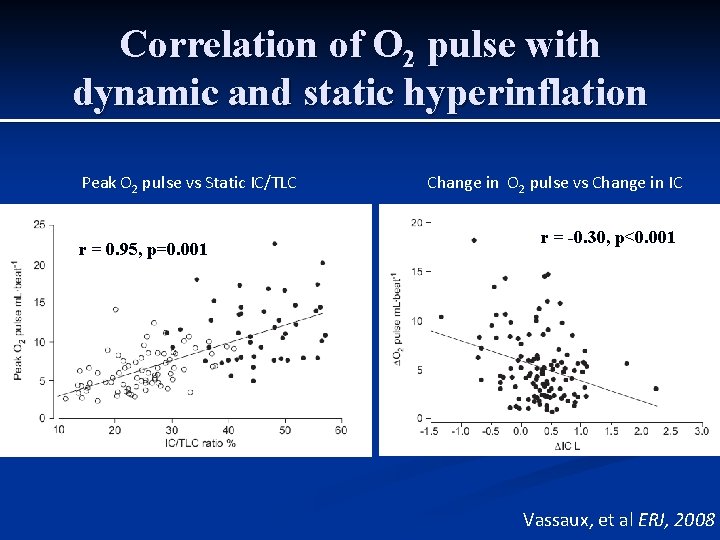
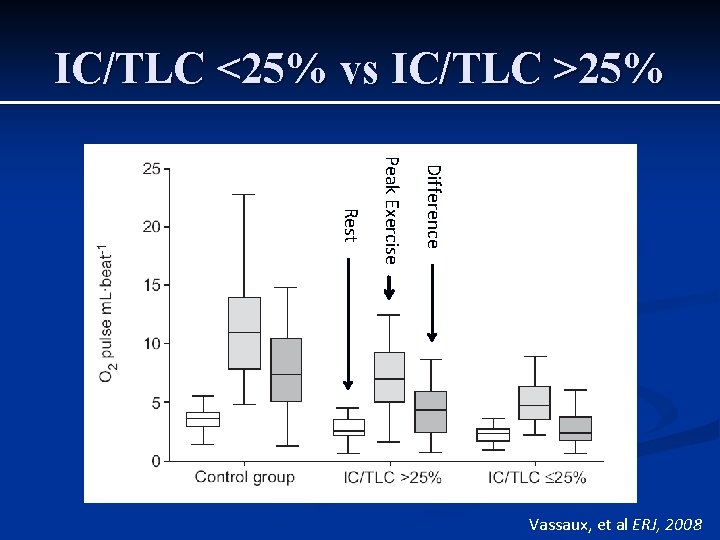
Effects of hyperinflation on the oxygen pulse as a marker of cardiac performance in COPD 87 COPD patients compared to 46 healthy controls n CPET n Measured O 2 pulse (VO 2/HR) n Dynamic hyperinflation (IC/TLC) n Vassaux, et al ERJ, 2008
Correlation of O 2 pulse with dynamic and static hyperinflation Peak O 2 pulse vs Static IC/TLC r = 0. 95, p=0. 001 Change in O 2 pulse vs Change in IC r = -0. 30, p<0. 001 Vassaux, et al ERJ, 2008
IC/TLC <25% vs IC/TLC >25% Difference Peak Exercise Rest Vassaux, et al ERJ, 2008
Summary Patients with COPD seem to have diminished cardiac chamber size n Have decreased intra-thoracic blood volume with under filled LV n Appears to be related to hyperinflation n Occurs across GOLD stages n Can this be altered? n
Effect of LVRS on Cardiac Function
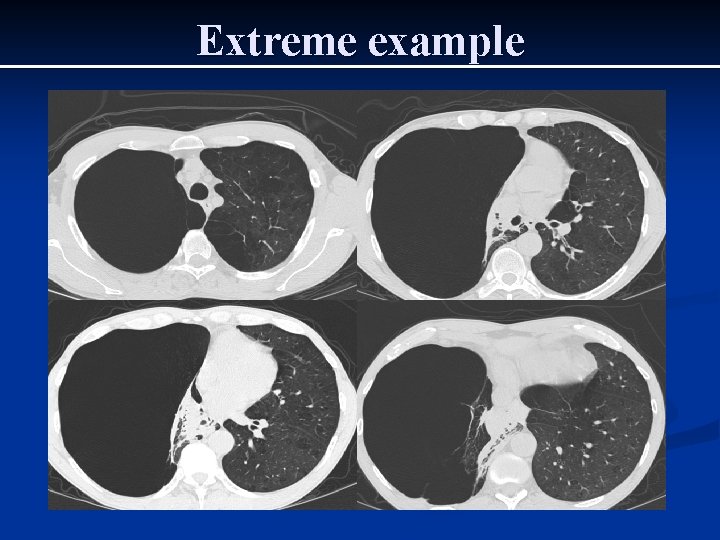
Extreme example
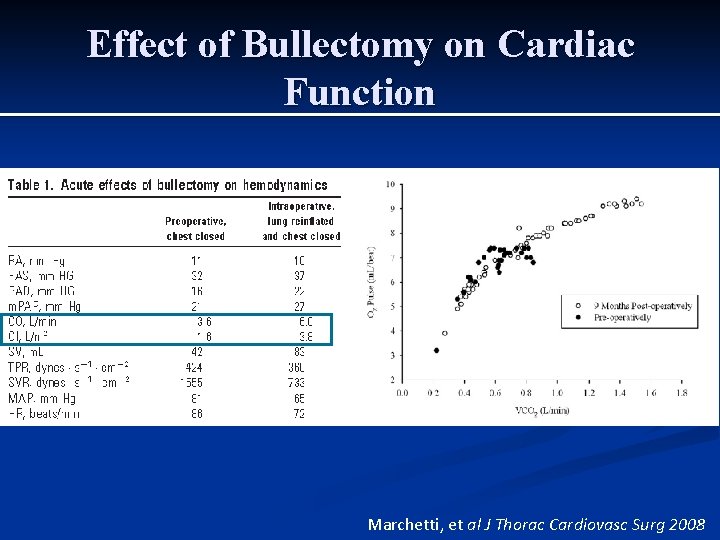
Effect of Bullectomy on Cardiac Function Marchetti, et al J Thorac Cardiovasc Surg 2008
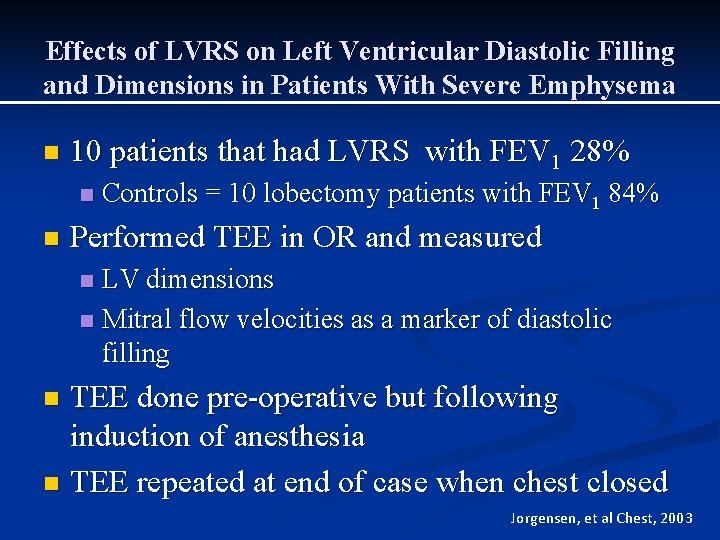
Effects of LVRS on Left Ventricular Diastolic Filling and Dimensions in Patients With Severe Emphysema n 10 patients that had LVRS with FEV 1 28% n n Controls = 10 lobectomy patients with FEV 1 84% Performed TEE in OR and measured LV dimensions n Mitral flow velocities as a marker of diastolic filling n TEE done pre-operative but following induction of anesthesia n TEE repeated at end of case when chest closed n Jorgensen, et al Chest, 2003
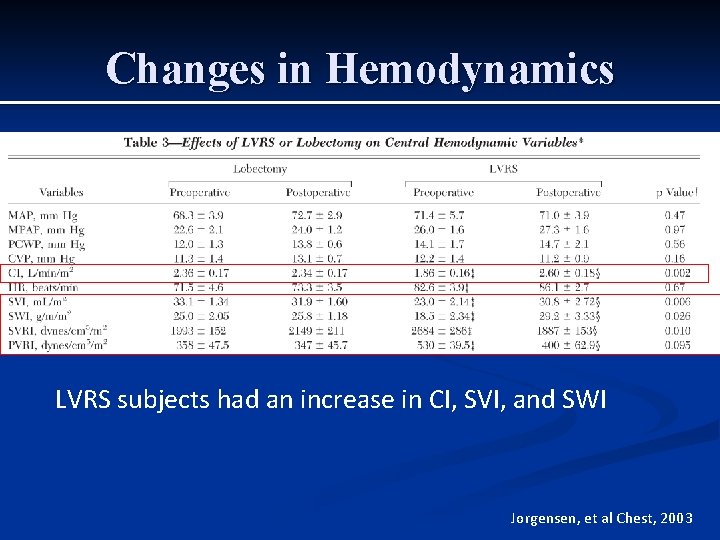
Changes in Hemodynamics LVRS subjects had an increase in CI, SVI, and SWI Jorgensen, et al Chest, 2003
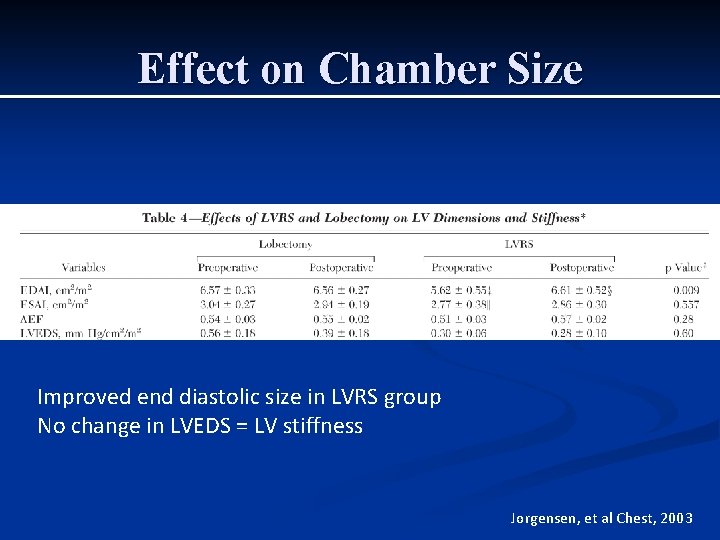
Effect on Chamber Size Improved end diastolic size in LVRS group No change in LVEDS = LV stiffness Jorgensen, et al Chest, 2003
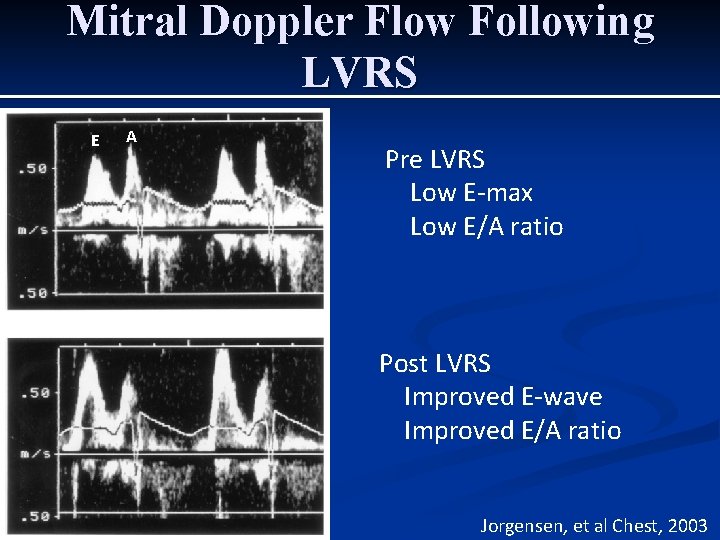
Mitral Doppler Flow Following LVRS E A Pre LVRS Low E-max Low E/A ratio Post LVRS Improved E-wave Improved E/A ratio Jorgensen, et al Chest, 2003
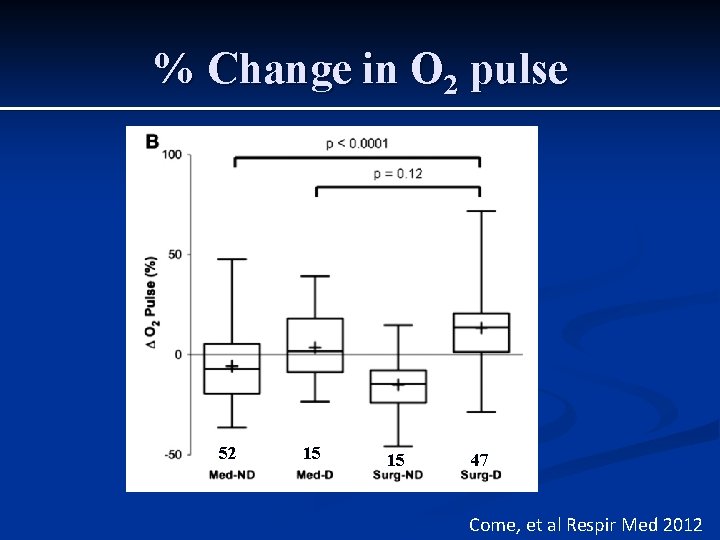
Lung Deflation and Oxygen Pulse in COPD: Results from the NETT Randomized Trial n 129 NETT patients that had CPET and arterial blood gas during exercise n n n Divided group in to “deflators” and “nondeflators” n n 67 medical 62 LVRS Deflators defined as the change in RV/TLC by 75% of subjects Main outcome was % change in peak O 2 pulse from baseline to 6 months Come, et al Respir Med 2012
% Change in O 2 pulse 52 15 15 47 Come, et al Respir Med 2012
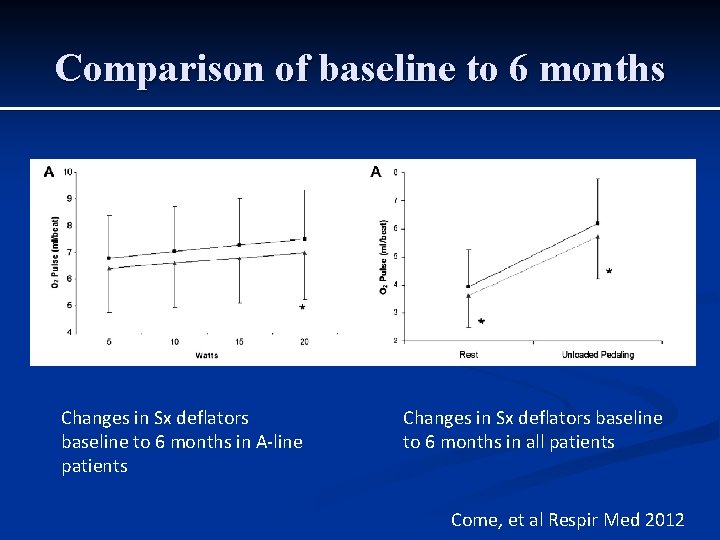
Comparison of baseline to 6 months Changes in Sx deflators baseline to 6 months in A-line patients Changes in Sx deflators baseline to 6 months in all patients Come, et al Respir Med 2012
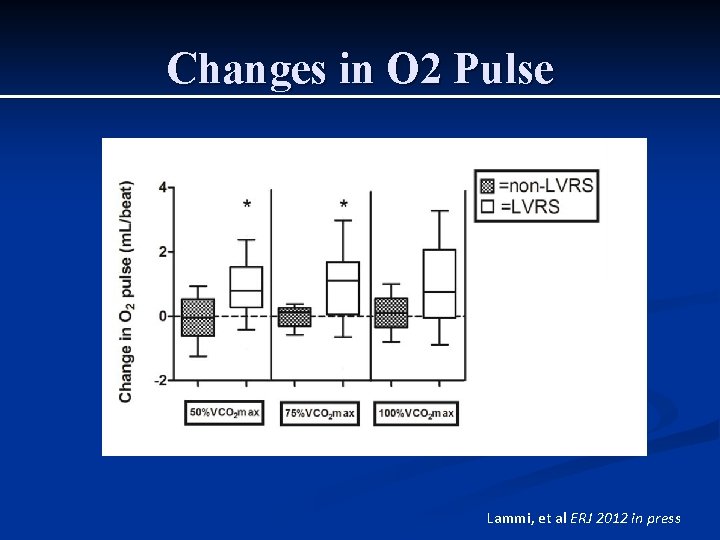
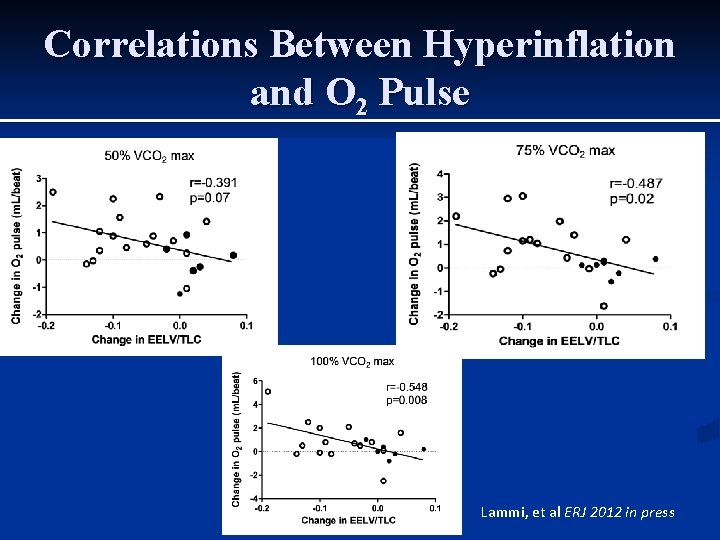
Increased oxygen pulse after LVRS is associated with reduced dynamic hyperinflation 16 patients that had LVRS compared to 6 patients with medical therapy n CPET done baseline and 6 months n O 2 pulse and pulse pressure were outcomes n Lammi, et al ERJ 2012 in press
Changes in O 2 Pulse Lammi, et al ERJ 2012 in press
Correlations Between Hyperinflation and O 2 Pulse Lammi, etetalal. ERJ 2012 ininpress
Conclusions • LVRS improved non-invasive markers of stroke volume • Increase in O 2 pulse after LVRS correlated with reductions in static and dynamic hyperinflation • Strategies to reduce DH might improve exercise performance in part by ameliorating exerciseinduced cardiac dysfunction Lammi, et al ERJ 2012 in press
Summary n COPD can impair LV function and it is related to hyperinflation Leads to low end-diastolic pressures n Decreased intra-thoracic blood volumes n Small cardiac chamber size n n Reducing lung volumes theoretically will help with improving LV function