
Do we need triple therapy for everyone for




- Slides: 21
Do we need triple therapy for everyone. . for life ? Treatment Initiation: What to Expect from Dual or Mono-therapy ? Pr Christine Katlama Sorbonne Université Paris VI Pitié-Salpêtriere Hospital, Paris
#IAS 2017 | @IAS_conference Disclosure § Pr C Katlama has served as a speaker and scientific board consultant for MSD , Janssen , Vii. V , BMS § Research grant : Janssen
Reasons for individualizing ART Using mono/dual strategies Context § Earlier ART initiation Pitié Salpétriere 2016 57% start ART with > 350 CD 4 and 41% with VL< 30 000 cp/m. L § Recent / New drugs more potent and robust § Decades of suppressive ART needed with prolonged drug exposure § Preserve drug options Challenges § Maintain long life viral suppression § Keep ART simple § Minimize toxicity § Avoid drug-drug interactions § Maintain non infectious status § Optimize ART Cost
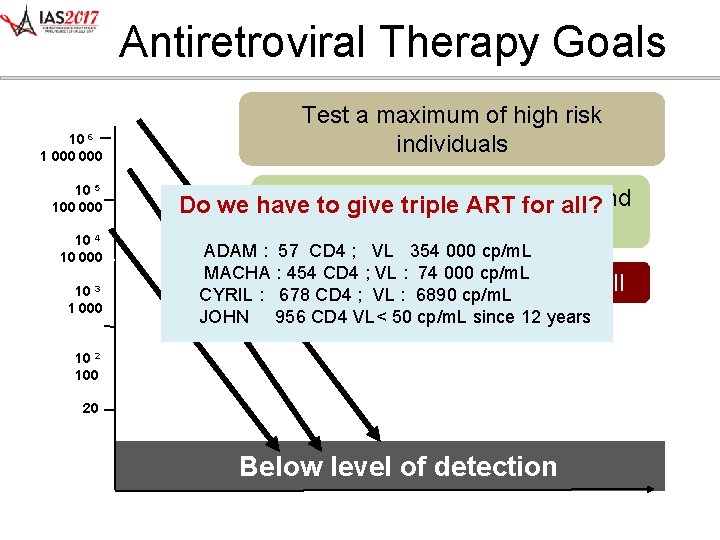
Antiretroviral Therapy Goals 10 6 1 000 10 5 100 000 10 4 10 000 10 3 1 000 10 2 100 Test a maximum of high risk individuals Do we have to give triple ART for all? Treat all HIV infected patients and maintain in care ADAM : 57 CD 4 ; VL 354 000 cp/m. L MACHA : 454 CD 4 ; VL : 74 000 cp/m. L Maximal Viral suppression for all CYRIL : 678 CD 4 ; VL : 6890 cp/m. L JOHN 956 CD 4 VL< 50 cp/m. L since 12 years 20 Below level of detection
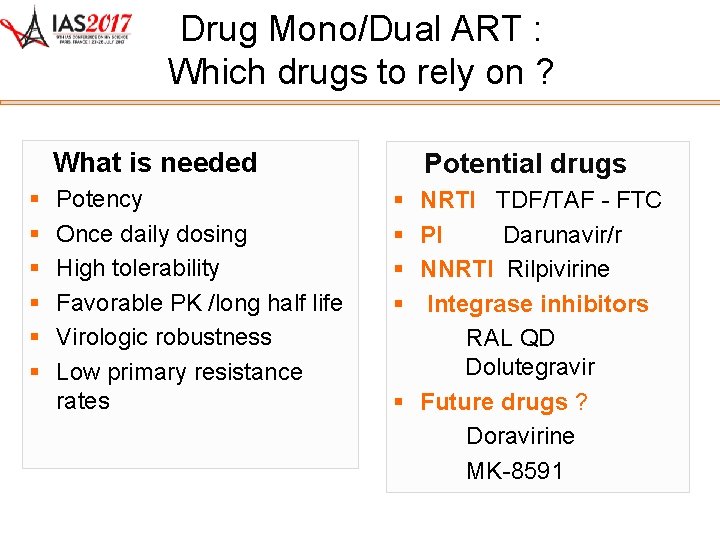
Drug Mono/Dual ART : Which drugs to rely on ? What is needed Potential drugs § § § § NRTI TDF/TAF - FTC § PI Darunavir/r § NNRTI Rilpivirine § Integrase inhibitors RAL QD Dolutegravir § Future drugs ? Doravirine MK-8591 Potency Once daily dosing High tolerability Favorable PK /long half life Virologic robustness Low primary resistance rates
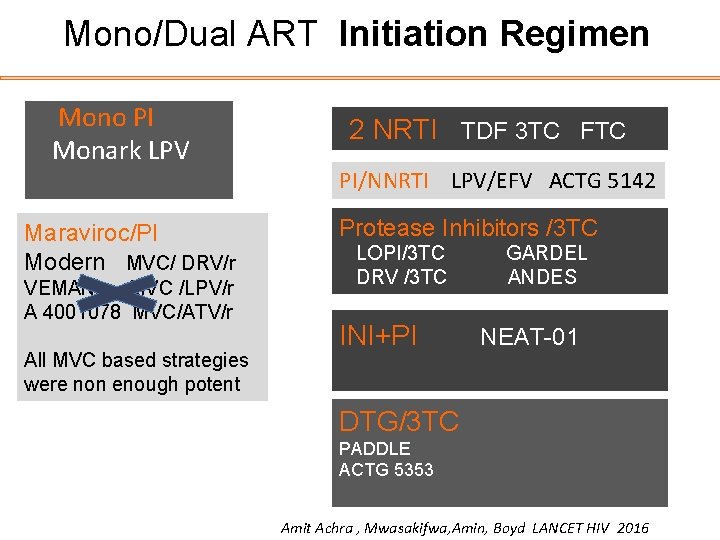
Mono/Dual ART Initiation Regimen Mono PI Monark LPV Maraviroc/PI Modern MVC/ DRV/r VEMAN MVC /LPV/r A 4001078 MVC/ATV/r All MVC based strategies were non enough potent 2 NRTI TDF 3 TC FTC INI + IP XTG/3 TC ACTG 5353 PADDLE PI/NNRTI LPV/EFV ACTG 5142 Protease Inhibitors /3 TC LOPI/3 TC GARDEL DRV /3 TC ANDES INI+PI NEAT-01 DTG/3 TC PADDLE ACTG 5353 Amit Achra , Mwasakifwa, Amin, Boyd LANCET HIV 2016
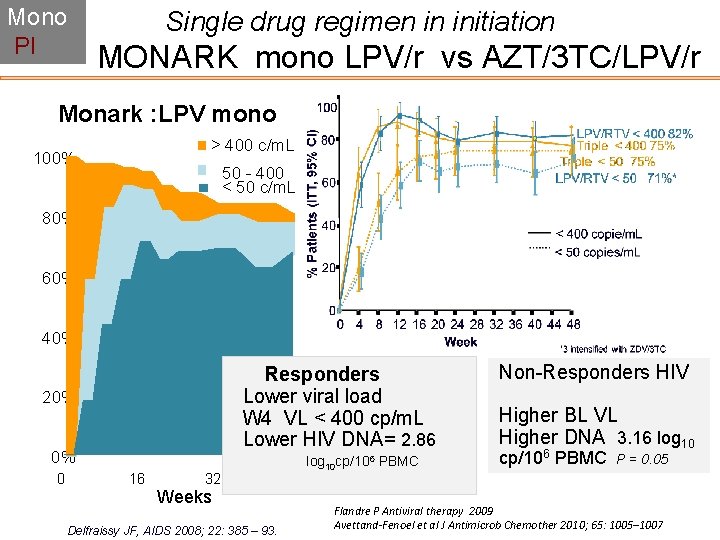
Mono PI Single drug regimen in initiation MONARK mono LPV/r vs AZT/3 TC/LPV/r Monark : LPV mono > 400 c/m. L 100% 50 - 400 < 50 c/m. L 80% 60% 40% Responders Lower viral load W 4 VL < 400 cp/m. L Lower HIV DNA= 2. 86 20% 0% 0 16 32 Weeks Delfraissy JF, AIDS 2008; 22: 385 – 93. 48 log 10 cp/106 PBMC Non-Responders HIV Higher BL VL Higher DNA 3. 16 log 10 cp/106 PBMC P = 0. 05 Flandre P Antiviral therapy 2009 Avettand-Fenoel et al J Antimicrob Chemother 2010; 65: 1005– 1007
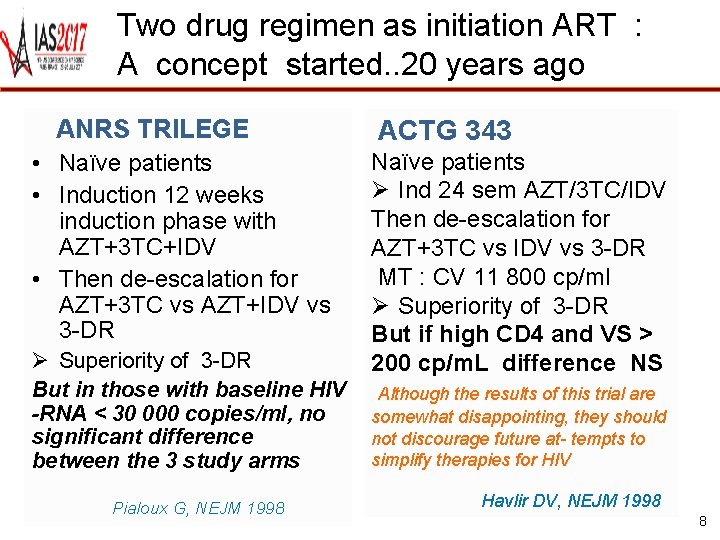
Two drug regimen as initiation ART : A concept started. . 20 years ago ANRS TRILEGE • Naïve patients • Induction 12 weeks induction phase with AZT+3 TC+IDV • Then de-escalation for AZT+3 TC vs AZT+IDV vs 3 -DR Ø Superiority of 3 -DR But in those with baseline HIV -RNA < 30 000 copies/ml, no significant difference between the 3 study arms Pialoux G, NEJM 1998 ACTG 343 Naïve patients Ø Ind 24 sem AZT/3 TC/IDV Then de-escalation for AZT+3 TC vs IDV vs 3 -DR MT : CV 11 800 cp/ml Ø Superiority of 3 -DR But if high CD 4 and VS > 200 cp/m. L difference NS Although the results of this trial are somewhat disappointing, they should not discourage future at- tempts to simplify therapies for HIV Havlir DV, NEJM 1998 8
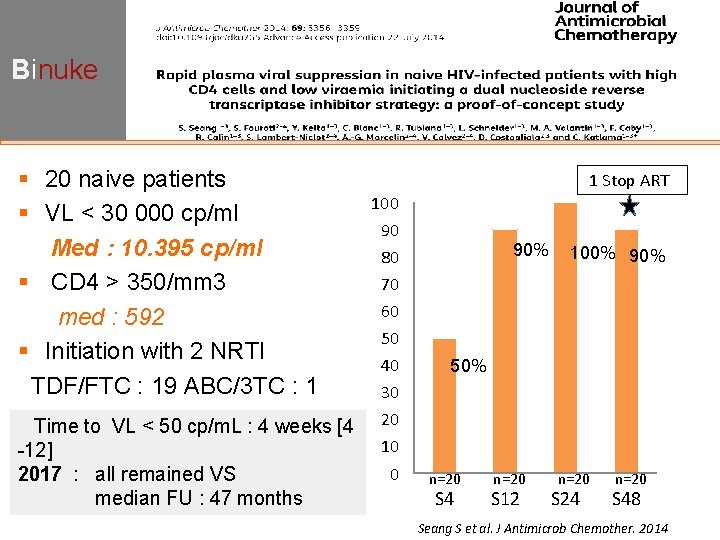
Binuke § 20 naive patients § VL < 30 000 cp/ml Med : 10. 395 cp/ml § CD 4 > 350/mm 3 med : 592 § Initiation with 2 NRTI TDF/FTC : 19 ABC/3 TC : 1 Time to VL < 50 cp/m. L : 4 weeks [4 -12] 2017 : all remained VS median FU : 47 months 1 Stop ART 100 90 90% 80 100% 90% 70 60 50 40 50% 30 20 10 0 n=20 S 4 n=20 S 12 n=20 S 24 n=20 S 48 Seang S et al. J Antimicrob Chemother. 2014
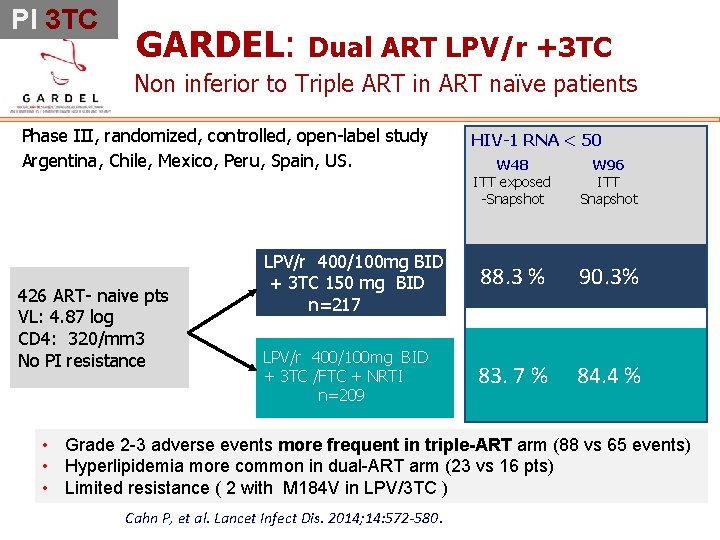
PI 3 TC GARDEL: Dual ART LPV/r +3 TC Non inferior to Triple ART in ART naïve patients Phase III, randomized, controlled, open-label study Argentina, Chile, Mexico, Peru, Spain, US. 426 ART- naive pts VL: 4. 87 log CD 4: 320/mm 3 No PI resistance HIV-1 RNA < 50 W 48 ITT exposed -Snapshot W 96 ITT Snapshot LPV/r 400/100 mg BID + 3 TC 150 mg BID n=217 88. 3 % 90. 3% LPV/r 400/100 mg BID + 3 TC /FTC + NRTI n=209 83. 7 % 84. 4 % • Grade 2 -3 adverse events more frequent in triple-ART arm (88 vs 65 events) • Hyperlipidemia more common in dual-ART arm (23 vs 16 pts) • Limited resistance ( 2 with M 184 V in LPV/3 TC ) Cahn P, et al. Lancet Infect Dis. 2014; 14: 572 -580.
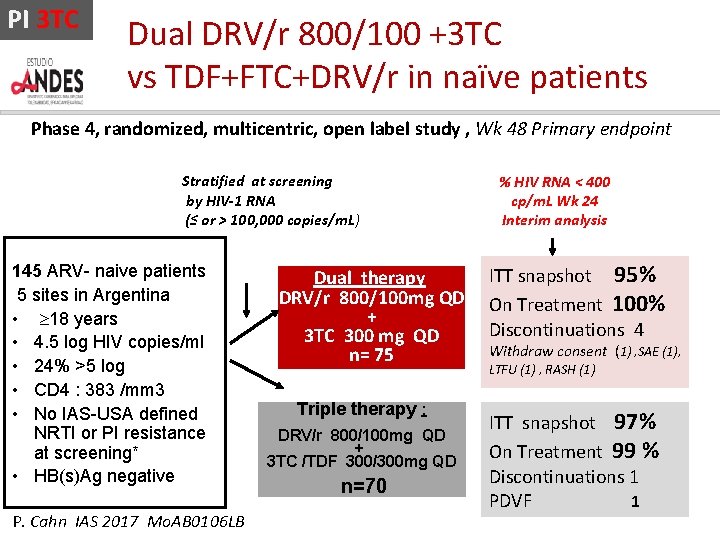
PI 3 TC Dual DRV/r 800/100 +3 TC vs TDF+FTC+DRV/r in naïve patients Phase 4, randomized, multicentric, open label study , Wk 48 Primary endpoint Stratified at screening by HIV-1 RNA (≤ or > 100, 000 copies/m. L) 145 ARV- naive patients 5 sites in Argentina • 18 years • 4. 5 log HIV copies/ml • 24% >5 log • CD 4 : 383 /mm 3 • No IAS-USA defined NRTI or PI resistance at screening* • HB(s)Ag negative P. Cahn IAS 2017 Mo. AB 0106 LB Dual therapy DRV/r 800/100 mg QD + 3 TC 300 mg QD n= 75 Triple therapy : DRV/r 800/100 mg QD + 3 TC /TDF 300/300 mg QD n=70 % HIV RNA < 400 cp/m. L Wk 24 Interim analysis ITT snapshot 95% On Treatment 100% Discontinuations 4 Withdraw consent (1) , SAE (1), LTFU (1) , RASH (1) ITT snapshot 97% On Treatment 99 % Discontinuations 1 PDVF 1
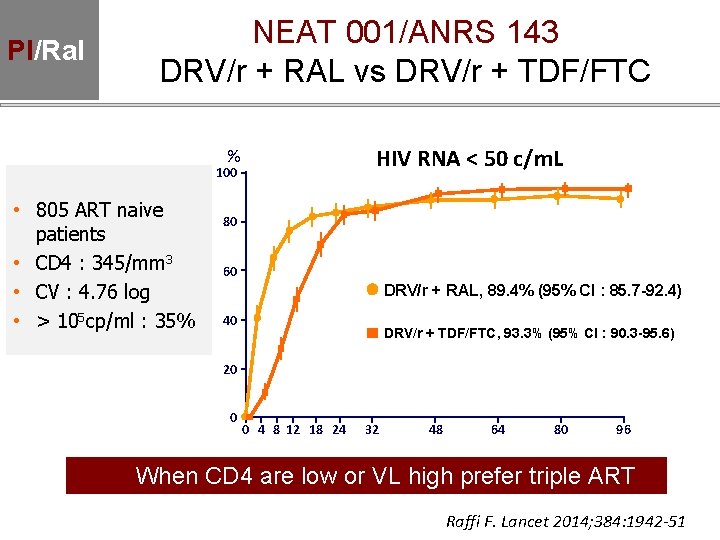
PI/Ral NEAT 001/ANRS 143 DRV/r + RAL vs DRV/r + TDF/FTC HIV RNA < 50 c/m. L % 100 • 805 ART naive patients • CD 4 : 345/mm 3 • CV : 4. 76 log • > 105 cp/ml : 35% 80 60 DRV/r + RAL, 89. 4% (95% CI : 85. 7 -92. 4) 40 DRV/r + TDF/FTC, 93. 3% (95% CI : 90. 3 -95. 6) 20 0 0 4 8 12 18 24 32 48 64 80 96 When CD 4 are low or VL high prefer triple ART Raffi F. Lancet 2014; 384: 1942 -51
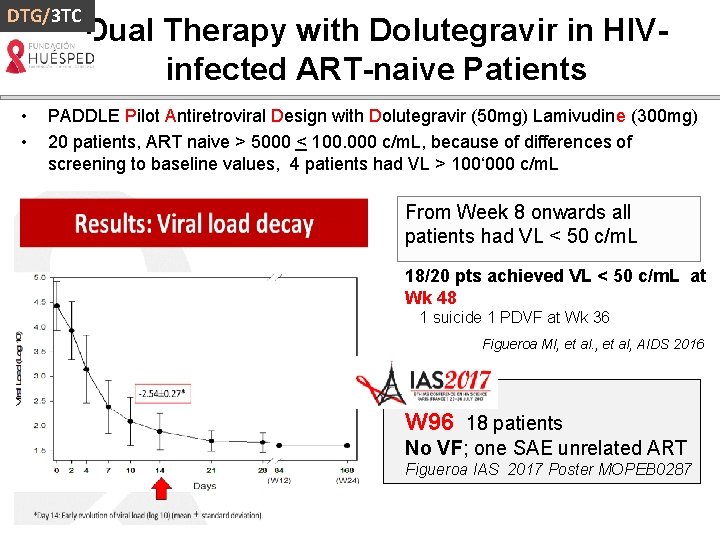
DTG/3 TC • • Dual Therapy with Dolutegravir in HIVinfected ART-naive Patients PADDLE Pilot Antiretroviral Design with Dolutegravir (50 mg) Lamivudine (300 mg) 20 patients, ART naive > 5000 < 100. 000 c/m. L, because of differences of screening to baseline values, 4 patients had VL > 100‘ 000 c/m. L From Week 8 onwards all patients had VL < 50 c/m. L 18/20 pts achieved VL < 50 c/m. L at Wk 48 1 suicide 1 PDVF at Wk 36 Figueroa MI, et al, AIDS 2016 W 96 18 patients No VF; one SAE unrelated ART Figueroa IAS 2017 Poster MOPEB 0287
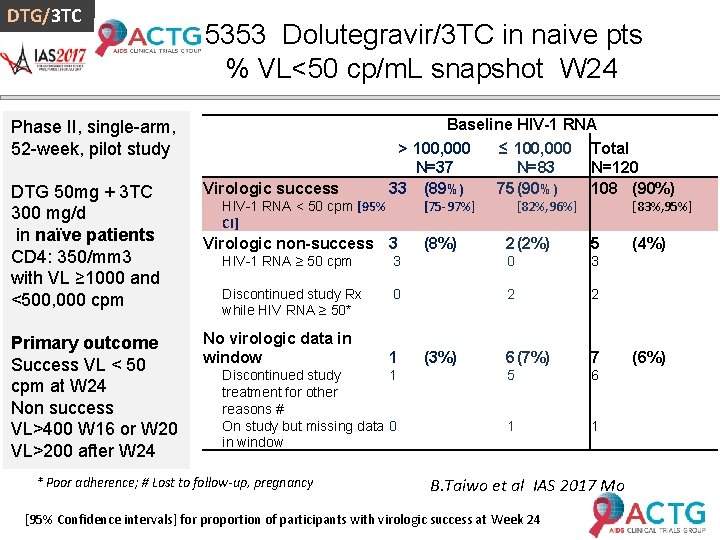
DTG/3 TC 5353 Dolutegravir/3 TC in naive pts % VL<50 cp/m. L snapshot W 24 Phase II, single-arm, 52 -week, pilot study DTG 50 mg + 3 TC 300 mg/d in naïve patients CD 4: 350/mm 3 with VL ≥ 1000 and <500, 000 cpm Primary outcome Success VL < 50 cpm at W 24 Non success VL>400 W 16 or W 20 VL>200 after W 24 Virologic success Baseline HIV-1 RNA > 100, 000 ≤ 100, 000 Total N=37 N=83 N=120 33 (89%) 75 (90%) 108 (90%) [75 -97%] HIV-1 RNA < 50 cpm [95% CI] Virologic non-success 3 [82%, 96%] [83%, 95%] (8%) 2 (2%) 5 (4%) HIV-1 RNA ≥ 50 cpm 3 0 3 Discontinued study Rx while HIV RNA ≥ 50* 0 2 2 1 (3%) 6 (7%) 7 (6%) 5 6 1 1 No virologic data in window Discontinued study 1 treatment for other reasons # On study but missing data 0 in window * Poor adherence; # Lost to follow-up, pregnancy B. Taiwo et al IAS 2017 Mo [95% Confidence intervals] for proportion of participants with virologic success at Week 24
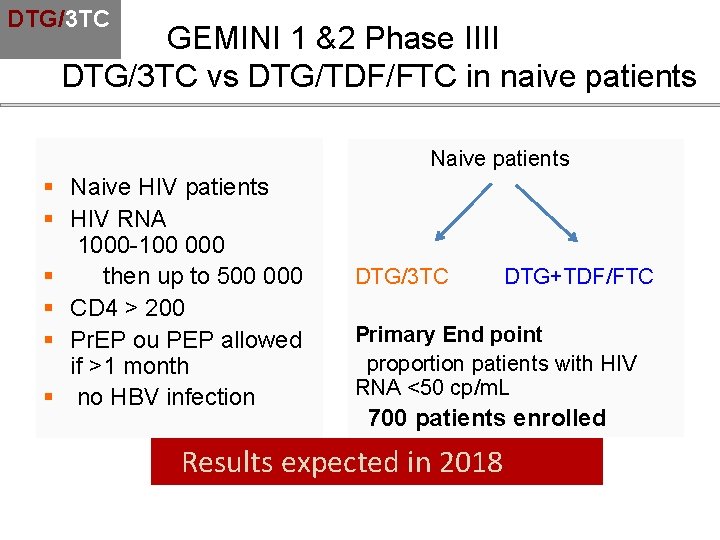
DTG/3 TC GEMINI 1 &2 Phase IIII DTG/3 TC vs DTG/TDF/FTC in naive patients Naive patients § Naive HIV patients § HIV RNA 1000 -100 000 § then up to 500 000 § CD 4 > 200 § Pr. EP ou PEP allowed if >1 month § no HBV infection DTG/3 TC DTG+TDF/FTC Primary End point proportion patients with HIV RNA <50 cp/m. L 700 patients enrolled Results expected in 2018
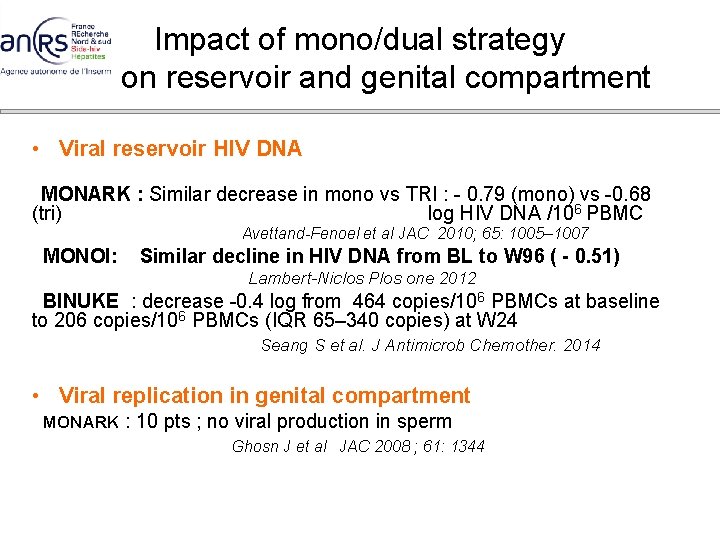
Impact of mono/dual strategy on reservoir and genital compartment • Viral reservoir HIV DNA MONARK : Similar decrease in mono vs TRI : - 0. 79 (mono) vs -0. 68 (tri) log HIV DNA /106 PBMC Avettand-Fenoel et al JAC 2010; 65: 1005– 1007 MONOI: Similar decline in HIV DNA from BL to W 96 ( - 0. 51) Lambert-Niclos Plos one 2012 BINUKE : decrease -0. 4 log from 464 copies/106 PBMCs at baseline to 206 copies/106 PBMCs (IQR 65– 340 copies) at W 24 Seang S et al. J Antimicrob Chemother. 2014 • Viral replication in genital compartment MONARK : 10 pts ; no viral production in sperm Ghosn J et al JAC 2008 ; 61: 1344
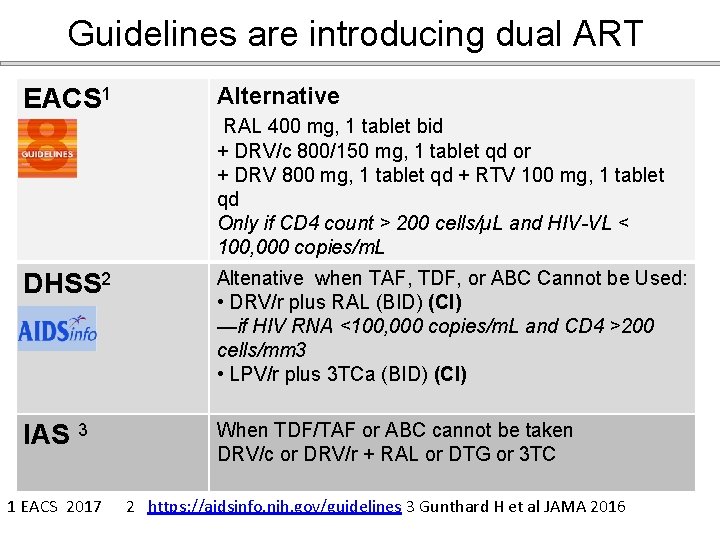
Guidelines are introducing dual ART EACS 1 Alternative RAL 400 mg, 1 tablet bid + DRV/c 800/150 mg, 1 tablet qd or + DRV 800 mg, 1 tablet qd + RTV 100 mg, 1 tablet qd Only if CD 4 count > 200 cells/µL and HIV-VL < 100, 000 copies/m. L DHSS 2 Altenative when TAF, TDF, or ABC Cannot be Used: • DRV/r plus RAL (BID) (CI) —if HIV RNA <100, 000 copies/m. L and CD 4 >200 cells/mm 3 • LPV/r plus 3 TCa (BID) (CI) IAS 3 When TDF/TAF or ABC cannot be taken DRV/c or DRV/r + RAL or DTG or 3 TC 1 EACS 2017 2 https: //aidsinfo. nih. gov/guidelines 3 Gunthard H et al JAMA 2016
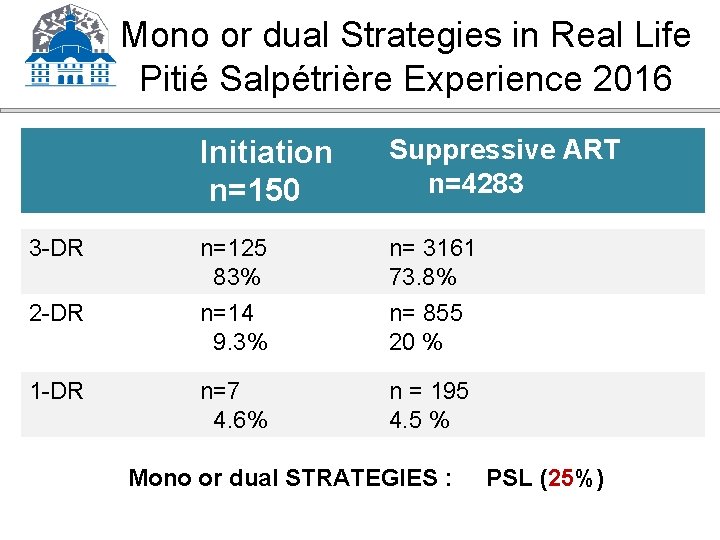
Mono or dual Strategies in Real Life Pitié Salpétrière Experience 2016 Initiation n=150 Suppressive ART n=4283 3 -DR n=125 83% n= 3161 73. 8% 2 -DR n=14 9. 3% n= 855 20 % 1 -DR n=7 4. 6% n = 195 4. 5 % Mono or dual STRATEGIES : PSL (25%)
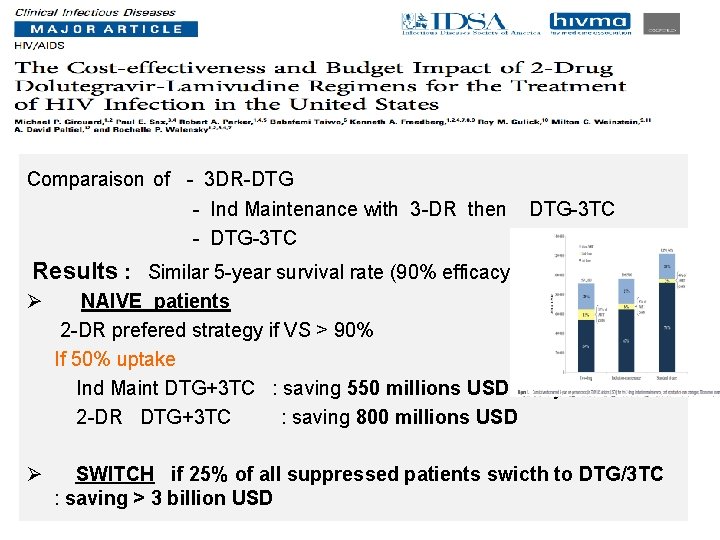
Comparaison of - 3 DR-DTG - Ind Maintenance with 3 -DR then DTG-3 TC - DTG-3 TC Results : Similar 5 -year survival rate (90% efficacy ) Ø NAIVE patients 2 -DR prefered strategy if VS > 90% If 50% uptake Ind Maint DTG+3 TC : saving 550 millions USD in 5 years 2 -DR DTG+3 TC : saving 800 millions USD Ø SWITCH if 25% of all suppressed patients swicth to DTG/3 TC : saving > 3 billion USD
Final Thoughts § Individualization of ART is a key challenge for lifelong HIV infection with currently no option for stopping treatment § Dual ART with potent and robust drugs is a realistic ART option for treatment-naive patients with low to moderate viral load and good immune status. § Robust options such as Darunavir or Dolutegravir combined with 3 TC are very promising ; more data will be forthcoming in 2018 § New NRTIs , NNRTIs, INIs and other classes of drugs with high potency and robust genetic barrier to resistance should be investigated as part of dual ART
Acknowledgement Ø Pitie Salpétriere Team et al outside R. Tubiana, MA Valantin, F. Caby, L Schneider, S. Seang, R. Palich, J. Ghosn V Calve, z AG Marcelin, G Peytavin, B. Autran, D. Costagliola, L. Assoumou Ø International drug reduced strategies aficionados Pedro Cahn, Babafemi Taiwo, E Martinez, R. Murphy