
Disorders of Water Electrolytes Acid Base Metabolism Lecture

Disorders of Water, Electrolytes & Acid– Base Metabolism Lecture 5
Introduction A complex system of chemical buffers together with highly specialized mechanisms of the lungs and kidneys continuously work together to ensure a precise balance of water, electrolytes, and p. H in both the intracellular and extracellular compartments of the human body. Although these systems display impressive flexibility and responsiveness to perturbation by illness or injury, they do have limits, at which point medical evaluation and treatment are required. 2

TOTAL BODY WATER: VOLUME AND DISTRIBUTION 3

TOTAL BODY WATER: VOLUME AND DISTRIBUTION The minimum daily requirement for water can be estimated from renal & insensible losses: renal (1200 to 1500 m. L in urine) and “insensible” losses (≈400 to 700 m. L) evaporation from the skin and respiratory tract. 4 Activity, environmental conditions, and disease all have dramatic effects on daily water (and electrolyte) requirements. On average, an adult must take in ≈1. 5 to 2. 0 L of water daily to maintain fluid balance. Because primary regulatory mechanisms are designed to first maintain intracellular hydration status, imbalances in TBW are initially reflected in the ECF compartment.
TOTAL BODY WATER: VOLUME AND DISTRIBUTION Changes in Extracellular Fluid Volume 5 Clinical Manifestations Causes ECF loss Thirst, anorexia, nausea, lightheadedness, Orthostatic hypotension, syncope, tachycardia, oliguria, decreased skin turgor and “sunken eyes”, shock, coma, death Trauma (and other causes of acute blood loss), “third spacing” of fluid (eg, burns, pancreatitis, peritonitis), vomiting, diarrhea, diuretics, renal or adrenal (ie, sodium wasting) Disease ECF gain Weight gain, edema, dyspnea (secondary to pulmonary edema), tachycardia, jugular venous distention (HF), portal hypertension (ascites) cirrhosis, esophageal Varices Heart failure, cirrhosis, nephrotic syndrome, iatrogenic (intravenous fluid overload)

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS The primary cationic (positively charged) electrolytes are: Sodium (Na+), potassium (K+), calcium (Ca 2+), and magnesium (Mg 2+), Whereas the anions (negatively charged) include: Chloride (Cl-), bicarbonate ( HCO 3 - ), phosphate (HPO 24 - , H 2 PO 24 - ), sulfate ( SO 24 - ), organic ions such as lactate, and negatively charged proteins. Na+, K+, Cl-, and HCO 3 - in the plasma or serum are commonly analyzed in an electrolyte profile because their concentrations provide the most relevant information about the osmotic, hydration, and acidbase status of the body. 6

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Any increase in the concentration of one anion is accompanied by a corresponding decrease in other anions, or by an increase in one or more cations or both because total electrical neutrality must be maintained. Similarly, any decrease in the concentration of anions involves a corresponding increase in other anions, a decrease in cations, or both. In the case of polyvalent ions (eg, Ca 2+, Mg 2+), it is important to distinguish between the substance concentration of the ion itself and the concentration of the ion charge. Thus, although the concentration of total calcium ions in normal plasma is ≈2. 5 mmol/L, the concentration of the total calcium ion charge is 5. 0 mmol/L (also called 5 milliequivalents per liter [m. Eq/L]). 7

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium Disorders of Na+ homeostasis can occur because of: Excessive loss, gain, or retention of Na+, or as The result of excessive loss, gain, or retention of H 2 O. It is difficult to separate disorders of Na+ and H 2 O balance because of their close relationship in establishing normal osmolality in all body water compartments. Homeostasis within a narrow window is necessary for life, and the body must defend against excessive gains or losses. 8

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia is defined as a decreased plasma Na+ concentration (sodium level goes below 135 mmol/L). Hyponatremia typically manifests clinically as: Nausea, generalized weakness, Mental confusion at values below 120 mmol/L, & Severe mental confusion plus seizures at less than 105 mmol/L. The rapidity of development of hyponatremia influences the Na+ concentrations at which symptoms develop ie, clinically apparent symptoms may manifest at higher Na+ concentrations [≈125 mmol/L] when hyponatremia develops rapidly. 9
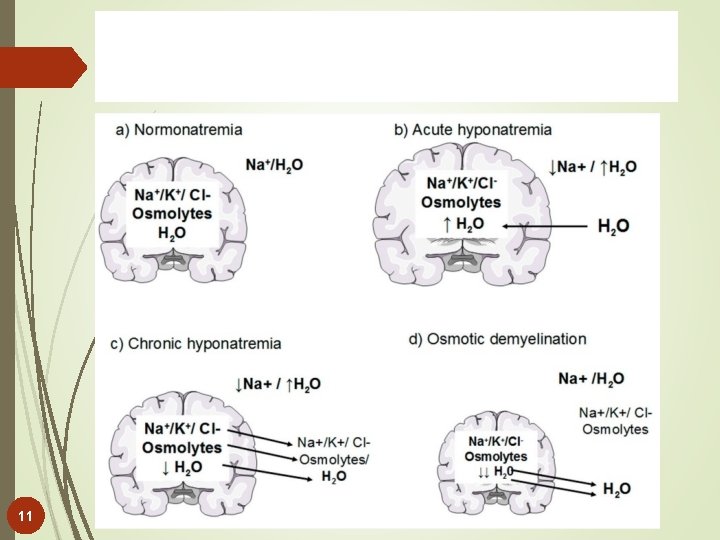
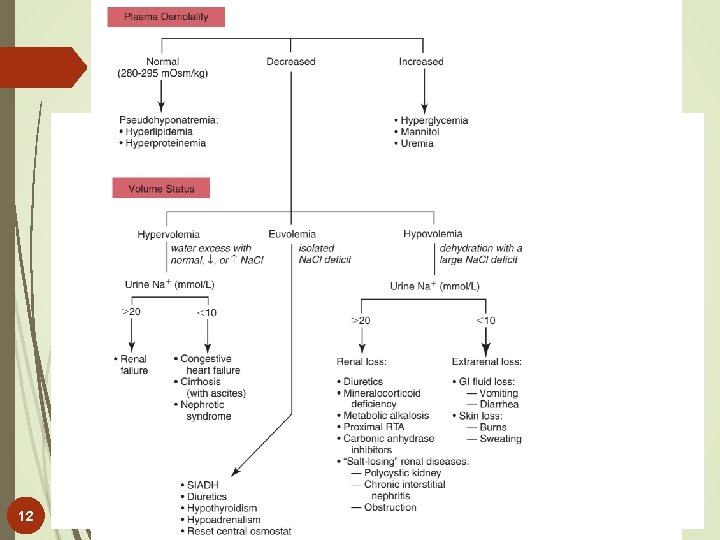
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Symptoms are due to changes in osmolality rather than to the Na+ concentration by itself. CNS symptoms are due to movement of H 2 O into cells to maintain osmotic balance and subsequent swelling of CNS cells. These symptoms can occur more rapidly in children, so there is a need to be particularly aware in the pediatric population. Hyponatremia can be: hypo-osmotic, hyperosmotic, or iso-osmotic. Thus measurement of plasma osmolality is an important initial step in the assessment of hyponatremia. the most common form is hypo-osmotic hyponatremia. 10
11
12

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hyperosmotic Hyponatremia in the presence of increased quantities of other solutes in the ECF is the result of an extracellular shift of water or an intracellular shift of Na+ to maintain osmotic balance between ECF and ICF compartments. The most common cause of this type of hyponatremia is severe hyperglycemia. As a general rule, Na+ is decreased by ≈1. 6 to 2. 0 mmol/L for every 100 mg/d. L increase in glucose above 100 mg/d. L. Correction of hyperglycemia will restore normal blood Na+. It also may occur when mannitol and glycine, used for irrigation during certain surgical procedures, enter the intravascular fluid compartment. 13

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Isosmotic Hyponatremia If the measured Na+ concentration in plasma is decreased, but measured plasma osmolality, glucose, and urea are normal, the most likely explanation is pseudohyponatremia caused by the electrolyte exclusion effect. This occurs when Na+ is measured by an indirect ion-selective electrode in patients with severe hyperlipidemia or hyperproteinemia. Pseudohyponatremia is confirmed if direct ISE value is normal. If direct ISE is not available, simultaneous calculation and measurement of plasma osmolarity is very useful. Measured osmolarity is normal in pseudohyponatremia but calculated osmolarity – based as it is on erroneously low plasma sodium result – is reduced. 14
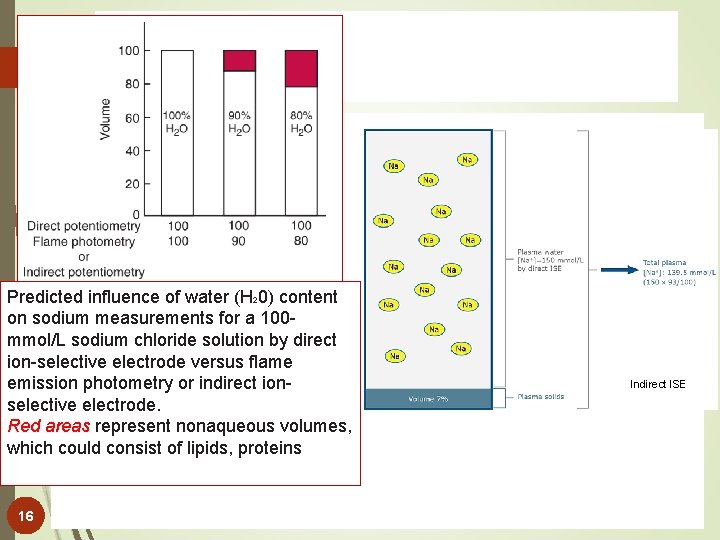
Predicted influence of water (H 20) content on sodium measurements for a 100 mmol/L sodium chloride solution by direct ion-selective electrode versus flame emission photometry or indirect ionselective electrode. Red areas represent nonaqueous volumes, which could consist of lipids, proteins 16 Indirect ISE

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia Typically, when plasma Na+ concentration is low, calculated or measured osmolality also will be low. This type of hyponatremia can be due to: Excess loss of Na+ (depletional hyponatremia) or increased ECF volume (dilutional hyponatremia). Differentiating these initially requires clinical assessment of TBW and ECF volume by history and physical examination. 17

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia Depletional hyponatremia results from a loss of Na+ from the ECF space that exceeds the concomitant loss of water. The net loss of Na+ from the ECF space also stimulates thirst and production of vasopressin, both of which contribute to the maintenance of hyponatremia. Hypovolemia is apparent in the physical examination (orthostatic hypotension, tachycardia, decreased skin turgor). If urine Na+ is low (<10 mmol/L), the kidneys are properly retaining filtered Na+ and the loss is extrarenal, most commonly from the GIT or skin. 18

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia Alternatively, if urine Na+ is increased in this setting (generally >20 mmol/L), renal loss of Na+ likely. Renal loss of Na+ occurs with: Use of diuretics (which inhibit reabsorption of Cl- and Na+ in the ascending loop), Adrenal insufficiency (no aldosterone), or Salt-wasting nephropathies, as can occur with interstitial nephritis. 19

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia Renal loss of Na+ in excess of H 2 O can also occur in metabolic alkalosis from prolonged vomiting, because increased renal HCO 3 - excretion is accompanied by Na+ ions. In this case, urine sodium is increased (>20 mmol/L), but urine chloride remains low. In proximal renal tubular acidosis (RTA) type 2, bicarbonate is lost because of a defect in HCO 3 - reabsorption, and Na+ is coexcreted to maintain electrical neutrality. As with extrarenal Na+ loss, management is centered around the reversal of underlying cause and restoration of ECF volume. 20

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia 21 Dilutional hyponatremia is a result of excess H 2 O retention and often can be detected during the physical examination as edema. In advanced renal failure, water is retained because of decreased filtration and H 2 O excretion. When ECF is increased but the circulating blood volume is decreased, as occurs in hepatic cirrhosis and nephrotic syndrome, a vicious cycle is established. The decreased blood volume is sensed by baroreceptors and results in increased aldosterone and vasopressin, even though ECF volume is excessive. The kidneys reabsorb Na+ and H 2 O in response to increased aldosterone and vasopressin in an attempt to restore the blood volume, resulting in further increases in ECF and further dilution of Na+.

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia In hypo-osmotic hyponatremia with a normal or euvolemic volume status, the most common causes are the syndrome of inappropriate antidiuretic hormone (ADH) (vasopressin) (SIADH), primary polydipsia, and endocrine disorders such as adrenal insufficiency and hypothyroidism. Hypothyroidism impairs free H 2 O excretion. Free water restriction is the mainstay of therapy in SIADH. 22

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia However, in severe or symptomatic hyponatremia from any cause, the use of hypertonic saline solutions may be required to correct serum Na+ concentrations. In such cases, the hyponatremia must be corrected cautiously because too rapid correction can lead to brain demyelination. Current recommendations are to increase Na+ by 0. 5 to 2. 0 mmol/L per hour and not to exceed a total increase in Na+ greater than 18 to 25 mmol/L over 48 hours. 23

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hyponatremia Hypo-Osmotic Hyponatremia Finally, euvolemic hyponatremia also can be found in primary polydipsia when water intake is greater than the renal capacity to excrete excess H 2 O. This can be the result of psychiatric illness, but diseases that cause hypothalamic disorders, such as sarcoidosis, also may cause polydipsia by altering the thirst reflex. 24

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia is generally defined as a serum sodium level of more than 145 mmol/L. Symptoms of hypernatremia are primarily neurologic (because of neuronal cell loss of H 2 O to the ECF) and include tremors, irritability, ataxia, confusion, and coma. As with hyponatremia, the rapidity of development of hypernatremia will determine the plasma Na+ concentration at which symptoms occur. Acute development may cause symptoms at 160 mmol/L, although in chronic hypernatremia, symptoms may not occur until Na+ exceeds 175 mmol/L. In chronic hypernatremia, the intracellular osmolality of CNS cells will increase to protect against intracellular dehydration. 25

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Because of this, rapid correction of hypernatremia can cause dangerous cerebral edema because CNS cells will take up too much water if the ICF is hyperosmotic when normonatremia is achieved. In many cases, the symptoms of hypernatremia may be masked by underlying conditions. Hypernatremia rarely occurs in an alert patient with a normal thirst response and access to water. Most cases are observed in patients with altered mental status or infants, both of whom may not be capable of rehydrating themselves. 26

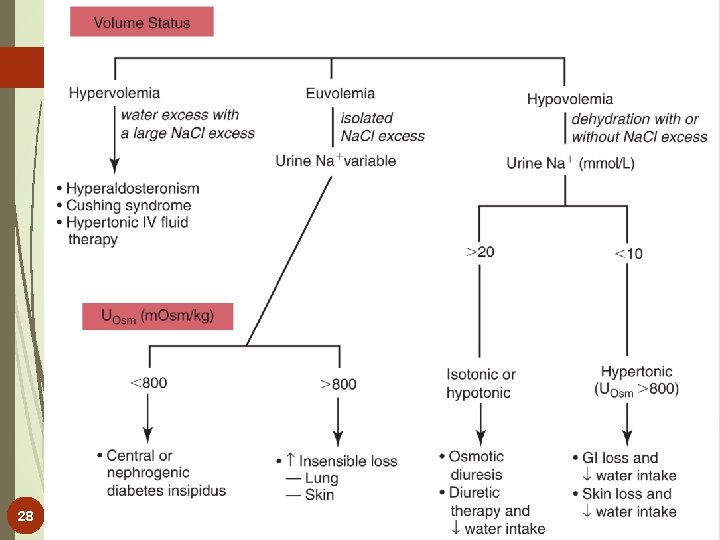
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia arises in the setting of: Hypovolemia (excessive water loss or failure to replace normal water losses), Hypervolemia (a net Na+ gain in excess of water gain), or Normovolemia. Again, assessment of TBW status by physical examination and measurement of urine Na+ and osmolality are important steps in establishing a diagnosis. 27
28

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Hypovolemic Hypernatremia in the setting of decreased ECF is caused by renal or extrarenal loss of hypo-osmotic fluid, leading to dehydration. Thus, once hypovolemia is established by physical examination, measurement of urine Na+ and osmolality is used to determine the source of fluid loss. Patients who have large extrarenal losses will have concentrated urine (often >800 m. Osmol/L) with low urine Na+ (<20 mmol/L), reflecting a proper renal response to conserve Na+ and water to restore ECF volume. Extrarenal causes include diarrhea, skin losses (burns, fever, or excessive sweating), and respiratory losses coupled with failure to replace the water. 29

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Hypovolemic Hypernatremia When gastrointestinal loss is excluded, and the patient has normal mental status and access to H 2 O, a hypothalamic disorder (tumor or granuloma) inducing diabetes insipidus (DI) should be suspected. In patients with poorly controlled diabetes with glucose values greater than 600 mg/d. L, an osmotic diuresis can occur that results in extreme dehydration and hypernatremia. This condition is referred to as hyperosmolar hyperglycemic nonketotic syndrome and occurs most commonly in elderly individuals with type 2 diabetes. 30

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Normovolemic Hypernatremia in the presence of normal ECF volume is often a prelude to hypovolemic hypernatremia. Insensible losses through the lung or skin must be suspected and are characterized by concentrated urine as the kidneys conserve water. Another cause of normovolemic hypernatremia is water diuresis, which is manifested by polyuria. The differential for polyuria (generally defined as >3 L urine output/d) is a water or solute diuresis. Solute diuresis is exemplified by the osmotic diuresis of diabetes mellitus and generally is characterized by urine osmolality greater than 300 m. Osmol/L and hyponatremia. Water diuresis, a manifestation of DI, is characterized by dilute urine (osmolality <250 m. Osmol/L) and hypernatremia. 31

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Normovolemic Hypernatremia DI can be central or nephrogenic. Central DI is due to decreased or absent vasopressin secretion resulting from head trauma or pituitary tumor Nephrogenic DI is due to renal resistance to vasopressin as a result of drugs (eg, lithium) or electrolyte disorders. When thirst and access to water are uncompromised, many patients with DI will remain normonatremic because their free water losses are compensated by intake. 32

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Normovolemic Hypernatremia Such patients display symptoms of only polyuria and polydipsia. However, overt hypernatremia can become manifest with progression of underlying causes, impaired thirst, or restricted access to water. Administration of vasopressin can be used to treat central DI, although patients with nephrogenic DI may be resistant to it. Correction of underlying disorders or discontinuation of offending drugs may be required to normalize Na+ concentrations in nephrogenic DI. 33

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Sodium: Hypernatremia Hypervolemic Hypernatremia The presence of excess TBW and hypernatremia indicates a net gain of water and Na+, with Na+ gain in excess of water. This rare condition is observed most commonly in hospitalized patients receiving hypertonic saline or sodium bicarbonate. 34
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium The total body potassium of a 70 -kg subject is ≈3. 5 mol (40 to 59 mmol/kg), of which only 1. 5 to 2% is present in the ECF. Nevertheless, plasma K+ is often a good indicator of total K+ stores. Disturbance of K+ homeostasis has serious consequences. For example, a decrease in extracellular K+ (hypokalemia) is characterized by muscle weakness, irritability, and paralysis. Plasma K+ concentrations < 3. 0 mmol/L are often associated with marked neuromuscular symptoms and indicate a critical degree of intracellular depletion. At lower concentrations, tachycardia and cardiac conduction defects are apparent on electrocardiogram (ECG) and can lead to cardiac arrest. 35
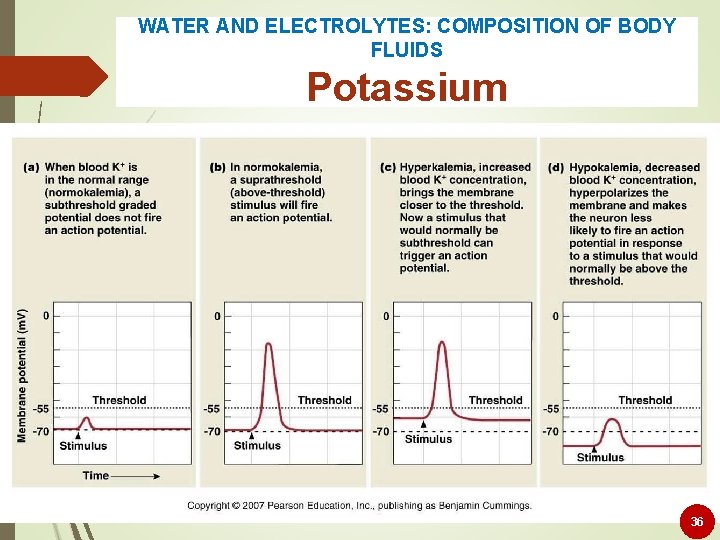
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium 36
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium High extracellular K+ (hyperkalemia) concentrations may produce symptoms of mental confusion, weakness, and weakness of the respiratory muscles. Cardiac effects of hyperkalemia include bradycardia and conduction defects. Prolonged, severe hyperkalemia >7. 0 mmol/L can lead to peripheral vascular collapse and cardiac arrest. Symptoms or ECG abnormalities are almost always present at K+ concentrations above 6. 5 mmol/L. Concentrations greater than 10. 0 mmol/L in most cases are fatal, although fatalities can occur at significantly lower values. 37
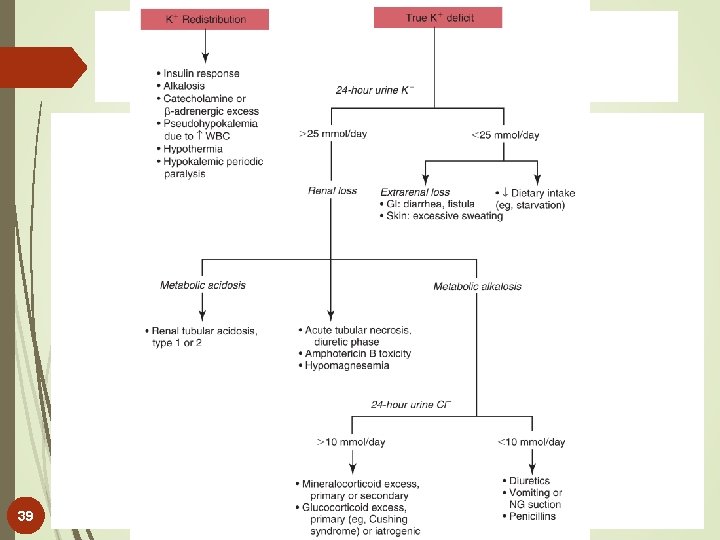
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hypokalemia Causes of hypokalemia (plasma K+ <3. 5 mmol/L) are classified as: Redistribution of extracellular K+ into ICF, or True K+ deficits, caused by: decreased intake or loss of potassium-rich body fluids. 38
39

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hypokalemia Redistribution Insulin promotes acute entry of K into skeletal muscle and liver by increasing Na, K-ATPase activity. In alkalosis, K+ moves from ECF into cells in exchange with H+. Pseudohypokalemia can occur in cases of very high white blood cell or platelet counts. when the blood sample is kept at room temp. for a relatively long period. 40
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hypokalemia Autosomal dominant channelopathy characterized by muscle weakness or paralysis when there is a fall in potassium levels in the blood caused most commonly by mutations in the alpha subunit of the skeletal muscle calcium channel gene Cav 1. 1 Clinically, redistributive hypokalemia is generally a transient phenomenon that is reversed once underlying conditions are corrected. 41

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hypokalemia True Potassium Deficit Hypokalemia reflecting true total body deficits of K+ as a consequence of potassium loss can be classified into renal and nonrenal losses, based on daily excretion of K+ in the urine. If urine excretion of K+ is < 25 mmol/d, it can be concluded that the kidneys are functioning properly and are attempting to reabsorb K+. The cause may be: decreased K+ intake Causes of decreased intake include chronic starvation and postoperative intravenous fluid therapy with K+-poor solutions. extrarenal loss of K+-rich fluid Gastrointestinal loss of K+ occurs most commonly with diarrhea and loss of gastric fluid through vomiting. 42

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hypokalemia Urine excretion exceeding 25 mmol/d in a hypokalemic setting is inappropriate and indicates that the kidneys are the primary source of K+ loss. Renal losses of K+ may occur: during the diuretic (recovery) phase of acute tubular necrosis and Magnesium deficiency also can lead to increased renal loss of K+, which is attributable to a reduction in the inhibitory effect of magnesium on luminal potassium channels Due to metabolic acidosis (renal tubular acidosis) 43
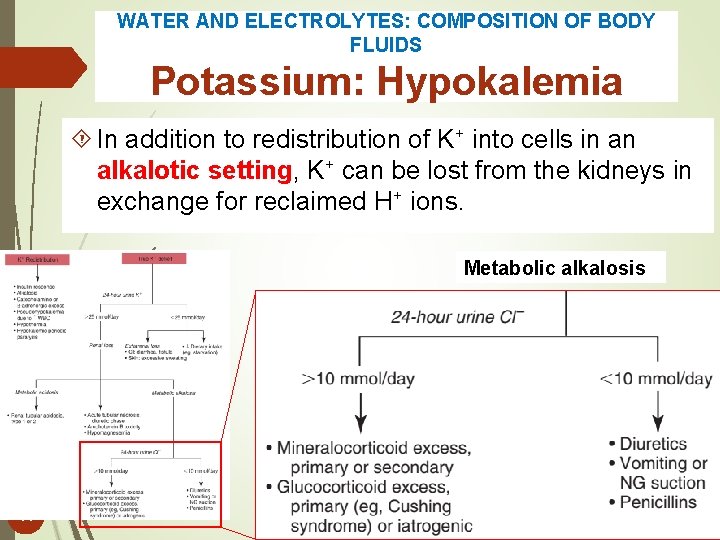
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hypokalemia In addition to redistribution of K+ into cells in an alkalotic setting, K+ can be lost from the kidneys in exchange for reclaimed H+ ions. Metabolic alkalosis 44
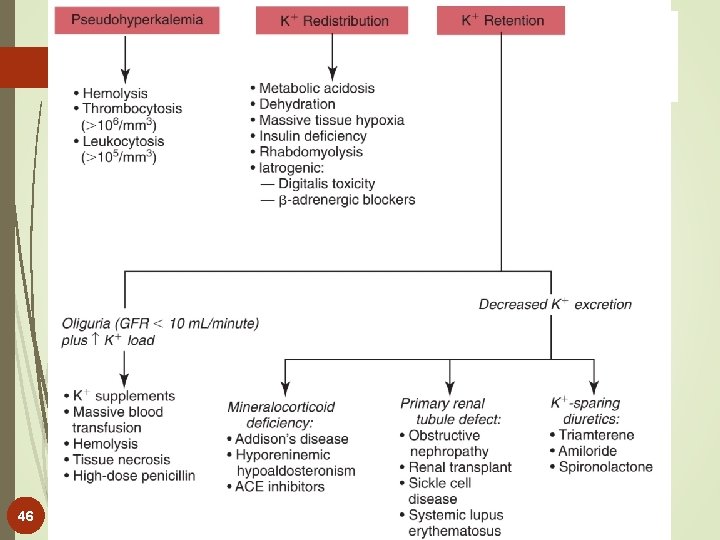
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Potassium: Hyperkalemia (plasma K+ >5. 0 mmol/L) is a result of (singly or in combination) Redistribution, Increased intake, or Increased retention. In addition, preanalytical conditions—such as: Hemolysis, Thrombocytosis (>106/µL), and Leukocytosis (>105/µL together with delayed sample analysis)—have been known to cause marked pseudohyperkalemia 45
46

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Chloride In the absence of acid-base disturbances, Clconcentrations in plasma generally will follow those of Na+. However, determination of plasma Cl- concentration is useful in the differential diagnosis of acid-base disturbances and is essential for calculating the anion gap. Fluctuations in serum or plasma Cl- have little clinical consequence, but do serve as signs of an underlying disturbance in fluid or acid-base homeostasis. The specific replacement of chloride is rarely targeted at chloride deficit independently, but it is a corner stone of management for metabolic alkalosis. 47
WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Chloride: Hypochloremia is defined as a chloride level less than 95 mmol/L. In general, causes of hypochloremia parallel causes of hyponatremia. Persistent gastric secretion and prolonged vomiting result in significant loss of Cl- and ultimately in hypochloremic alkalosis and depletion of total body Cl- with retention of HCO 3 -. Respiratory acidosis, which is accompanied by increased HCO 3 - , is another common cause of decreased Cl- with normal Na+. 48

WATER AND ELECTROLYTES: COMPOSITION OF BODY FLUIDS Chloride: Hyperchloremia Increased plasma Cl- concentration, similar to increased Na+ concentration, occurs with dehydration, prolonged diarrhea with loss of sodium bicarbonate, DI, and overtreatment with normal saline solutions, which have a Cl- content of 150 mmol/L. In fact, mounting evidence suggests that use of saline (Na. Cl) solution for maintenance, intraoperative, and resuscitative therapy can result in a host of hyperchloremia induced side effects. A rise in Cl- concentration also may be seen in respiratory alkalosis because of renal compensation for excreting HCO 3 -. 49

50 Case Studies Disorders of Water, Electrolytes

Case 1 A 45‐year‐old man was brought into the A&E department late at night in a comatose state. It was impossible to obtain a history from him, and clinical examination was difficult, but it was noted that he smelt strongly of alcohol. The following analyses were requested urgently. 51
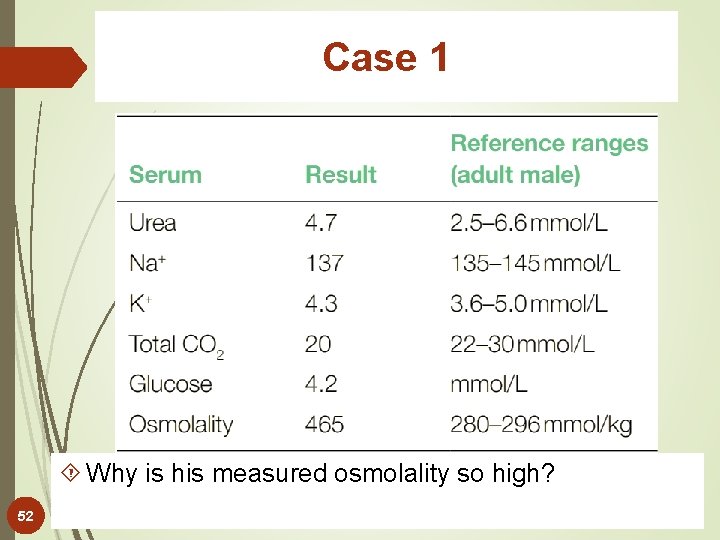
Case 1 Why is his measured osmolality so high? 52
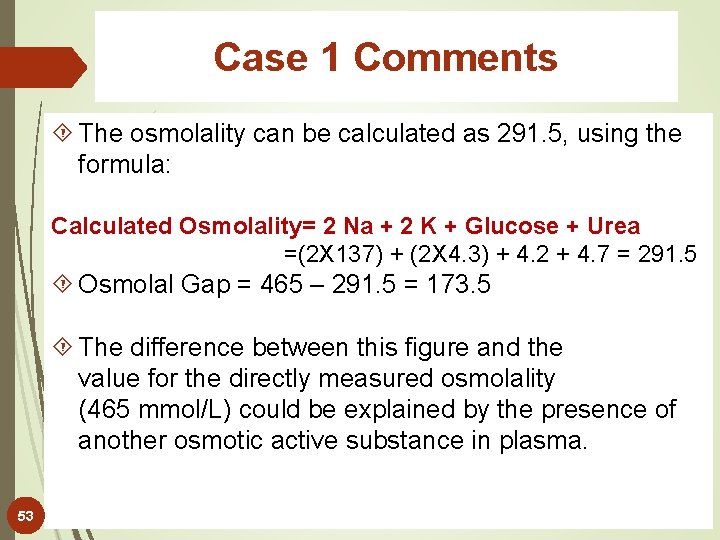
Case 1 Comments The osmolality can be calculated as 291. 5, using the formula: Calculated Osmolality= 2 Na + 2 K + Glucose + Urea =(2 X 137) + (2 X 4. 3) + 4. 2 + 4. 7 = 291. 5 Osmolal Gap = 465 – 291. 5 = 173. 5 The difference between this figure and the value for the directly measured osmolality (465 mmol/L) could be explained by the presence of another osmotic active substance in plasma. 53

Case 1 Comments From the patient’s history, it seemed that ethanol might be contributing significantly to the plasma osmolality, and plasma ethanol was measured the following day, on the residue of the specimen collected at the time of emergency admission. The result was 170 mmol/L, very close to the difference between the measured and calculated osmolalities. 54
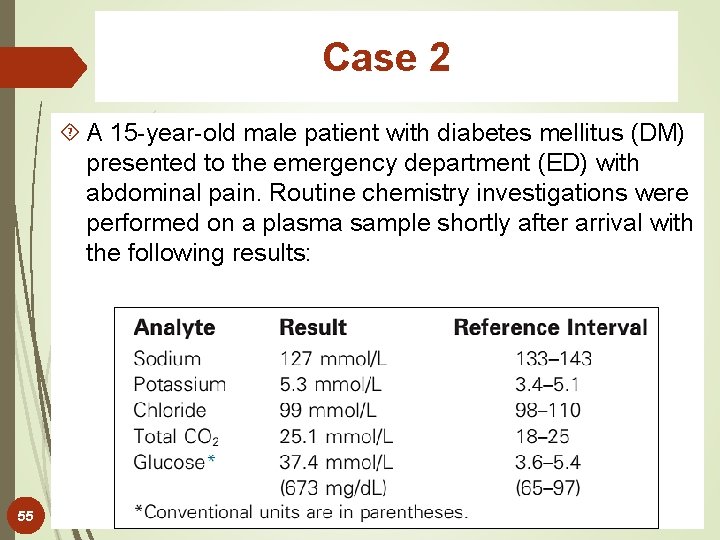
Case 2 A 15 -year-old male patient with diabetes mellitus (DM) presented to the emergency department (ED) with abdominal pain. Routine chemistry investigations were performed on a plasma sample shortly after arrival with the following results: 55

Case 2 Comments Patients with DM and increased plasma glucose concentration have a high plasma osmolality in the extracellular compartment. This causes shifting of water from inside the cells into the extracellular compartment and a subsequent dilution of plasma components, including sodium. Therefore the hyponatremia in this case can be explained solely on the basis of the increased plasma glucose concentration. 56

Case 2 Comments As a general rule, Na+ is decreased by ≈1. 6 to 2. 0 mmol/L for every 100 mg/d. L increase in glucose above 100 mg/d. L. In this case, the plasma glucose of 673 mg/d. L will depress plasma sodium by approximately 9 mmol/L. Therefore, using a correction formula, the sodium concentration becomes: 127 + 9 = 136 mmol/L The hyponatremia may be corrected simply by restoring the plasma glucose concentration to normal. 57

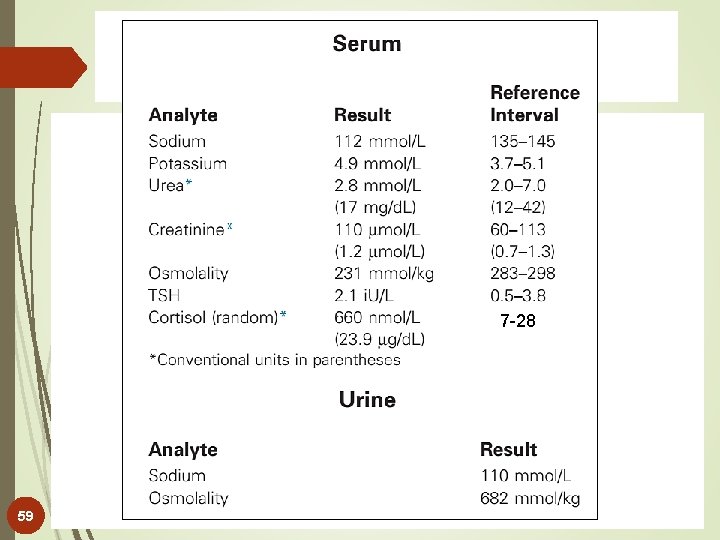
Case 3 A 60 -year-old male was admitted to hospital with persistent cough, disorientation, and confusion. He was a heavy smoker and was not taking any medications. On examination, he appeared euvolemic. The following results were obtained in blood and urine samples sent to the laboratory: 58
7 -28 59

Case 3 Comments This patient had severe, symptomatic hyponatremia. There was no biochemical evidence of renal, adrenal, or pituitary disease. On examination, the patient did not appear to be volume depleted or overloaded. Based on his laboratory results and clinical history, a diagnosis of the syndrome of inappropriate diuretic hormone secretion (SIADH) was considered. 60
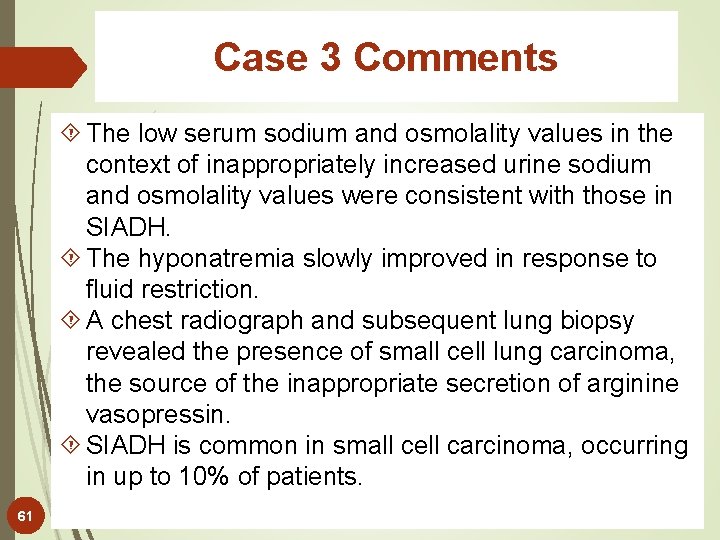
Case 3 Comments The low serum sodium and osmolality values in the context of inappropriately increased urine sodium and osmolality values were consistent with those in SIADH. The hyponatremia slowly improved in response to fluid restriction. A chest radiograph and subsequent lung biopsy revealed the presence of small cell lung carcinoma, the source of the inappropriate secretion of arginine vasopressin. SIADH is common in small cell carcinoma, occurring in up to 10% of patients. 61
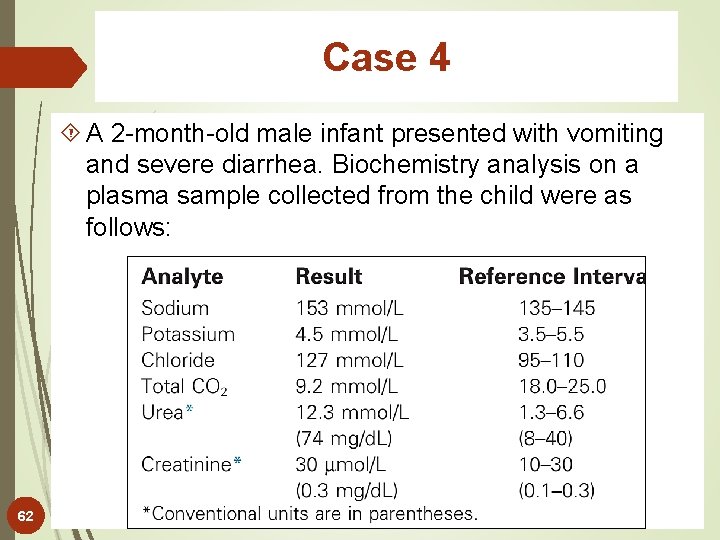
Case 4 A 2 -month-old male infant presented with vomiting and severe diarrhea. Biochemistry analysis on a plasma sample collected from the child were as follows: 62

Case 4 Comments The results show hypernatremia and biochemical evidence of dehydration (uremia). Diarrheal fluid is hypotonic in relation to plasma; therefore, unless the patient’s water intake is high, severe diarrhea can easily lead to a hypernatremic state, especially in infants and young children. Diarrheal fluid from the small bowel is also rich in bicarbonate; therefore episodes of diarrhea may result in decreased plasma bicarbonate (total CO 2) levels with concurrent increases in the plasma chloride concentration, as demonstrated in this case. 63

Case 4 Comments In the presence of hypernatremia, water moves out of the intracellular compartment into the extracellular compartment in an attempt to decrease the osmolality of the plasma. The clinical signs of dehydration in cases of hypernatremia are not always apparent or perhaps as obvious as with cases involving a normal or low plasma sodium concentration. 64
ACID-BASE PHYSIOLOGY The p. H of plasma may be considered to be a function of two independent variables: The PCO 2, which is regulated by the lungs and represents the acid component of the carbonic acid/bicarbonate buffer system, and The concentration of titratable base (base excess or deficit), which is regulated by the kidneys. The plasma total CO 2 concentration generally is taken as a measure of the base excess or deficit in plasma and ECF. 65
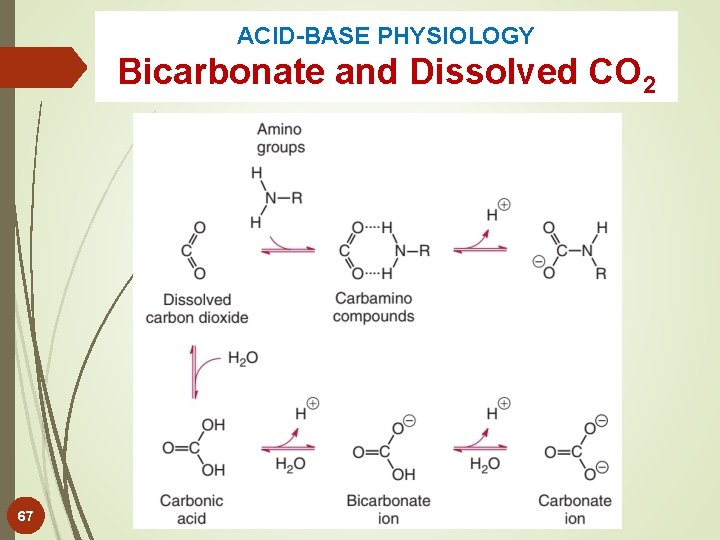
ACID-BASE PHYSIOLOGY Bicarbonate and Dissolved CO 2 Bicarbonate is the second largest fraction (behind Cl) of plasma anions. Conventionally, it is defined to include: Plasma bicarbonate ion ( HCO 3 - ), Carbonate ion ( CO 32 - ), and CO 2 bound in plasma carbamino compounds (RCNHCOOH). 66 Actual bicarbonate ion concentration is not measured in clinical laboratories. The analyte usually measured in plasma is total CO 2, which includes bicarbonate and dissolved CO 2 (d. CO 2) but is often referred to as “serum bicarb. ”
ACID-BASE PHYSIOLOGY Bicarbonate and Dissolved CO 2 67
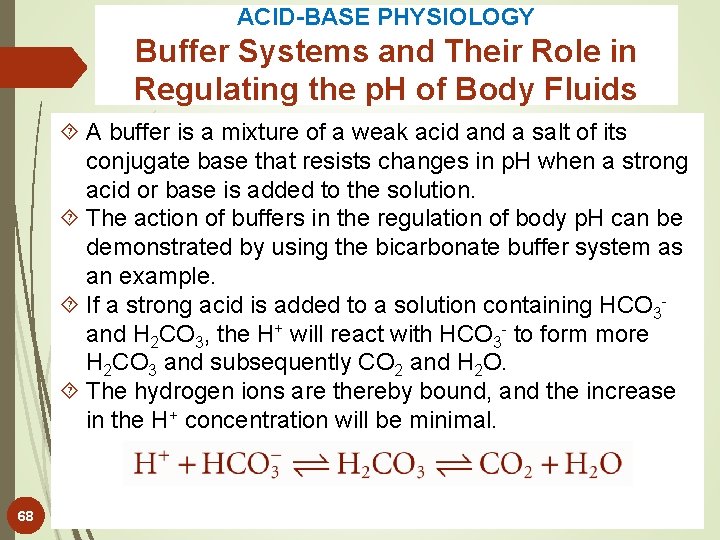
ACID-BASE PHYSIOLOGY Buffer Systems and Their Role in Regulating the p. H of Body Fluids A buffer is a mixture of a weak acid and a salt of its conjugate base that resists changes in p. H when a strong acid or base is added to the solution. The action of buffers in the regulation of body p. H can be demonstrated by using the bicarbonate buffer system as an example. If a strong acid is added to a solution containing HCO 3 - and H 2 CO 3, the H+ will react with HCO 3 - to form more H 2 CO 3 and subsequently CO 2 and H 2 O. The hydrogen ions are thereby bound, and the increase in the H+ concentration will be minimal. 68

ACID-BASE PHYSIOLOGY Buffer Systems and Their Role in Regulating the p. H of Body Fluids Bicarbonate and Carbonic Acid Buffer System Phosphate Buffer System Plasma Protein Buffer System Hemoglobin Buffer System 69
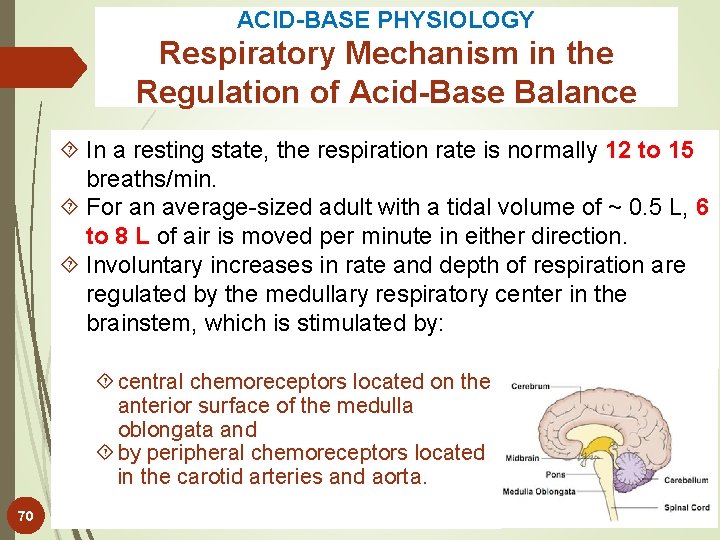
ACID-BASE PHYSIOLOGY Respiratory Mechanism in the Regulation of Acid-Base Balance In a resting state, the respiration rate is normally 12 to 15 breaths/min. For an average-sized adult with a tidal volume of ~ 0. 5 L, 6 to 8 L of air is moved per minute in either direction. Involuntary increases in rate and depth of respiration are regulated by the medullary respiratory center in the brainstem, which is stimulated by: central chemoreceptors located on the anterior surface of the medulla oblongata and by peripheral chemoreceptors located in the carotid arteries and aorta. 70
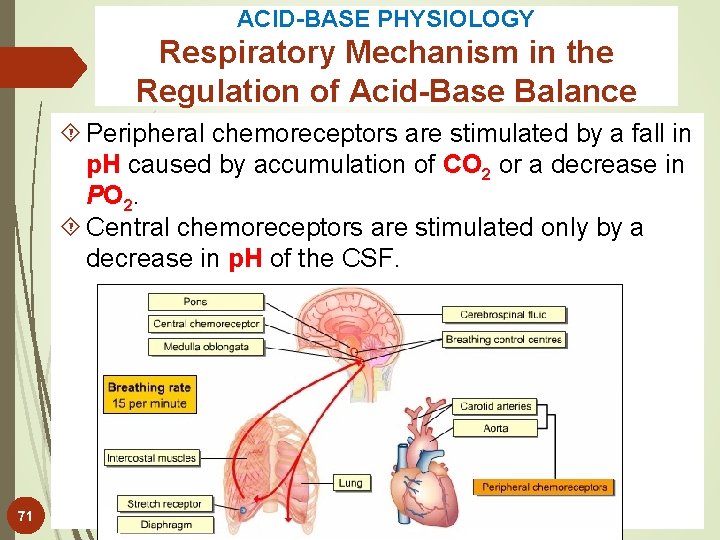
ACID-BASE PHYSIOLOGY Respiratory Mechanism in the Regulation of Acid-Base Balance Peripheral chemoreceptors are stimulated by a fall in p. H caused by accumulation of CO 2 or a decrease in PO 2. Central chemoreceptors are stimulated only by a decrease in p. H of the CSF. 71

ACID-BASE PHYSIOLOGY Respiratory Response to Acid. Base Perturbations 72 Most metabolic acid-base disorders develop slowly, within hours in diabetic ketoacidosis and months in chronic renal disease. The respiratory system responds immediately to a change in acid-base status, but several hours may be required for the response to become maximal. The maximum response is not attained until both central and peripheral chemoreceptors are fully stimulated. For example, in the early stages of metabolic acidosis, plasma p. H decreases, but because H+ ions equilibrate rather slowly across the blood-brain barrier, the p. H in CSF remains nearly normal.

ACID-BASE PHYSIOLOGY Respiratory Response to Acid. Base Perturbations However, because peripheral chemoreceptors are stimulated by decreased plasma p. H, hyperventilation occurs, and plasma PCO 2 is decreased. When this occurs, the PCO 2 of the CSF decreases immediately because CO 2 equilibrates rapidly across the blood-brain barrier, leading to a rise in p. H of the CSF that inhibits the central chemoreceptors. As plasma bicarbonate gradually falls because of acidosis, bicarbonate concentration, and p. H in the CSF will also eventually fall. At this point, stimulation of respiration becomes maximal from both central and peripheral chemoreceptors. 73
ACID-BASE PHYSIOLOGY Renal Mechanisms in the Regulation of Acid-Base Balance Various functions of the kidneys respond to different alterations in acid-base status. In the case of acidosis, excretion of acids is increased and that of base is conserved; In alkalosis, the opposite occurs. The p. H of the urine changes correspondingly and may vary in random specimens from p. H 4. 5 to 8. 0. The ability to excrete variable amounts of acid or base makes the kidney the final defense mechanism against changes in body p. H. The various acids produced during metabolic processes are buffered in the ECF at the expense of HCO 3 -. 74

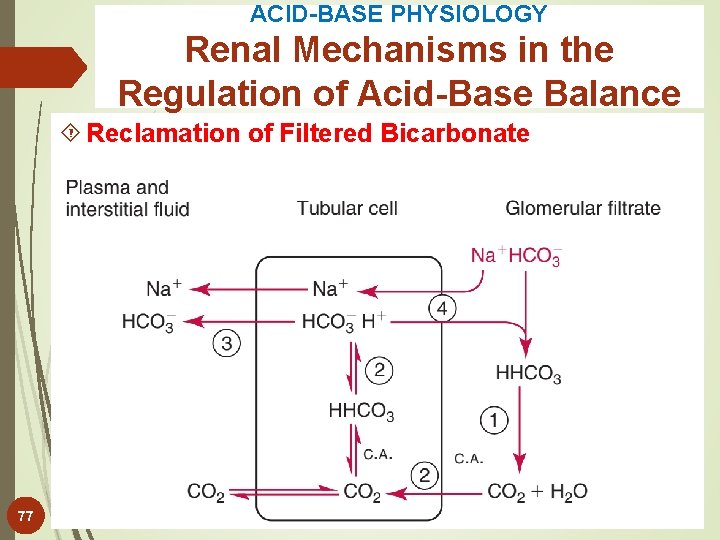
ACID-BASE PHYSIOLOGY Renal Mechanisms in the Regulation of Acid-Base Balance Renal excretion of acid and conservation of HCO 3 - occur through several mechanisms, including: Na+-H+ exchange, Production of ammonia and excretion of NH 4+ & Reclamation of HCO 3 -. 75
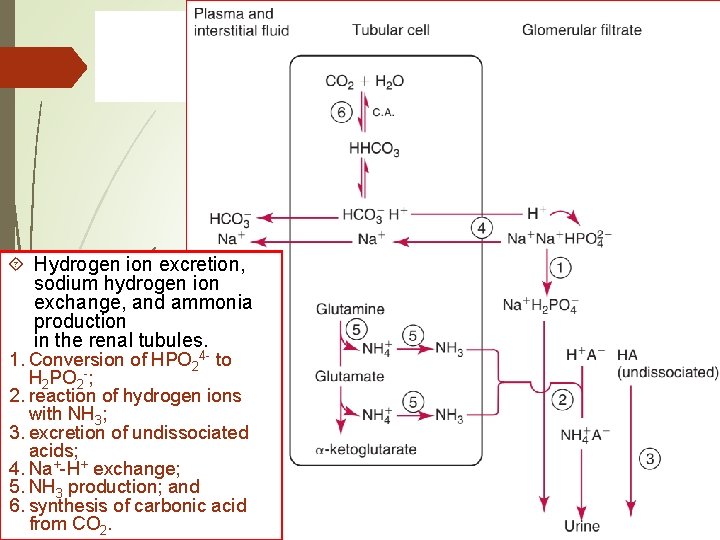
Hydrogen ion excretion, sodium hydrogen ion exchange, and ammonia production in the renal tubules. 1. Conversion of HPO 24 - to H 2 PO 2 -; 2. reaction of hydrogen ions with NH 3; 3. excretion of undissociated acids; 4. Na+-H+ exchange; 5. NH 3 production; and 6. 76 synthesis of carbonic acid from CO 2.
ACID-BASE PHYSIOLOGY Renal Mechanisms in the Regulation of Acid-Base Balance Reclamation of Filtered Bicarbonate 77
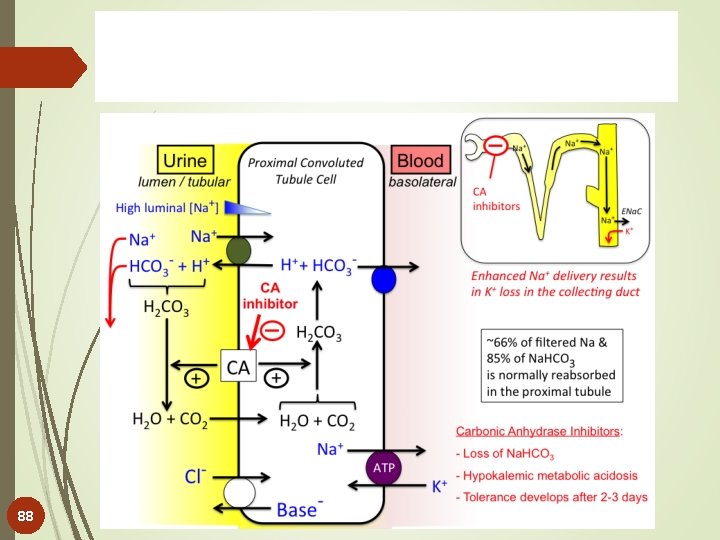
ACID-BASE PHYSIOLOGY Renal Mechanisms in the Regulation of Acid-Base Balance 78 Normally, ≈90% of filtered HCO 3 - (or ~4500 mmol/d) is reclaimed in the proximal tubule, which parallels Na+ reabsorption. Thus, for each mmol H+ secreted into the tubular fluid, 1 mmol Na+ and 1 mmol HCO 3 - enter the tubular cell and return to the general circulation. When plasma HCO 3 - concentration increases above ≈28 mmol/L, the capacity of the proximal and distal tubules to reclaim HCO 3 - is exceeded and HCO 3 - is excreted in the urine. RTA type 2 is caused by a decreased ability to reabsorb HCO 3 - in the proximal tubules, leading to a decrease in blood p. H.

ABNORMAL ACID-BASE STATUS Abnormalities in acid-base status of the blood are always accompanied by characteristic changes in electrolyte concentrations in the plasma. H+ ions cannot accumulate without concomitant accumulation of anions, such as Cl- or lactate, or without exchange for cations, such as K+ or Na+. Consequently, the electrolyte composition of blood serum or plasma is often determined along with measurements of blood gases and p. H to assess acid-base disturbances. Acid-base disturbances are traditionally classified as: Metabolic acidosis, Metabolic alkalosis, Respiratory acidosis, or Respiratory alkalosis. 79

ABNORMAL ACID-BASE STATUS Classification and Characteristics of Simple Acid-Base Disorders 80

ABNORMAL ACID-BASE STATUS Classification and Characteristics of Simple Acid-Base Disorders A logical approach to the classification of acid-base disorders is to consider that an acidosis can occur only as the result of one (or a combination) of three mechanisms: Increased addition of acid, decreased elimination of acid, and increased loss of base. Similarly, alkalosis occurs only by: increased addition of base, decreased elimination of base, and increased loss of acid. 81
ABNORMAL ACID-BASE STATUS Metabolic Acidosis (Primary Bicarbonate Deficit) Metabolic acidosis is readily detected by decreased plasma bicarbonate (or a negative extracellular base excess)—the primary perturbation in this acid-base disorder. Causes include the following: 1. Increased production of organic acids that exceeds the rate of elimination eg, production of acetoacetic acid and β-hydroxybutyric acid in diabetic ketoacidosis Bicarbonate is “lost” in the buffering of excess acid. 82 2. Reduced excretion of acids (H+) as occurs in renal failure and some RTAs, resulting in an accumulation of acid that consumes bicarbonate. 3. Excessive loss of bicarbonate secondary to increased renal excretion (decreased tubular reclamation) or excessive loss of duodenal fluid (as in diarrhea).

ABNORMAL ACID-BASE STATUS Metabolic Acidosis (Primary Bicarbonate Deficit) Plasma c. HCO 3 - falls; the fall is associated with a rise in the concentration of inorganic anions (mostly chloride) or, rarely, a concomitant fall in the sodium concentration. When any of these conditions exists, the ratio of c. HCO 3 - /CO 2 is decreased because of the primary decrease in bicarbonate. The resulting drop in p. H stimulates respiratory compensation via hyperventilation, which lowers PCO 2 in order to raise the p. H. 83

ABNORMAL ACID-BASE STATUS Metabolic Acidosis (Primary Bicarbonate Deficit) Metabolic acidosis are classified as those associated with an increased anion gap or a normal anion gap. All anion gap metabolic acidosis, besides inborn errors of metabolism, can be explained by one (or a combination) of eight underlying mechanisms listed here according to the common mnemonic device MUDPILES 84

Anion Gap Body water compartments exist in a state of electroneutrality (anions=cations) Routine measurements: Na, K, Cl & HCO 3 levels Anion Gap is the difference between unmeasured anions and unmeasured cations. Formula: AG=(Na + K)- (Cl + HCO 3) The "real" balance is given by the equation: [Na]+ [K] + [other cations] = [Cl] + [HCO 3] + [other anions] ([Na]+ [K]) - ([Cl] + [HCO 3])= [other anions] - [other cations] = "Anion Gap“ It has a reference range of 10 -20 mmol/L 85
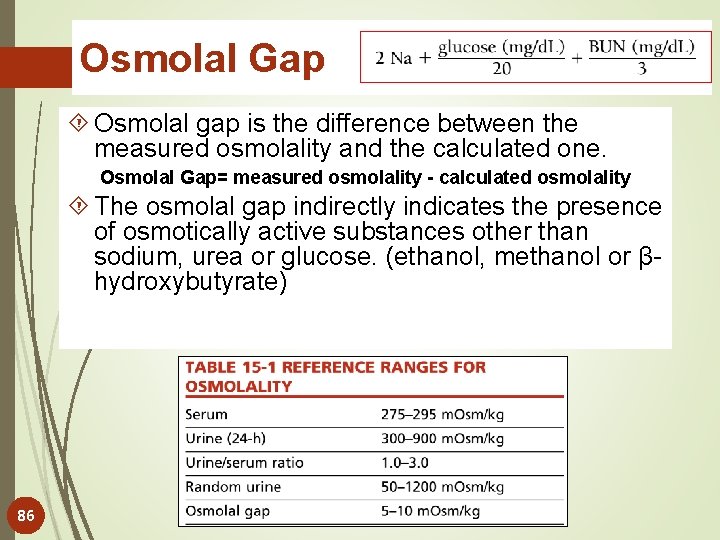
Osmolal Gap Osmolal gap is the difference between the measured osmolality and the calculated one. Osmolal Gap= measured osmolality - calculated osmolality The osmolal gap indirectly indicates the presence of osmotically active substances other than sodium, urea or glucose. (ethanol, methanol or βhydroxybutyrate) 86
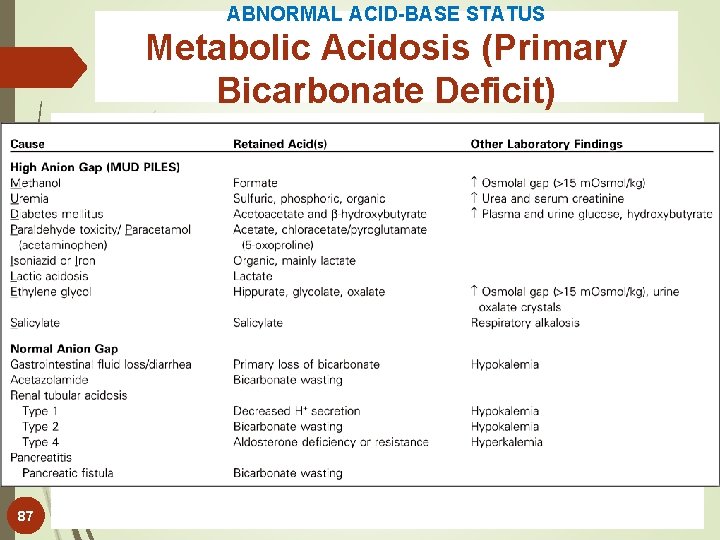
ABNORMAL ACID-BASE STATUS Metabolic Acidosis (Primary Bicarbonate Deficit) Increased Anion Gap Acidosis (Organic Acidosis) 87
88

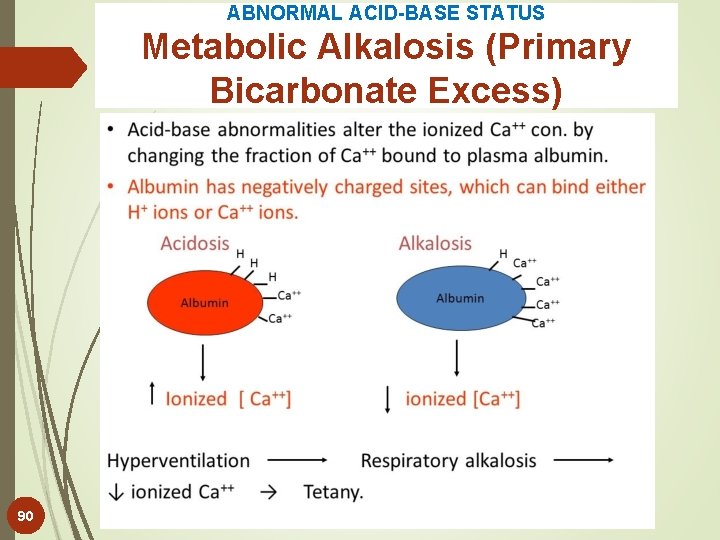
ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Alkalosis occurs when: excess base is added to the system, base elimination is decreased, or acid-rich fluids are lost. The patient will hypoventilate to raise PCO 2, thereby lowering the p. H toward normal. However, hypoxia usually prevents the patient from achieving a PCO 2 greater than 55 mm Hg. Above p. H 7. 55, tetany may develop, even in the presence of a normal serum total calcium conc. Due to a decreased concentration of ionized calcium resulting from increased binding of calcium ions by albumin. 89
ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) 90

ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Measurement of urine Cl- can be helpful becauses of metabolic alkalosis fall into: Cl- responsive, Cl- resistant, and Exogenous base categories. 91

ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Chloride-Responsive Metabolic Alkalosis Most cases of Cl--responsive metabolic alkalosis occur as a result of hypovolemia. Urine Cl- will be less than 10 mmol/L because both the available Cl- is reabsorbed with Na+, excess bicarbonate is reabsorbed in the absence of sufficient Cl- to maintain electrical neutrality. When the ECF is severely depleted, the resulting acidbase disorder is often referred to as contraction alkalosis. Urine Na+ is not useful for classifying metabolic alkalosis, because an obligatory loss of Na+ will occur when filtered HCO 3 - exceeds reclamation. 92

ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Common causes of contraction alkalosis include: prolonged vomiting or nasogastric suction, excessive loss of hydrochloric acid Pyloric or upper duodenal obstruction, and The use of certain diuretics. Treatment consists of replacing TBW with water and Na. Cl tablets or saline infusion. 93

ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Chloride-Resistant Metabolic Alkalosis In these conditions, urine Cl- will usually be greater than 20 mmol/L. This condition is far less common than Cl-responsive metabolic alkalosis and is almost always associated with an underlying disease Primary hyperaldosteronism, Cushing’s syndrome or with excess addition of exogenous base. K+ and H+ are “wasted” by the kidneys as a consequence of increased Na+ reabsorption stimulated by increased aldosterone or cortisol. The associated hypokalemia often further contributes to the alkalosis and should be treated with K+ replacement therapy. 94

ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Excessive licorice ingestion may cause a form of Cl-resistant alkalosis. Black licorice contains glycyrrhizic acid, which inhibits the enzyme 11 -β hydroxysteroid dehydrogenase, which catalyzes the conversion of cortisol to cortisone. The excess cortisol exerts a mineralocorticoid effect on the distal tubule aldosterone receptors. Conditions known collectively as Bartter’s syndrome, a rare cause of Cl--resistant metabolic alkalosis are several genetic (autosomal recessive) defects in Cl- reabsorption within the thick ascending limb of the loop of Henle. 95
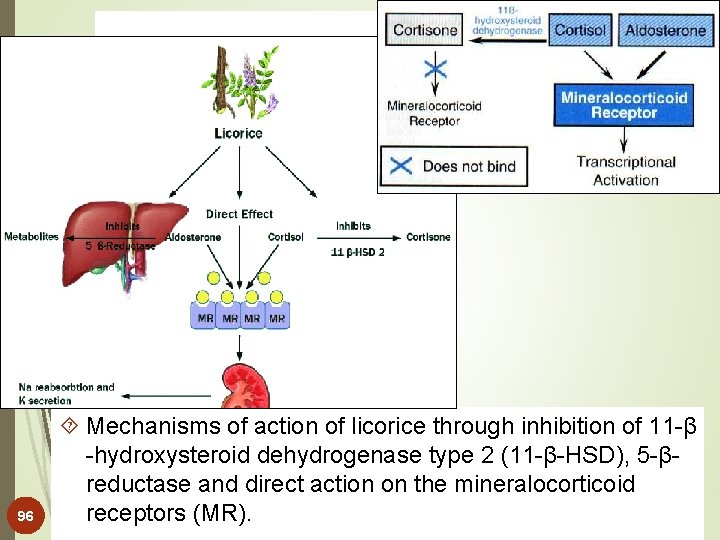
96 Mechanisms of action of licorice through inhibition of 11 -β -hydroxysteroid dehydrogenase type 2 (11 -β-HSD), 5 -βreductase and direct action on the mineralocorticoid receptors (MR).

ABNORMAL ACID-BASE STATUS Metabolic Alkalosis (Primary Bicarbonate Excess) Exogenous Base Examples in this category include: Citrate toxicity after massive blood transfusion, Aggressive intravenous therapy with bicarbonate solutions, and Ingestion of large quantities of antacids in the treatment of gastritis or peptic ulcer (milk-alkali syndrome). The latter is far less commonly seen since the introduction and now widespread use of H 2 -receptor antagonists and proton pump inhibitors. 97
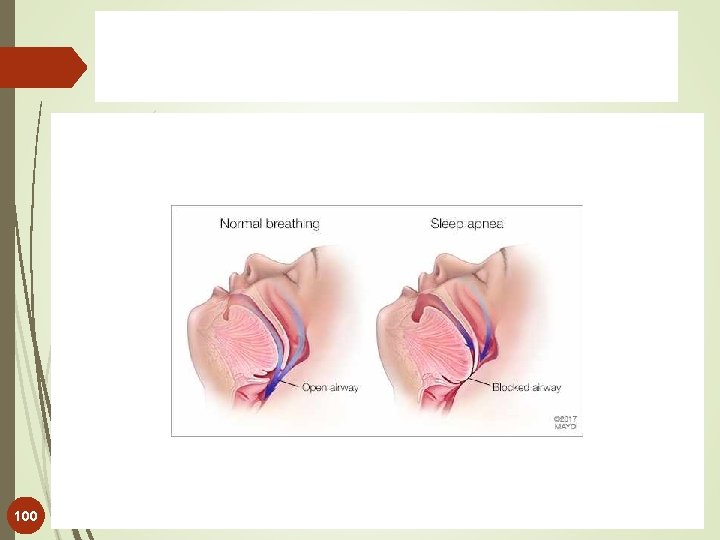
ABNORMAL ACID-BASE STATUS Respiratory Acidosis Any condition that decreases elimination of CO 2 through the lungs results in an increase in PCO 2 (hypercapnia). Thus respiratory acidosis occurs only through decreased elimination of CO 2. 98

99
100
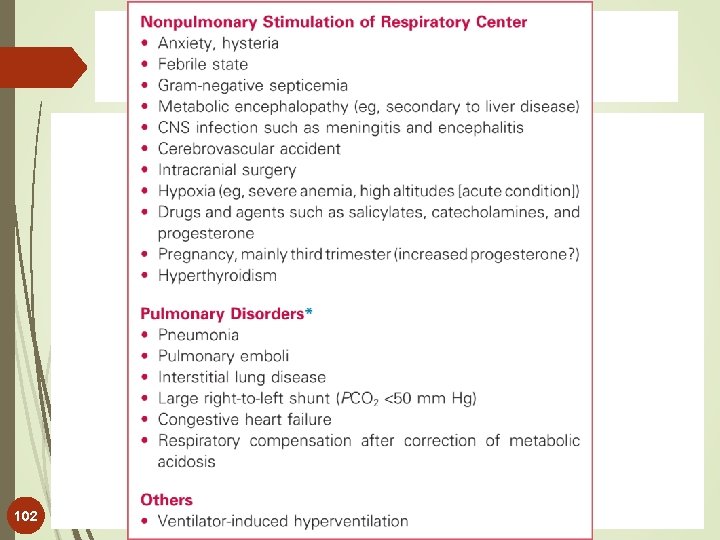
ABNORMAL ACID-BASE STATUS Respiratory Alkalosis A decrease in PCO 2 (hypocapnia) and the resulting primary deficit in c. CO 2 (respiratory alkalosis) are caused by an increased rate and/or depth of respiration. Therefore the basic cause of respiratory alkalosis is excess elimination of acid by the respiratory route. Excessive elimination of CO 2 reduces the PCO 2 and causes an increase in the c. HCO 3 - / c. CO 2 ratio. The latter shifts the normal equilibrium of the bicarbonate/carbonic acid buffer system, reducing the hydrogen ion concentration and increasing the p. H. 101
102

103 Case Studies Acid Base Balance

Case 1 A 2 -year-old baby with a suspected gastrointestinal infection presented to the Emergency Department (ED) with a recent history of diarrhea. Routine chemistry results in blood were as follows: 104

Case 1 Comments These are typical findings observed in severe, acute gastroenteritis. The diarrhea has resulted in the gastrointestinal loss of sodium, potassium, and bicarbonate. The loss of bicarbonate is compensated by an increase in chloride concentration, resulting in normal anion gap metabolic acidosis (hyperchloremic acidosis). Although the chloride concentration observed in this patient is within the reference interval, it is actually increased relative to the sodium concentration. Fluid secreted into the gut lumen contains higher amounts of sodium than chloride. 105
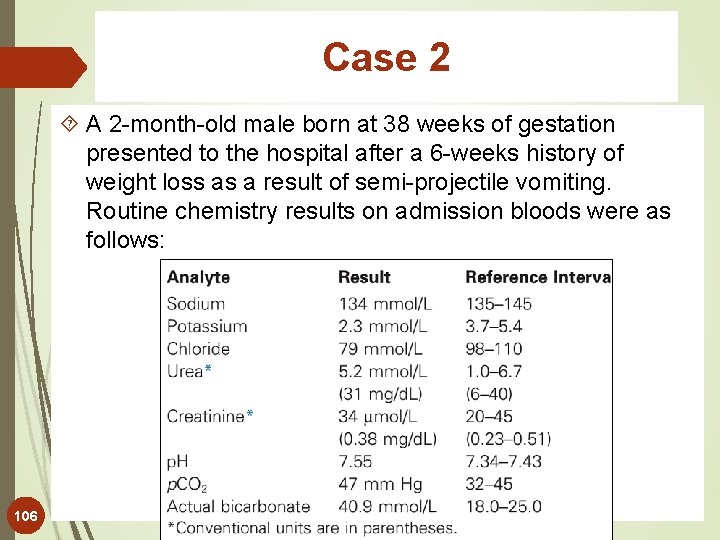
Case 2 A 2 -month-old male born at 38 weeks of gestation presented to the hospital after a 6 -weeks history of weight loss as a result of semi-projectile vomiting. Routine chemistry results on admission bloods were as follows: 106
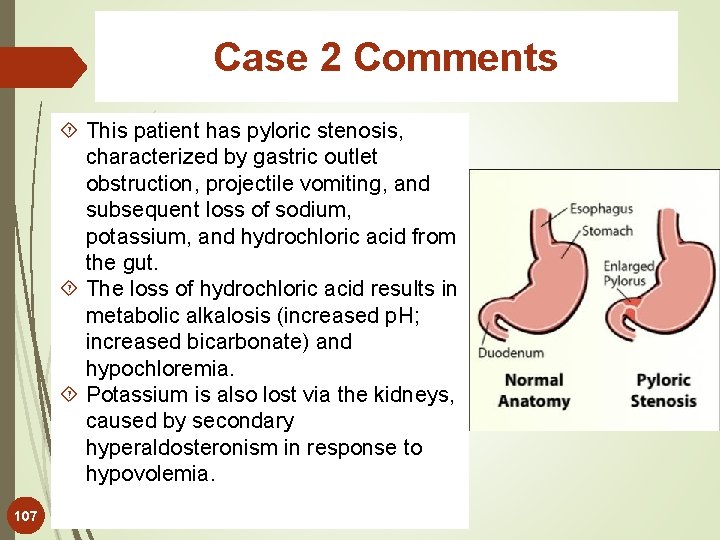
Case 2 Comments This patient has pyloric stenosis, characterized by gastric outlet obstruction, projectile vomiting, and subsequent loss of sodium, potassium, and hydrochloric acid from the gut. The loss of hydrochloric acid results in metabolic alkalosis (increased p. H; increased bicarbonate) and hypochloremia. Potassium is also lost via the kidneys, caused by secondary hyperaldosteronism in response to hypovolemia. 107

Case 2 Comments Aldosterone promotes the reabsorption of sodium ions in the distal convoluted tubules in exchange for either potassium or hydrogen ions, which are excreted. In addition, metabolic alkalosis tends toward hypokalemia, the result in part of transcellular shifting of potassium ions into the intracellular compartment. In this particular case, the history of vomiting is unusually long, causing severe metabolic alkalosis and hypokalemia. 108

Pyloric stenosis (also called infantile hypertrophic pyloric stenosis) is a type of gastric outlet obstruction, which means a blockage from the stomach to the intestines. Pyloric stenosis affects about 3 out of 1, 000 babies in the United States. Runs in families — if a parent had pyloric stenosis, then a baby has up to a 20% risk of developing it. Most infants who have it develop symptoms 3 to 5 weeks after birth. 109

Pyloric stenosis It's thought that babies who develop pyloric stenosis are not born with it, but have progressive thickening of the pylorus after birth. A baby will start to show symptoms when the pylorus is so thick that the stomach can't empty properly. The cause of this thickening isn't clear. It might be a combination of several things; for example: use of erythromycin (an antibiotic) in babies in the first 2 weeks of life or antibiotics given to mothers at the end of pregnancy or during breastfeeding can be associated with pyloric stenosis. 110

Case 3 A young woman was admitted in a confused and restless condition. History taking was not easy, but it seemed that she had been becoming progressively unwell over the preceding week or two. Acid–base analysis was performed and results were as follows: 111
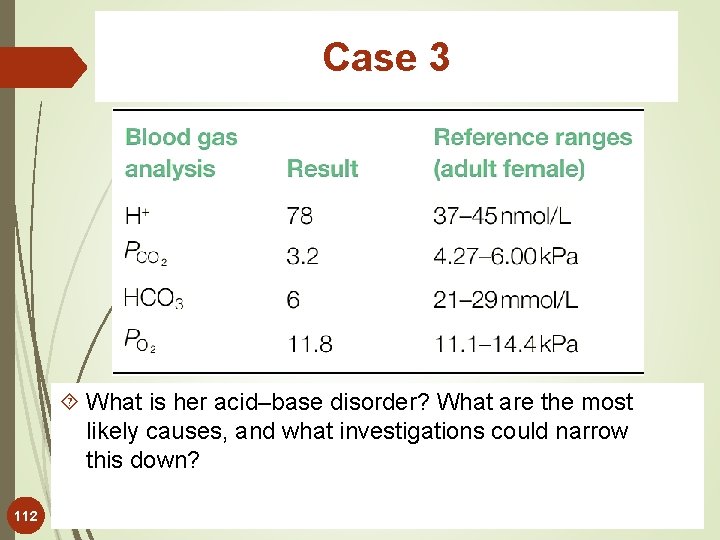
Case 3 What is her acid–base disorder? What are the most likely causes, and what investigations could narrow this down? 112

Case 3 She has a metabolic acidosis. Despite the long list of possible causes of metabolic acidosis, the most common causes are relatively few, and are DKA, renal failure, salicylate overdose and lactic acidosis. Usually these can be differentiated on the basis of the history; by measuring urea and electrolytes (U&Es) and glucose (and salicylate if indicated); and performing urinalysis (using a dipstick, and looking especially for ketones). Lactate can also be measured if required, but is often not necessary. This woman was a newly presenting type 1 diabetic. 113
- Slides: 112