
Development of the Heart Development of primitive heart






- Slides: 63
Development of the Heart
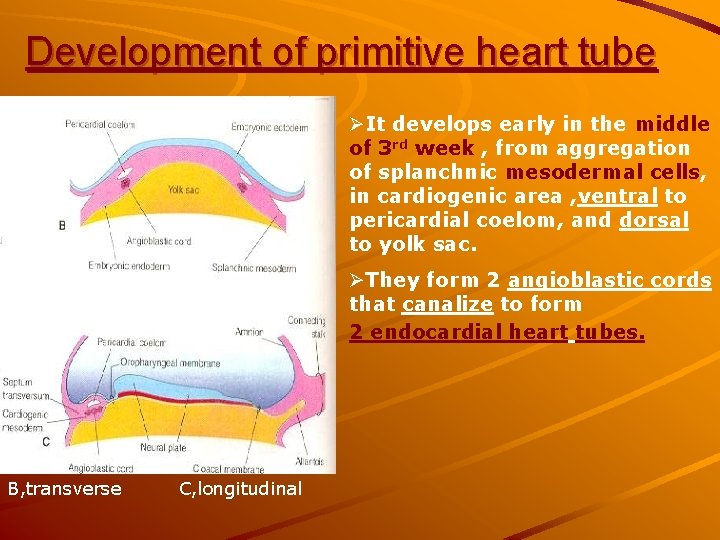
Development of primitive heart tube ØIt develops early in the middle of 3 rd week , from aggregation of splanchnic mesodermal cells, in cardiogenic area , ventral to pericardial coelom, and dorsal to yolk sac. ØThey form 2 angioblastic cords that canalize to form 2 endocardial heart tubes. B, transverse C, longitudinal
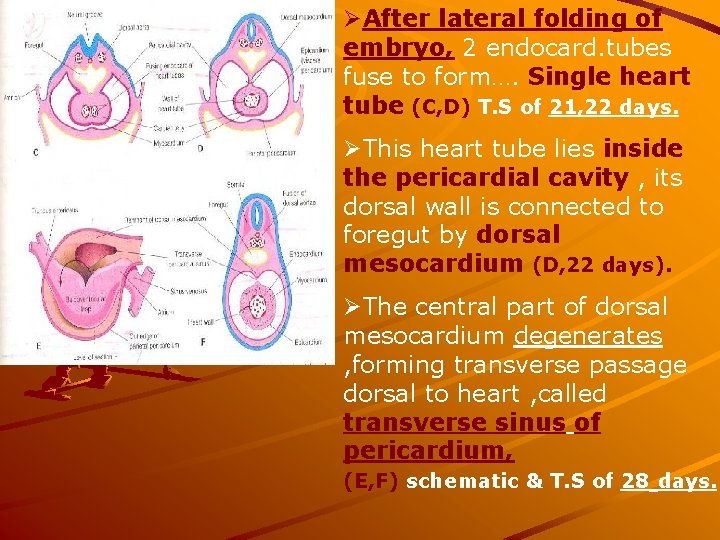
ØAfter lateral folding of embryo, 2 endocard. tubes fuse to form…. Single heart tube (C, D) T. S of 21, 22 days. ØThis heart tube lies inside the pericardial cavity , its dorsal wall is connected to foregut by dorsal mesocardium (D, 22 days). ØThe central part of dorsal mesocardium degenerates , forming transverse passage dorsal to heart , called transverse sinus of pericardium, (E, F) schematic & T. S of 28 days.
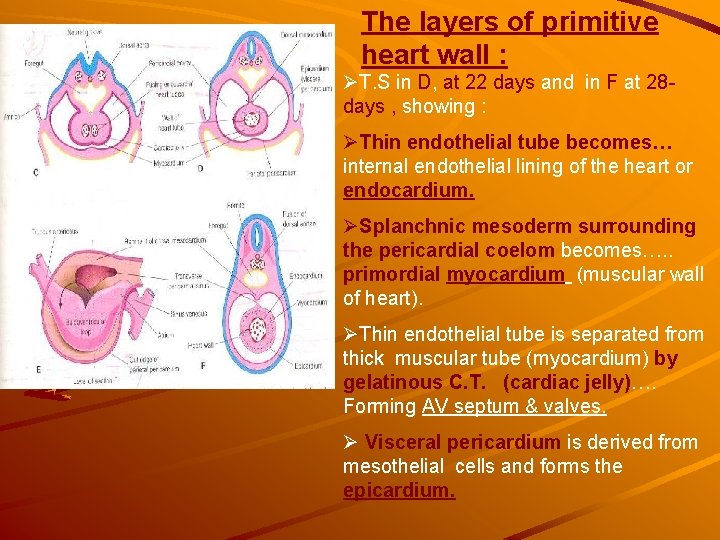
The layers of primitive heart wall : ØT. S in D, at 22 days and in F at 28 days , showing : ØThin endothelial tube becomes… internal endothelial lining of the heart or endocardium. ØSplanchnic mesoderm surrounding the pericardial coelom becomes…. . primordial myocardium (muscular wall of heart). ØThin endothelial tube is separated from thick muscular tube (myocardium) by gelatinous C. T. (cardiac jelly)…. Forming AV septum & valves. Ø Visceral pericardium is derived from mesothelial cells and forms the epicardium.
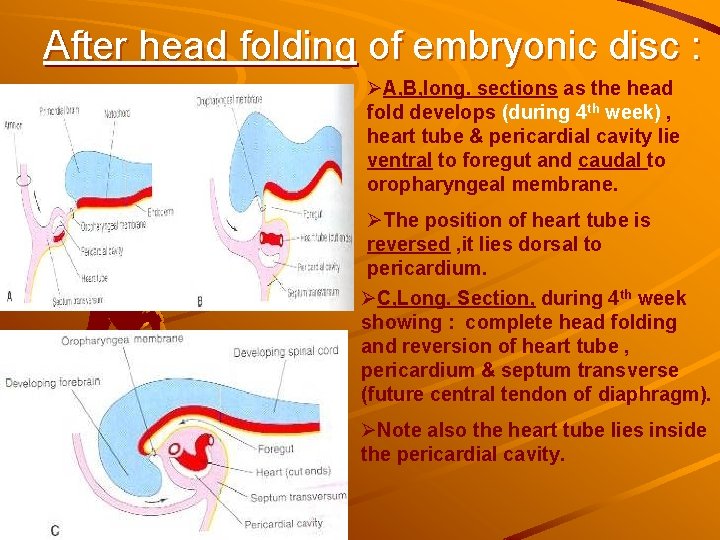
After head folding of embryonic disc : ØA, B, long. sections as the head fold develops (during 4 th week) , heart tube & pericardial cavity lie ventral to foregut and caudal to oropharyngeal membrane. ØThe position of heart tube is reversed , it lies dorsal to pericardium. ØC, Long. Section, during 4 th week showing : complete head folding and reversion of heart tube , pericardium & septum transverse (future central tendon of diaphragm). ØNote also the heart tube lies inside the pericardial cavity.
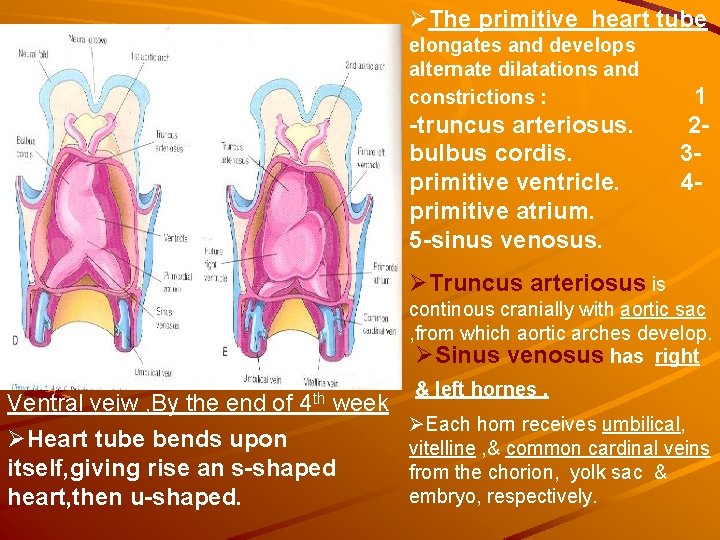
ØThe primitive heart tube elongates and develops alternate dilatations and constrictions : -truncus arteriosus. bulbus cordis. primitive ventricle. primitive atrium. 5 -sinus venosus. 1 234 - ØTruncus arteriosus is continous cranially with aortic sac , from which aortic arches develop. ØSinus venosus has right 4 th Ventral veiw , By the end of week ØHeart tube bends upon itself, giving rise an s-shaped heart, then u-shaped. & left hornes. ØEach horn receives umbilical, vitelline , & common cardinal veins from the chorion, yolk sac & embryo, respectively.
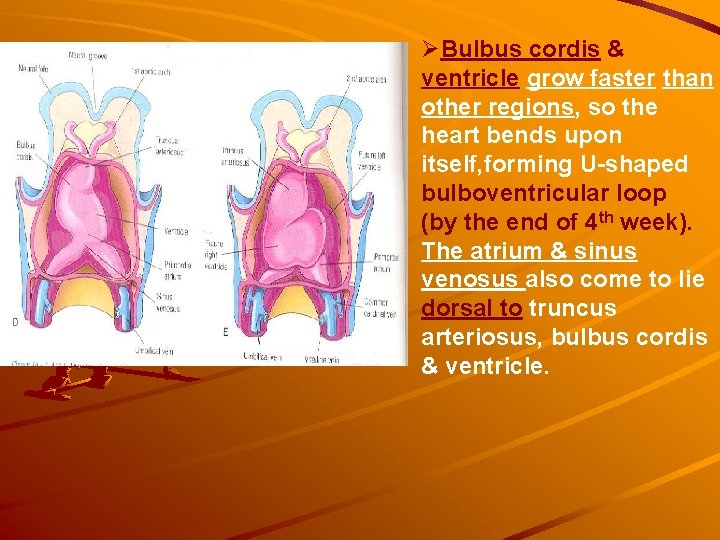
ØBulbus cordis & ventricle grow faster than other regions, so the heart bends upon itself, forming U-shaped bulboventricular loop (by the end of 4 th week). The atrium & sinus venosus also come to lie dorsal to truncus arteriosus, bulbus cordis & ventricle.
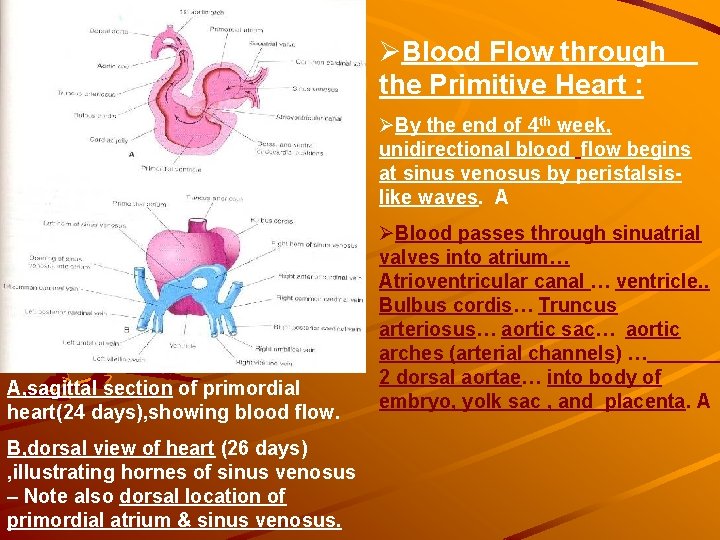
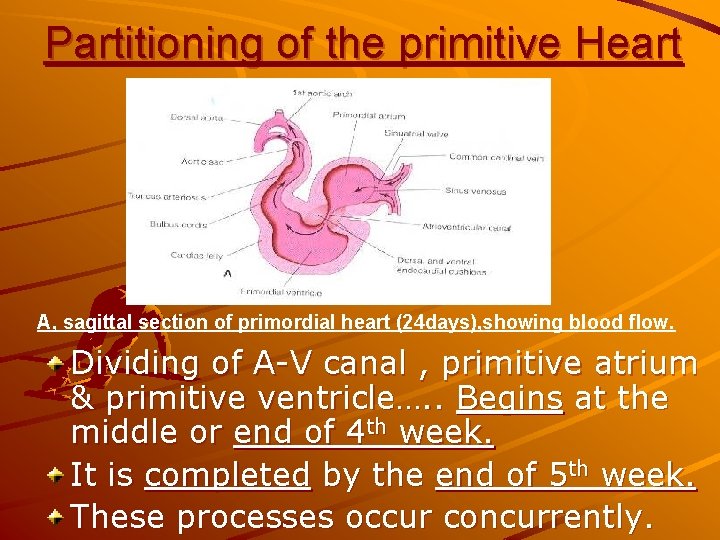
ØBlood Flow through the Primitive Heart : ØBy the end of 4 th week, unidirectional blood flow begins at sinus venosus by peristalsislike waves. A A, sagittal section of primordial heart(24 days), showing blood flow. B, dorsal view of heart (26 days) , illustrating hornes of sinus venosus – Note also dorsal location of primordial atrium & sinus venosus. ØBlood passes through sinuatrial valves into atrium… Atrioventricular canal … ventricle. . Bulbus cordis… Truncus arteriosus… aortic sac… aortic arches (arterial channels) … 2 dorsal aortae… into body of embryo, yolk sac , and placenta. A
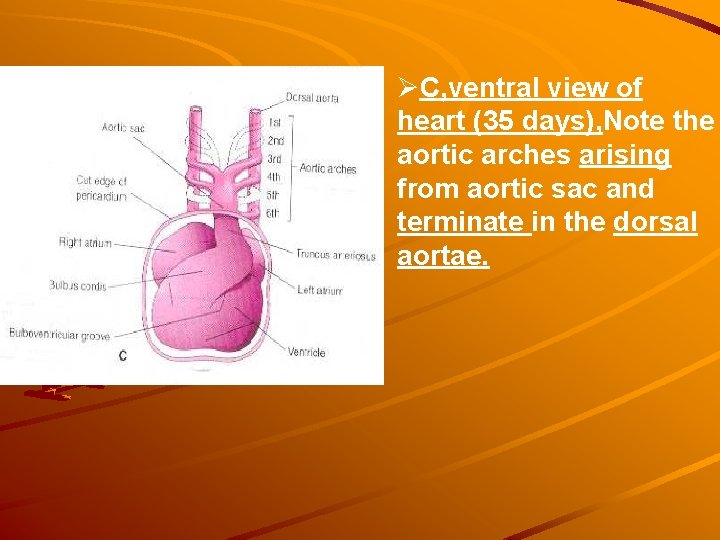
ØC, ventral view of heart (35 days), Note the aortic arches arising from aortic sac and terminate in the dorsal aortae.
Partitioning of the primitive Heart A, sagittal section of primordial heart (24 days), showing blood flow. Dividing of A-V canal , primitive atrium & primitive ventricle…. . Begins at the middle or end of 4 th week. It is completed by the end of 5 th week. These processes occur concurrently.
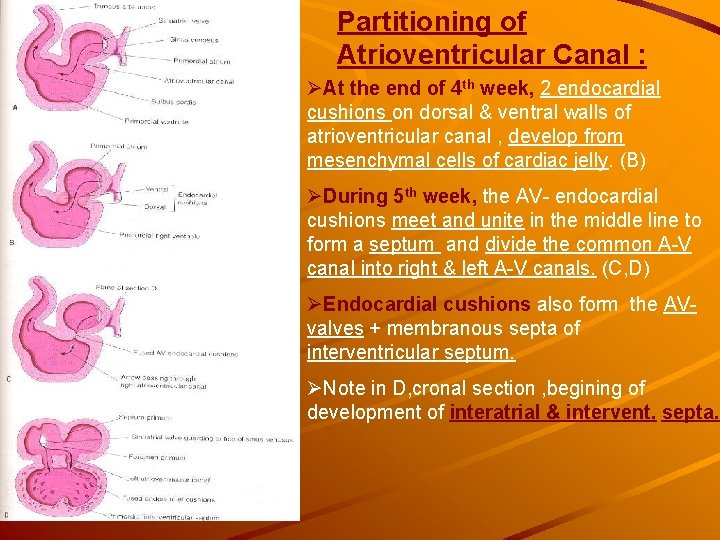
Partitioning of Atrioventricular Canal : ØAt the end of 4 th week, 2 endocardial cushions on dorsal & ventral walls of atrioventricular canal , develop from mesenchymal cells of cardiac jelly. (B) ØDuring 5 th week, the AV- endocardial cushions meet and unite in the middle line to form a septum and divide the common A-V canal into right & left A-V canals. (C, D) ØEndocardial cushions also form the AVvalves + membranous septa of interventricular septum. ØNote in D, cronal section , begining of development of interatrial & intervent. septa.
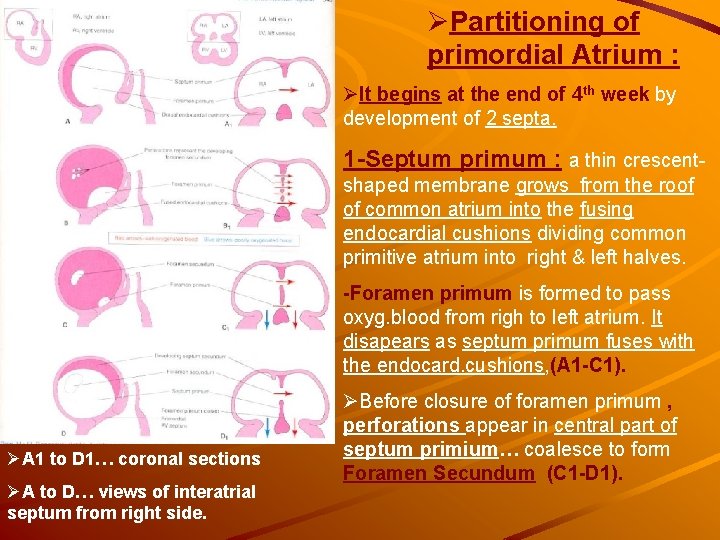
ØPartitioning of primordial Atrium : ØIt begins at the end of 4 th week by development of 2 septa. 1 -Septum primum : a thin crescentshaped membrane grows from the roof of common atrium into the fusing endocardial cushions dividing common primitive atrium into right & left halves. -Foramen primum is formed to pass oxyg. blood from righ to left atrium. It disapears as septum primum fuses with the endocard. cushions, (A 1 -C 1). ØA 1 to D 1… coronal sections ØA to D… views of interatrial septum from right side. ØBefore closure of foramen primum , perforations appear in central part of septum primium… coalesce to form Foramen Secundum (C 1 -D 1).
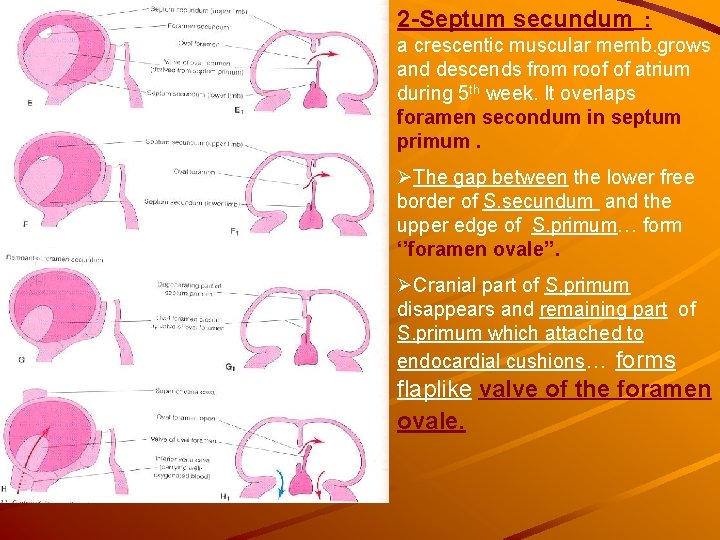
2 -Septum secundum : a crescentic muscular memb. grows and descends from roof of atrium during 5 th week. It overlaps foramen secondum in septum primum. ØThe gap between the lower free border of S. secundum and the upper edge of S. primum… form ‘’foramen ovale’’. ØCranial part of S. primum disappears and remaining part of S. primum which attached to endocardial cushions… forms flaplike valve of the foramen ovale.
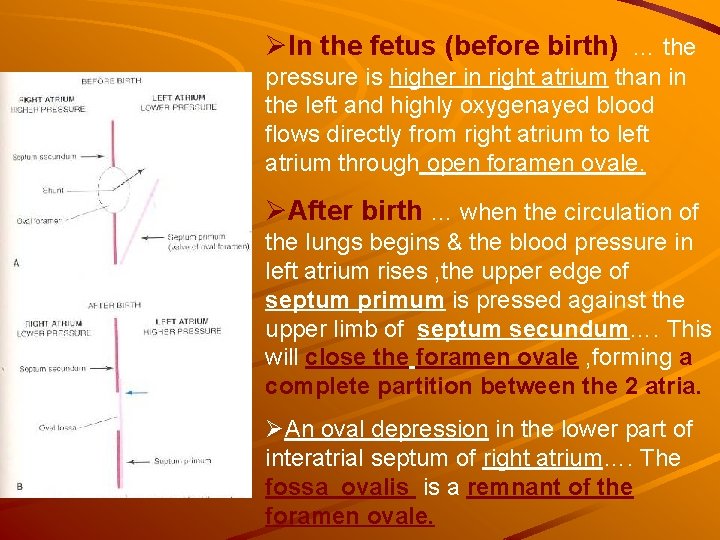
ØIn the fetus (before birth) … the pressure is higher in right atrium than in the left and highly oxygenayed blood flows directly from right atrium to left atrium through open foramen ovale. ØAfter birth … when the circulation of the lungs begins & the blood pressure in left atrium rises , the upper edge of septum primum is pressed against the upper limb of septum secundum…. This will close the foramen ovale , forming a complete partition between the 2 atria. ØAn oval depression in the lower part of interatrial septum of right atrium…. The fossa ovalis is a remnant of the foramen ovale.
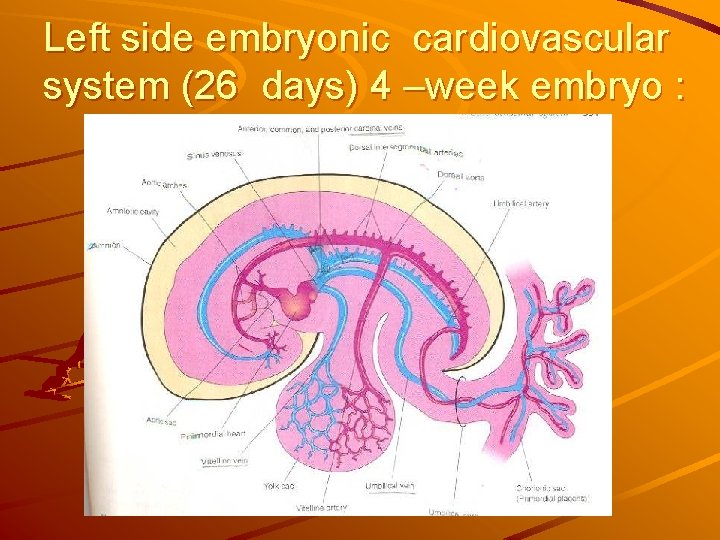
Left side embryonic cardiovascular system (26 days) 4 –week embryo :
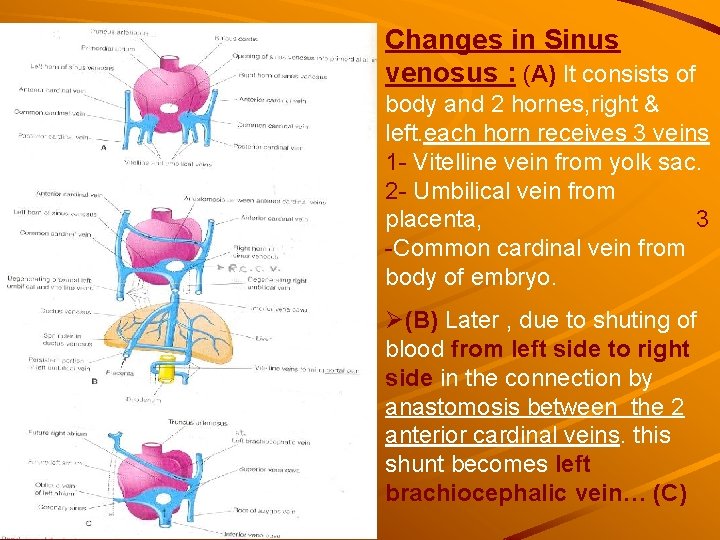
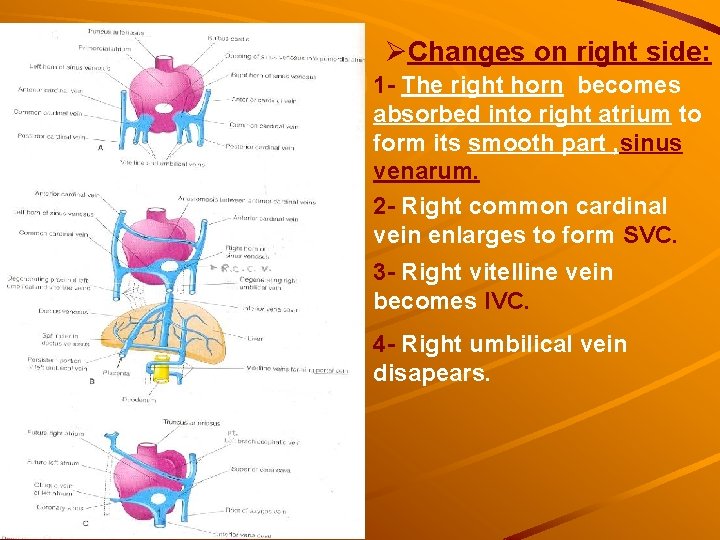
Changes in Sinus venosus : (A) It consists of body and 2 hornes, right & left. each horn receives 3 veins 1 - Vitelline vein from yolk sac. 2 - Umbilical vein from placenta, 3 -Common cardinal vein from body of embryo. Ø(B) Later , due to shuting of blood from left side to right side in the connection by anastomosis between the 2 anterior cardinal veins. this shunt becomes left brachiocephalic vein… (C)
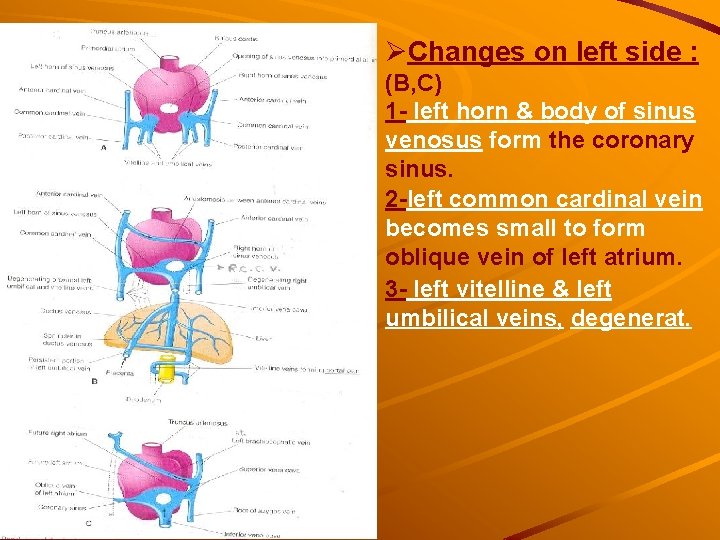
ØChanges on left side : (B, C) 1 - left horn & body of sinus venosus form the coronary sinus. 2 -left common cardinal vein becomes small to form oblique vein of left atrium. 3 - left vitelline & left umbilical veins, degenerat.
ØChanges on right side: 1 - The right horn becomes absorbed into right atrium to form its smooth part , sinus venarum. 2 - Right common cardinal vein enlarges to form SVC. 3 - Right vitelline vein becomes IVC. 4 - Right umbilical vein disapears.
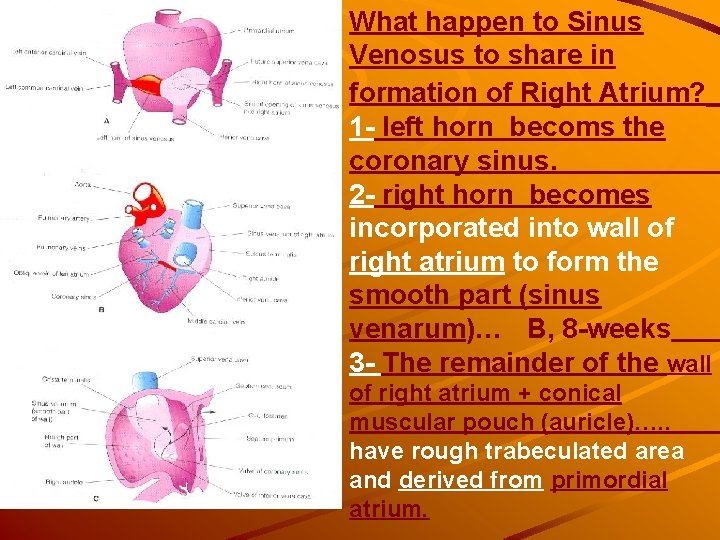
What happen to Sinus Venosus to share in formation of Right Atrium? 1 - left horn becoms the coronary sinus. 2 - right horn becomes incorporated into wall of right atrium to form the smooth part (sinus venarum)… B, 8 -weeks 3 - The remainder of the wall of right atrium + conical muscular pouch (auricle)…. . have rough trabeculated area and derived from primordial atrium.
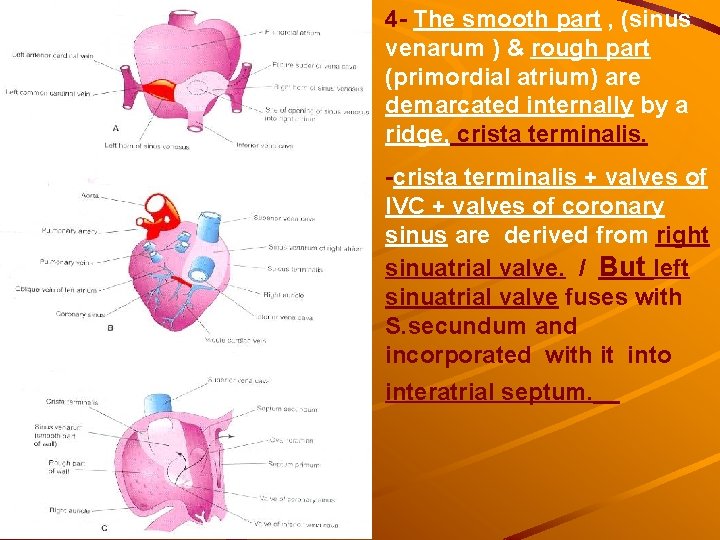
4 - The smooth part , (sinus venarum ) & rough part (primordial atrium) are demarcated internally by a ridge, crista terminalis. -crista terminalis + valves of IVC + valves of coronary sinus are derived from right sinuatrial valve. / But left sinuatrial valve fuses with S. secundum and incorporated with it into interatrial septum.
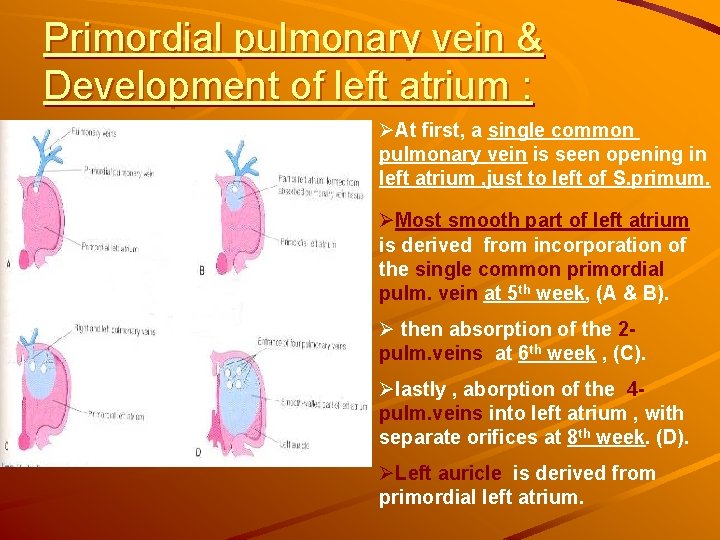
Primordial pulmonary vein & Development of left atrium : ØAt first, a single common pulmonary vein is seen opening in left atrium , just to left of S. primum. ØMost smooth part of left atrium is derived from incorporation of the single common primordial pulm. vein at 5 th week, (A & B). Ø then absorption of the 2 pulm. veins at 6 th week , (C). Ølastly , aborption of the 4 pulm. veins into left atrium , with separate orifices at 8 th week. (D). ØLeft auricle is derived from primordial left atrium.
Embryological origin of the definitive atrium: Right Atrium Left Atrium 1 -Its rough part + auricle from Right ½ of primitive atrium. 1 - Its rough part +auricle from left ½ of primitive atrium. 2 -right ½ of A-V canal. 2 - left ½ of A-V canal. 3 - Its smooth part from Absorbed right horn of sinus venosus. 3 - Its smooth part from Absorbed part of pulmonary veins.
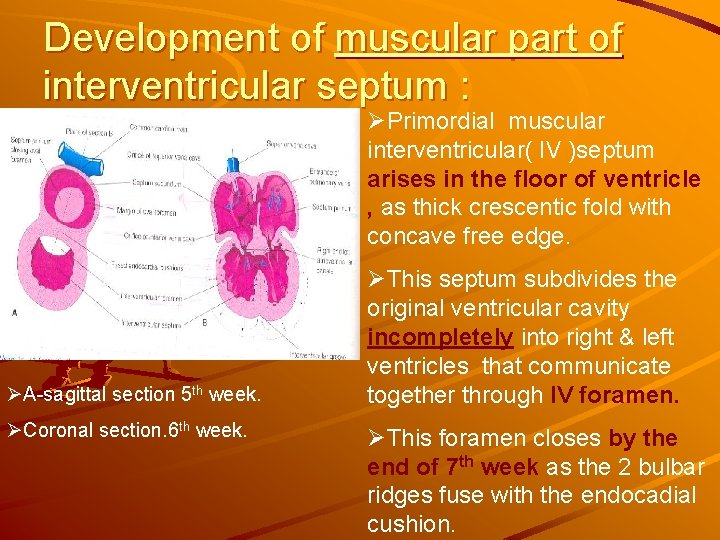
Development of muscular part of interventricular septum : ØPrimordial muscular interventricular( IV )septum arises in the floor of ventricle , as thick crescentic fold with concave free edge. ØA-sagittal section 5 th week. ØCoronal section. 6 th week. ØThis septum subdivides the original ventricular cavity incompletely into right & left ventricles that communicate together through IV foramen. ØThis foramen closes by the end of 7 th week as the 2 bulbar ridges fuse with the endocadial cushion.
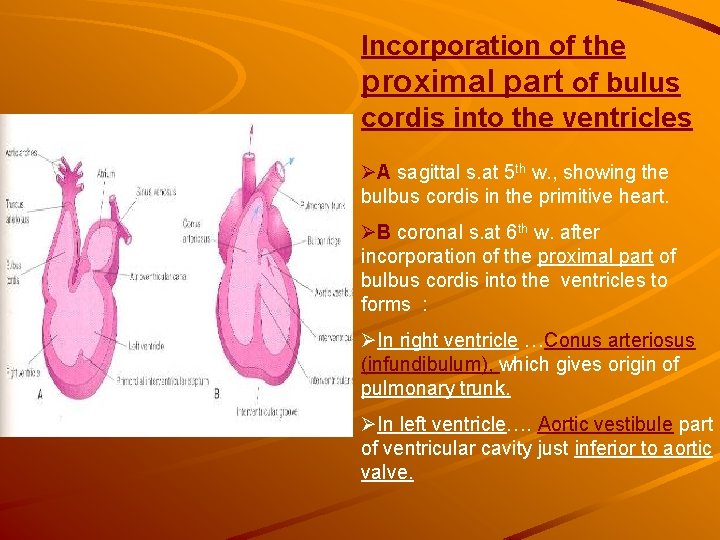
Incorporation of the proximal part of bulus cordis into the ventricles ØA sagittal s. at 5 th w. , showing the bulbus cordis in the primitive heart. ØB coronal s. at 6 th w. after incorporation of the proximal part of bulbus cordis into the ventricles to forms : ØIn right ventricle …Conus arteriosus (infundibulum), which gives origin of pulmonary trunk. ØIn left ventricle…. Aortic vestibule part of ventricular cavity just inferior to aortic valve.
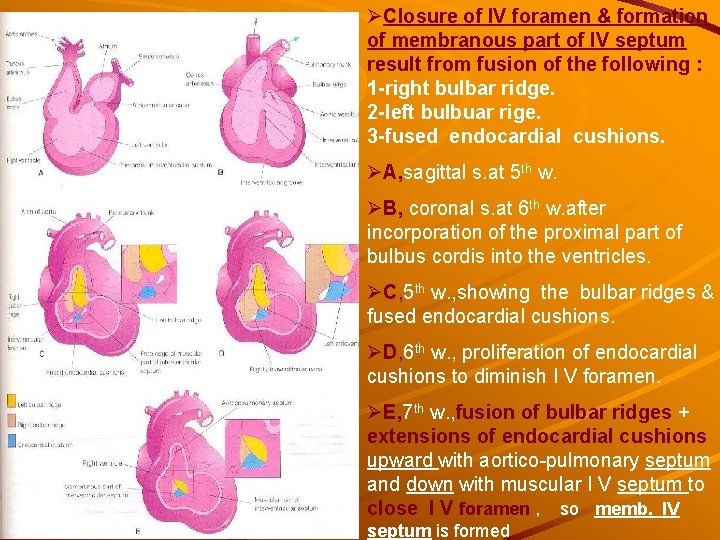
ØClosure of IV foramen & formation of membranous part of IV septum result from fusion of the following : 1 -right bulbar ridge. 2 -left bulbuar rige. 3 -fused endocardial cushions. ØA, sagittal s. at 5 th w. ØB, coronal s. at 6 th w. after incorporation of the proximal part of bulbus cordis into the ventricles. ØC, 5 th w. , showing the bulbar ridges & fused endocardial cushions. ØD, 6 th w. , proliferation of endocardial cushions to diminish I V foramen. ØE, 7 th w. , fusion of bulbar ridges + extensions of endocardial cushions upward with aortico-pulmonary septum and down with muscular I V septum to close I V foramen , so memb. IV septum is formed
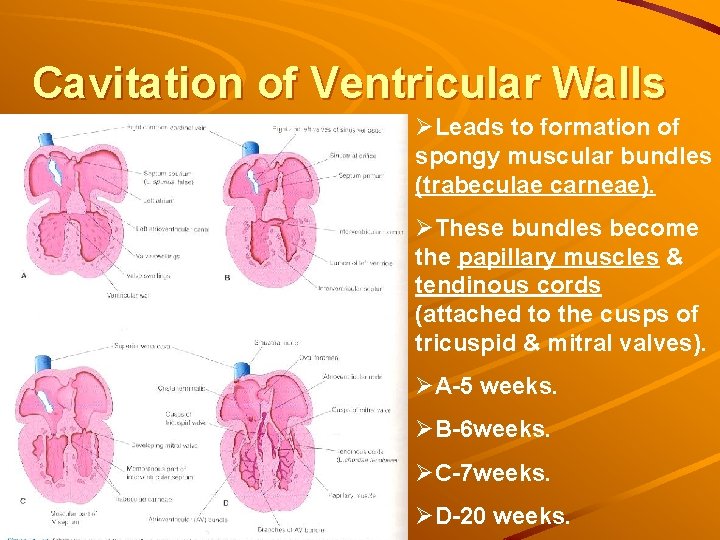
Cavitation of Ventricular Walls ØLeads to formation of spongy muscular bundles (trabeculae carneae). ØThese bundles become the papillary muscles & tendinous cords (attached to the cusps of tricuspid & mitral valves). ØA-5 weeks. ØB-6 weeks. ØC-7 weeks. ØD-20 weeks.
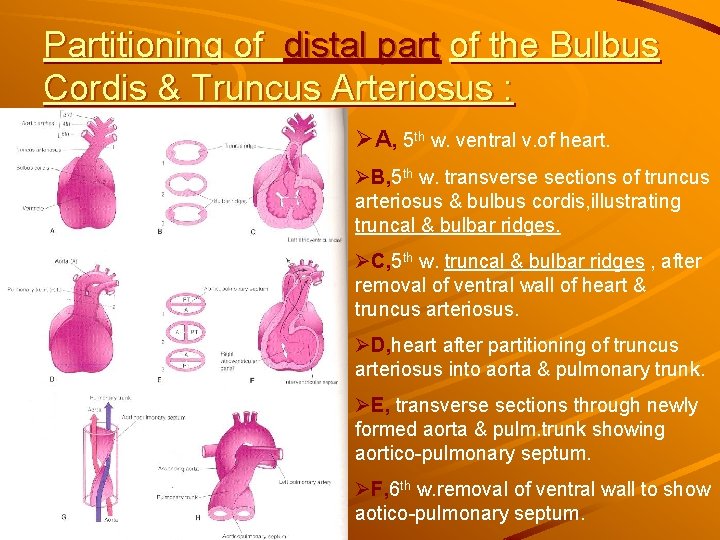
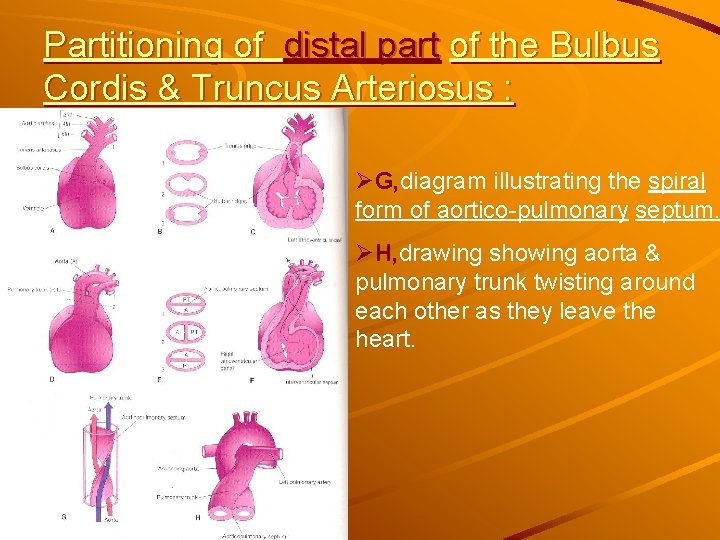
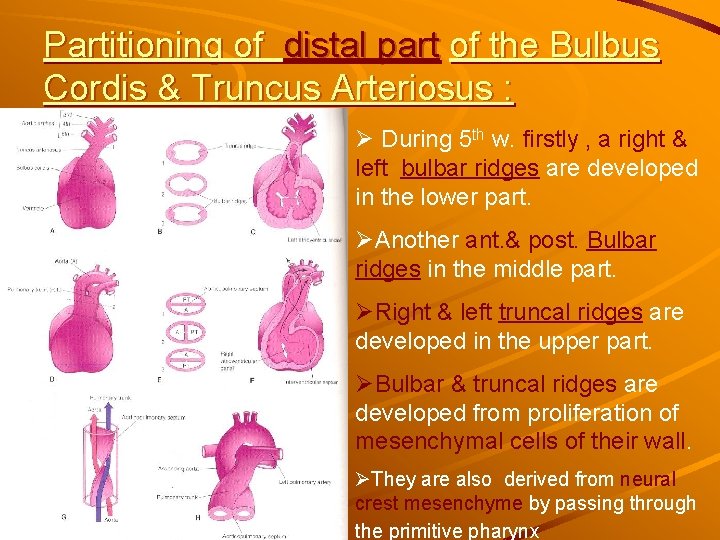
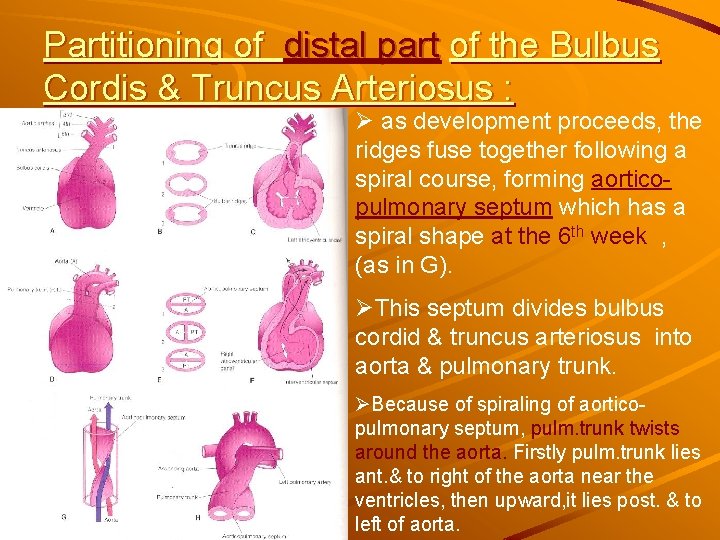
Partitioning of distal part of the Bulbus Cordis & Truncus Arteriosus : ØA, 5 th w. ventral v. of heart. ØB, 5 th w. transverse sections of truncus arteriosus & bulbus cordis, illustrating truncal & bulbar ridges. ØC, 5 th w. truncal & bulbar ridges , after removal of ventral wall of heart & truncus arteriosus. ØD, heart after partitioning of truncus arteriosus into aorta & pulmonary trunk. ØE, transverse sections through newly formed aorta & pulm. trunk showing aortico-pulmonary septum. ØF, 6 th w. removal of ventral wall to show aotico-pulmonary septum.
Partitioning of distal part of the Bulbus Cordis & Truncus Arteriosus : ØG, diagram illustrating the spiral form of aortico-pulmonary septum. ØH, drawing showing aorta & pulmonary trunk twisting around each other as they leave the heart.
Partitioning of distal part of the Bulbus Cordis & Truncus Arteriosus : Ø During 5 th w. firstly , a right & left bulbar ridges are developed in the lower part. ØAnother ant. & post. Bulbar ridges in the middle part. ØRight & left truncal ridges are developed in the upper part. ØBulbar & truncal ridges are developed from proliferation of mesenchymal cells of their wall. ØThey are also derived from neural crest mesenchyme by passing through the primitive pharynx
Partitioning of distal part of the Bulbus Cordis & Truncus Arteriosus : Ø as development proceeds, the ridges fuse together following a spiral course, forming aorticopulmonary septum which has a spiral shape at the 6 th week , (as in G). ØThis septum divides bulbus cordid & truncus arteriosus into aorta & pulmonary trunk. ØBecause of spiraling of aorticopulmonary septum, pulm. trunk twists around the aorta. Firstly pulm. trunk lies ant. & to right of the aorta near the ventricles, then upward, it lies post. & to left of aorta.
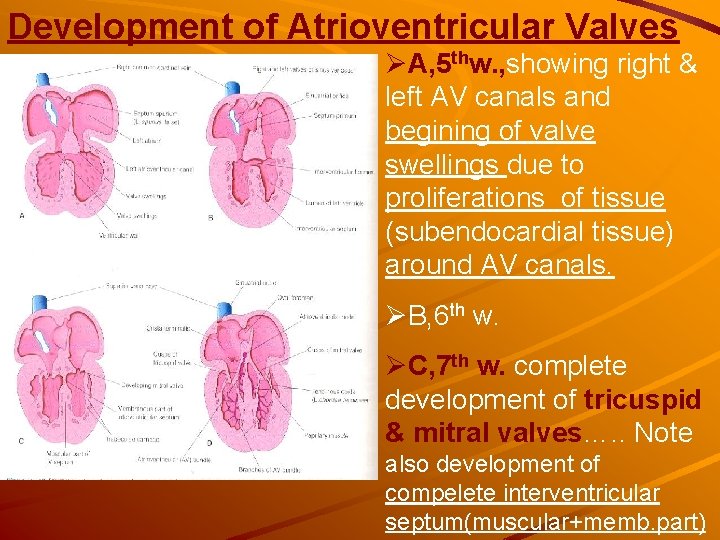
Development of Atrioventricular Valves ØA, 5 thw. , showing right & left AV canals and begining of valve swellings due to proliferations of tissue (subendocardial tissue) around AV canals. ØB, 6 th w. ØC, 7 th w. complete development of tricuspid & mitral valves…. . Note also development of compelete interventricular septum(muscular+memb. part)
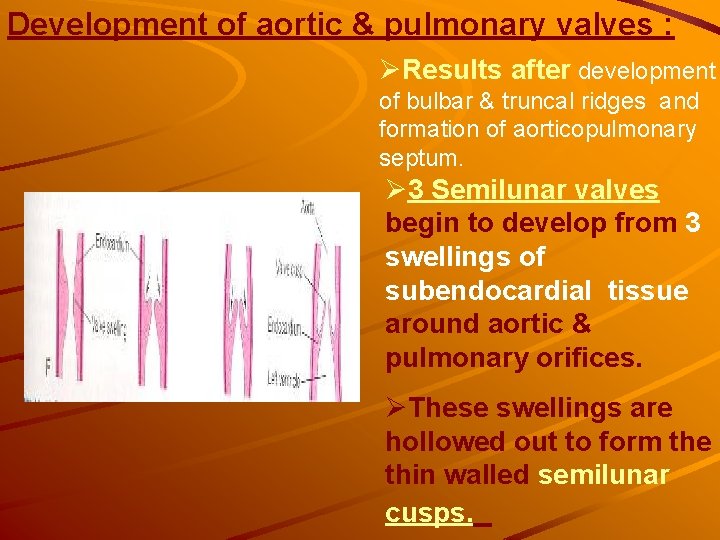
Development of aortic & pulmonary valves : ØResults after development of bulbar & truncal ridges and formation of aorticopulmonary septum. Ø 3 Semilunar valves begin to develop from 3 swellings of subendocardial tissue around aortic & pulmonary orifices. ØThese swellings are hollowed out to form the thin walled semilunar cusps.
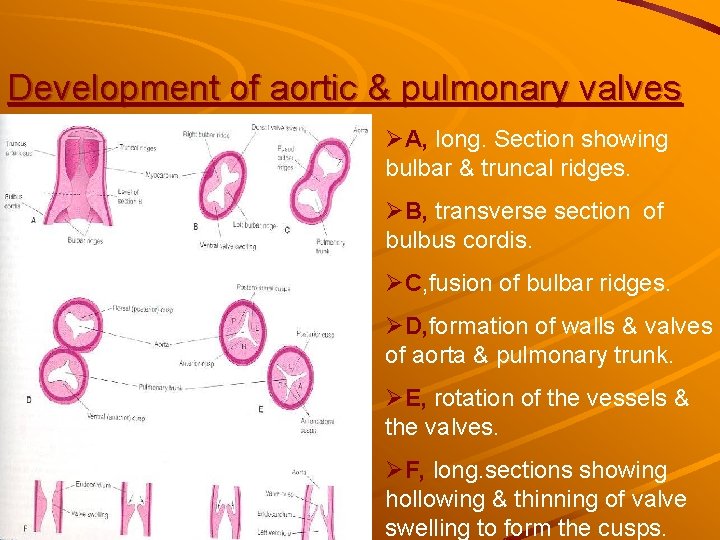
Development of aortic & pulmonary valves ØA, long. Section showing bulbar & truncal ridges. ØB, transverse section of bulbus cordis. ØC, fusion of bulbar ridges. ØD, formation of walls & valves of aorta & pulmonary trunk. ØE, rotation of the vessels & the valves. ØF, long. sections showing hollowing & thinning of valve swelling to form the cusps.
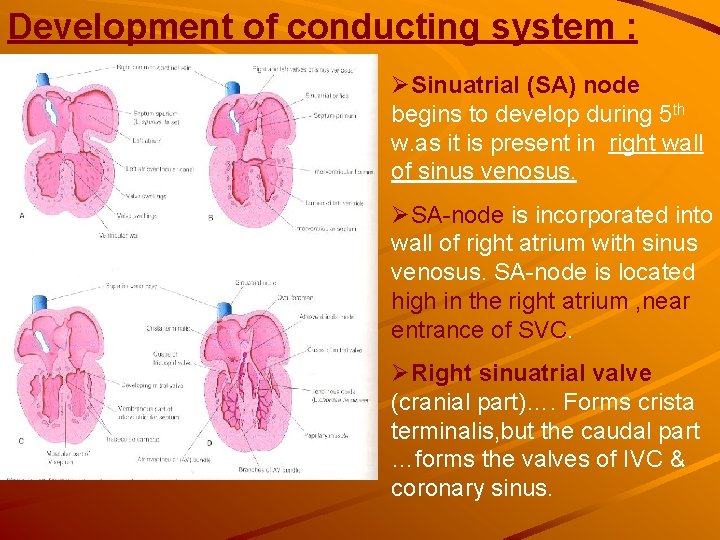
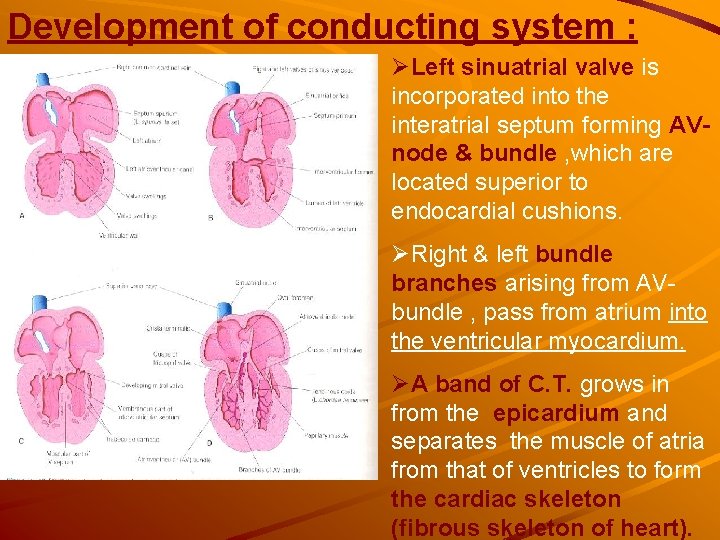
Development of conducting system : ØSinuatrial (SA) node begins to develop during 5 th w. as it is present in right wall of sinus venosus. ØSA-node is incorporated into wall of right atrium with sinus venosus. SA-node is located high in the right atrium , near entrance of SVC. ØRight sinuatrial valve (cranial part)…. Forms crista terminalis, but the caudal part …forms the valves of IVC & coronary sinus.
Development of conducting system : ØLeft sinuatrial valve is incorporated into the interatrial septum forming AVnode & bundle , which are located superior to endocardial cushions. ØRight & left bundle branches arising from AVbundle , pass from atrium into the ventricular myocardium. ØA band of C. T. grows in from the epicardium and separates the muscle of atria from that of ventricles to form the cardiac skeleton (fibrous skeleton of heart).
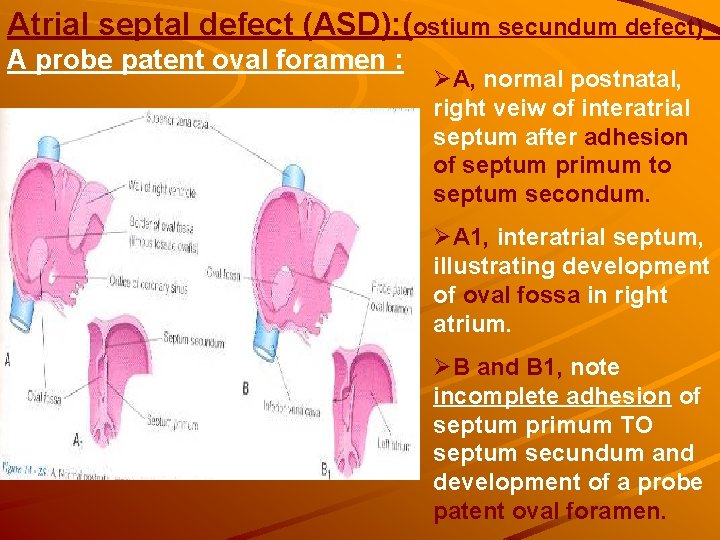
Atrial Septal defects (ASD) There are 4 types of clinically significant types of ASD : 1 -ostium secundum defect. (with patent oval foramen). 2 -endocardial cushion defect. (with ostium primum defect). 3 -sinus venosus defect. 4 -common atrium…. Rare cardiac defect , in which the interatrial septum is absent due to failure of septum primum & septum secundum to develop.
Atrial septal defect (ASD): (ostium secundum defect) A probe patent oval foramen : ØA, normal postnatal, right veiw of interatrial septum after adhesion of septum primum to septum secondum. ØA 1, interatrial septum, illustrating development of oval fossa in right atrium. ØB and B 1, note incomplete adhesion of septum primum TO septum secundum and development of a probe patent oval foramen.
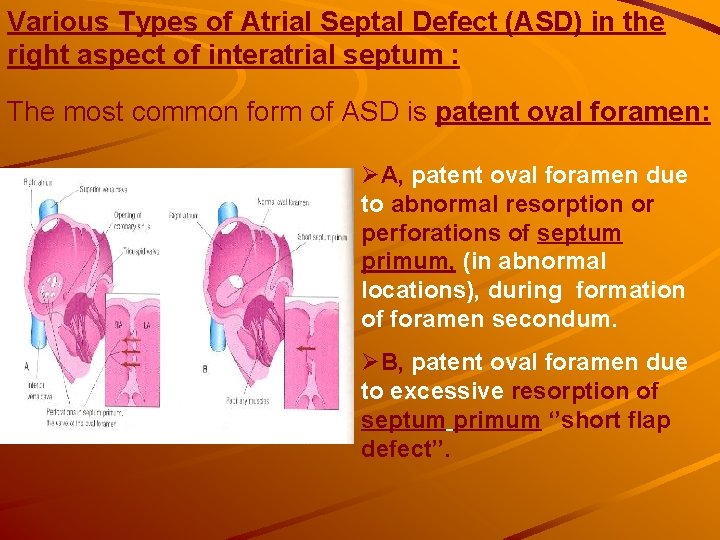
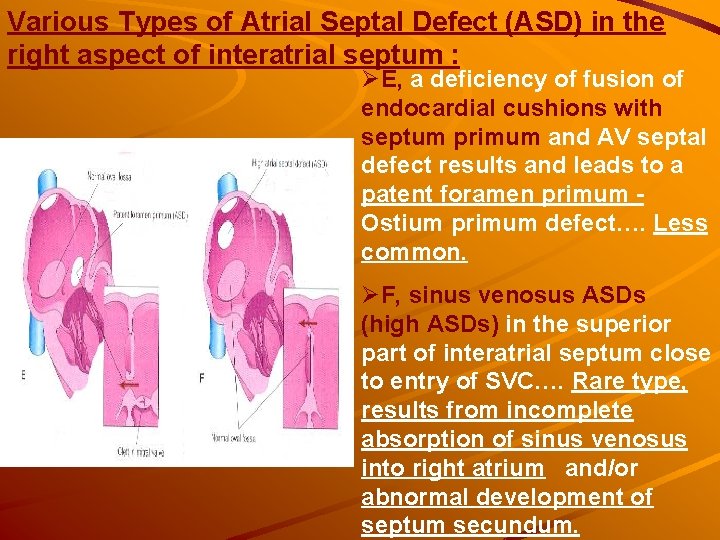
Various Types of Atrial Septal Defect (ASD) in the right aspect of interatrial septum : The most common form of ASD is patent oval foramen: ØA, patent oval foramen due to abnormal resorption or perforations of septum primum, (in abnormal locations), during formation of foramen secondum. ØB, patent oval foramen due to excessive resorption of septum primum ‘’short flap defect’’.
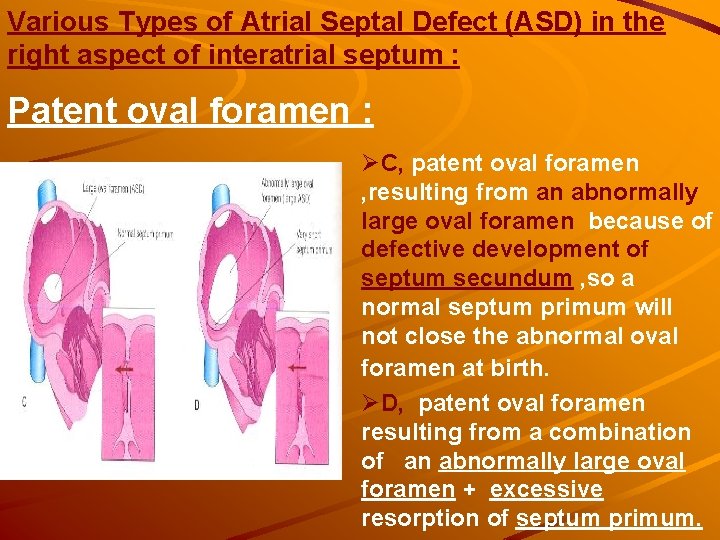
Various Types of Atrial Septal Defect (ASD) in the right aspect of interatrial septum : Patent oval foramen : ØC, patent oval foramen , resulting from an abnormally large oval foramen because of defective development of septum secundum , so a normal septum primum will not close the abnormal oval foramen at birth. ØD, patent oval foramen resulting from a combination of an abnormally large oval foramen + excessive resorption of septum primum.
Various Types of Atrial Septal Defect (ASD) in the right aspect of interatrial septum : ØE, a deficiency of fusion of endocardial cushions with septum primum and AV septal defect results and leads to a patent foramen primum Ostium primum defect…. Less common. ØF, sinus venosus ASDs (high ASDs) in the superior part of interatrial septum close to entry of SVC…. Rare type, results from incomplete absorption of sinus venosus into right atrium and/or abnormal development of septum secundum.
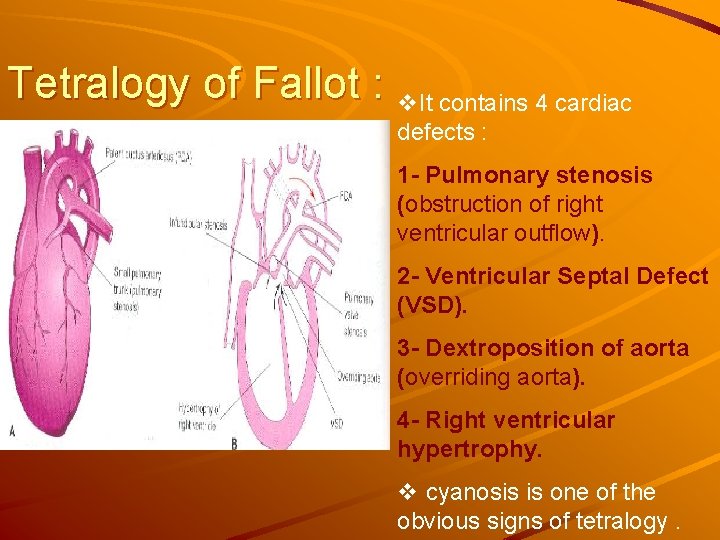
Tetralogy of Fallot : v. It contains 4 cardiac defects : 1 - Pulmonary stenosis (obstruction of right ventricular outflow). 2 - Ventricular Septal Defect (VSD). 3 - Dextroposition of aorta (overriding aorta). 4 - Right ventricular hypertrophy. v cyanosis is one of the obvious signs of tetralogy.
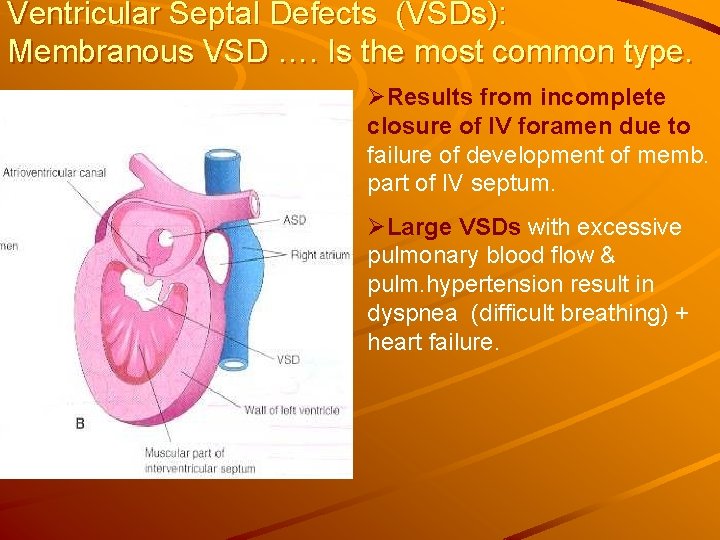
Ventricular Septal Defects (VSDs): Membranous VSD …. Is the most common type. ØResults from incomplete closure of IV foramen due to failure of development of memb. part of IV septum. ØLarge VSDs with excessive pulmonary blood flow & pulm. hypertension result in dyspnea (difficult breathing) + heart failure.
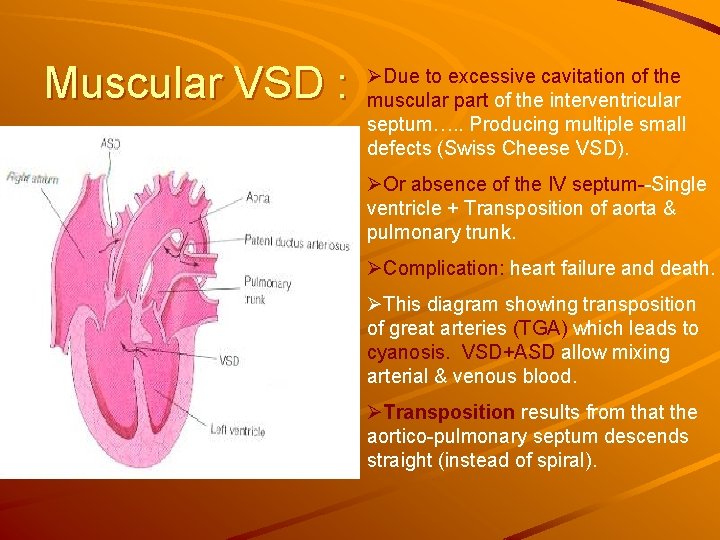
Muscular VSD : ØDue to excessive cavitation of the muscular part of the interventricular septum…. . Producing multiple small defects (Swiss Cheese VSD). ØOr absence of the IV septum--Single ventricle + Transposition of aorta & pulmonary trunk. ØComplication: heart failure and death. ØThis diagram showing transposition of great arteries (TGA) which leads to cyanosis. VSD+ASD allow mixing arterial & venous blood. ØTransposition results from that the aortico-pulmonary septum descends straight (instead of spiral).
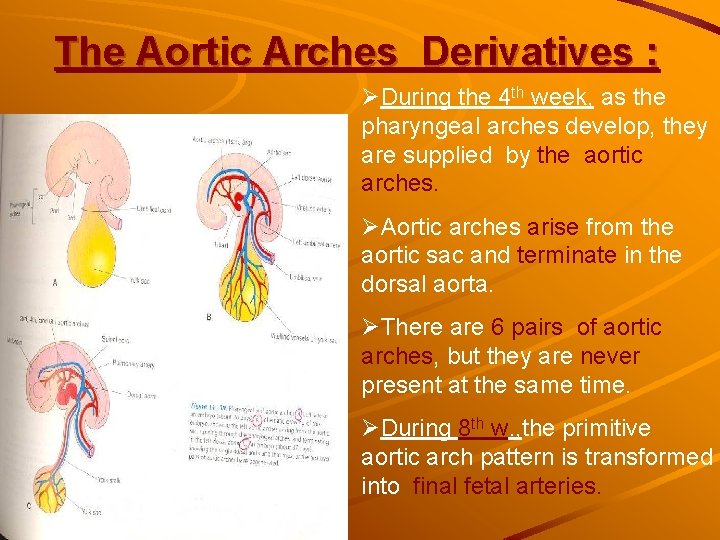
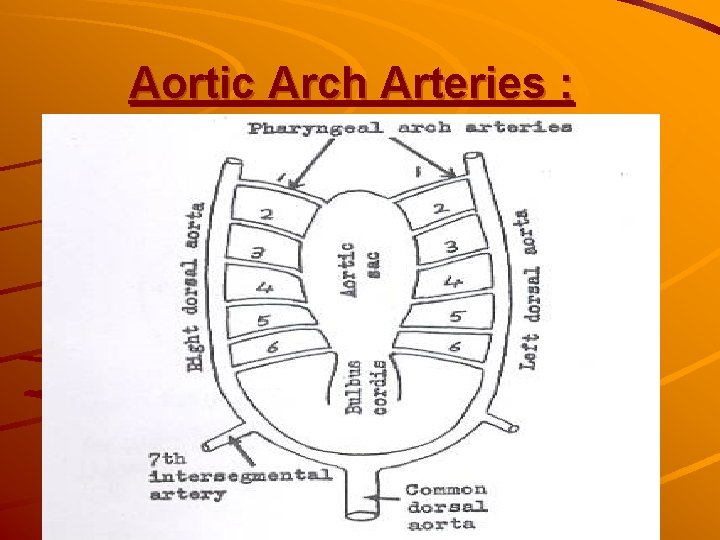
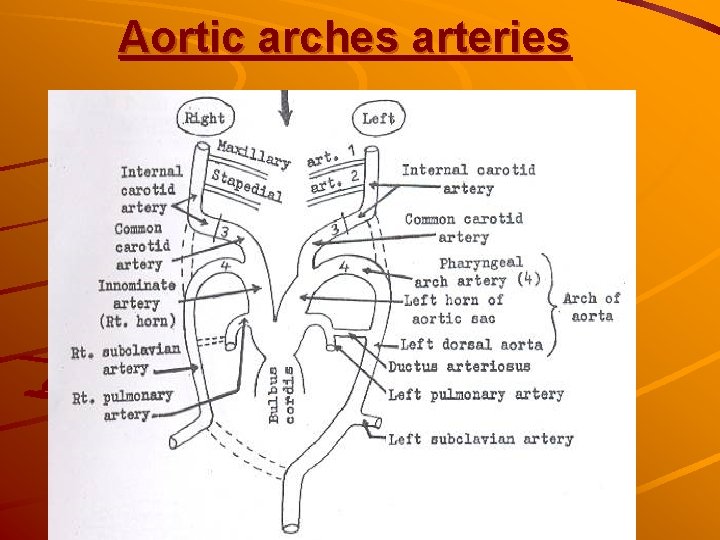
The Aortic Arches Derivatives : ØDuring the 4 th week, as the pharyngeal arches develop, they are supplied by the aortic arches. ØAortic arches arise from the aortic sac and terminate in the dorsal aorta. ØThere are 6 pairs of aortic arches, but they are never present at the same time. ØDuring 8 th w. , the primitive aortic arch pattern is transformed into final fetal arteries.
Aortic Arch Arteries :
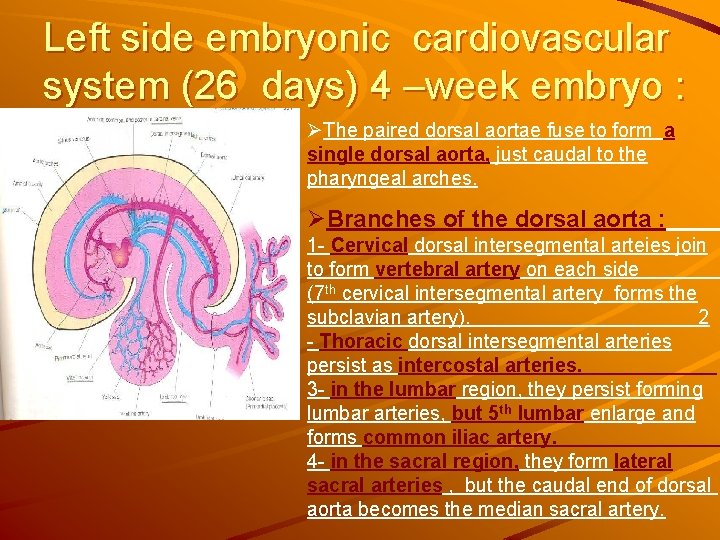
Left side embryonic cardiovascular system (26 days) 4 –week embryo : ØThe paired dorsal aortae fuse to form a single dorsal aorta, just caudal to the pharyngeal arches. ØBranches of the dorsal aorta : 1 - Cervical dorsal intersegmental arteies join to form vertebral artery on each side (7 th cervical intersegmental artery forms the subclavian artery). 2 - Thoracic dorsal intersegmental arteries persist as intercostal arteries. 3 - in the lumbar region, they persist forming lumbar arteries, but 5 th lumbar enlarge and forms common iliac artery. 4 - in the sacral region, they form lateral sacral arteries , but the caudal end of dorsal aorta becomes the median sacral artery.
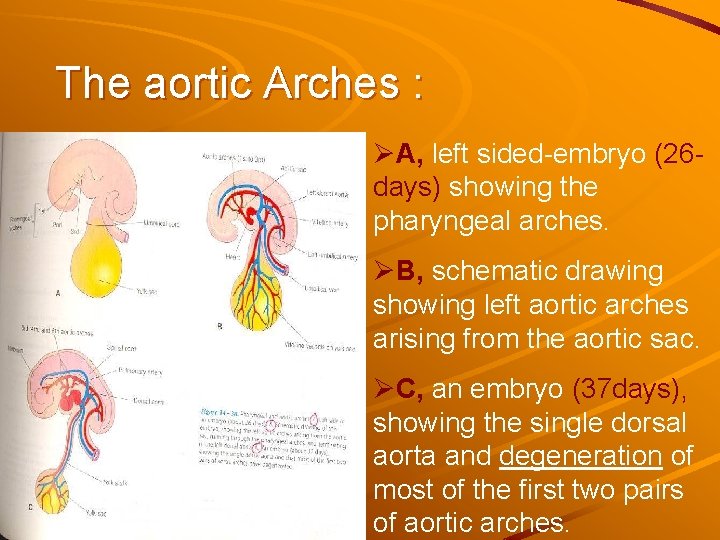
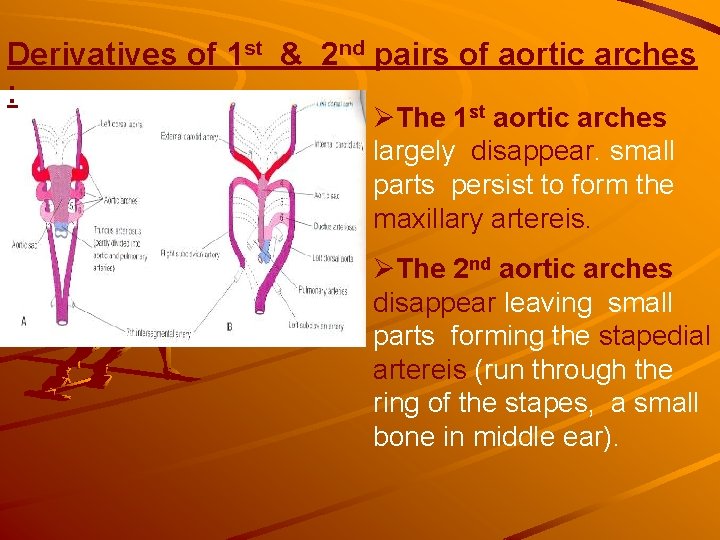
The aortic Arches : ØA, left sided-embryo (26 days) showing the pharyngeal arches. ØB, schematic drawing showing left aortic arches arising from the aortic sac. ØC, an embryo (37 days), showing the single dorsal aorta and degeneration of most of the first two pairs of aortic arches.
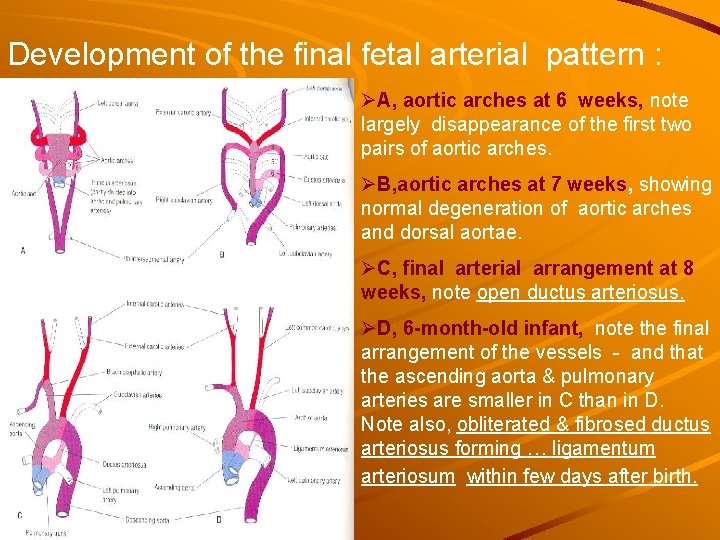
Development of the final fetal arterial pattern : ØA, aortic arches at 6 weeks, note largely disappearance of the first two pairs of aortic arches. ØB, aortic arches at 7 weeks, showing normal degeneration of aortic arches and dorsal aortae. ØC, final arterial arrangement at 8 weeks, note open ductus arteriosus. ØD, 6 -month-old infant, note the final arrangement of the vessels - and that the ascending aorta & pulmonary arteries are smaller in C than in D. Note also, obliterated & fibrosed ductus arteriosus forming … ligamentum arteriosum within few days after birth.
Derivatives of 1 st & 2 nd pairs of aortic arches : st ØThe 1 aortic arches largely disappear. small parts persist to form the maxillary artereis. ØThe 2 nd aortic arches disappear leaving small parts forming the stapedial artereis (run through the ring of the stapes, a small bone in middle ear).
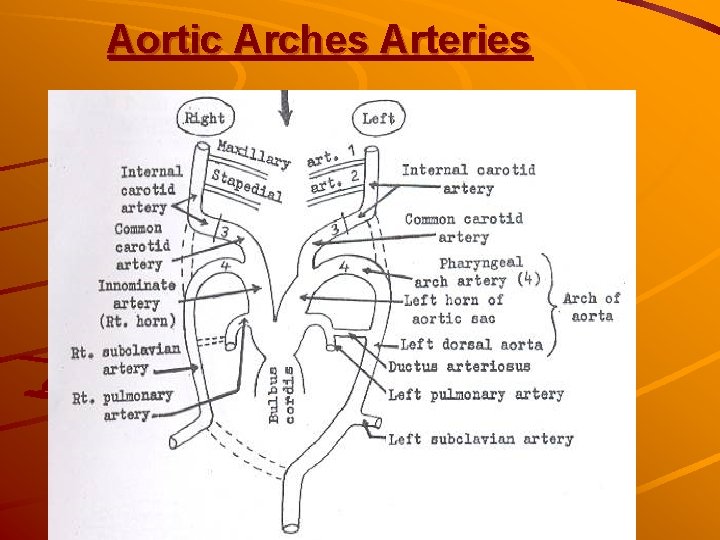
Aortic Arches Arteries
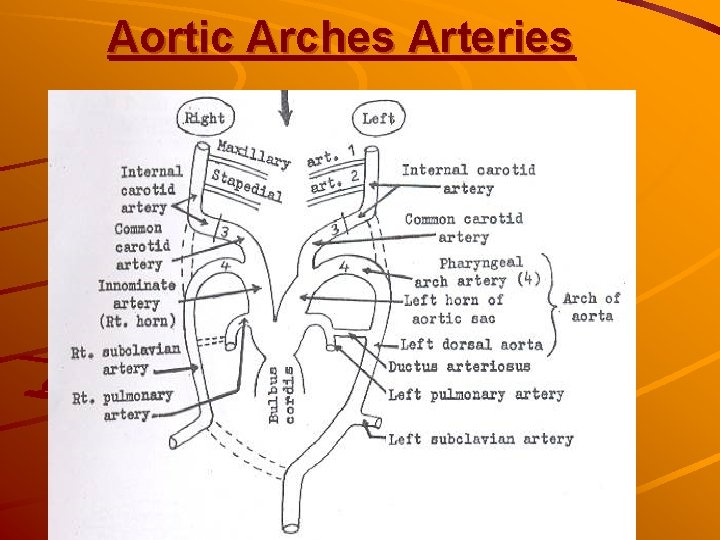
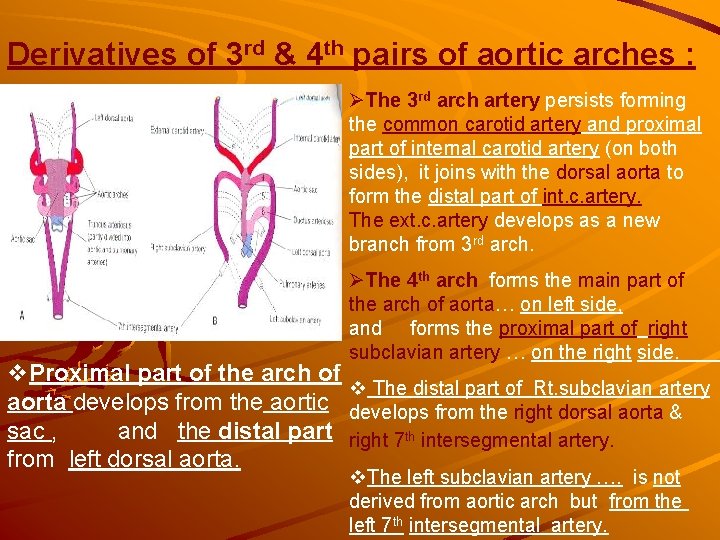
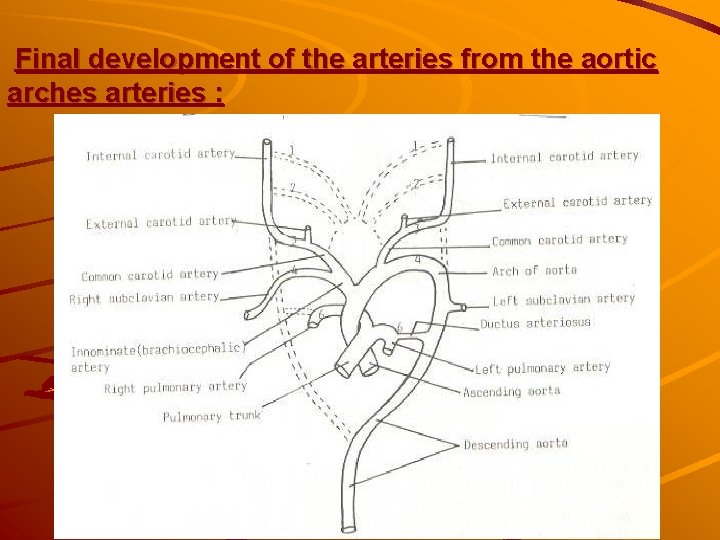
Derivatives of 3 rd & 4 th pairs of aortic arches : ØThe 3 rd arch artery persists forming the common carotid artery and proximal part of internal carotid artery (on both sides), it joins with the dorsal aorta to form the distal part of int. c. artery. The ext. c. artery develops as a new branch from 3 rd arch. ØThe 4 th arch forms the main part of the arch of aorta… on left side, and forms the proximal part of right subclavian artery … on the right side. v. Proximal part of the arch of v The distal part of Rt. subclavian artery aorta develops from the aortic develops from the right dorsal aorta & sac , and the distal part right 7 th intersegmental artery. from left dorsal aorta. v. The left subclavian artery …. is not derived from aortic arch but from the left 7 th intersegmental artery.
Aortic arches arteries
Derivatives of 5 th & 6 th pairs of aortic arches : ØThe portion of dorsal aorta connecting the 3 rd & 4 th arches disappears on both sides. ØThe 5 th arch artery disappears in 50% and in the other 50% of the embryos, these arteries do not develop. v. The dorsal aorta on the right side caudal to 4 th arch disappears down to the single dorsal aorta, while persists on left side to form descending aorta. ØThe 6 th arch artery : a- proximal part on both sides … forms the pulmonary artery. b - distal part of left artery : forms ductus arteriosus which connects left pulmonary artery with arch of aorta. C- distal part of right artery : disappears.
Aortic Arches Arteries
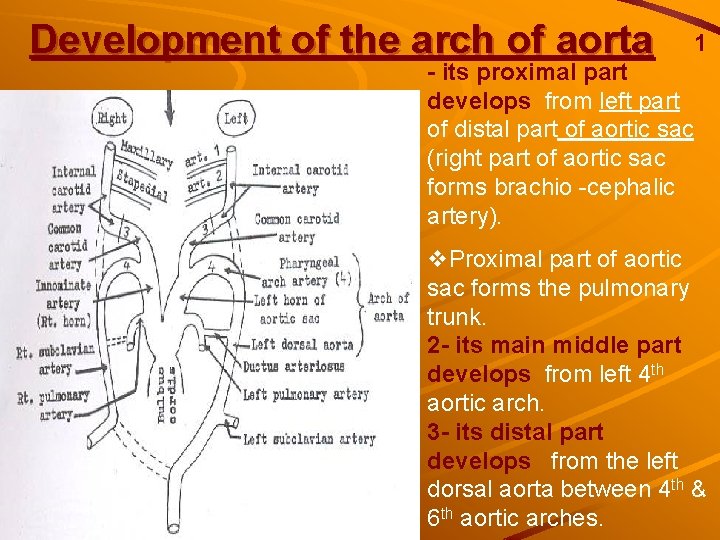
Development of the arch of aorta 1 - its proximal part develops from left part of distal part of aortic sac (right part of aortic sac forms brachio -cephalic artery). v. Proximal part of aortic sac forms the pulmonary trunk. 2 - its main middle part develops from left 4 th aortic arch. 3 - its distal part develops from the left dorsal aorta between 4 th & 6 th aortic arches.
Final development of the arteries from the aortic arches arteries :
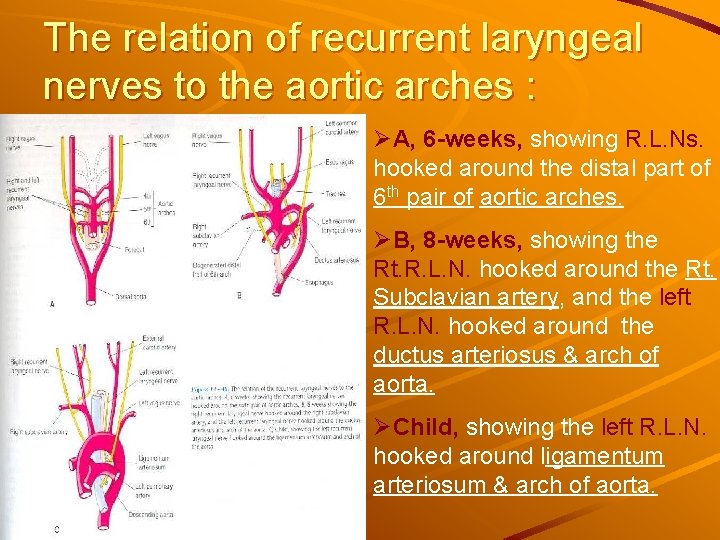
The relation of recurrent laryngeal nerves to the aortic arches : ØA, 6 -weeks, showing R. L. Ns. hooked around the distal part of 6 th pair of aortic arches. ØB, 8 -weeks, showing the Rt. R. L. N. hooked around the Rt. Subclavian artery, and the left R. L. N. hooked around the ductus arteriosus & arch of aorta. ØChild, showing the left R. L. N. hooked around ligamentum arteriosum & arch of aorta.
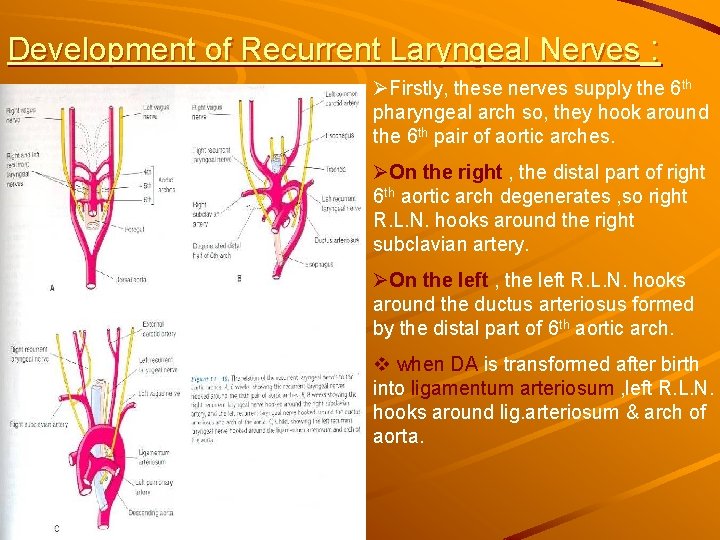
Development of Recurrent Laryngeal Nerves : ØFirstly, these nerves supply the 6 th pharyngeal arch so, they hook around the 6 th pair of aortic arches. ØOn the right , the distal part of right 6 th aortic arch degenerates , so right R. L. N. hooks around the right subclavian artery. ØOn the left , the left R. L. N. hooks around the ductus arteriosus formed by the distal part of 6 th aortic arch. v when DA is transformed after birth into ligamentum arteriosum , left R. L. N. hooks around lig. arteriosum & arch of aorta.
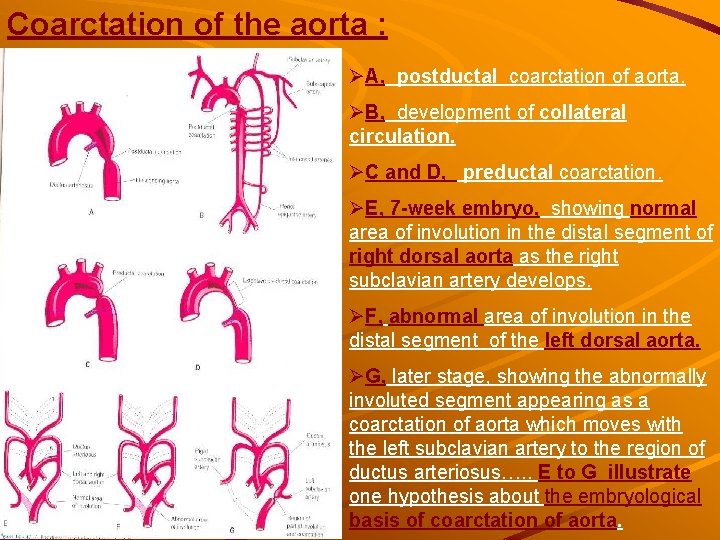
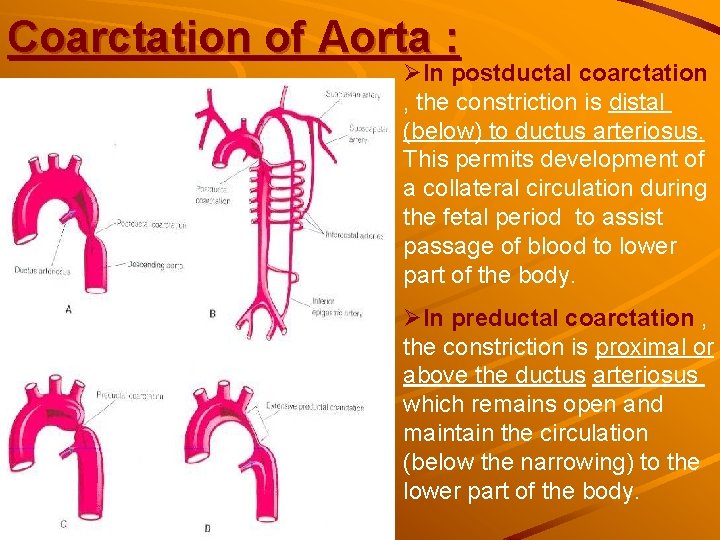
Coarctation of the aorta : ØA, postductal coarctation of aorta. ØB, development of collateral circulation. ØC and D, preductal coarctation. ØE, 7 -week embryo, showing normal area of involution in the distal segment of right dorsal aorta as the right subclavian artery develops. ØF, abnormal area of involution in the distal segment of the left dorsal aorta. ØG, later stage, showing the abnormally involuted segment appearing as a coarctation of aorta which moves with the left subclavian artery to the region of ductus arteriosus…. . E to G illustrate one hypothesis about the embryological basis of coarctation of aorta.
Coarctation of Aorta : ØIn postductal coarctation , the constriction is distal (below) to ductus arteriosus. This permits development of a collateral circulation during the fetal period to assist passage of blood to lower part of the body. ØIn preductal coarctation , the constriction is proximal or above the ductus arteriosus which remains open and maintain the circulation (below the narrowing) to the lower part of the body.