
Curriculum Update Endocrinology Gastrointestinal Disorders RenalUrology Disorders Condell





































































- Slides: 98
Curriculum Update: Endocrinology, Gastrointestinal Disorders, Renal/Urology Disorders Condell Medical Center EMS System March, 2007 Site Code #10 -7200 E-1207 S. Hopkins, RN, BSN, EMT-P
Objectives • Upon successful completion of this module, the EMS provider should be able to: – identify the function of the endocrine system – distinguish a variety of medical disorders of the endocrine system – describe pain for gastrointestinal and genitourinary disorders – identify and appropriately state interventions for a variety of EKG rhythms – successfully complete the quiz with a score of 80% or better
Endocrine System • Composed of glands that secrete hormones into the circulatory system • Helps regulate various metabolic functions • Hormones function in a lock and key fashion • All hormones operate within a feedback system
Hormones • Act on target organs elsewhere in the body • Controls and coordinates wide spread processes on organs, tissues, or general effects on the entire body – homeostasis – reproduction – growth & development – metabolism – response to stress
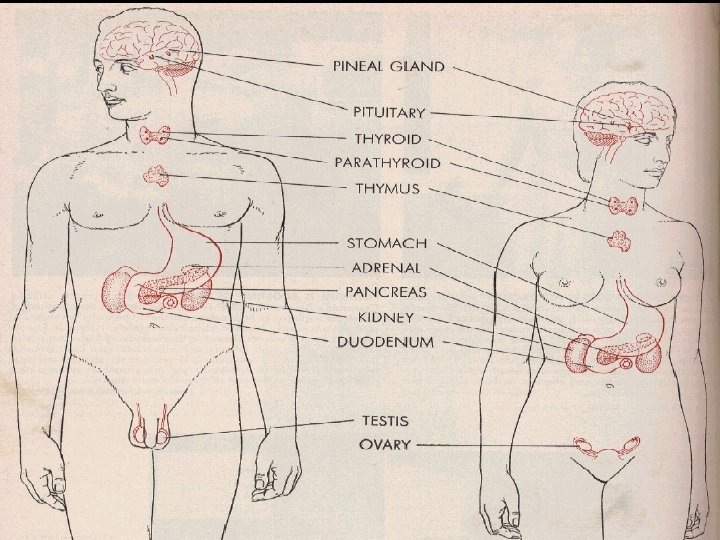
Endocrine Glands ü Hypothalamus – located deep within the cerebrum of the brain; serves as connection between the central nervous system (CNS) and endocrine system – secretes hormones that make other endocrine glands secrete hormones ü Pituitary - anterior & posterior – located in the brain; size of a pea – secretes hormones essential to growth, reproduction, and water balance in the body
Endocrine Glands cont’d ü Thyroid – 2 lobes located in anterior neck – plays important role in controlling metabolism ü Parathyroid – normally 4 glands found next to thyroid gland – secretes hormone to increase blood calcium levels
Endocrine Glands cont’d ü Thymus gland – located in mediastinum behind sternum – during childhood secretes a hormone critical in maturing T lymphocytes (cells responsible for cellmediated immunity) ü Pancreas – located in upper retroperitoneum behind stomach – secretes digestive enzymes for digestion of fats & proteins – controls production or inhibition of the hormones glucagon & insulin
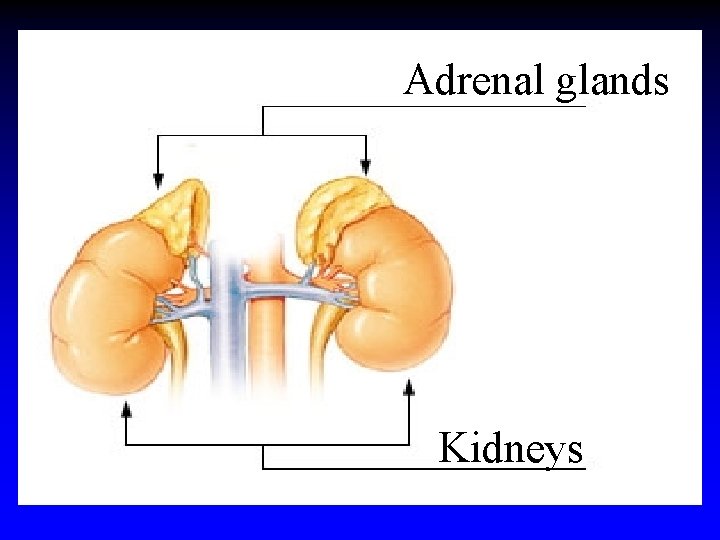
Endocrine Glands cont’d ü Adrenal gland – located on superior surface of each kidney – adrenal medulla - secretes the catecholamine hormones epinephrine & norepinephrine – adrenal cortex - secretes 3 steroidal hormones ü Gonads – chief responsibility for sexual maturation or puberty and subsequent reproduction – ovaries produce eggs – testes produce sperm
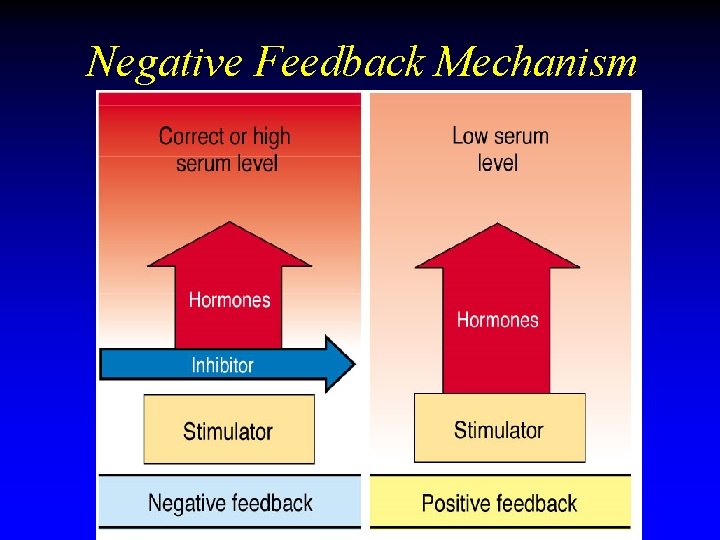
Regulation of Hormone Secretion • Hormones operate within a positive or negative feedback system to maintain homeostasis • Negative feedback – Most common feedback mechanism – Usually refers to an increase in the serum level of hormone or hormone-related substance that suppresses further hormone output – Hormone production is stimulated when the serum levels fall
Negative Feedback Mechanism
Specific Disorders of the Endocrine System • Disorders of the endocrine system arise from: – the effects of an imbalance in the production of one or more hormones – the effects of an alteration in the body’s ability to use the hormones produced
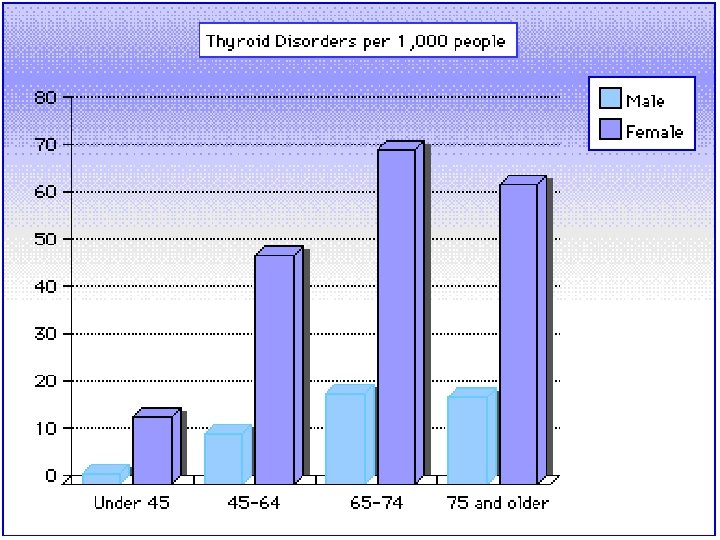
Specific Disorders of the Endocrine System • Clinical effects of endocrine gland imbalance are determined by: üthe degree of dysfunction üthe age and gender of the affected person
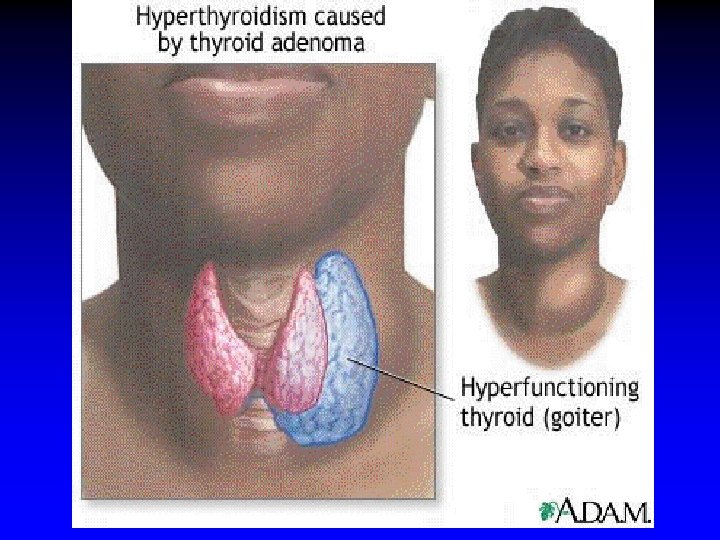
Disorders of Thyroid Gland • Usually seen more as part of the medical history than as a medical emergency • Complications of thyroid disorders more likely to be seen – hyperthyroidism - too much thyroid hormone in the blood (goiter) – thyrotoxicosis - prolonged exposure to excess thyroid hormones (Grave’s disease) – hypothyroidism - inadequate thyroid hormone – myxedema - long term exposure to inadequate levels of thyroid hormones
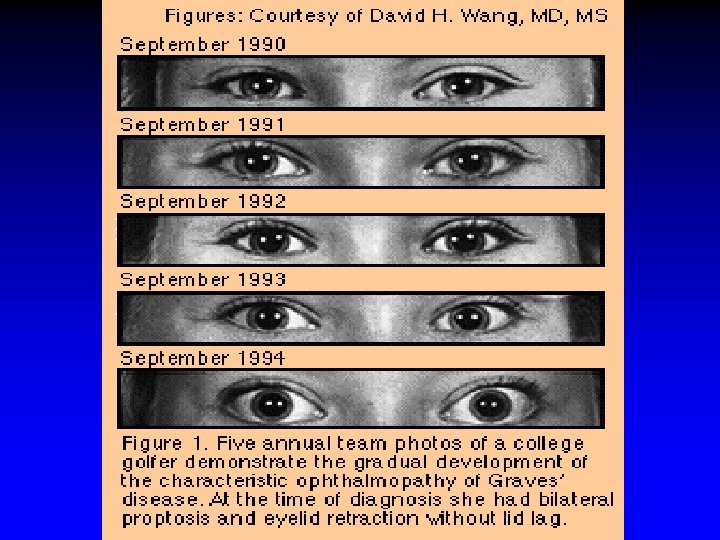
Grave’s Disease • A type of excessive thyroid activity characterized by a generalized enlargement of the gland (goiter), leading to a swollen neck and often protruding eyes (exophthalmos) – More common in women than men (6 times) – Typical onset young adulthood (20’s & 30’s) – May be due to an autoimmune process in which an antibody stimulates the thyroid cells – Strong hereditary role in predisposition of the disorder
Grave’s Disease • EMS significance ücardiac dysfunction the most common EMS event • tachycardia or new-onset atrial fibrillation in absence of cardiac history • Other signs & symptoms üagitation, emotional changeability, insomnia, poor heat tolerance, weight loss with increased appetite, weakness, dyspnea
Thyrotoxicosis • A term that refers to any toxic condition that results from prolonged excess thyroid hormone • Thyroid storm is a heightened and life-threatening manifestation of thyroid hyperfunction – A relatively rare condition; can be fatal – Usually associated with exposure to physiological stress (trauma, infection) – signs & symptoms indicate extreme hypermetabolic state (high fever (1060 F), irritability, delirium or coma, tachycardia, hypotension, vomiting, diarrhea) • EMS care - supportive, rapid transport
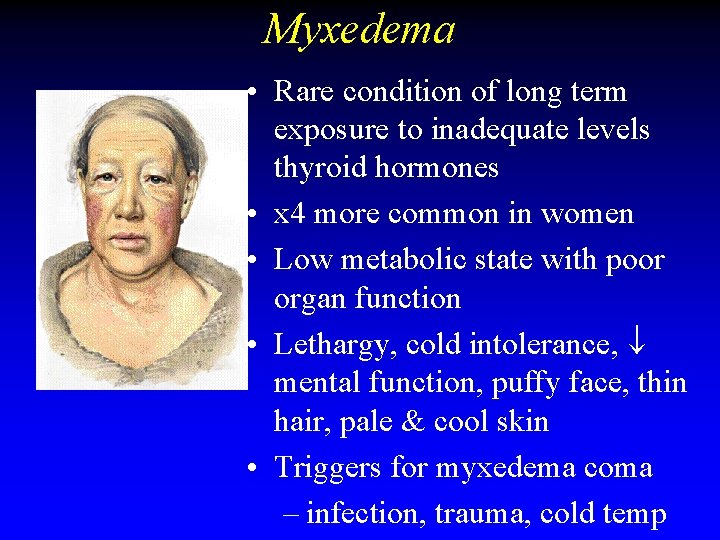
Myxedema • Rare condition of long term exposure to inadequate levels thyroid hormones • x 4 more common in women • Low metabolic state with poor organ function • Lethargy, cold intolerance, mental function, puffy face, thin hair, pale & cool skin • Triggers for myxedema coma – infection, trauma, cold temp
Myxedema Coma • Myxedema coma difficult to identify • EMS impact – Heart failure not uncommon – Focus on maintenance of ABC’s – Monitor pulmonary and cardiac systems closely – Rapid transport important – Active rewarming in field not indicated • may cause cardiac dysrhythmias • vasodilation may cause cardiovascular collapse
Disorders of Adrenal Glands Adrenal cortex - outer portion of adrenal gland • Secretes steroidal hormones – glucocorticoids - increase blood glucose levels – mineralocorticoids - contributes to salt & fluid balance – androgenic hormones - influences similar to the gonads (role in puberty and reproduction) • Two medical emergencies of the adrenal cortex üCushing’s syndrome üAddison’s disease
Cushing’s Syndrome • Caused by an abnormally high circulating level of corticosteroid hormones produced naturally by the adrenal glands • May be produced: – Directly by an adrenal gland tumor – By prolonged administration of corticosteroid drugs (ie: prednisone, hydrocortisone) – By enlargement of both adrenal glands due to a pituitary tumor • Relatively common problem of adrenals
Adrenal glands Kidneys
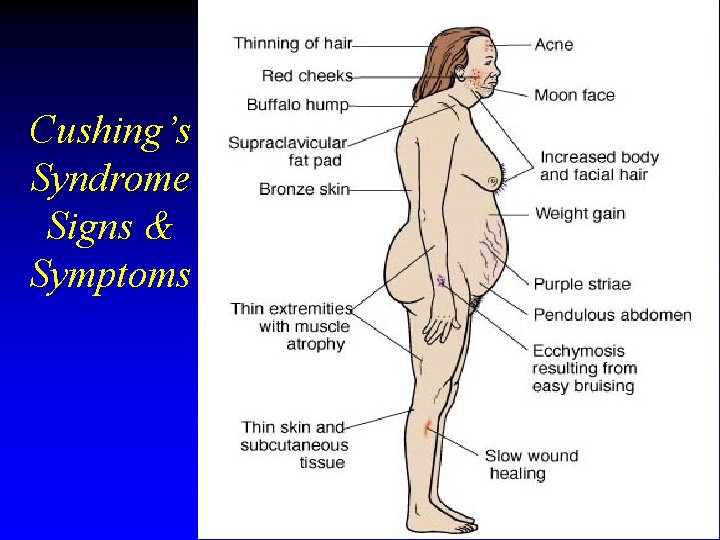
Cushing’s Syndrome • Characteristic appearance – Face appears round (“moon-faced”) and red – Trunk tends to become obese from disturbances in fat metabolism; “buffalo hump” on back – Limbs become wasted from muscle atrophy – Mood swings , impaired concentration – Purple stretch marks may appear on the abdomen, thighs, and breasts – Skin often thins and bruises easily – Weakened bones are at increased risk for fracture
Moon Face
Cushing’s Syndrome Signs & Symptoms
Management Cushing’s Syndrome • FYI: higher incidence of cardiovascular disease üstroke ühypertension • Fragile skin ücaution with IV starts ühandle the patient carefully to avoid trauma to their skin • Treat symptoms as presented
Addison’s Disease • Pathophysiology – Adrenal steroids reduced üGlucocorticoids üMineralocorticoids üAndrogens – Most common cause is idiopathic atrophy of adrenal tissue (cause unknown) – Less common causes include hemorrhage, infarctions, fungal infections, auto immune disease, therapy with steroids (ie: prednisone)
Addison’s Disease • Signs and symptoms – Progressive weakness, fatigue – Decreased appetite & weight loss – Hyperpigmentation of skin, especially over sun-exposed skin areas – Disturbances in water & electrolyte balance – Low blood volume – EKG changes – Abrupt stoppage of steroids may trigger Addisonian crisis with cardiovascular collapse
Addison’s Disease • Management – Evaluate ABC’s & correct issues – Cardiac status - watch for dysrhythmias and circulatory collapse • Fluid resuscitation – Respiratory status - evaluate Sa. O 2 levels – Blood glucose levels • Hypoglycemia very common
Diabetes Mellitus • Disease marked by inadequate insulin activity in the body • Glucose is important to all body cells but critical for the brain – Glucose only substance used by the brain for energy • Insulin maintains normal blood glucose levels – Enables body to store energy as glycogen, protein & fats – Action of insulin allows glucose to flow into cells
Normal Blood Glucose Levels • Healthy persons – Overnight fast - 80 -90 mg/d. L – 1 st hour after a meal - 120 -140 mg/d. L – <80 mg/d. L reflects hypoglycemia – >140 mg/d. L reflects hyperglycemia • Intervention necessary – Hypoglycemia -blood glucose <60 mg/d. L – Hyperglycemia - blood glucose >300 mg/d. L not uncommon
Type I Diabetes • Low or absent production of insulin in the pancreas • Too much sugar, not enough insulin • Patients require supplemental insulin • If untreated, glucose levels rise – excess glucose spills into urine; patient loses large amounts of water (becomes dehydrated); fatty acids used as energy source resulting in ketosis from fat catabolism
Untreated Type I Diabetes • Signs & symptoms due to elevated blood glucose levels üPolydipsia (constant thirst) üPolyuria (excessive urination) üPolyphagia (ravenous appetite) üWeakness üWeight loss • Above signs & symptoms are what usually prompt people to seek a medical checkup for “not feeling well”
Type II Diabetes • More common than Type I diabetes (90% of cases) • Moderate decline in insulin production and inefficient use of the insulin that is produced • Risk factors: heredity, obesity • Treatment: dietary changes, increased exercise, oral hypoglycemics (to stimulate insulin production), possible addition of insulin if necessary
• • • Diabetic Ketoacidosis (Diabetic Coma) Too much sugar, not enough insulin Onset slow (12 - 24 hours) Increased urination; dehydration (warm, dry skin) Excessive hunger and thirst Tachycardia & weakness (volume depletion) Ketoacidosis Kussmaul’s respirations (deep and rapid) to exhale CO 2 (an acid) • Decline in mental function • Low potassium - cardiac dysrhythmias
Diabetic Coma - Hyperglycemia • ABC’s addressed • Search for medic alert bracelet or insulin in refrigerator • Blood glucose levels (not uncommon to be >300) • Fluid resuscitation to treat dehydration • The higher the glucose level, the more critical the situation and the sicker the patient
Insulin Shock - Hypoglycemia • • • Too much insulin, not enough sugar Onset rapid Bizarre, unusual, inappropriate behavior Diaphoretic, tachycardic Seizures at critically low glucose levels Rapid recovery with correct treatment – supplemental glucose
Insulin Shock - Hypoglycemia • ABC’s addressed • Search for medical alert bracelet or insulin in refrigerator • Treated when blood sugar drops below 60 • IV access to administer dextrose – Adult - D 50 (50 ml) – Child (1 to 15) - D 25 (2 ml/kg) – Child <1 - D 12. 5% (4 ml/kg) • 1: 1 dilution of D 25% and normal saline • Lack of IV access – Glucagon IM: adult 1 mg; peds 0. 1 mg/kg (max 1 mg)
Glucagon vs Dextrose • Glucagon – a hormone, not a sugar – helps release stores of sugar if there is any in the liver but does not supply sugar itself • What do I do if no IV access, glucagon given, patient remains with altered level of consciousness and now I get an IV? ? ? • Recheck the glucose level and if indicated, administer dextrose IVP
Gestational Diabetes • Onset can occur during pregnancy • While pregnant, most women require 2 -3 times more insulin than would usually be required when not pregnant • During pregnancy, must be treated with insulin vs oral medication – insulin does not cross placental barrier, oral medication does • After delivery blood glucose levels return to normal
Skill Review Precision Xtra Glucose Monitoring System
Precision Xtra Calibration • Done when every new bottle opened • Calibration strip remains with those strips • Machine turns on when calibration strip slid into monitor • Confirm that LOT number displayed matches LOT number on strips • Turn monitor off • Monitor preprogrammed to display in English and results in mg/d. L
Precision Xtra Glucose Testing • Insert glucose strip into monitor • Verify machine on & lot number correct • Obtain blood sample – hang hand dependently – cleanse area with alcohol wipe, let air dry – Use lancet to prick finger • use site on ulnar side of finger (easier for patient to hold hand in good position to obtain sample)
Precision Xtra Glucose Testing – Touch blood drop to target area on strip • blood may be applied to edge or top of test strip • continue touching the test strip to blood drop until monitor begins test (--- shows) • a second drop of blood may be applied, if needed, up to 30 seconds after 1 st drop – Monitor turns off automatically after 30 seconds – View (& record) your results
• Your Precision Xtra strips are designed to give accurate results based on capillary samples • You cannot be using venous samples (ie: from IV starts) • Venous results will be inaccurate Now You Know
Gastrointestinal System
Gastrointestinal Emergencies • GI system includes from the mouth to anus and all parts in between • Risk factors for disease (usually self-induced) – excessive alcohol consumption – excessive smoking – increased stress – ingestion of caustic substances – poor bowel habits • Pain is the hallmark of acute abdominal problems – visceral, somatic, or referred
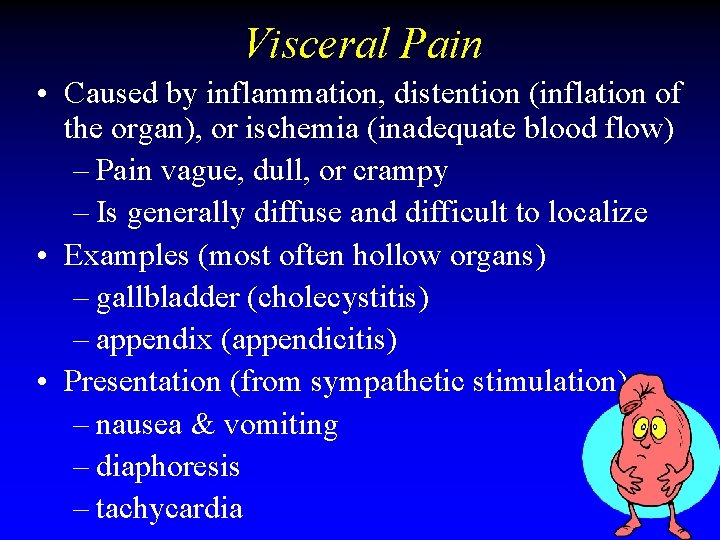
Visceral Pain • Caused by inflammation, distention (inflation of the organ), or ischemia (inadequate blood flow) – Pain vague, dull, or crampy – Is generally diffuse and difficult to localize • Examples (most often hollow organs) – gallbladder (cholecystitis) – appendix (appendicitis) • Presentation (from sympathetic stimulation) – nausea & vomiting – diaphoresis – tachycardia
Somatic Pain • Produced by bacterial or chemical irritation of nerve fibers in the peritoneum (peritonitis) – Is usually constant and localized to a specific area – Often described as sharp or stabbing • Examples – ruptured appendix – perforated ulcer – inflamed pancreas • Peritonitis can lead to sepsis & death
Somatic Pain • Presentation – Patient often hesitant to move – Lies on their back or side with legs flexed to prevent additional pain from stimulation of the peritoneal area – Often exhibits involuntary guarding of the abdomen – Rebound tenderness often noted during the physical examination
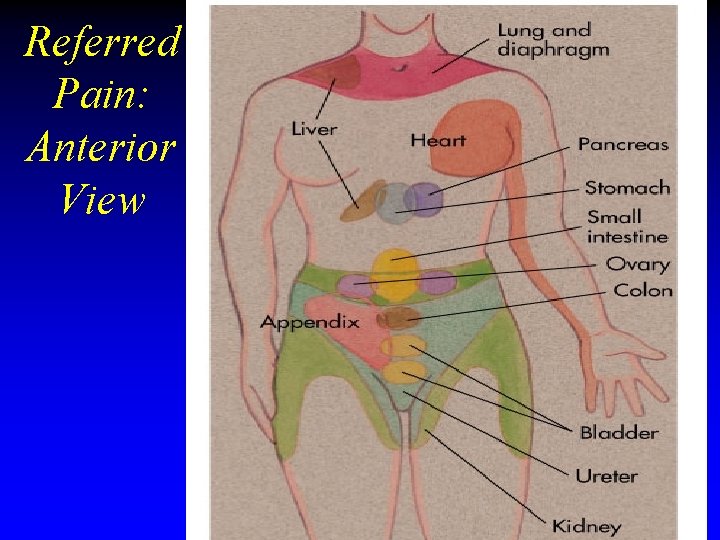
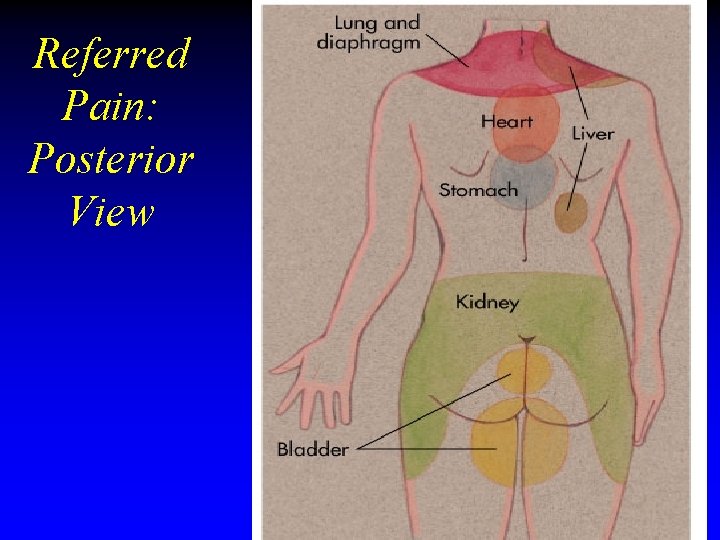
Referred Pain • Pain in a part of the body considerably removed from the tissues that cause the pain – Results from neural pathways from various organs passing thru or over a region where the organ was initially formed in fetal stage – Examples • diaphragm injury refers pain to neck or shoulders • dissecting abdominal aneurysm refers pain between shoulder blades • appendicitis refers pain to periumbilical area • gallbladder refers pain to right shoulder
Referred Pain: Anterior View
Referred Pain: Posterior View
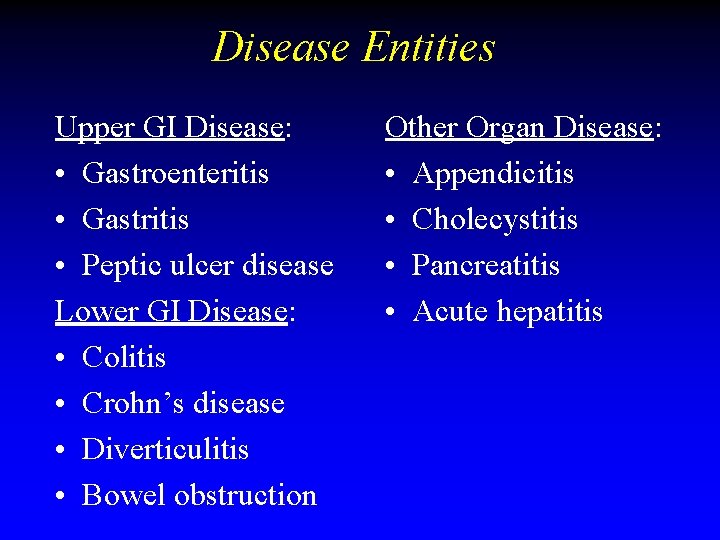
Disease Entities Upper GI Disease: • Gastroenteritis • Gastritis • Peptic ulcer disease Lower GI Disease: • Colitis • Crohn’s disease • Diverticulitis • Bowel obstruction Other Organ Disease: • Appendicitis • Cholecystitis • Pancreatitis • Acute hepatitis
Gastroenteritis • Inflammation of the stomach and intestines that accompanies numerous GI disorders • Causes: – bacteria or viral infections, chemical toxins, and other conditions • Signs and symptoms: – anorexia (loss of appetite), nausea, vomiting, abdominal pain • Management – supportive
Gastroenteritis • EMS personnel who are working in disaster areas should observe the following guidelines: – Avoid patient contact if you are ill – Know the source of water supplies or drink hot beverages brisk-boiled or disinfected – Avoid habits that facilitate fecal-oral/mucous membrane transmission (keep your hands away from your mouth and nose) – Observe BSI precautions, especially gloves – Practice diligent handwashing procedures
Gastritis • An acute or chronic inflammation of the gastric mucosa • Causes – hyperacidity – alcohol or drug ingestion – infection • Signs and symptoms: – epigastric pain – nausea and vomiting – bleeding
Peptic Ulcer Disease • Erosions in the GI tract from gastric acid • Duodenal ulcers - most frequently in proximal duodenum – most common 25 -50 years old & in those under stress – pain at night when stomach empty • Gastric ulcers - in the stomach – more common over 50 years old & in jobs of physical activity – usually no pain at night; pain on full stomach
Peptic Ulcer Disease • Causes of peptic ulcer disease üH. pylori infection (treated with antibiotics) üNonsteroidal anti-inflammatory drug use • aspirin, Motrin, Advil üAcid stimulating products • alcohol, nicotine üAcid secreting tumor • Zollinger-Ellison syndrome
Colitis • An inflammatory condition of the large intestine characterized by severe diarrhea and ulceration of the mucosa of the intestine (ulcerative colitis) • Incidence - most often 20 -40 year olds • Cause is unknown • Signs and symptoms – Nausea, vomiting, weight loss – Significant pain - cramping & colicky – Grossly bloody stools or stool containing mucus
Crohn’s Disease • A chronic, inflammatory bowel disease thought to be of autoimmune etiology, usually affecting the ileum, the colon, or both structures • Exact cause unknown • Most prevalent in: white females, those under stress, and in the Jewish population • The diseased segments associated with Crohn’s disease may be separated by normal bowel segments or skip areas – Formation of fistulas from the diseased bowel to the anus, vagina, skin surface, or to other loops of bowel are common
Crohn’s Disease • Signs and symptoms: – GI bleeding – frequent diarrhea – abdominal cramping – diffuse abdominal pain – nausea/vomiting/diarrhea – fever and chills – weakness, anorexia, weight loss
Diverticulitis • A diverticulum is a sac or pouch that develops in the wall of the colon – Common development with advancing years – Associated with diets low in fiber • Diverticulitis is inflammation of diverticula • Signs and symptoms: – Fever, anorexia, nausea, lower left sided pain, bright-red rectal bleeding • Complications: – Hypovolemic shock and sepsis
Bowel Obstruction • A partial or complete blockage of the large or small intestines • Causes: – adhesions, hernias, fecal impaction, polyps, tumors • Signs and symptoms: – decreased appetite, nausea and vomiting, diffuse abdominal pain, constipation, and abdominal distention • If untreated can lead to death
Appendicitis • A common abdominal emergency that occurs when the opening between the lumen of the appendix and the cecum is obstructed by fecal material or from inflammation from viral or bacterial infection • Signs and symptoms: – early abdominal pain is diffuse, colicky, & in periumbilical area (later RLQ), abdominal tenderness & guarding, nausea, vomiting, chills, low-grade fever, anorexia • If ruptured, risk of peritonitis
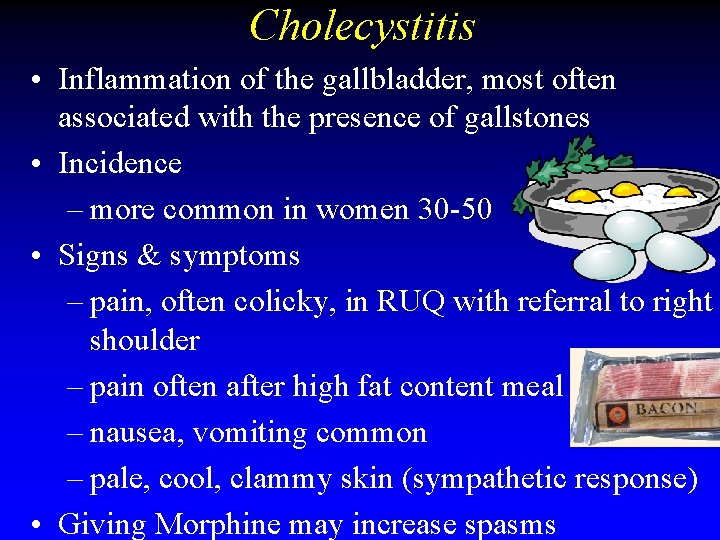
Cholecystitis • Inflammation of the gallbladder, most often associated with the presence of gallstones • Incidence – more common in women 30 -50 • Signs & symptoms – pain, often colicky, in RUQ with referral to right shoulder – pain often after high fat content meal – nausea, vomiting common – pale, cool, clammy skin (sympathetic response) • Giving Morphine may increase spasms
Pancreatitis • Inflammation of the pancreas • Alcoholism causes 80% of cases in USA • Signs and symptoms: – severe abdominal pain • localized to LUQ or referred to back or epigastric area – nausea and uncontrolled vomiting & retching – abdominal tenderness and distention – fever, tachycardia, diaphoresis – sepsis & shock possible, 30 -40% mortality
Acute Hepatitis • Inflammation of the liver • Signs & symptoms related to severity of disease – Associated with the sudden onset of malaise, weakness, anorexia, intermittent nausea and vomiting, and dull right upper quadrant pain or referral to right shoulder – Usually followed within 1 week by the onset of jaundice of skin & sclera, dark urine, clay colored stool
Risk Factors for Hepatitis A • Spread by fecal-oral route ü Health care practice without BSI precautions ü Household or sexual contact with an infected person ü Living in an area with HAV outbreak ü Traveling to developing countries ü Poor handwashing hygiene practice especially after toileting • Disease often self-limiting, lasts 2 -8 weeks, low mortality rate
Risk Factors for Hepatitis B • “Serum hepatitis” transmitted as bloodborne pathogen - can stay active in body fluids outside body for days ü Health care practice without BSI precautions ü Infant born to HBV infected mother ü Engaging in sex with infected partners and/or multiple partners ü Drug use by injection ü Patients receiving hemodialysis • Incidence with vaccine use
Risk Factors for Hepatitis C ü Health care practice without BSI precautions ü Blood transfusion recipients before July 1992 ü Engaging in sex with infected partners and/or multiple partners ü Drug use by injection ü Patients receiving hemodialysis • #1 reason for liver transplant need in USA • Currently no vaccine 1991
Abdominal Pain What Could It Be? • Naval area – small intestine – appendix • Upper middle abdomen (called “epigastric” area) – stomach disorders • Left upper quadrant – uncommon area for pain – colon, stomach, spleen, pancreas • Right upper quadrant – gallbaldder, liver • Lower middle abdomen – colon disorder – for women: UTI, PID • Lower left abdomen – lower colon • Lower right abdomen – colon, appendicitis • Right shoulder – gallbladder • Between shoulder blades – pancreas
Assessing Abdominal Pain • Onset - when did it begin • Provocation/palliation - what makes the pain worse/better • Quality - described in the patient’s own words • Region/radiation - if the patient can use one finger the pain is localized; if the patient rubs their hands over the general entire abdomen it is diffuse • Severity - on a scale of 0 -10 (0 being no pain and 10 being the worse) • Time - how long has the pain been present?
Management GI Problems • Majority of care is supportive and aimed at treating signs and symptoms presented • Position of comfort with ability to protect airway in the case of vomiting • Abdominal pain control - need to contact medical control for medication orders • IV to replace fluid loss (vomiting, diarrhea, internal hemorrhage) • Shock (hypovolemic, septic) possible and then aggressive care & rapid transport required
Renal/ Urology System • Functions of the urinary system ümaintains blood volume ümaintains proper balance of water, electrolytes and p. H üretains key compounds in the bloodstream üexcretes waste ücontrols arterial blood pressure • Leading causes of end-stage renal failure üpoorly controlled diabetes üuncontrolled or inadequately controlled B/P
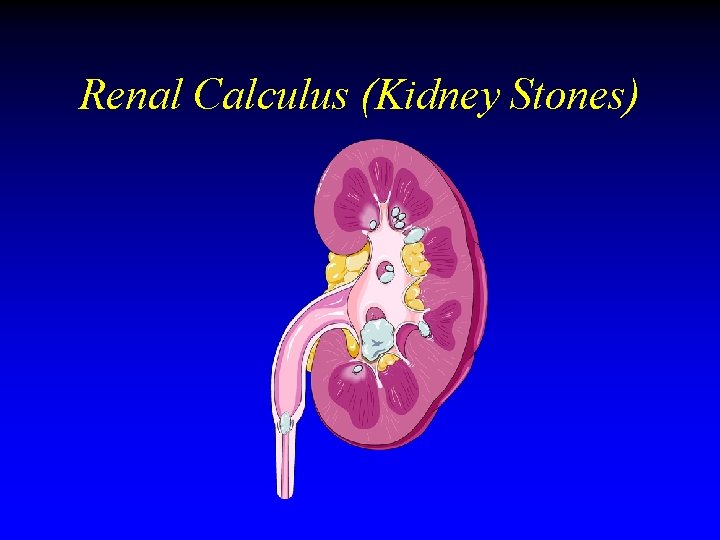
Renal Calculus (Kidney Stones)
Renal Calculus • Crystal aggregation in kidney’s collecting system • Severe pain due to movement of stone through the urinary system • Kidney stones recognized as one of the most painful of human problems • Pain starts subtle and quickly escalates
Kidney Stone • Pain starts vague over 1 flank & quickly becomes sharp in flank and radiating down and toward groin • Patient agitated, uncomfortable, restless • Skin cool, pale, clammy • B/P and heart rate elevated due to pain • Nausea & vomiting due to pain
Management Kidney Stones • Majority of care is supportive and aimed at treating signs and symptoms presented • Position of comfort with ability to protect airway in the case of vomiting • Flank pain - need to contact medical control for medication orders (ie: morphine) (Abdominal/Flank Pain SOP) • If patient is unstable with B/P <100 mm. Hg, establish IV sites and give fluid challenge (200 ml increments)
Prevention Strategies for Renal Calculus • Increase water consumption • Take daily supplements of Vitamin B 6 and magnesium (to reduce formation of oxalates) • Avoid foods that raise uric acid levels (ie: anchovies, sardines) • Reduce uric acid by eating a low-protein diet • Limit salt intake to reduce the level of calcium oxalate in the urine • Avoid foods containing calcium oxalate (ie: chocolate, celery, grapes, strawberries, beans, asparagus
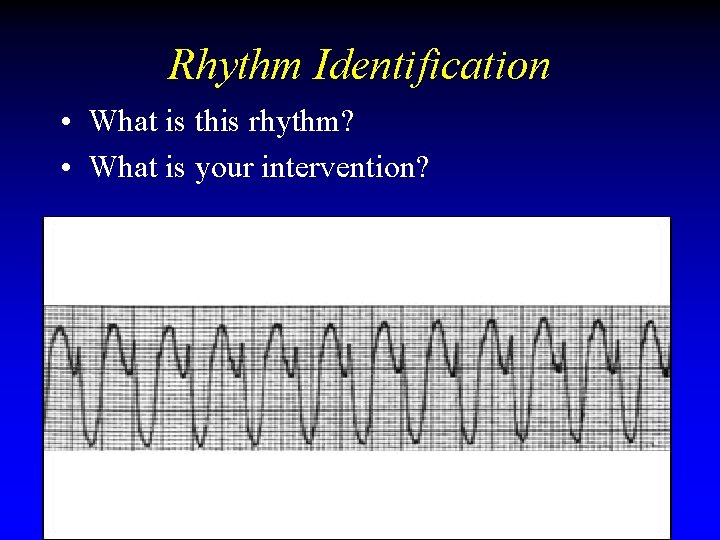
Rhythm Identification • What is this rhythm? • What is your intervention?
Ventricular Tachycardia • If stable with pulse: – Amiodarone 150 mg diluted in 100 ml D 5 W IVPB over 20 minutes or (EMS choice) – Lidocaine 0. 75 mg/kg IVP bolus – Contact Medical Control for further bolus/drip orders • If no pulse - treat like ventricular fibrillation – emphasis on good quality CPR – switch CPR compressor every 2 minutes to keep CPR effective – all shocks given at max joules & singular
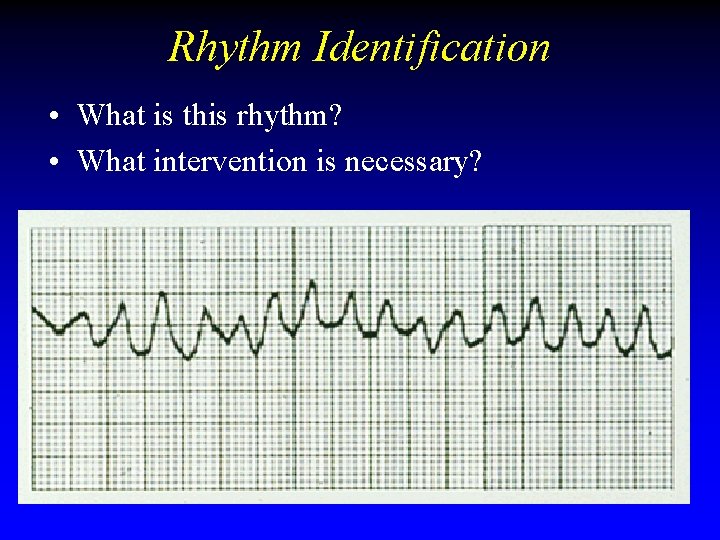
Rhythm Identification • What is this rhythm? • What intervention is necessary?
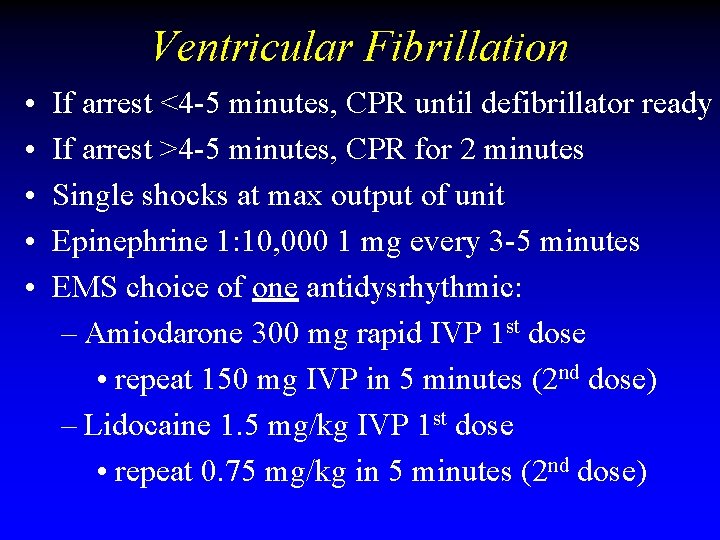
Ventricular Fibrillation • • • If arrest <4 -5 minutes, CPR until defibrillator ready If arrest >4 -5 minutes, CPR for 2 minutes Single shocks at max output of unit Epinephrine 1: 10, 000 1 mg every 3 -5 minutes EMS choice of one antidysrhythmic: – Amiodarone 300 mg rapid IVP 1 st dose • repeat 150 mg IVP in 5 minutes (2 nd dose) – Lidocaine 1. 5 mg/kg IVP 1 st dose • repeat 0. 75 mg/kg in 5 minutes (2 nd dose)
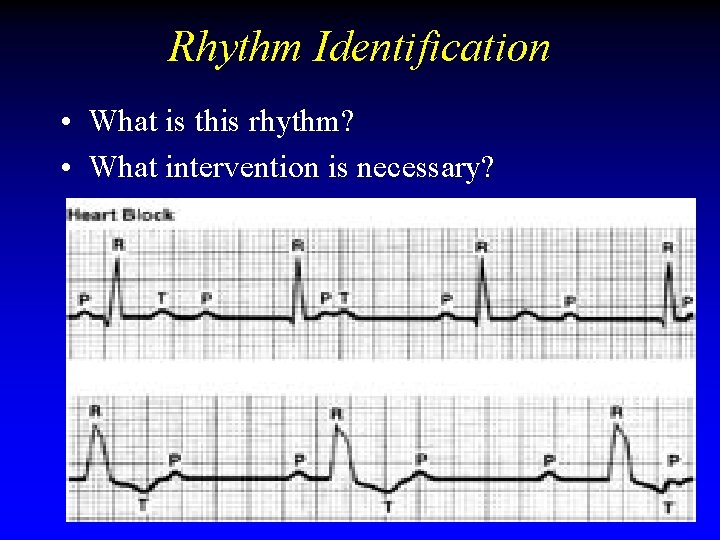
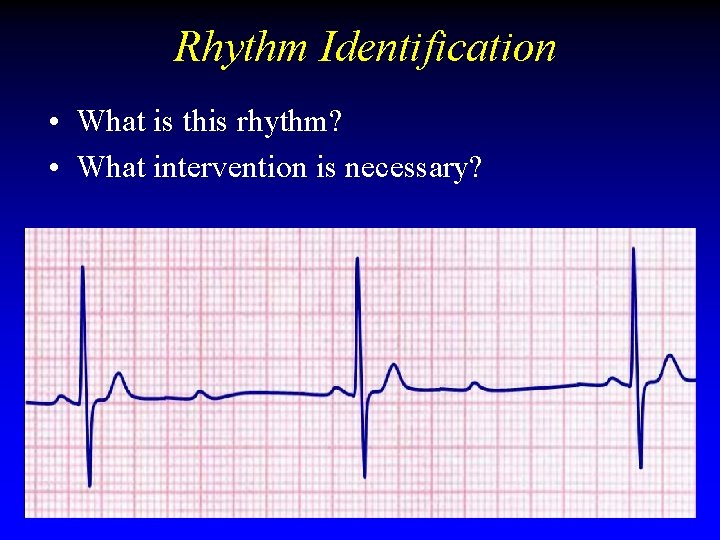
Rhythm Identification • What is this rhythm? • What intervention is necessary?
Third Degree Heart Block • If stable patient - monitor • If unstable patient narrow complex (QRS) – Atropine 0. 5 mg rapid IVP – May repeat every 3 -5 minutes to max of 3 mg – TCP if Atropine not effective • If unstable patient wide complex (QRS) – Begin TCP (Valium for comfort) – If TCP ineffective, then Atropine 0. 5 mg repeated every 3 -5 minutes to a max of 3 mg “When they’re alive, give them 0. 5”
Rhythm Identification • What is this rhythm?
Third Degree Heart Block Complete In bradycardias, always need to ask 2 questions: #1 - Is the patient stable or unstable? Stable needs monitoring Unstable needs intervention #2 - Is the QRS narrow or wide? Narrow treated initially with Atropine Wide treated initially with TCP
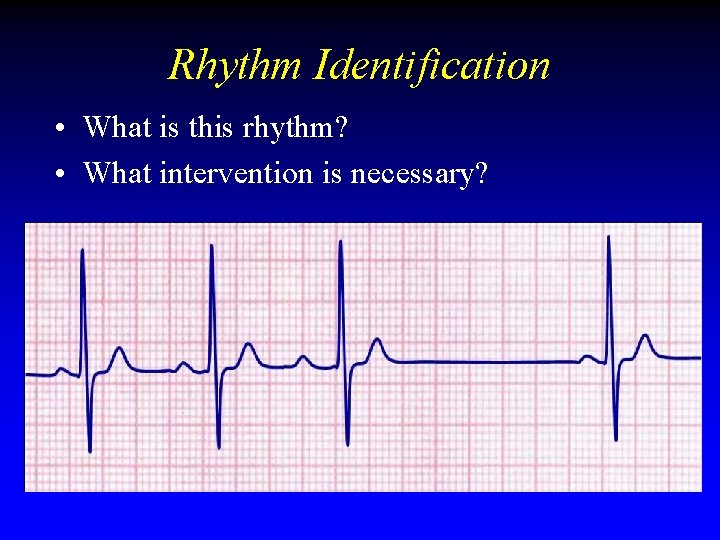
Rhythm Identification • What is this rhythm? • What intervention is necessary?
Second Degree Type II • If stable patient - monitor • If unstable patient narrow complex (QRS) – Atropine 0. 5 mg rapid IVP – May repeat every 3 -5 minutes to max of 3 mg – TCP if Atropine not effective • If unstable patient wide complex (QRS) – Begin TCP (Valium for comfort) – If TCP ineffective, then Atropine 0. 5 mg repeated every 3 -5 minutes to a max of 3 mg “When they’re alive, give them 0. 5”
Rhythm Identification • What is this rhythm? • What intervention is necessary?
Second Degree Type I - Wenckebach • If stable patient - monitor • If unstable patient narrow complex (QRS) – Atropine 0. 5 mg rapid IVP – May repeat every 3 -5 minutes to max of 3 mg – TCP if Atropine not effective • If unstable patient wide complex (QRS) – Begin TCP (Valium for comfort) – If TCP ineffective, then Atropine 0. 5 mg repeated every 3 -5 minutes to a max of 3 mg “When they’re alive, give them 0. 5”
Rhythm Identification • What is this rhythm (the patient has no pulse)? • What intervention is necessary? There is no pulse!
PEA (rate under 60) • Emphasis will be on good quality CPR • CPR is 30: 2 (compressions to ventilations) • After intubation, breaths delivered once every 6 -8 seconds, compressor doesn’t stop • Search for causes (6 H’s, 5 T’s) & treat them! • Epinephrine 1: 10, 000 1 mg every 3 -5 minutes • If rate <60, Atropine 1 mg every 3 -5 minutes (max 3 mg) • If rate >60, just Epinephrine & good CPR