
CPC vignettes challenging cases in the elderly Dr




















- Slides: 46
CPC vignettes – challenging cases in the elderly Dr Neil Rabin Consultant Haematologist University College London Hospital & North Middlesex University Hospital
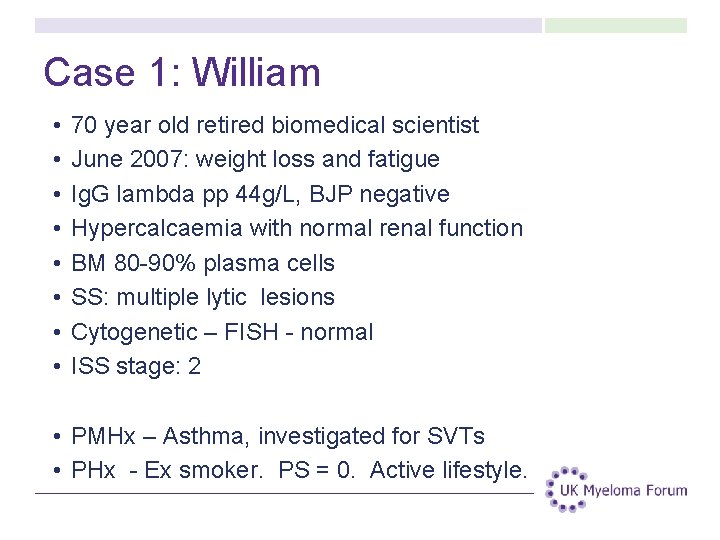
Case 1: William • • 70 year old retired biomedical scientist June 2007: weight loss and fatigue Ig. G lambda pp 44 g/L, BJP negative Hypercalcaemia with normal renal function BM 80 -90% plasma cells SS: multiple lytic lesions Cytogenetic – FISH - normal ISS stage: 2 • PMHx – Asthma, investigated for SVTs • PHx - Ex smoker. PS = 0. Active lifestyle.
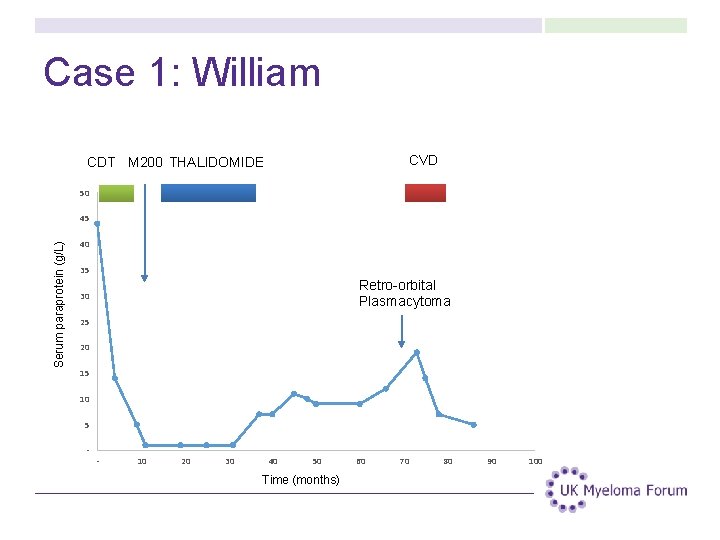
Case 1: William • Diagnosed with symptomatic myeloma (age 70) • Treated with Cyclophosphamide Dexamethasone Thalidomide (CTD) for 4 months at local hospital • PP falls from 44 g/L to 13 g/L (partial response) • Echocardiogram – normal • Creatinine clearance – normal How would you treat him ?
Case 1: William Decision – what treatment now? • • Continue CTD to maximal response Switch to salvage treatment (Velcade based) Proceed to ASCT Other
Case 1: William CVD CDT M 200 THALIDOMIDE 50 Serum paraprotein (g/L) 45 40 35 Retro-orbital Plasmacytoma 30 25 20 15 10 5 - - 10 20 30 40 50 Time (months) 60 70 80 90 100
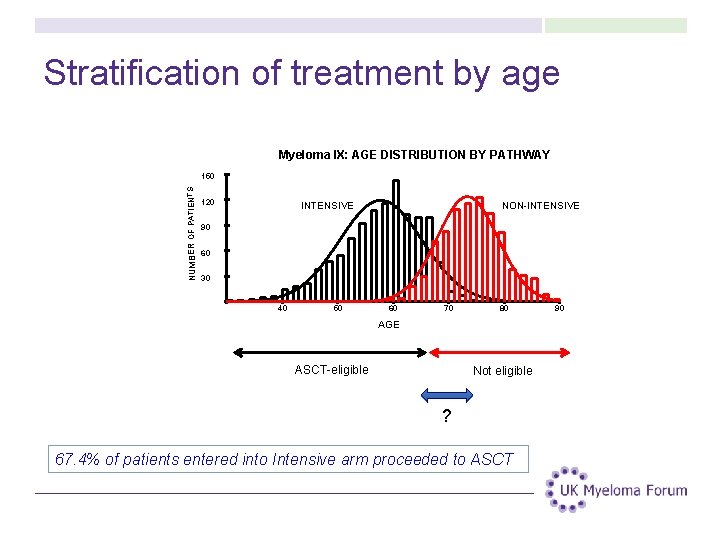
Stratification of treatment by age Myeloma IX: AGE DISTRIBUTION BY PATHWAY NUMBER OF PATIENTS 150 120 INTENSIVE NON-INTENSIVE 90 60 30 40 50 60 70 80 AGE ASCT-eligible Not eligible ? 67. 4% of patients entered into Intensive arm proceeded to ASCT 90
How do we decide if a patient is for intensive therapy (ASCT eligible) ? • • Age Performance status Organ Function Disease biology Adequate stem cells Patient choice
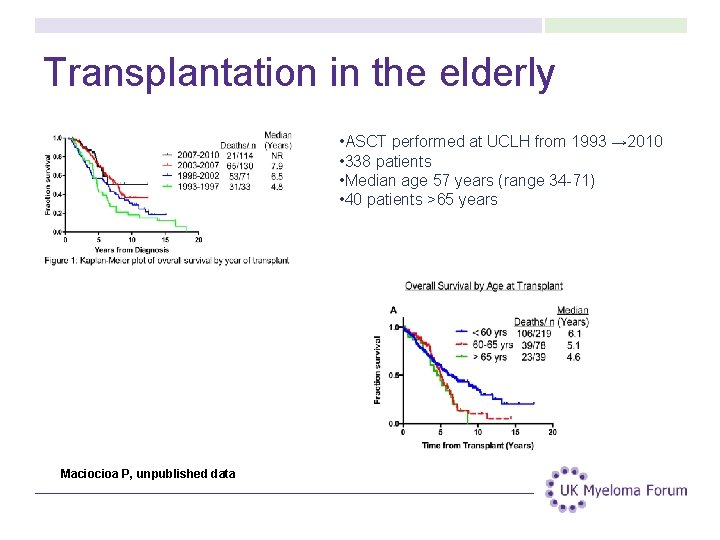
Transplantation in the elderly • ASCT performed at UCLH from 1993 → 2010 • 338 patients • Median age 57 years (range 34 -71) • 40 patients >65 years Maciocioa P, unpublished data
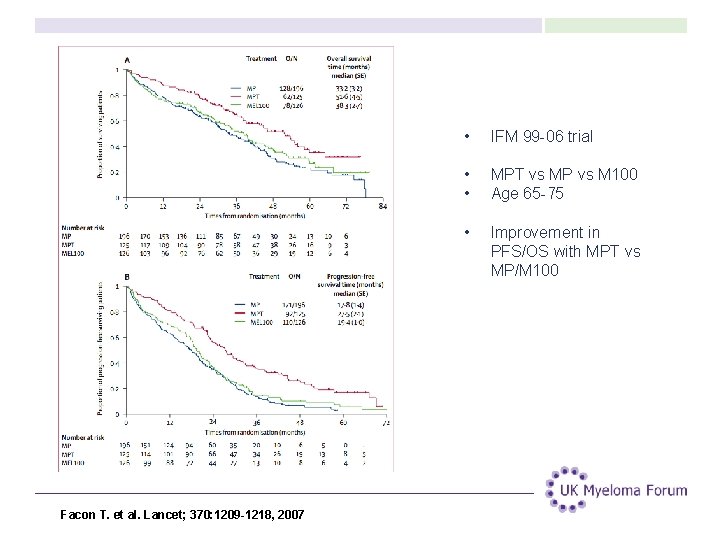
Facon T. et al. Lancet; 370: 1209 -1218, 2007 • IFM 99 -06 trial • • MPT vs MP vs M 100 Age 65 -75 • Improvement in PFS/OS with MPT vs MP/M 100
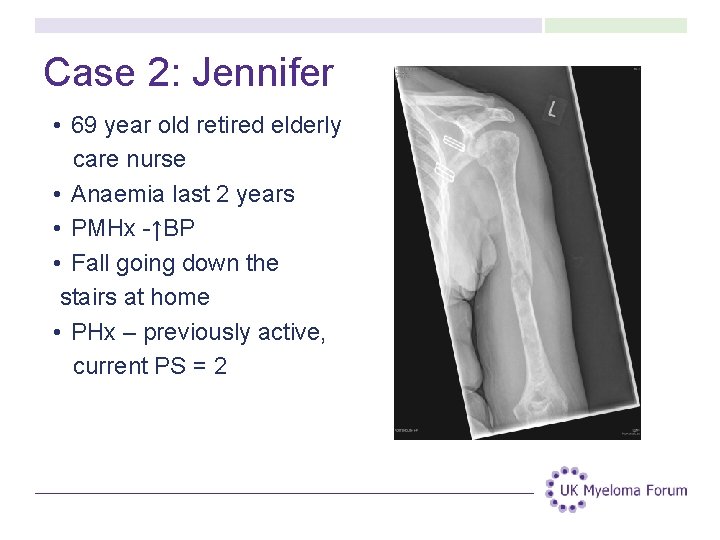
Case 2: Jennifer • 69 year old retired elderly care nurse • Anaemia last 2 years • PMHx -↑BP • Fall going down the stairs at home • PHx – previously active, current PS = 2
Case 2: Jennifer • CT fracture through lytic lesion with extraosseous tumour • Biopsy lytic lesion = plasma cell neoplasm • MRI: multiple lytic lesions vertebrae, sacrum, femora, fractures T 6, L 1, L 5, small paravertebral mass at T 6 • Haemoglobin 9 g/d. L, Creatinine 107 umol/L, Calcium normal • Ig. D lambda PP 12 g/L + Lambda LC • Urinary BJP 2. 72 g/L • BM 80 -90% plasma cells • ISS stage 3 (beta-2 m 7. 7 mg/L) • Cytogenetic – FISH failed
Case 2: Jennifer Decision – what initial treatment? • • Aim for induction treatment prior to ASCT MPV CTDa or MPT Clinical trial
Case 2: Jennifer • • Decision for non-intensive treatment Declined clinical trial entry Treated with MPV November 2012 Intra-medullary nail inserted November 2012 Single fraction radiotherapy to humerus Completed 8 cycles – achieving CR Lambda LC 15, 571 mg/l pre-cycle 1 3, 274 mg/l pre-cycle 2 SFLC normal from cycle 4 onward “Velcade eyes” cycle 6
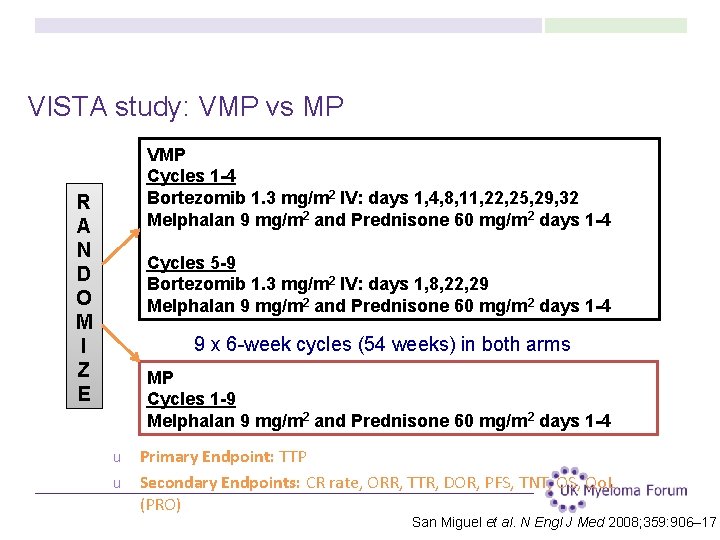
VISTA study: VMP vs MP VMP Cycles 1 -4 Bortezomib 1. 3 mg/m 2 IV: days 1, 4, 8, 11, 22, 25, 29, 32 Melphalan 9 mg/m 2 and Prednisone 60 mg/m 2 days 1 -4 R A N D O M I Z E Cycles 5 -9 Bortezomib 1. 3 mg/m 2 IV: days 1, 8, 22, 29 Melphalan 9 mg/m 2 and Prednisone 60 mg/m 2 days 1 -4 9 x 6 -week cycles (54 weeks) in both arms MP Cycles 1 -9 Melphalan 9 mg/m 2 and Prednisone 60 mg/m 2 days 1 -4 u u Primary Endpoint: TTP Secondary Endpoints: CR rate, ORR, TTR, DOR, PFS, TNT, OS, Qo. L (PRO) San Miguel et al. N Engl J Med 2008; 359: 906– 17
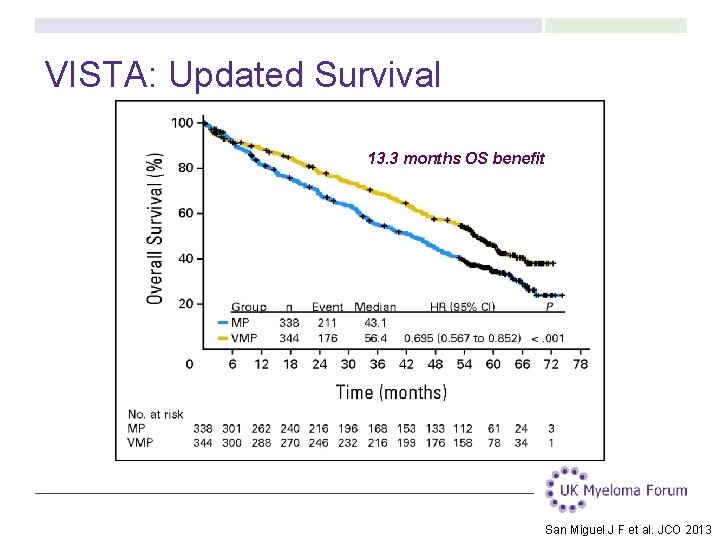
VISTA: Updated Survival 13. 3 months OS benefit San Miguel J F et al. JCO 2013
Case 3: Ruth • 68 year old retired secretary • PMHx – 2005: invasive ductal breast ca – treated with lumpectomy, RT, tamoxifem / arimidex • 2008: Anaemia, Back pain, Epistaxis • Ig. G lambda PP 82 g/L, BJP 0. 74 g/L • BM 80% plasma cells • SS: multiple lytic lesions • Cytogenetic – FISH – t(4: 14) • ISS stage: 2
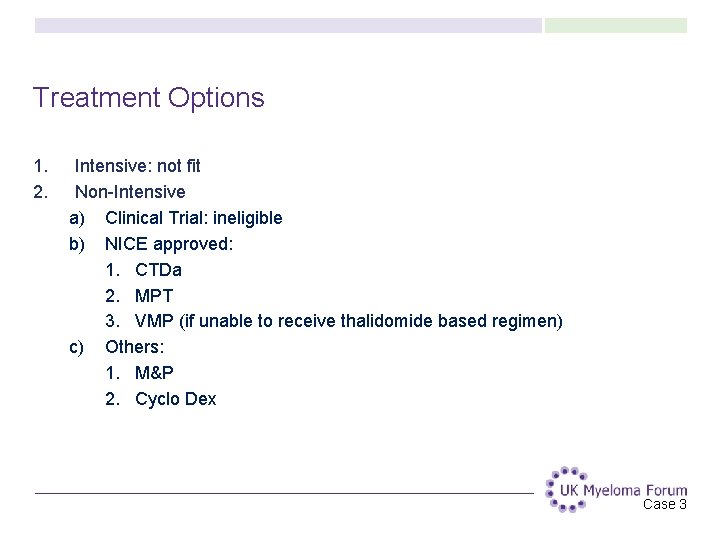
Treatment Options 1. 2. Intensive: not fit Non-Intensive a) Clinical Trial: ineligible b) NICE approved: 1. CTDa 2. MPT 3. VMP (if unable to receive thalidomide based regimen) c) Others: 1. M&P 2. Cyclo Dex Case 3
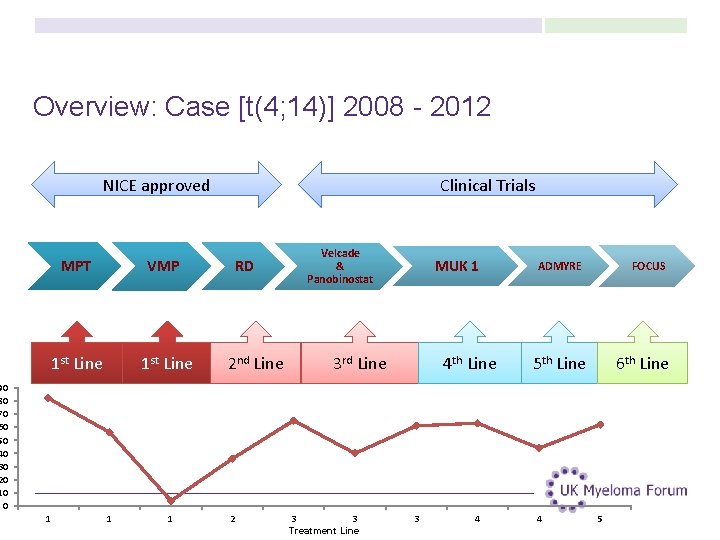
Case 3: Ruth • MPT x 3 – Bowel disturbance, neutropaenia – MR (PP 82 → 56 g/L) • VMP x 8 – Biweekly to weekly bortezomib – Weekly bortezomib at 1. 3 mg/m 2→ 1 mg/m 2 (progressive PN) – VGPR (PP 56 → 4 g/L) • Relapsed 2 years later (2010): • Lenalidomide and Dex x 4 – PD on treatment (pp 36 → 65 g/L)
Case 3: Ruth Decision – what treatment now? • • Velcade re-treatment Bendamustine Clinical trial Other
Overview: Case [t(4; 14)] 2008 - 2012 NICE approved MPT VMP 1 st Line Clinical Trials RD 2 nd Line Velcade & Panobinostat MUK 1 3 rd Line 4 th Line FOCUS ADMYRE 5 th Line 6 th Line 90 80 70 60 50 40 30 20 10 0 1 1 1 2 3 3 Treatment Line 3 4 4 5
Case 4: John • 76 year old Afro-Caribbean retired builder • 6 month history of exertional dyspnoea and marked peripheral oedema • Repeat admissions to hospital • PMHx – Diabetes / ↑BP / ↑Cholesterol / Atrial fibrillation • Echocardiogram – 30% LVEF, severe concentric LVH • Lambda LC noted in serum and urine – Kappa FLC 11 mg/L, lambda FLC 864 mg/L – Haemoglobin / Creatinine / Calcium - normal • Bone marrow – 75% plasma cells • Skeletal survey normal
Case 4: John Decision – what is the likely diagnosis? • • Symptomatic myeloma AL cardiac amyloidosis Cardiac failure (unrelated) Other
Case 4: John • Referred to National Amyloidosis Centre – Echocardiogram characteristic of amyloid IVSd 1. 9 cm, moderate to severely impaired LV systolic function, grade 2 diastolic dysfunction. – ECG showed atrial flutter, variable AV block, ↓ QRS – Troponin-t 0. 1 ng/m. L (normal), NT pro BNP 430 pmol/L – No visceral amyloid detected on SAP scintography • Differential diagnosis of – AL amyloid – Senile cardiac amyloid with co-existent myeloma – Hereditary cardiac amyloid with co-existent myeloma
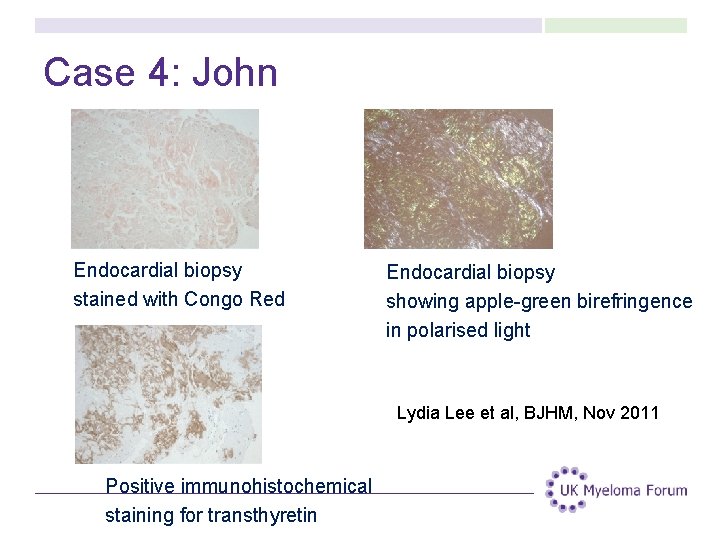
Case 4: John Endocardial biopsy stained with Congo Red Endocardial biopsy showing apple-green birefringence in polarised light Lydia Lee et al, BJHM, Nov 2011 Positive immunohistochemical staining for transthyretin
Case 4: John • Hereditary cardiac amyloid (TTR variant) – Reviewed regularly at the NAC and local cardiologist – Cardiac medication (Enalapril, Digoxin and Furosemide) adjusted. Anti-coagulated for mural thrombus – Cardiac function remained stable for 2 years (NYHA II) – Treatment – low salt diet, fluid management, diuretics • Myeloma – Declined chemotherapy (? initial treatment needed) – Inappropriate to treat for AL cardiac amyloid • Died 2 years later
Cardiac amyloid • Deposition of amyloid fibrils (cardiac and other tissues) • Common findings – Low amplitude QRS complexes (<1 m. V in pre-cordial leads or <0. 5 m. V in all limb leads) – Pseudoinfarction pattern (Q waves in consecutive leads) – Conduction delays + arrhythmias (commonly AF) – LV wall thickening in the absence of hypertension • AL amyloid (associated with a plasma cell clone) • Senile systemic amyloid (wild type transthyretin) • Hereditary cardiac amyloid (ATTR)
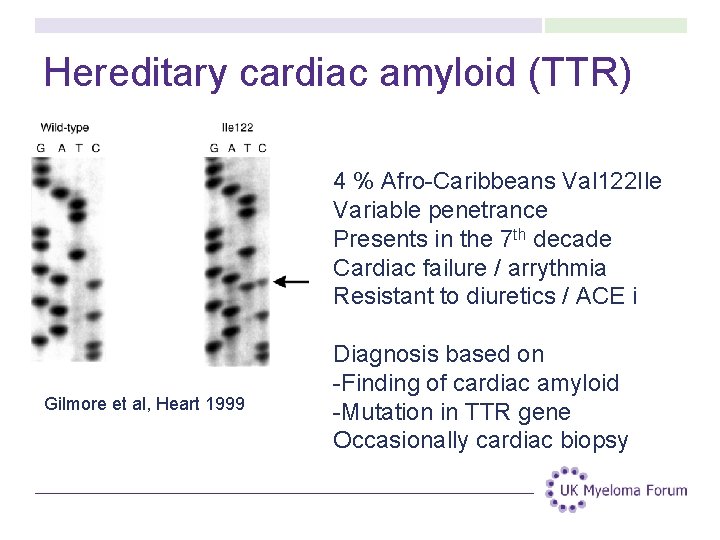
Hereditary cardiac amyloid (TTR) 4 % Afro-Caribbeans Val 122 Ile Variable penetrance Presents in the 7 th decade Cardiac failure / arrythmia Resistant to diuretics / ACE i Gilmore et al, Heart 1999 Diagnosis based on -Finding of cardiac amyloid -Mutation in TTR gene Occasionally cardiac biopsy
Case 5: Joan • 86 year old artist • Referred to general haematology clinic with normocytic anaemia (Hb 9. 8 g/d. L) developed previous 2 years • Symptom - fatigue, and exertional chest pain • Ig. G kappa PP 16 g/L, no BJP, normal SFLC ratio • Creatinine, Calcium - normal • BM 20% plasma cells • SS: no lytic lesions • Cytogenetic – FISH – 1 q gain • ISS stage: 1 • PMHx - ↑BP, Hiatus hernia, previous Cystitis • PHx - Lives alone, independent with ADL
Case 5: Joan Decision – how would you treat? • • Observation only Treatment for anaemia alone Systemic chemotherapy Other
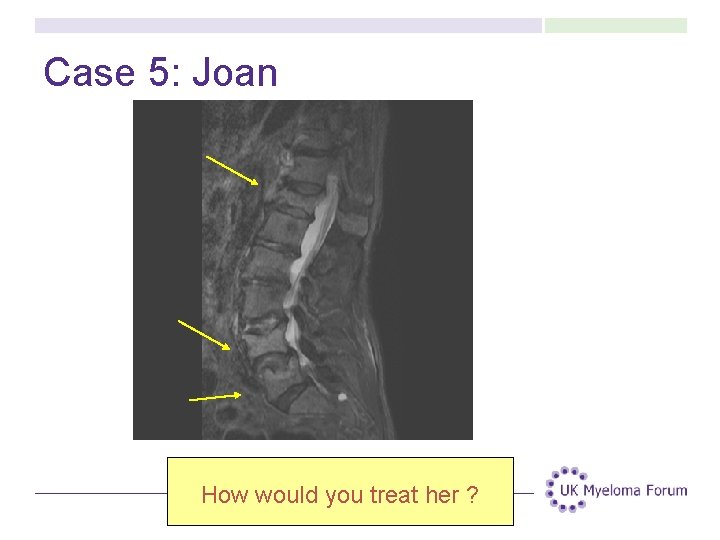
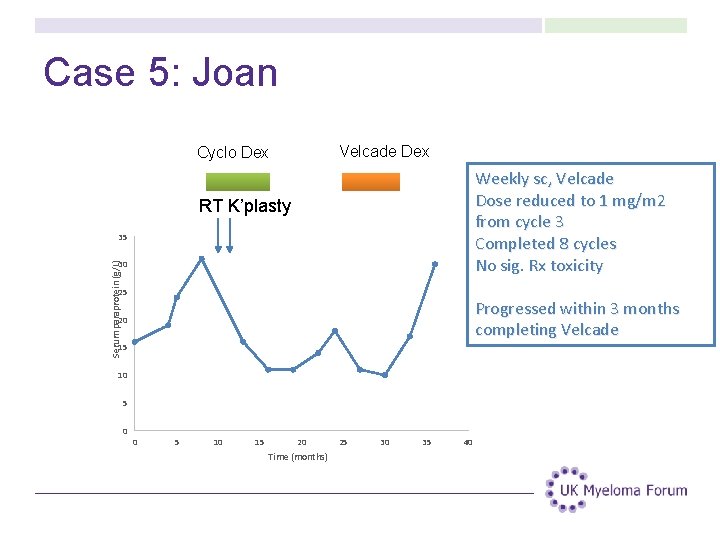
Case 5: Joan • Adopted watchful waiting – Reviewed by cardiologist – normal myocardial perfusion scan – Erythropoetin, rise in haemaglobin → 11 g/L – Bisphonates (absence of bone disease) • Observed for 9 months Asymptomatic • Presented with acute lower back pain – Lower back pain whilst gardening – Plain x-rays showed fractures T 12, L 4 and L 5 – Paraprotein increase from 16 g/L → 24 g/L
Case 5: Joan How would you treat her ?
Case 5: Joan Decision – how would you treat her? • • Systemic chemotherapy + Analgesia Systemic chemotherapy + Radiotherapy Systemic chemotherapy + Vertebral augmentation Other
Case 5: Joan • Admitted for pain control – Treated with long acting and short acting opiate analgesia – Received palliative RT to lumbar spine (8 Gy) – Started on Cyclophosphamide po weekly, and Dexamethasone 20 mg daily for 4 days / month • Discharged when mobility improved • Ongoing problems with pain – Multiple level kyphoplasty at Royal National Orthopaedic Hospital (Sean Molloy) – Very good symptomatic benefit – Support from palliative care team, and liaison with primary care
Case 5: Joan Velcade Dex Cyclo Dex Weekly sc, Velcade Dose reduced to 1 mg/m 2 from cycle 3 Completed 8 cycles No sig. Rx toxicity RT K’plasty 35 Serum paraprotein (g/L) 30 25 Progressed within 3 months completing Velcade 20 15 10 5 0 0 5 10 15 20 Time (months) 25 30 35 40
Case 6: Arthur • 97 year old • Known diagnosis of Alzheimer’s disease – Mobile with a Zimmer Frame – Lives at home with carers – washing/cooking/cleaning – Memantadine. • PMHx - ↑BP, GORD, BPH • 2012: 6 week history – Confusion – Lower back pain – Bed bound
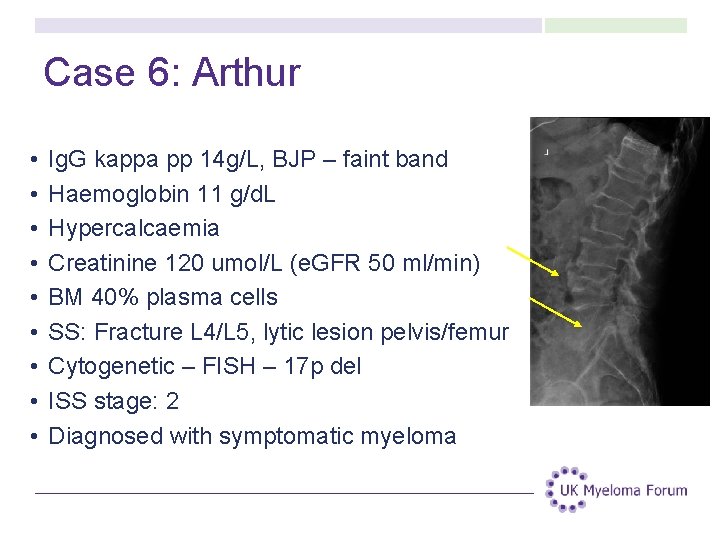
Case 6: Arthur • • • Ig. G kappa pp 14 g/L, BJP – faint band Haemoglobin 11 g/d. L Hypercalcaemia Creatinine 120 umol/L (e. GFR 50 ml/min) BM 40% plasma cells SS: Fracture L 4/L 5, lytic lesion pelvis/femur Cytogenetic – FISH – 17 p del ISS stage: 2 Diagnosed with symptomatic myeloma
Case 6: Arthur Decision – how would you treat? • • Analgesia + Bisphonate treatment + Radiotherapy + Dexamethasone + Systemic chemotherapy
Case 6: Arthur • Pain control – Palliative care input – Opiate analgesia • Treatment – Dexamethasone (low dose). Decision not systemic RX – Bisphophonate – Radiotherapy to lumbar spine and left ilium • Discharged home, returned to previous baseline – Re-instituted package of care – Community palliative care input – Haematology day unit
Case 6: Arthur • Well for 3 months • Decline mobility – Pain weight bearing right leg. Unable to mobilise • Re-assessed – Radiotherapy – right femur + sacrum (symptom better) – Systemic chemotherapy • ? Imid based (need for anticoagulation) • ? Proteosome inhibitor (able to visit hospital) – Velcade sc weekly at 1 mg/m 2, with Dex (10 mg 2/7) • PP 14 → < 3 g/L (VGPR). Received 4 cycles, stop. • No treatment emergent problems • Stable for 9 months → RIP
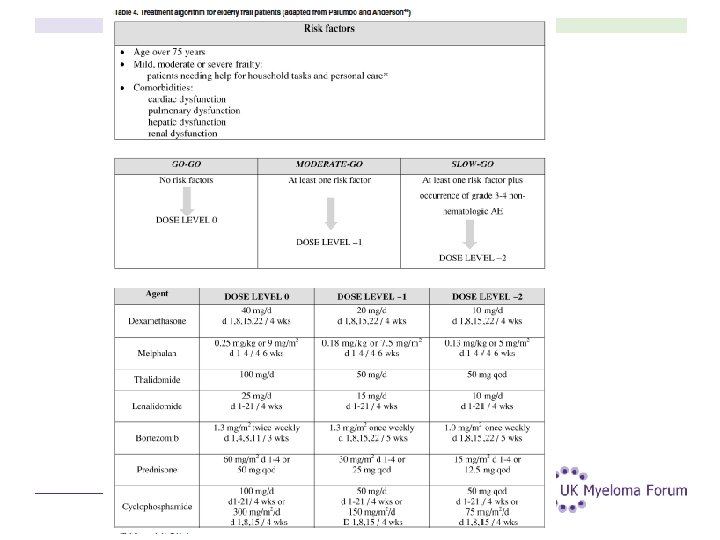
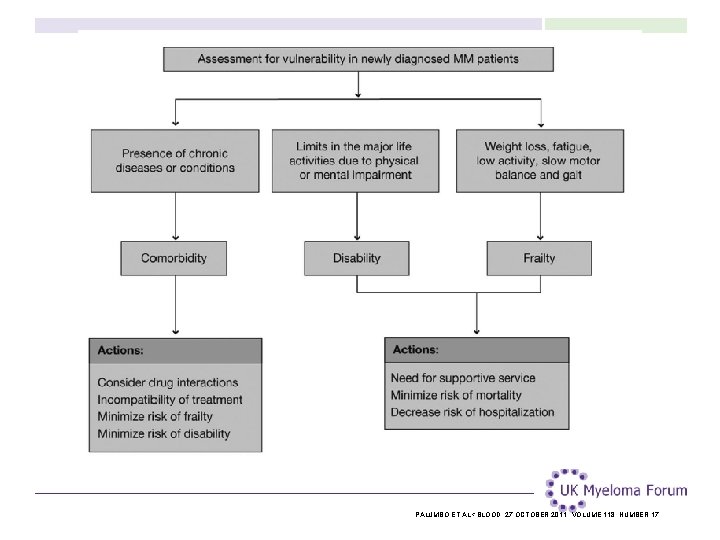
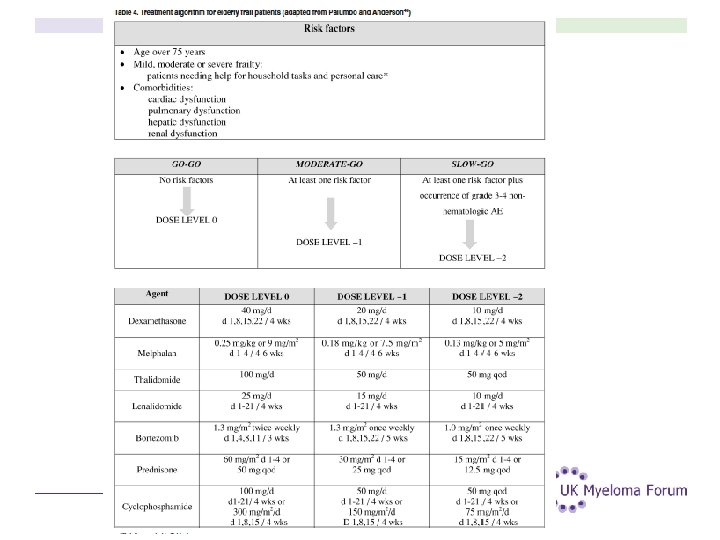
Frail elderly patient • Dependent on co-morbidities – more likely > 75 yrs. • Assessments of frailty / co-morbidities – Comprehensive geriatric assessment (CGA) – Cumulative illness rating scale (CIRS-G) • Important to note the impact of disease on performance status • Ability to benefit from novel agents • Modification of treatment dose and schedule • Balance goal of depth of response with minimising toxicities
PALUMBO ET AL< BLOOD, 27 OCTOBER 2011 VOLUME 118, NUMBER 17
Summary • • Fit elderly should be treated as any other patient Dependent on co-morbidities – more likely > 75 yrs. Assessments of frailty / co-morbidities Important to note the impact of disease on performance status Ability to benefit from novel agents Modification of treatment dose and schedule Balance goal of depth of response with minimising toxicities Consider other causes for co-existent medical problems
UCLH • Clinical team Kwee Yong / Shirley D’Sa / Ali Rismani / Rakesh Popat Jaimal Kothari / Dean Smith / Laura Percy / Lydia Lee • Clinical Nurse Specialists Aviva Cerner / Samantha Darby Jude Dorman • Clinical Trials Janet Lyons – Lewis / Diane Gowers North Middlesex • • Clinical Nurse Specialist Millicent Blake – Mc. Coy Clinical Trials Christy Griffin-Pritchard