
Clinical assessment Aims 1 Is it a stroke





















- Slides: 44
Clinical assessment Aims (1) Is it a stroke? (MSD) (2) What part of the brain is affected? (3) What caused this stroke? Is it a haemorrhage or an infarct? Can we prevent a further stroke? (4) What are this patient’s problems? + (5) What can we do to treat this patient? (RIL)
Is it a stroke? (a) The setting (or demographics) • • • age hypertension smoking diabetes cholesterol presence of other vascular disease (b) The nature of the event • • • onset course focal vs general symptoms “negative” symptoms (loss of function) associated symptoms
Stroke mimics • Migraine • Epilepsy • Structural brain lesions – SDH, Tumour, abscess • Metabolic/toxic disorders – hypoglycemia • • Vestibular disorders Psychological disorders Demyelination Mononeuropathy
What part of the brain is affected?
Localisation: Why bother? 1. Confirms the diagnosis of stroke 2. Allows better selection of imaging 3. Gives an indication of cause 4. Gives an indication of prognosis
Localising the lesion depends on a basic understanding of neuroanatomy • • • the cortex the homunculus deep white matter the brainstem the vascular supply
What part of the brain is affected? • Left or right • Carotid territory or vertebrobasilar territory • Cerebral hemispheres or brainstem • Cortex or deep white matter
Neuroanatomy 1: Left or Right? • Crossing of sensory and motor fibres – corticospinal tracts - lower medulla – spinothalamic fibres - spinal cord – dorsal columns - upper medulla • Cerebellar lesions result in ipsilateral deficits • The “dominant hemisphere” – Language function localises to left hemisphere – Awareness of body localises to right hemisphere • Visual pathways – monocular vs homonymous deficits
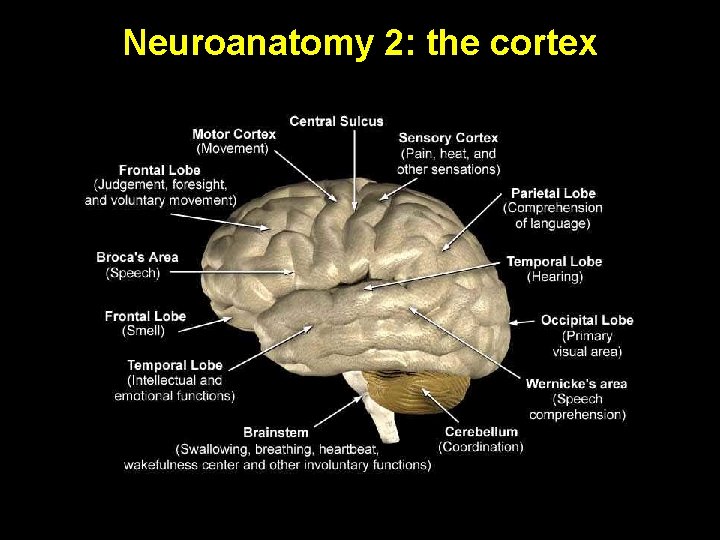
Neuroanatomy 2: the cortex
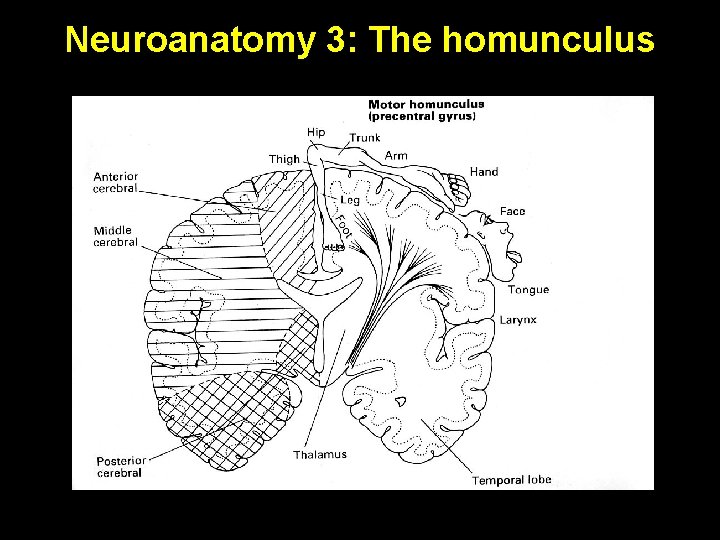
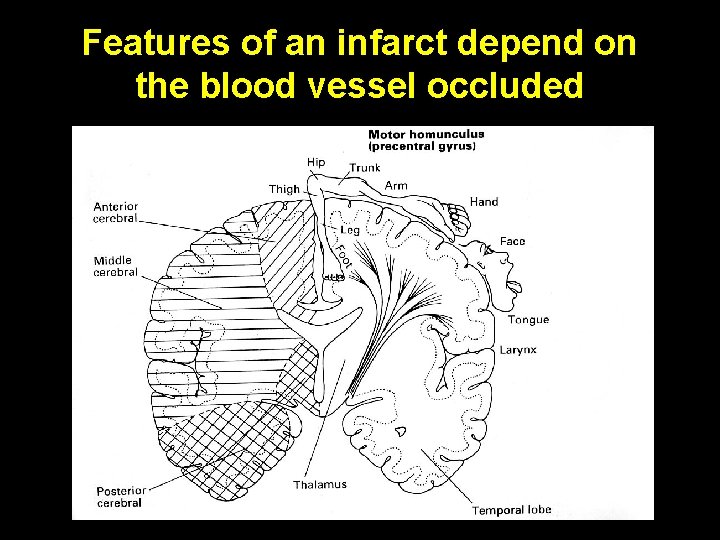
Neuroanatomy 3: The homunculus
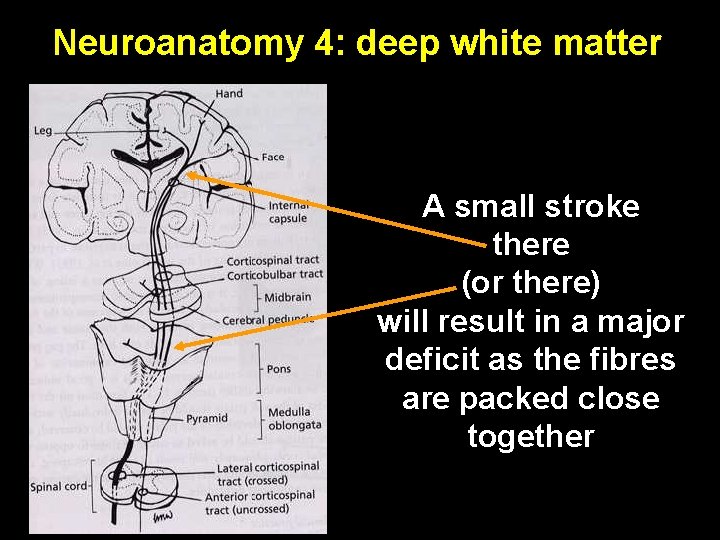
Neuroanatomy 4: deep white matter A small stroke there (or there) will result in a major deficit as the fibres are packed close together
Neuroanatomy 5: the brainstem Cranial nerve signs suggest localisation to (and within) the brainstem
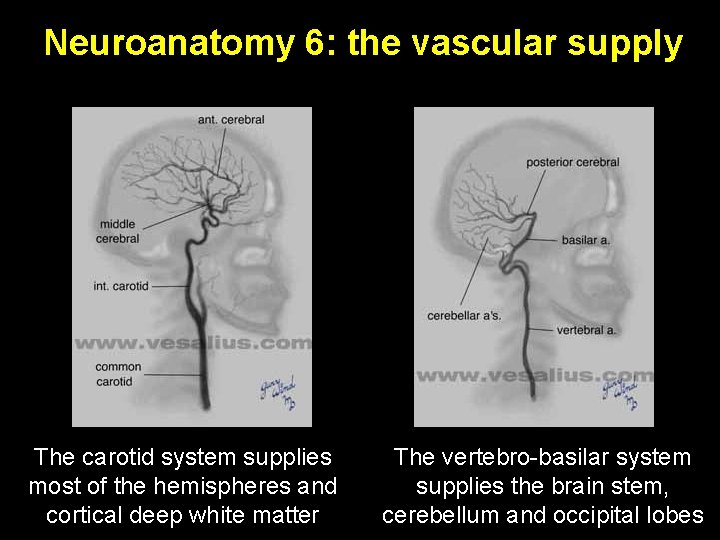
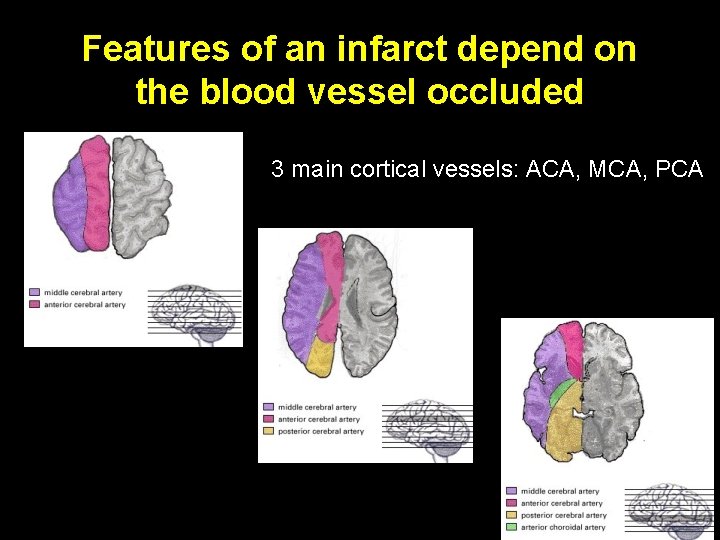
Neuroanatomy 6: the vascular supply The carotid system supplies most of the hemispheres and cortical deep white matter The vertebro-basilar system supplies the brain stem, cerebellum and occipital lobes
So, from the symptoms and signs you observe, you can tell: • what side of the brain is affected • whether the lesion is in the brainstem (a brainstem stroke) • whether the cortex is involved (a cortical stroke) • or if the lesion is in the deep white matter (a lacunar stroke) • what blood vessel is involved
Some clinical vignettes
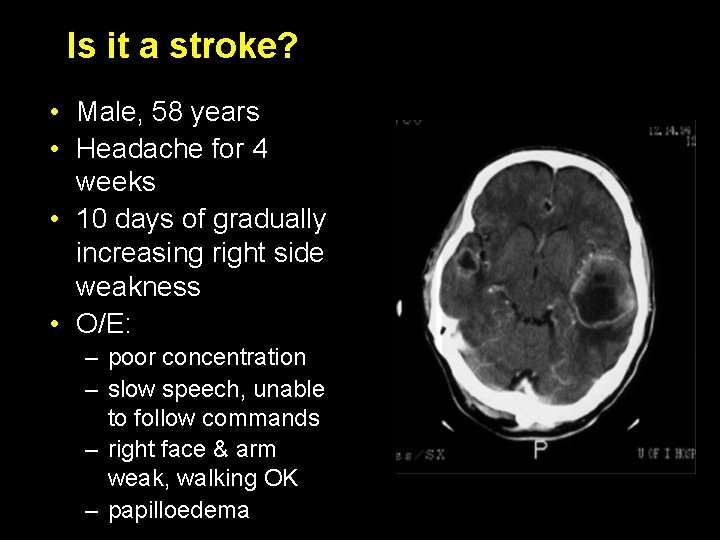
Is it a stroke? • Male, 58 years • Headache for 4 weeks • 10 days of gradually increasing right side weakness • O/E: – poor concentration – slow speech, unable to follow commands – right face & arm weak, walking OK – papilloedema
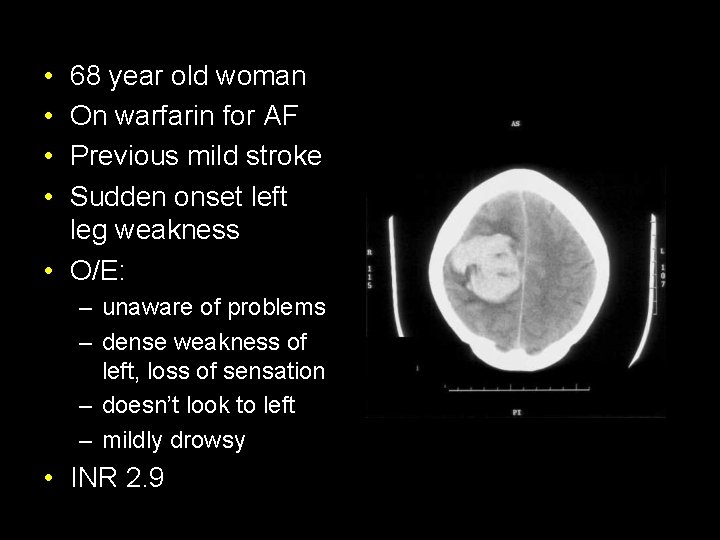
• • 68 year old woman On warfarin for AF Previous mild stroke Sudden onset left leg weakness • O/E: – unaware of problems – dense weakness of left, loss of sensation – doesn’t look to left – mildly drowsy • INR 2. 9
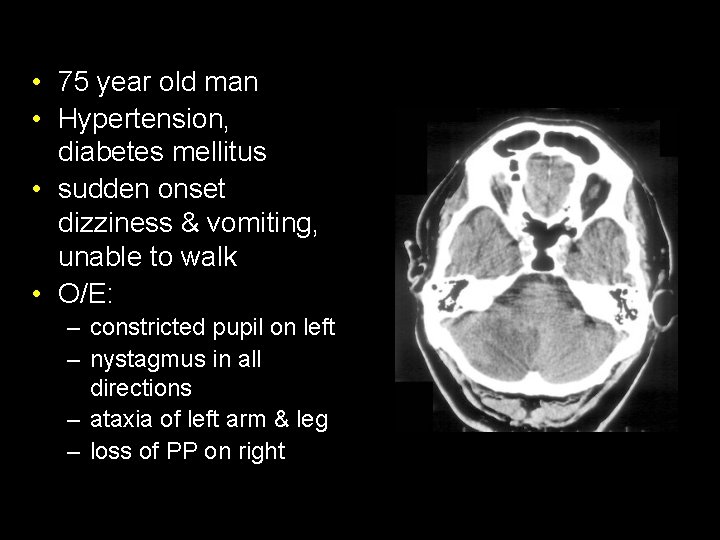
• 75 year old man • Hypertension, diabetes mellitus • sudden onset dizziness & vomiting, unable to walk • O/E: – constricted pupil on left – nystagmus in all directions – ataxia of left arm & leg – loss of PP on right
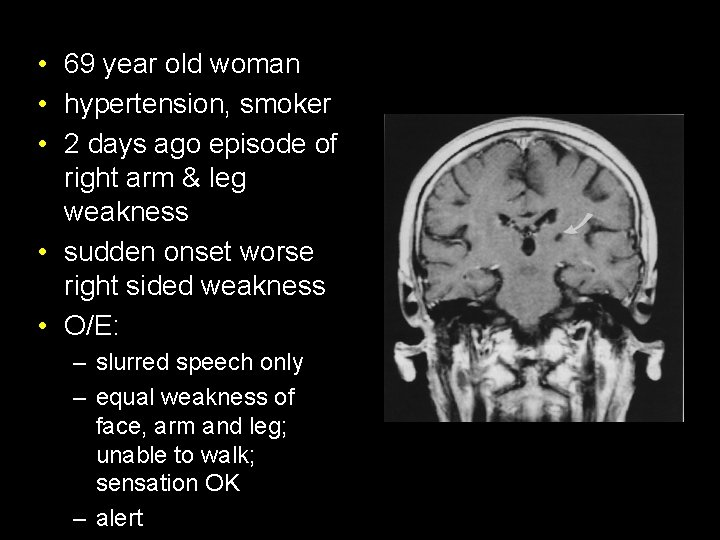
• 69 year old woman • hypertension, smoker • 2 days ago episode of right arm & leg weakness • sudden onset worse right sided weakness • O/E: – slurred speech only – equal weakness of face, arm and leg; unable to walk; sensation OK – alert
What caused this stroke?
The pathology 2 processes result in a stroke: (1) Infarction – 85% of strokes – occlusion of a vessel by thrombosis or embolus (2) Haemorrhage – 15% of strokes – rupture of a vessel results in bleeding into the substance of the brain
Intracerebral Haemorrhage • Usually caused by hypertension • thickening & weakening of walls of small arteries/arterioles • formation of small aneurysms • rupture produces a large blood filled cavity that acts as a SOL • typically basal ganglia or thalamus
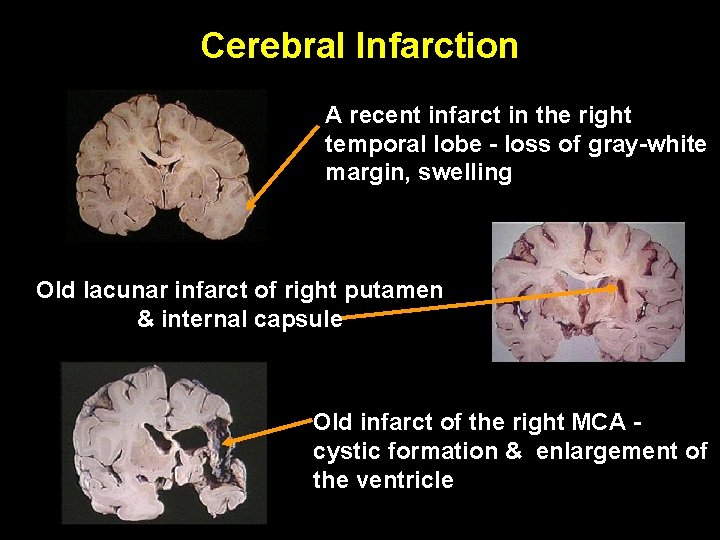
Cerebral Infarction • Infarction is caused by failure of blood flow to a region • damage to the brain is due to: – ischaemia – oedema surrounding the ischaemic area • sources of occlusion of vessels: – thrombosis of small vessels - hypertensive lipohyalinosis - lacunar infarcts – thrombosis of larger vessels – embolus from extracranial vessels or heart
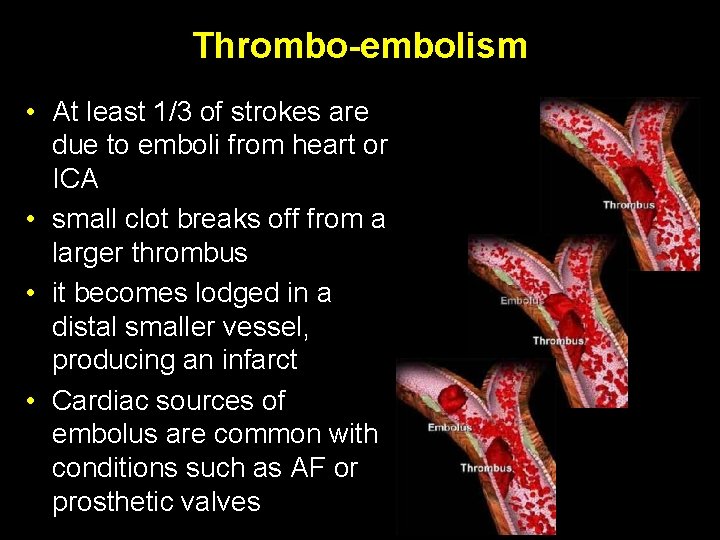
Thrombo-embolism • At least 1/3 of strokes are due to emboli from heart or ICA • small clot breaks off from a larger thrombus • it becomes lodged in a distal smaller vessel, producing an infarct • Cardiac sources of embolus are common with conditions such as AF or prosthetic valves
Cerebral Infarction A recent infarct in the right temporal lobe - loss of gray-white margin, swelling Old lacunar infarct of right putamen & internal capsule Old infarct of the right MCA cystic formation & enlargement of the ventricle
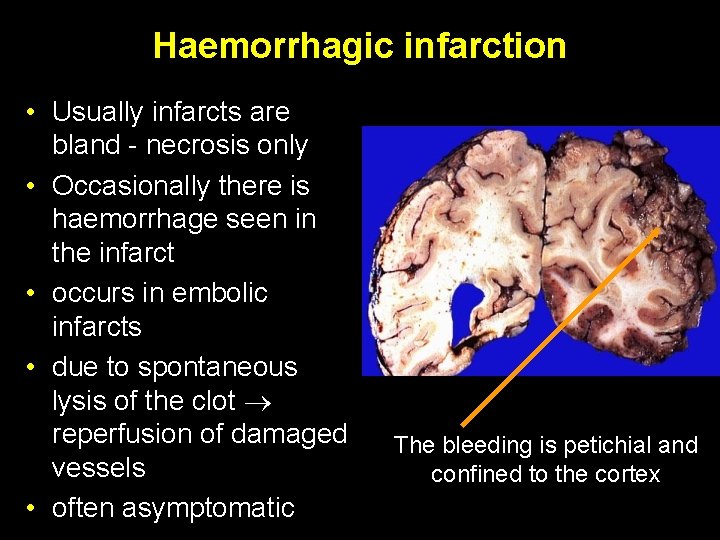
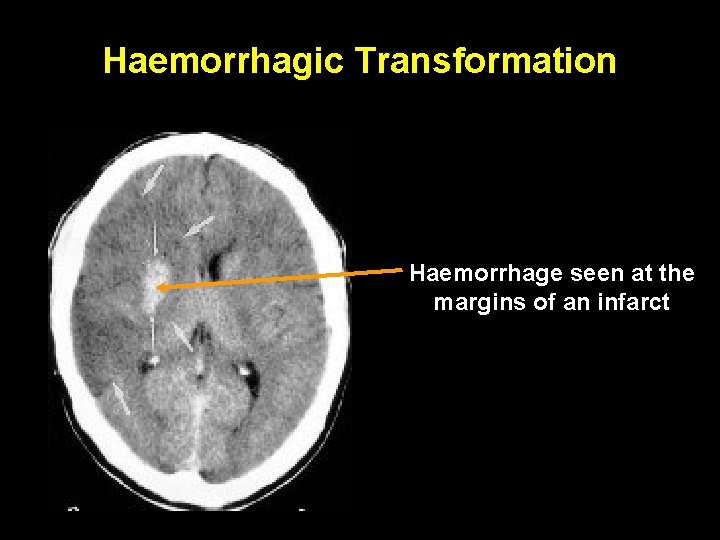
Haemorrhagic infarction • Usually infarcts are bland - necrosis only • Occasionally there is haemorrhage seen in the infarct • occurs in embolic infarcts • due to spontaneous lysis of the clot reperfusion of damaged vessels • often asymptomatic The bleeding is petichial and confined to the cortex
Features of an infarct depend on the blood vessel occluded 3 main cortical vessels: ACA, MCA, PCA
Features of an infarct depend on the blood vessel occluded
What was the cause in THIS patient?
Distinguishing haemorrhage from infarct clinically is difficult & unreliable • On history: • severe headache • vomiting within 2 hours of onset • On examination: • marked hypertension • altered conscious state • Increasing evidence to suggest that mild events may be due to PICH • Scanning is the only acceptable method
Brain Imaging • Rationale: – to exclude (rare) stroke mimics eg SDH – to distinguish between haemorrhage and infarct • Plain CT is the imaging technique of choice – available, rapid – reliably differentiates haemorrhage: blood is white
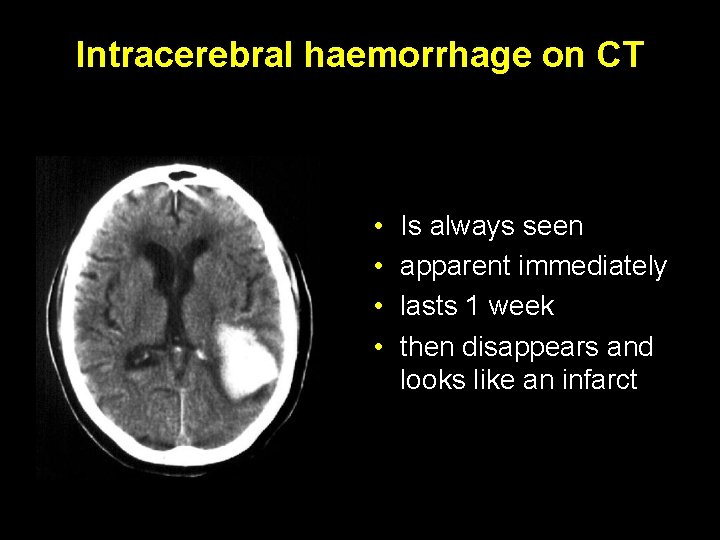
Intracerebral haemorrhage on CT • • Is always seen apparent immediately lasts 1 week then disappears and looks like an infarct
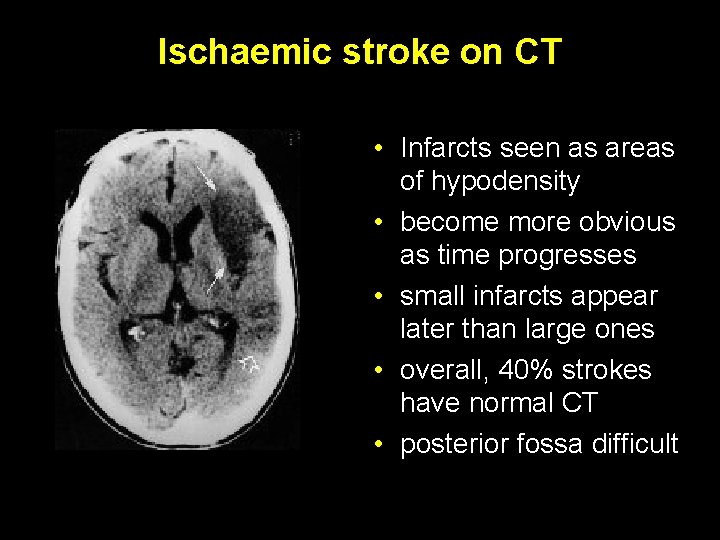
Ischaemic stroke on CT • Infarcts seen as areas of hypodensity • become more obvious as time progresses • small infarcts appear later than large ones • overall, 40% strokes have normal CT • posterior fossa difficult
Haemorrhagic Transformation Haemorrhage seen at the margins of an infarct
MR in acute stroke • Advantages: – much better at defining the anatomy – shows ischaemic changes earlier, and in a greater proportion of patients – diffusion weighted imaging can show ischaemia within minutes-hours, and differentiate between old and new lesions – MRA allows imaging of blood vessels noninvasively • Disadvantages: – expense, time, lack of access to the patient
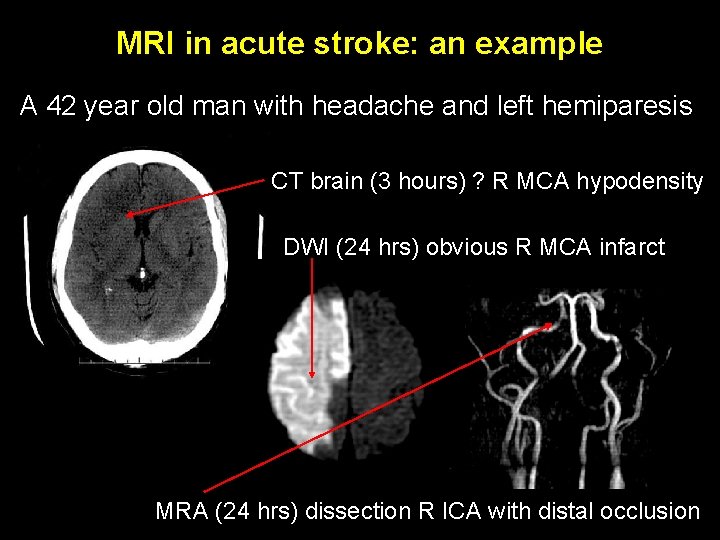
MRI in acute stroke: an example A 42 year old man with headache and left hemiparesis CT brain (3 hours) ? R MCA hypodensity DWI (24 hrs) obvious R MCA infarct MRA (24 hrs) dissection R ICA with distal occlusion
What caused this infarct? • The clinical assessment may provide clues to the likely cause – history - demographics atheroma – examination - carotid bruits atheroembolism, heart abnormalities (AF, murmurs) cardioembolism • Localisation provides the best clues: – cortical stroke cardiac or large artery embolus – lacunar stroke small vessel disease – brainstem stroke local atheroma
Knowing the likely cause tells you how to investigate further. . . • If cortical stroke: – look closely at the heart (ECG, ? Echo) – look for carotid atheroma (Carotid duplex) – specialised tests if young • If lacunar stroke: – look closely for risk factors, fewer tests
What caused this haemorrhage? • According to age: <45 years 45 -69 years >70 years AVM small vessel disease cerebral amyloid small vessel disease • According to location: Lobar Deep white amyloid, AVM, small vessel disease
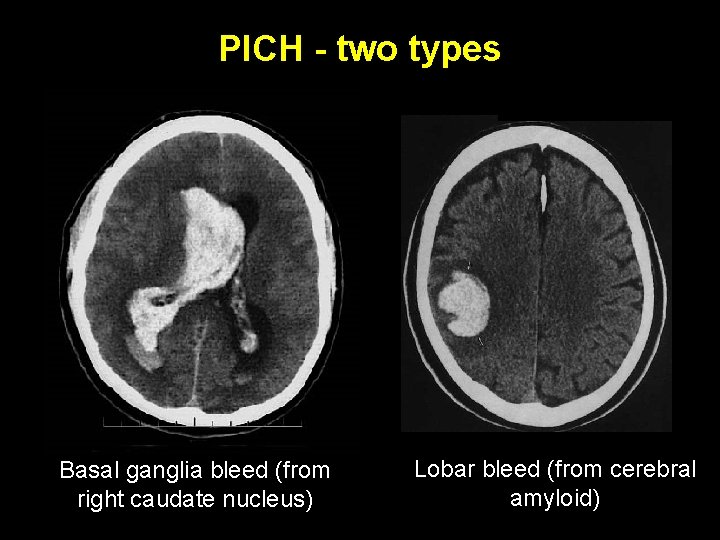
PICH - two types Basal ganglia bleed (from right caudate nucleus) Lobar bleed (from cerebral amyloid)
What is the likely prognosis after stroke?
Prognosis after Intracerebral Haemorrhage • 40% dead in first 7 days • 50% dead in first 30 days • 62% dead by 1 year more likely to die early, but mortality reduces thereafter of the 40% alive, 30% are independent
Prognosis after cerebral infarction • For all: 5% dead by 7 days 10% dead by 1 month 23% dead by 1 year • For large cortical strokes: 60% dead, 35% disabled • For lacunar strokes: 11% dead, 26% disabled
Clinical assessment Aims (1) Is it a stroke? (MSD) (2) What part of the brain is affected? (PJH) (3) What caused this stroke? (PJH) Is it a haemorrhage or an infarct? Can we prevent a further stroke? (4) What are this patient’s problems? + (5) What can we do to treat this patient? (RIL)