
Chronic Pain Dr MC Chu Anaesthesia and Intensive










































- Slides: 75
Chronic Pain Dr. MC Chu Anaesthesia and Intensive Care PWH
Agenda Start at acute pain Un-veil the complexity of chronic pain In second part we will try to treat them
Let’s start with acute pain Tissue damage Site and intensity correlation Gets better with healing (self limiting)
Case 1 A man with a pain in his right leg “Are you sure it is the right leg? ”
Case 1 A man with a pain in his right leg How does it feel like?
Case 1 A man with a pain in his right leg And any other abnormalities?
Case 1 A man with a pain in his right leg What causes it?
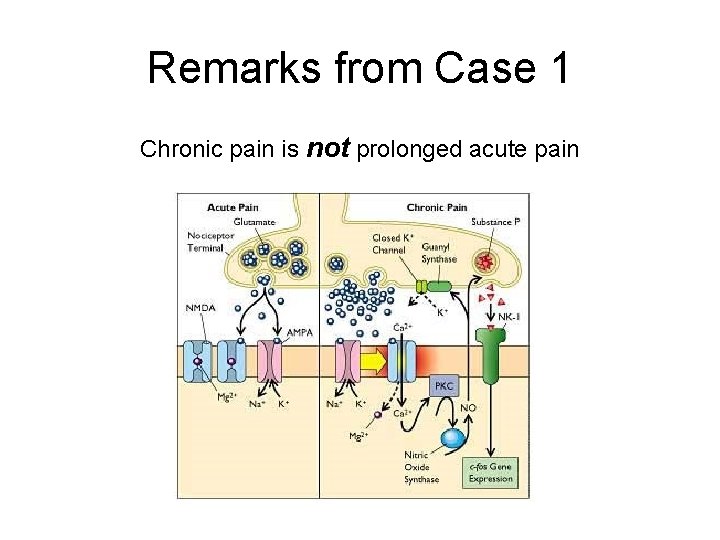
Remarks from Case 1 Chronic pain is not prolonged acute pain
Remarks from Case 1 Pathophysiology is different from acute pain Sensitization Reduced pain threshold (hyperalgesia) Non-painful stimulus (allodynia)
Remarks from Case 1 Pathophysiology is different from acute pain Neuropathic pain Site Character Timing More than that…
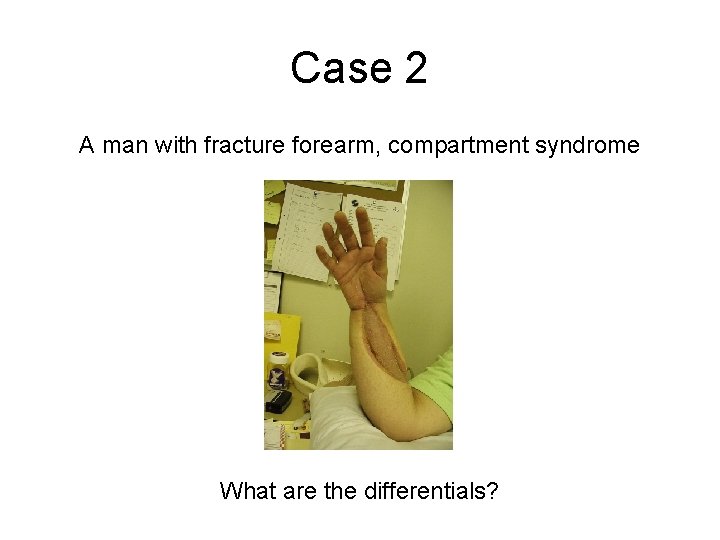
Case 2 A man with fracture forearm, compartment syndrome Fracture fixed, fasciotomy healed Neurovascular integrity OK But he has pain and other things
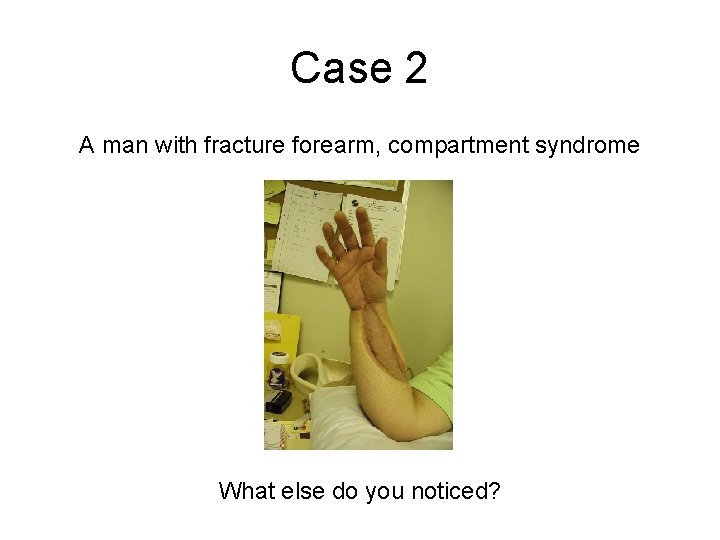
Case 2 A man with fracture forearm, compartment syndrome What else do you noticed?
Case 2 A man with fracture forearm, compartment syndrome What are the differentials?
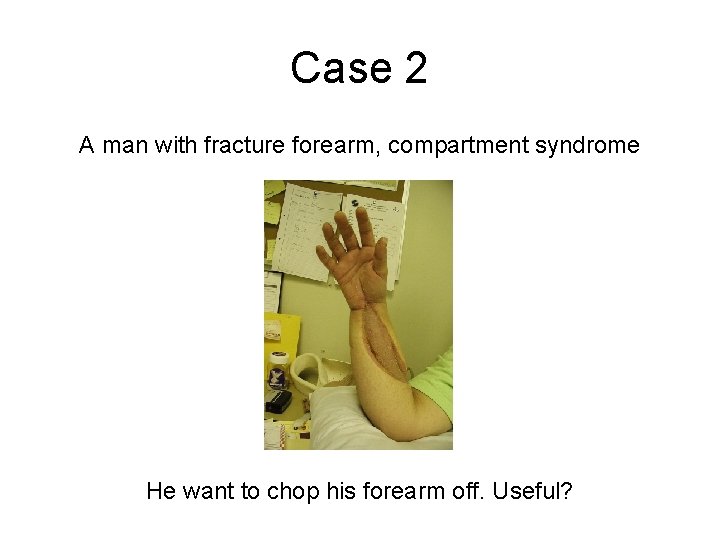
Case 2 A man with fracture forearm, compartment syndrome He want to chop his forearm off. Useful?
Remarks from Case 2 Impairment is different from acute pain Pain can come without obvious pathology Pain, motor, sudomotor or sensory changes Trophic changes Exclude differentials One more example…
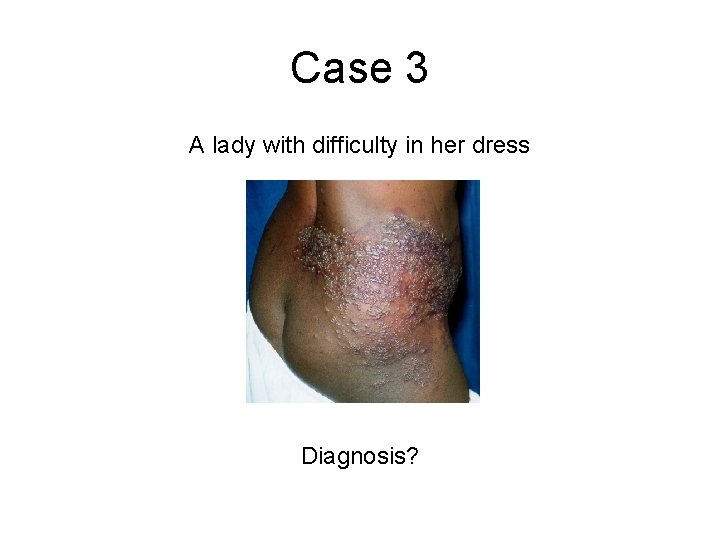
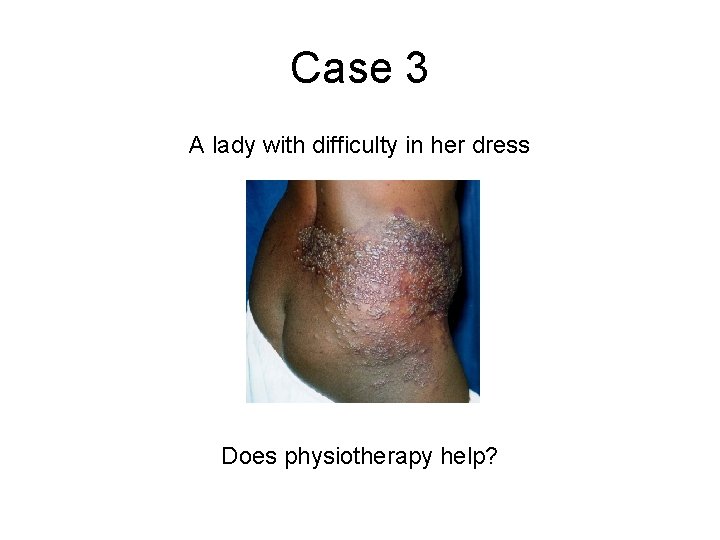
Case 3 A lady with difficulty in her dress Diagnosis?
Case 3 A lady with difficulty in her dress Does physiotherapy help?
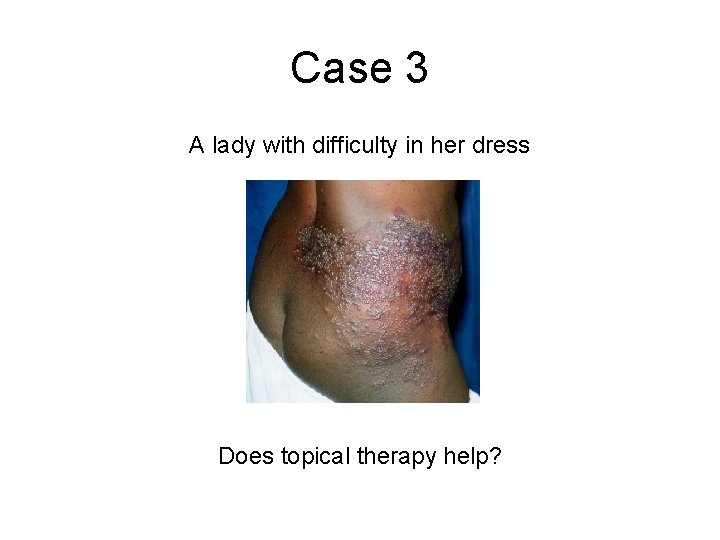
Case 3 A lady with difficulty in her dress Does topical therapy help?
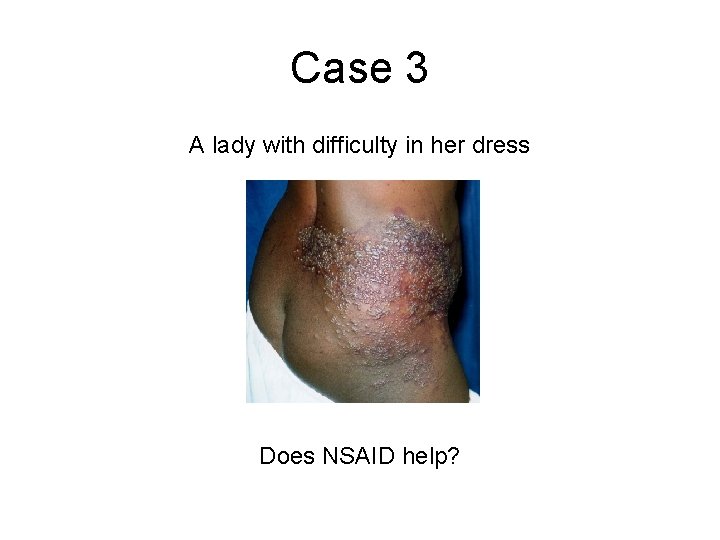
Case 3 A lady with difficulty in her dress Does NSAID help?
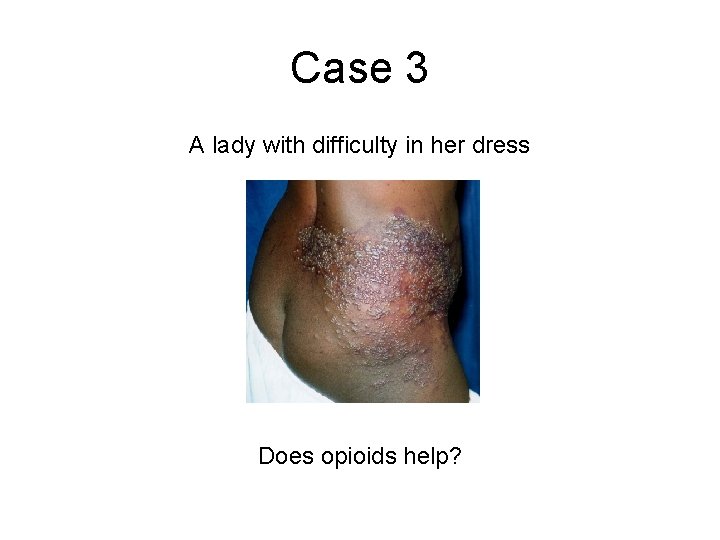
Case 3 A lady with difficulty in her dress Does opioids help?
Remarks from Case 3 Treatment are different from acute pain Partial response to “common” analgesics Long term side effects Tolerances, organ damages Not all chronic pains are neuropathies…
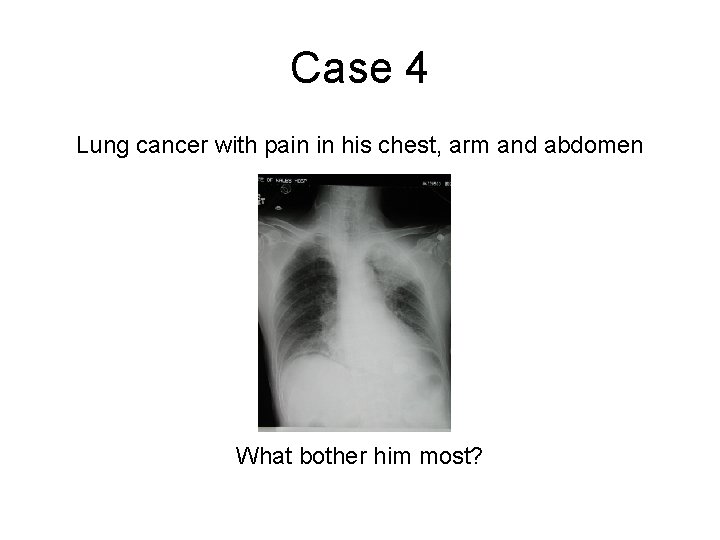
King Mongkut Lung cancer with pain in his chest, arm and abdomen
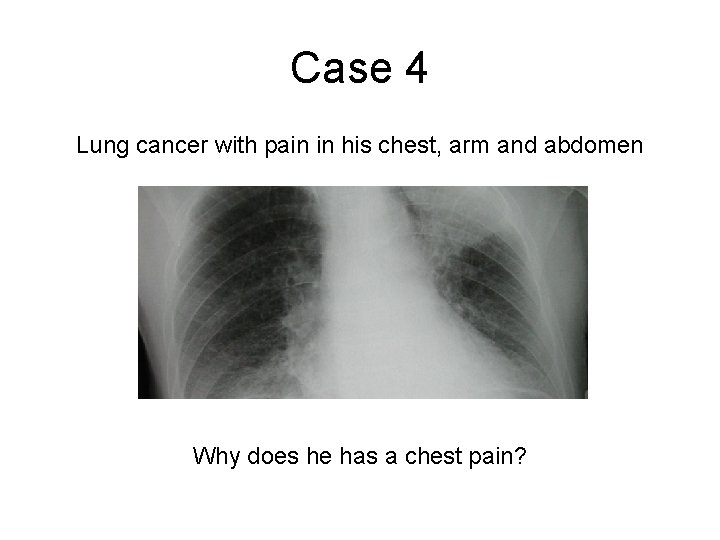
Case 4 Lung cancer with pain in his chest, arm and abdomen Why does he has a chest pain?
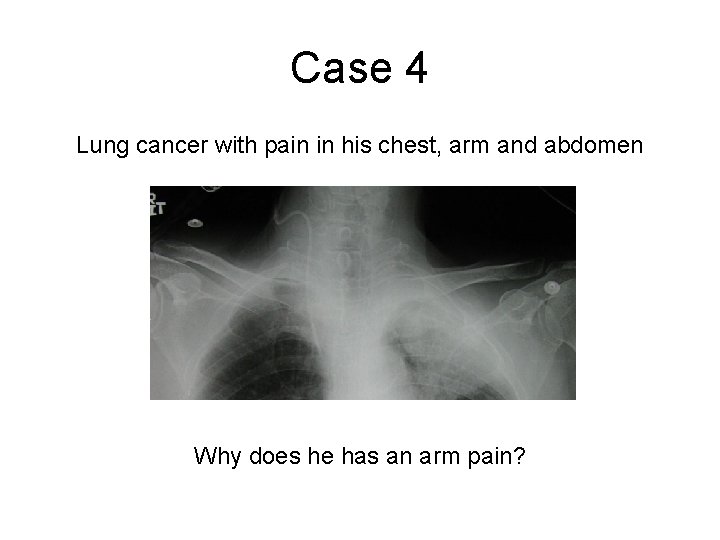
Case 4 Lung cancer with pain in his chest, arm and abdomen Why does he has an arm pain?
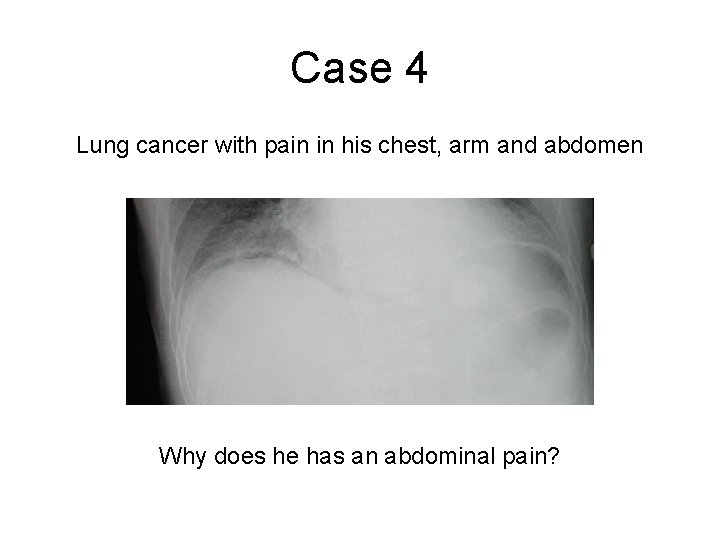
Case 4 Lung cancer with pain in his chest, arm and abdomen Why does he has an abdominal pain?
Case 4 Lung cancer with pain in his chest, arm and abdomen What bother him most?
Remarks from Case 4 Pain is common source of distress Multiple etiologies Iatrogenic Other somatic symptoms Other psychosocial factors Role of palliative medicine Now, the classical onion…
Ms. Unhappy Why can’t you fix my neck and fxxk off
Ms. Unhappy 33 year old woman, traffic accident “whiplash injury” MRI: unremarkable Nociception
Ms. Unhappy She felt so bad that he cannot sleep, cannot eat, and became irritable Affect
Ms. Unhappy She cannot work, cannot go out, cannot do housework, cannot…. Social
Ms. Unhappy She insisted to use a neck collar, visited 4 doctors for the “right diagnosis”, alcohol to “knock me off the pain” Behavior
Remarks from Case 5 Multi-facet problems of chronic pain Nociception is different Mood is altered Behavior and thoughts are changed Function is impaired They are a different person altogether Chronic pain is a disease of its own Pain Management is a specialty of its own
Want to have a break?
Chronic pain as a disease Definitions “Pain extending for a long period of time, represents low levels of underlying pathology that does not explain the presence and extent of pain, or both” Turk in: Bonica’s Management of Pain 3 rd Ed. “Pain without apparent biological value that persists beyond normal tissue healing (usually taken to be 3 months)” IASP 1986
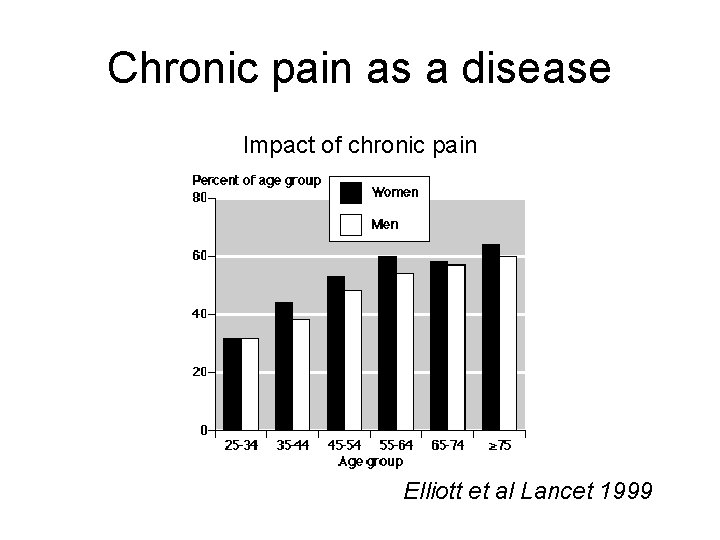
Chronic pain as a disease Impact of chronic pain Elliott et al Lancet 1999
Chronic pain as a disease Impact of chronic pain 10. 8% of local adult Chinese 38% work affected 34% daily activities affected 30% on long term analgesics Ng et al Clin. J. Pain 2002
Chronic pain as a disease Impact of chronic pain 38 Billion Euro per year in Germany 62 Billion US$ per year in US Zimmermann Orthopade 2004 Steward et al JAMA 2003 How much is this?
Chronic pain as a disease How much is this? Cost: 7 billion US$
Chronic pain as a disease How much is this? Cost: 4 million US$ per year
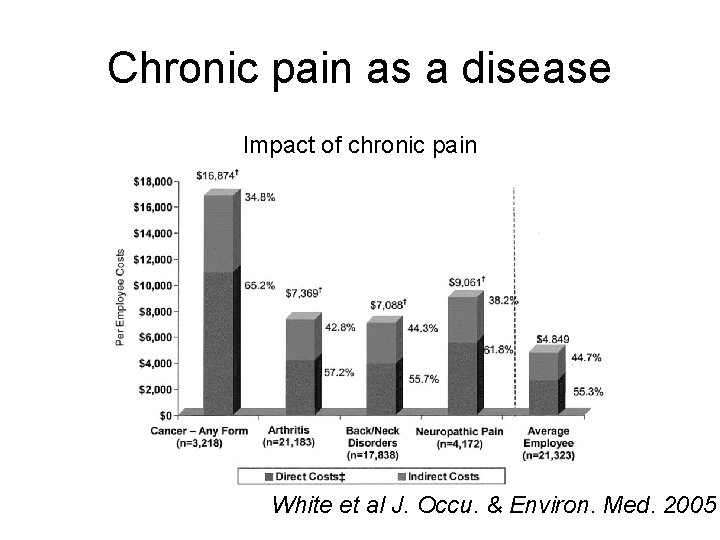
Chronic pain as a disease Impact of chronic pain White et al J. Occu. & Environ. Med. 2005
Clinical aspect
Scope of pain medicine Etiology Trauma (including iatrogenic) Cancer (and its treatment) Infections / inflammations Mechanical / functional Idiopathic
Scope of pain medicine Etiology Trauma (including iatrogenic) Cancer (and its treatment) Infections / inflammations Mechanical / functional Idiopathic
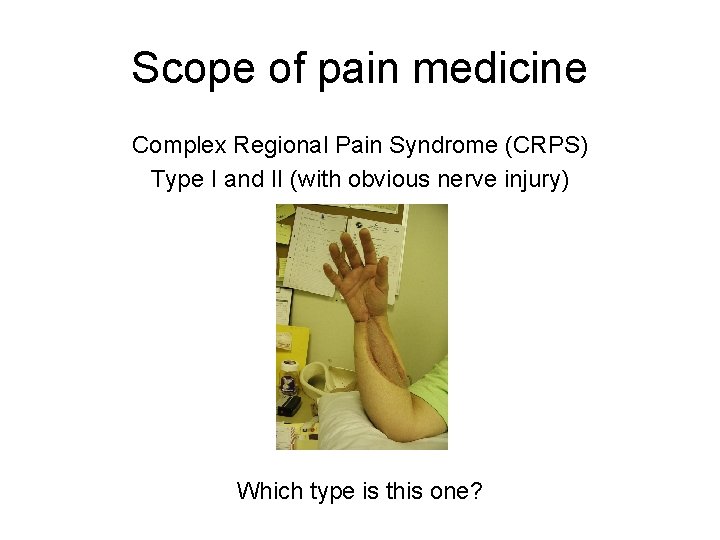
Scope of pain medicine Complex Regional Pain Syndrome (CRPS) Type I and II (with obvious nerve injury) Which type is this one?
Scope of pain medicine Complex Regional Pain Syndrome (CRPS) Pathophysiology is unknown Diagnosis is clinical Investigations are not diagnostic Treatment is empirical Prognosis: 30% loss of work at 1 year “early intervention to prevent disability” Atkins J. Bone & Joint Surg 2003
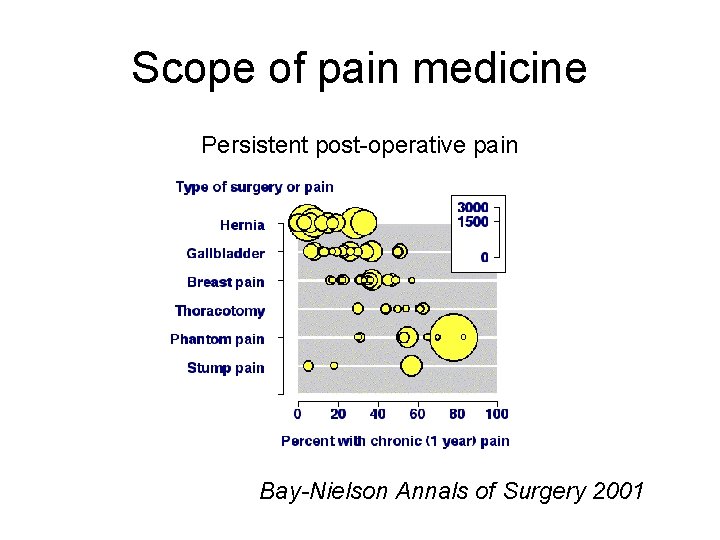
Scope of pain medicine Persistent post-operative pain Bay-Nielson Annals of Surgery 2001
Scope of pain medicine Persistent post-operative pain Predictive factor: intensity of early post-op. pain Most will resolve slowly Is it preventable? Role of pre-emptive analgesia still uncertain Should be part of the surgical consent
Scope of pain medicine Etiology Trauma (including iatrogenic) Cancer (and its treatment) Infections / inflammations Mechanical / functional Idiopathic
Scope of pain medicine Cancer pain Over 50% cancer patients have severe pain at their end What contribute to this un-desirable outcome?
Scope of pain medicine Cancer pain Difficulties with treatment Side effects may be intolerable Oral intolerance Fatigue or impaired consciousness
Scope of pain medicine Cancer pain Difficulties with treatment Patients and doctors refuse treatment Denial of disease progression Hope of curing the incurable Myths of analgesics, including addiction “Opio-phobia”
Scope of pain medicine Etiology Trauma (including iatrogenic) Cancer (and its treatment) Infections / inflammations Mechanical / functional Idiopathic
Scope of pain medicine Acute low back pain Leading cause for GP consultations Most (>90%) gets better in 2 weeks Blind investigation yield is very low (< 5%) How many of you have this?
Scope of pain medicine Acute low back pain Most important: to exclude organic pathology “Red flags” Fever History of trauma Constitutional (weight / appetide loss) Neurological (cauda equina /radiculopathy) Non-spine pathology eg: pulsatile abdominal mass
Scope of pain medicine Acute low back pain Most important: to exclude organic pathology “Red flags”
Scope of pain medicine Acute low back pain NSAID, paracetamol Avoid opioids / muscle relaxants Avoid aggressive physio Avoid bed rest Live a normal life
Scope of pain medicine Acute low back pain Predictive of chronicity and disability “Yellow flag” Fear avoidance behavior Negative belief that pain is harmful or disabling Excessive focusing on pain Expectation on passive pain management Linton Spine 2000
Scope of pain medicine Acute low back pain Predictive of chronicity and disability “Yellow flag” Depressed mood, social withdrawal Co-existing financial and social problems Poor job satisfaction Linton Spine 2000
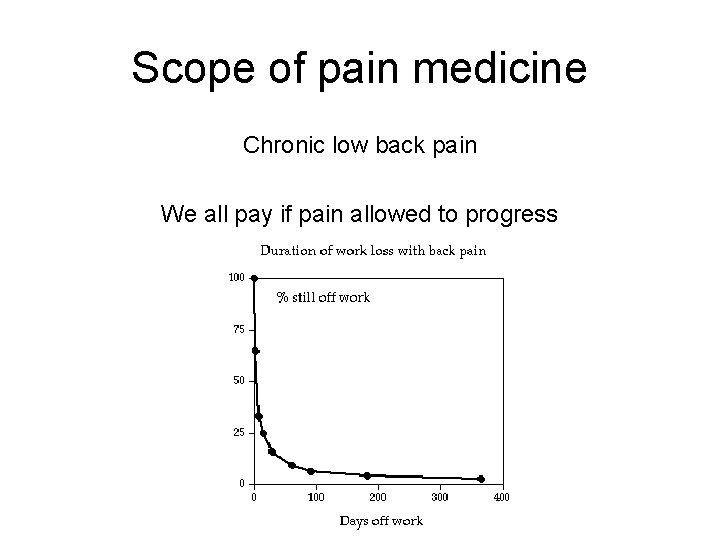
Scope of pain medicine Chronic low back pain We all pay if pain allowed to progress
Scope of pain medicine Chronic low back pain Structures potentially involved Bone, disc, facet joints, ligaments, muscle, nerves How can we tell?
Scope of pain medicine Chronic low back pain Musculoskeletal Examination Tenderness Muscle spasm k value 0. 24 < 0. 2 Deyo JAMA 1992
Scope of pain medicine Chronic low back pain k value Neurological Examination Weak ankle dorsiflexion Normal ankle reflexes Straight leg raising 1. 0 0. 39 0. 6 Deyo JAMA 1992
Scope of pain medicine Chronic low back pain Non-organic signs “find ways of predicting surgical failure to treat back pain” 8 physical signs associated with higher personality score abnormalities, multiple surgeries and surgeon’s suspicion. Waddell 1980
Scope of pain medicine Chronic low back pain Non-organic signs Non-anatomical motor / sensory loss Superficial / non-anatomical tenderness Simulation (pelvic rotate, axial load, distraction SLR) Over-reaction 3 out of 8
Scope of pain medicine Chronic low back pain Mis-interpretation of non-organic signs Malingering Secondary gain Exclude pathology False positives
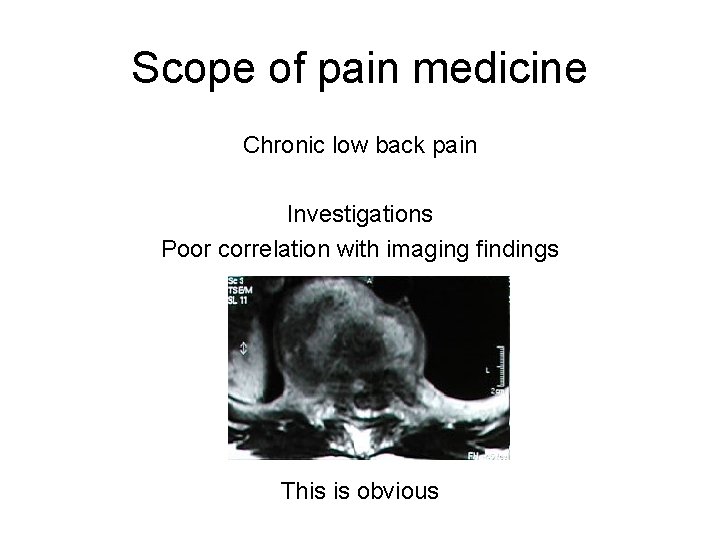
Scope of pain medicine Chronic low back pain Investigations Poor correlation with imaging findings This is obvious
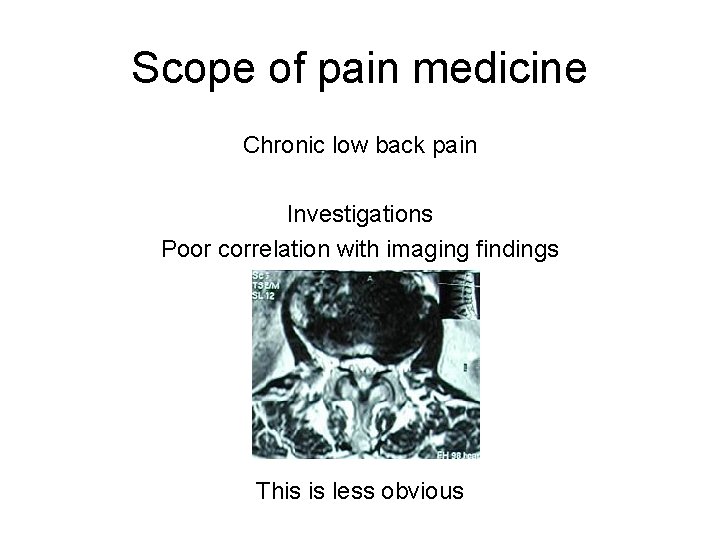
Scope of pain medicine Chronic low back pain Investigations Poor correlation with imaging findings This is less obvious
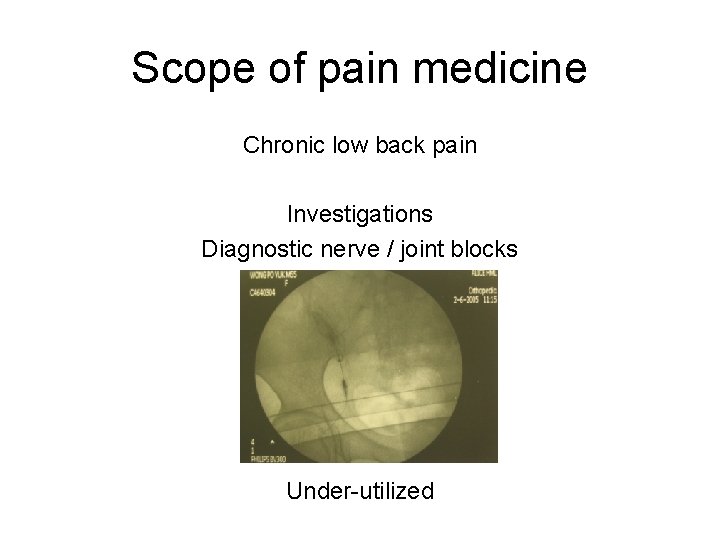
Scope of pain medicine Chronic low back pain Investigations Diagnostic nerve / joint blocks Under-utilized
Scope of pain medicine Chronic low back pain Surgery is indicated if Failed conservative treatment Demonstrable pathology Correlation with clinical findings Minimal psychosocial complications Why are we so cautious?
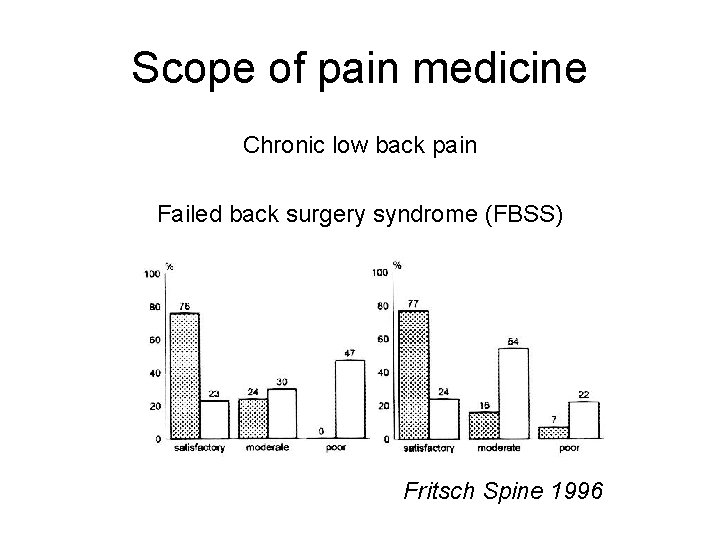
Scope of pain medicine Chronic low back pain Failed back surgery syndrome (FBSS) More MRI, more surgery Therefore…
Scope of pain medicine Chronic low back pain Failed back surgery syndrome (FBSS) Fritsch Spine 1996
Try this one 37 year old kindergarten teacher Sprained her back while lifting a child 2 years ago Seen GP and several Orthopediac surgeons Had a few spine X-rays and an MRI “Bone spurs everywhere” Scheduled for spinal fusion Patient next bed: “I have that 3 times, and I’m still here” You are consulted: “for better analgesics”
Try this one 37 year old kindergarten teacher How would you assess her? Any “better analgesic” to offer?
We will split the onion next time