
Chapter 19 The Cardiovascular System The Blood Tortora
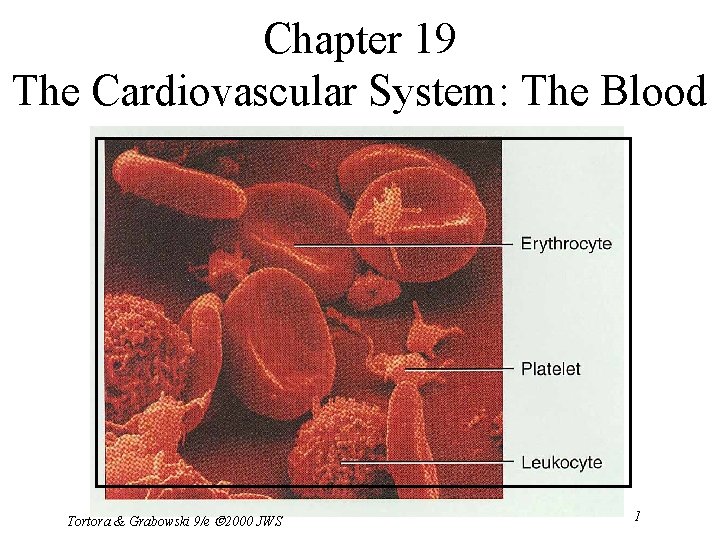
Chapter 19 The Cardiovascular System: The Blood Tortora & Grabowski 9/e 2000 JWS 1

Fluids of the Body • Cells of the body are serviced by 2 fluids – blood • composed of plasma and a variety of cells • transports nutrients and wastes – interstitial fluid • bathes the cells of the body • Nutrients and oxygen diffuse from the blood into the interstitial fluid & then into the cells • Wastes move in the reverse direction • Hematology is study of blood and blood disorders Tortora & Grabowski 9/e 2000 JWS 2

Functions of Blood • Transportation – O 2, CO 2, metabolic wastes, nutrients, heat & hormones • Regulation – helps regulate p. H through buffers – helps regulate body temperature • coolant properties of water • vasodilatation of surface vessels dump heat – helps regulate water content of cells by interactions with dissolved ions and proteins • Protection from disease & loss of blood Tortora & Grabowski 9/e 2000 JWS 3

Physical Characteristics of Blood • Thicker (more viscous) than water and flows more slowly than water • Temperature of 100. 4 degrees F • p. H 7. 4 (7. 35 -7. 45) • 8 % of total body weight • Blood volume – 5 to 6 liters in average male – 4 to 5 liters in average female – hormonal negative feedback systems maintain constant blood volume and osmotic pressure 4 Tortora & Grabowski 9/e 2000 JWS

Techniques of Blood Sampling • Venipuncture – sample taken from vein with hypodermic needle & syringe – median cubital vein (see page 717) – why not stick an artery? • less pressure • closer to the surface • Finger or heel stick – common technique for diabetics to monitor daily blood sugar – method used for infants Tortora & Grabowski 9/e 2000 JWS 5

Components of Blood • Hematocrit – 55% plasma – 45% cells • 99% RBCs • < 1% WBCs and platelets Tortora & Grabowski 9/e 2000 JWS 6
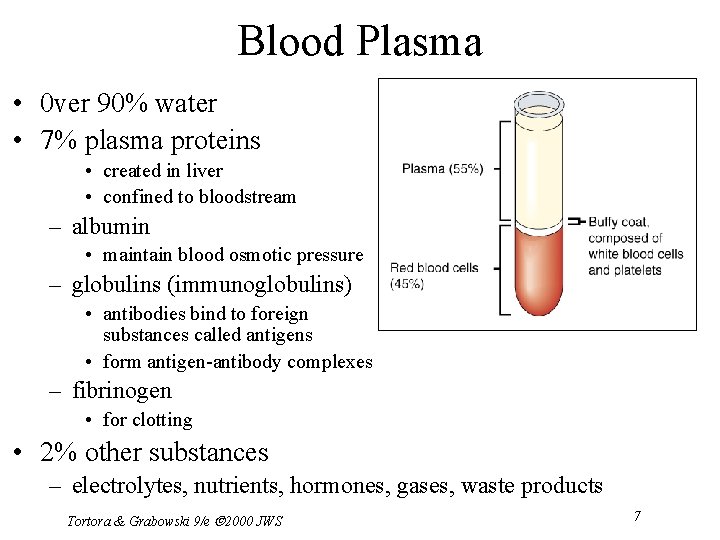
Blood Plasma • 0 ver 90% water • 7% plasma proteins • created in liver • confined to bloodstream – albumin • maintain blood osmotic pressure – globulins (immunoglobulins) • antibodies bind to foreign substances called antigens • form antigen-antibody complexes – fibrinogen • for clotting • 2% other substances – electrolytes, nutrients, hormones, gases, waste products Tortora & Grabowski 9/e 2000 JWS 7
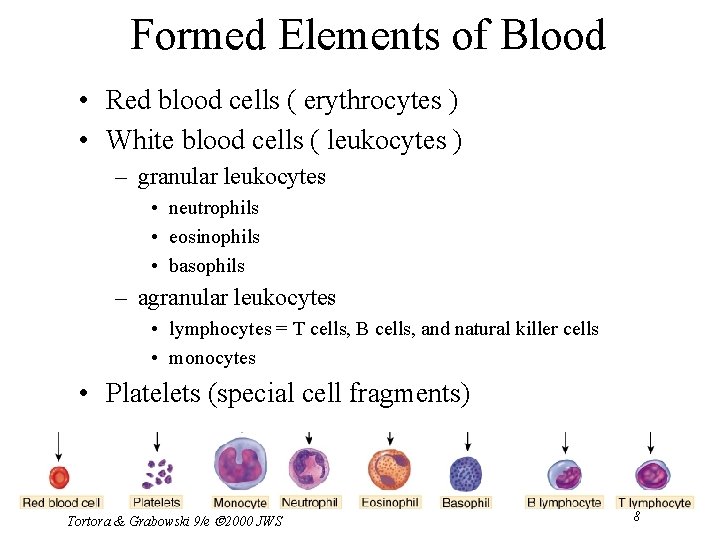
Formed Elements of Blood • Red blood cells ( erythrocytes ) • White blood cells ( leukocytes ) – granular leukocytes • neutrophils • eosinophils • basophils – agranular leukocytes • lymphocytes = T cells, B cells, and natural killer cells • monocytes • Platelets (special cell fragments) Tortora & Grabowski 9/e 2000 JWS 8
Hematocrit • Percentage of blood occupied by cells – female normal range • 38 - 46% (average of 42%) – male normal range • 40 - 54% (average of 46%) • testosterone • Anemia – not enough RBCs or not enough hemoglobin • Polycythemia – too many RBCs (over 65%) – dehydration, tissue hypoxia, blood doping in athletes Tortora & Grabowski 9/e 2000 JWS 9

Blood Doping • Injecting previously stored RBC’s before an athletic event – more cells available to deliver oxygen to tissues • Dangerous – increases blood viscosity – forces heart to work harder • Banned by Olympic committee Tortora & Grabowski 9/e 2000 JWS 10
Formation of Blood Cells • Most blood cells types need to be continually replaced – die within hours, days or weeks – process of blood cells formation is hematopoiesis or hemopoiesis • In the embryo – occurs in yolk sac, liver, spleen, thymus, lymph nodes & red bone marrow • In adult – occurs only in red marrow of flat bones like sternum, ribs, skull & pelvis and ends of long bones Tortora & Grabowski 9/e 2000 JWS 11
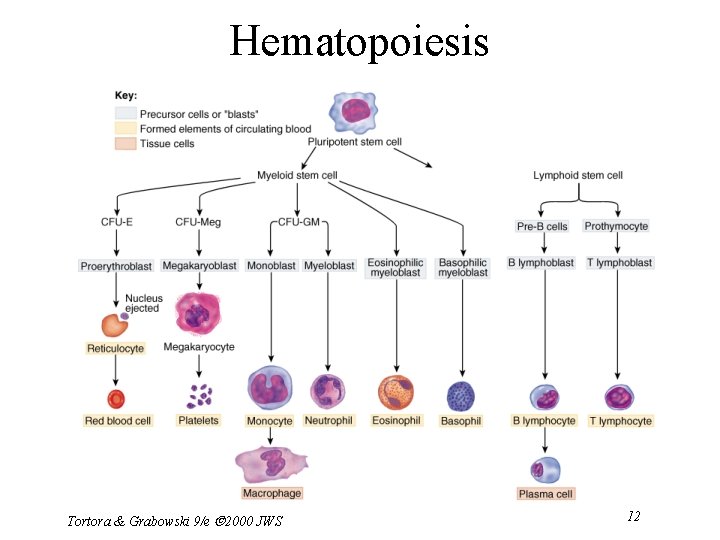
Hematopoiesis Tortora & Grabowski 9/e 2000 JWS 12
Stages of Blood Cell Formation • Pluripotent stem cells –. 1% of red marrow cells – replenish themselves as they differentiate into either myeloid or lymphoid stem cells • Myeloid stem cell line of development continues: – progenitor cells(colony-forming units) no longer can divide and are specialized to form specific cell types • example: CFU-E develops eventually into only red blood cells – next generation is blast cells • have recognizable histological characteristics • develop within several divisions into mature cell types • Lymphoid stem cell line of development – pre-B cells & prothymocytes finish their develop into B & T lymphocytes in the lymphatic tissue after leaving the red marrow Tortora & Grabowski 9/e 2000 JWS 13
Hemopoietic Growth Factors • Regulate differentiation & proliferation • Erythropoietin (EPO) – produced by the kidneys increase RBC precursors • Thrombopoietin (TPO) – hormone from liver stimulates platelet formation • Cytokines are local hormones of bone marrow – produced by some marrow cells to stimulate proliferation in other marrow cells – colony-stimulating factor (CSF) & interleukin stimulate WBC production Tortora & Grabowski 9/e 2000 JWS 14

Medical Uses of Growth Factors • Available through recombinant DNA technology – recombinant erythropoietin (EPO) very effective in treating decreased RBC production of end-stage kidney disease – other products given to stimulate WBC formation in cancer patients receiving chemotherapy which kills bone marrow • granulocyte-macrophage colony-stimulating factor • granulocyte colony stimulating factor – thrombopoietin helps prevent platelet depletion during chemotherapy Tortora & Grabowski 9/e 2000 JWS 15
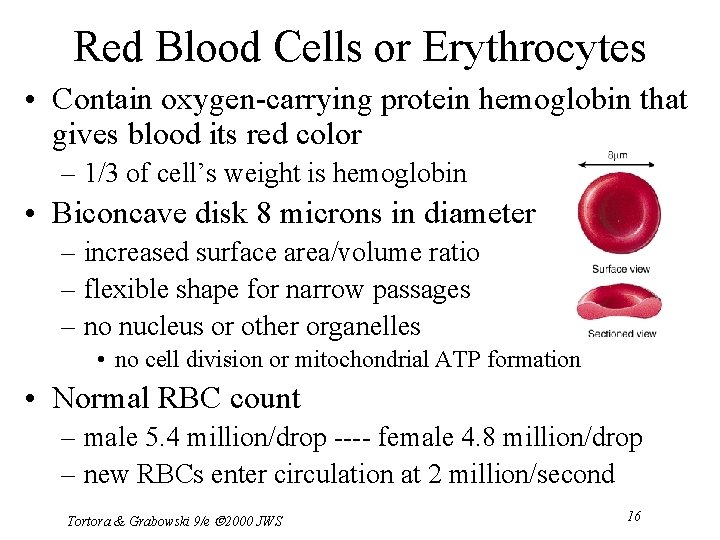
Red Blood Cells or Erythrocytes • Contain oxygen-carrying protein hemoglobin that gives blood its red color – 1/3 of cell’s weight is hemoglobin • Biconcave disk 8 microns in diameter – increased surface area/volume ratio – flexible shape for narrow passages – no nucleus or other organelles • no cell division or mitochondrial ATP formation • Normal RBC count – male 5. 4 million/drop ---- female 4. 8 million/drop – new RBCs enter circulation at 2 million/second Tortora & Grabowski 9/e 2000 JWS 16
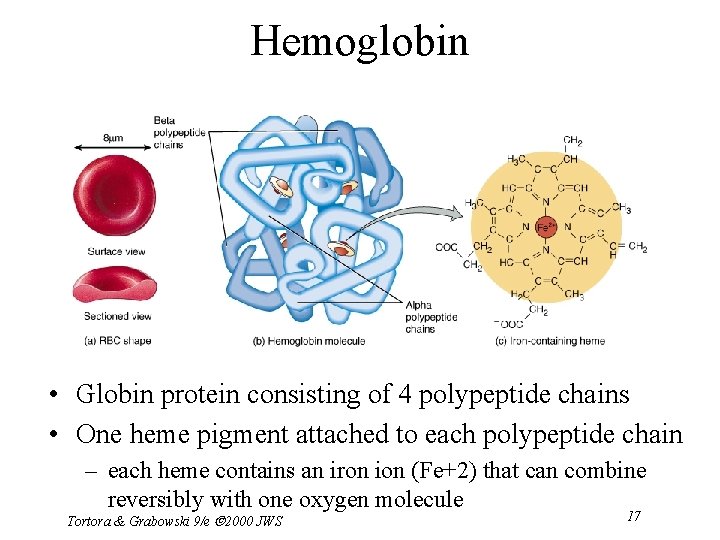
Hemoglobin • Globin protein consisting of 4 polypeptide chains • One heme pigment attached to each polypeptide chain – each heme contains an iron ion (Fe+2) that can combine reversibly with one oxygen molecule Tortora & Grabowski 9/e 2000 JWS 17
Transport of O 2, CO 2 and Nitric Oxide • Each hemoglobin molecule can carry 4 oxygen molecules from lungs to tissue cells • Hemoglobin transports 23% of total CO 2 waste from tissue cells to lungs for release – combines with amino acids in globin portion of Hb • Hemoglobin transports nitric oxide & super nitric oxide helping to regulate BP – iron ions pick up nitric oxide (NO) & super nitric oxide (SNO)& transport it to & from the lungs – NO causing vasoconstriction is released in the lungs – SNO causing vasodilation is picked up in the lungs 18 Tortora & Grabowski 9/e 2000 JWS

RBC Life Cycle • RBCs live only 120 days – wear out from bending to fit through capillaries – no repair possible due to lack of organelles • Worn out cells removed by fixed macrophages in spleen & liver • Breakdown products are recycled Tortora & Grabowski 9/e 2000 JWS 19
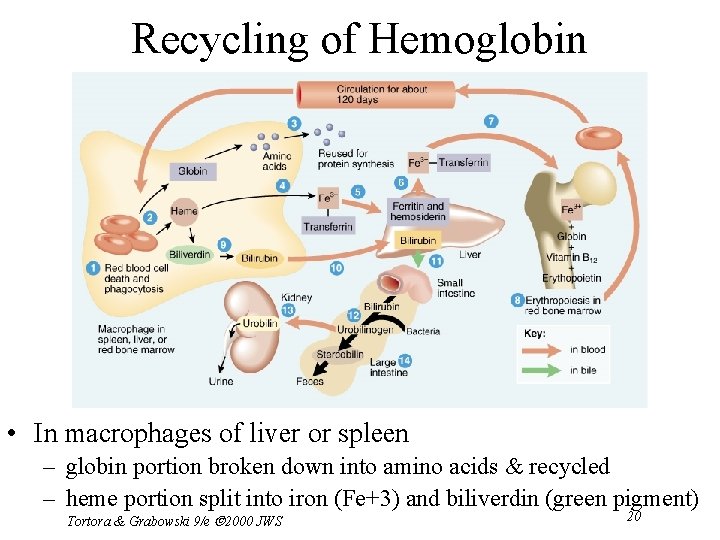
Recycling of Hemoglobin Components • In macrophages of liver or spleen – globin portion broken down into amino acids & recycled – heme portion split into iron (Fe+3) and biliverdin (green pigment) Tortora & Grabowski 9/e 2000 JWS 20
Fate of Components of Heme • Iron(Fe+3) – transported in blood attached to transferrin protein – stored in liver, muscle or spleen • attached to ferritin or hemosiderin protein – in bone marrow being used for hemoglobin synthesis • Biliverdin (green) converted to bilirubin (yellow) – bilirubin secreted by liver into bile • converted to urobilinogen then stercobilin (brown pigment in feces) by bacteria of large intestine • if reabsorbed from intestines into blood is converted to a yellow pigment, urobilin and excreted in urine Tortora & Grabowski 9/e 2000 JWS 21
Erythropoiesis: Production of RBCs • Proerythroblast starts to produce hemoglobin • Many steps later, nucleus is ejected & a reticulocyte is formed – orange in color with traces of visible rough ER • Reticulocytes escape from bone marrow into the blood • In 1 -2 days, they eject the remaining organelles to become a mature RBC Tortora & Grabowski 9/e 2000 JWS 22
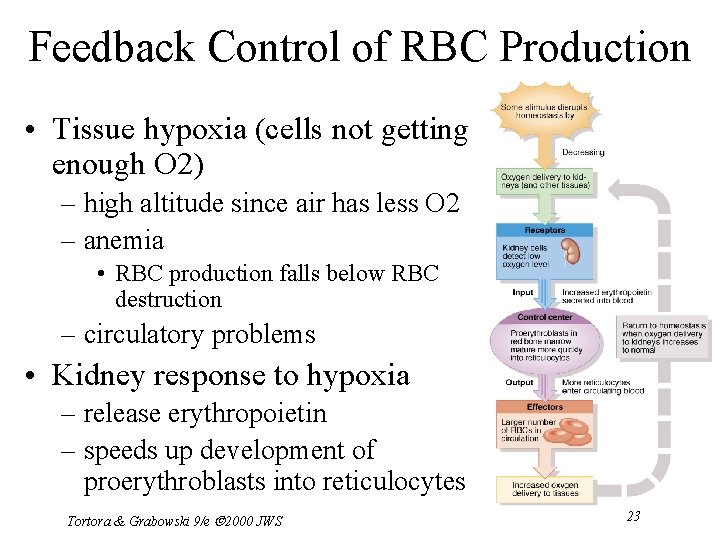
Feedback Control of RBC Production • Tissue hypoxia (cells not getting enough O 2) – high altitude since air has less O 2 – anemia • RBC production falls below RBC destruction – circulatory problems • Kidney response to hypoxia – release erythropoietin – speeds up development of proerythroblasts into reticulocytes Tortora & Grabowski 9/e 2000 JWS 23
Normal Reticulocyte Count • Should be. 5 to 1. 5% of the circulating RBC’s • Low count in an anemic person might indicate bone marrow problem – leukemia, nutritional deficiency or failure of red bone marrow to respond to erythropoietin stimulation • High count might indicate recent blood loss or successful iron therapy Tortora & Grabowski 9/e 2000 JWS 24
WBC Anatomy and Types • All WBCs (leukocytes) have a nucleus and no hemoglobin • Granular or agranular classification based on presence of cytoplasmic granules made visible by staining – granulocytes are neutrophils, eosinophils or basophils – agranulocytes are monocyes or lymphocytes Tortora & Grabowski 9/e 2000 JWS 25

Neutrophils (Granulocyte) • Polymorphonuclear Leukocytes or Polys • Nuclei = 2 to 5 lobes connected by thin strands – older cells have more lobes – young cells called band cells because of horseshoe shaped nucleus (band) • Fine, pale lilac practically invisible granules • Diameter is 10 -12 microns • 60 to 70% of circulating WBCs Tortora & Grabowski 9/e 2000 JWS 26
Eosinophils (Granulocyte) • Nucleus with 2 or 3 lobes connected by a thin strand • Large, uniform-sized granules stain orangered with acidic dyes – do not obscure the nucleus • Diameter is 10 to 12 microns • 2 to 4% of circulating WBCs Tortora & Grabowski 9/e 2000 JWS 27

Basophils (Granulocyte) • Large, dark purple, variable-sized granules stain with basic dyes – obscure the nucleus • Irregular, s-shaped, bilobed nuclei • Diameter is 8 to 10 microns • Less than 1% of circulating WBCs Tortora & Grabowski 9/e 2000 JWS 28
Lymphocyte (Agranulocyte) • Dark, oval to round nucleus • Cytoplasm sky blue in color – amount varies from rim of blue to normal amount • Small cells 6 - 9 microns in diameter • Large cells 10 - 14 microns in diameter – increase in number during viral infections • 20 to 25% of circulating WBCs Tortora & Grabowski 9/e 2000 JWS 29
Monocyte (Agranulocyte) • Nucleus is kidney or horse-shoe shaped • Largest WBC in circulating blood – does not remain in blood long before migrating to the tissues – differentiate into macrophages • fixed group found in specific tissues – alveolar macrophages in lungs – kupffer cells in liver • wandering group gathers at sites of infection • Diameter is 12 - 20 microns • Cytoplasm is a foamy blue-gray • 3 to 8% o circulating WBCs Tortora & Grabowski 9/e 2000 JWS 30

WBC Physiology • Less numerous than RBCs – 5000 to 10, 000 cells per drop of blood – 1 WBC for every 700 RBC • Leukocytosis is a high white blood cell count – microbes, strenuous exercise, anesthesia or surgery • Leukopenia is low white blood cell count – radiation, shock or chemotherapy • Only 2% of total WBC population is in circulating blood at any given time – rest is in lymphatic fluid, skin, lungs, lymph nodes & spleen 31 Tortora & Grabowski 9/e 2000 JWS
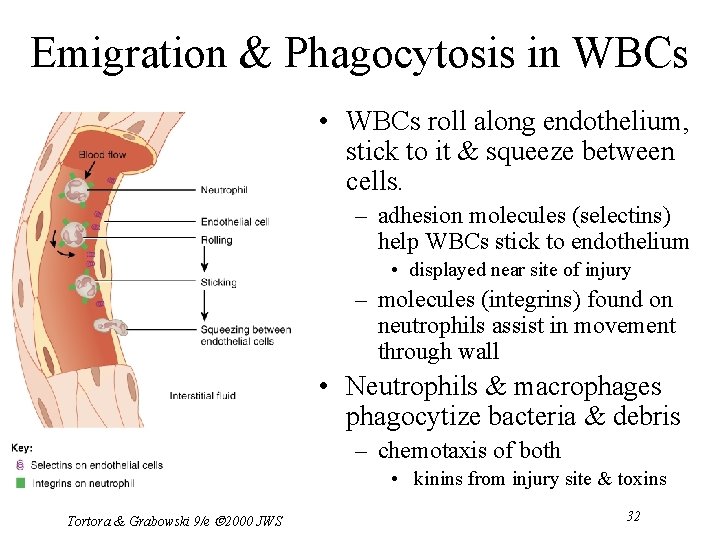
Emigration & Phagocytosis in WBCs • WBCs roll along endothelium, stick to it & squeeze between cells. – adhesion molecules (selectins) help WBCs stick to endothelium • displayed near site of injury – molecules (integrins) found on neutrophils assist in movement through wall • Neutrophils & macrophages phagocytize bacteria & debris – chemotaxis of both • kinins from injury site & toxins Tortora & Grabowski 9/e 2000 JWS 32

Neutrophil Function • Fastest response of all WBC to bacteria • Direct actions against bacteria – release lysozymes which destroy/digest bacteria – release defensin proteins that act like antibiotics & poke holes in bacterial cell walls destroying them – release strong oxidants (bleach-like, strong chemicals ) that destroy bacteria Tortora & Grabowski 9/e 2000 JWS 33

Monocyte Function • Take longer to get to site of infection, but arrive in larger numbers • Become wandering macrophages, once they leave the capillaries • Destroy microbes and clean up dead tissue following an infection Tortora & Grabowski 9/e 2000 JWS 34

Basophil Function • Involved in inflammatory and allergy reactions • Leave capillaries & enter connective tissue as mast cells • Release heparin, histamine & serotonin – heighten the inflammatory response and account for hypersensitivity (allergic) reaction Tortora & Grabowski 9/e 2000 JWS 35

Eosinophil Function • Leave capillaries to enter tissue fluid • Release histaminase – slows down inflammation caused by basophils • Attack parasitic worms • Phagocytize antibody-antigen complexes Tortora & Grabowski 9/e 2000 JWS 36
Lymphocyte Functions • B cells – destroy bacteria and their toxins – turn into plasma cells that produces antibodies • T cells – attack viruses, fungi, transplanted organs, cancer cells & some bacteria • Natural killer cells – attack many different microbes & some tumor cells – destroy foreign invaders by direct attack Tortora & Grabowski 9/e 2000 JWS 37
Differential WBC Count • Detection of changes in numbers of circulating WBCs (percentages of each type) – indicates infection, poisoning, leukemia, chemotherapy, parasites or allergy reaction • Normal WBC counts – neutrophils 60 -70% (up if bacterial infection) – lymphocyte 20 -25% (up if viral infection) – monocytes 3 -- 8 % (up if fungal/viral infection) – eosinophil 2 -- 4 % (up if parasite or allergy reaction) – basophil <1% (up if allergy reaction or hypothyroid) Tortora & Grabowski 9/e 2000 JWS 38
Bone Marrow Transplant • Intravenous transfer of healthy bone marrow • Procedure – destroy sick bone marrow with radiation & chemotherapy – donor matches surface antigens on WBC – put sample of donor marrow into patient's vein for reseeding of bone marrow – success depends on histocompatibility of donor & recipient • Treatment for leukemia, sickle-cell, breast, ovarian or testicular cancer, lymphoma or aplastic anemia Tortora & Grabowski 9/e 2000 JWS 39
Platelet (Thrombocyte) Anatomy • Disc-shaped, 2 - 4 micron cell fragment with no nucleus • Normal platelet count is 150, 000400, 000/drop of blood • Other blood cell counts – 5 million red & 5 -10, 000 white blood cells Tortora & Grabowski 9/e 2000 JWS 40
Platelets--Life History • Platelets form in bone marrow by following steps: – myeloid stem cells to megakaryocyte-colony forming cells to megakaryoblast to megakaryocytes whose cell fragments form platelets • Short life span (5 to 9 days in bloodstream) – formed in bone marrow – few days in circulating blood – aged ones removed by fixed macrophages in liver and spleen Tortora & Grabowski 9/e 2000 JWS 41
Complete Blood Count • Screens for anemia and infection • Total RBC, WBC & platelet counts; differential WBC; hematocrit and hemoglobin measurements • Normal hemoglobin range – infants have 14 to 20 g/100 m. L of blood – adult females have 12 to 16 g/100 m. L of blood – adult males have 13. 5 to 18 g/100 m. L of blood Tortora & Grabowski 9/e 2000 JWS 42

Hemostasis • Stoppage of bleeding in a quick & localized fashion when blood vessels are damaged • Prevents hemorrhage (loss of a large amount of blood) • Methods utilized – vascular spasm – platelet plug formation – blood clotting (coagulation = formation of fibrin threads) Tortora & Grabowski 9/e 2000 JWS 43

Vascular Spasm • Damage to blood vessel produces stimulates pain receptors • Reflex contraction of smooth muscle of small blood vessels • Can reduce blood loss for several hours until other mechanisms can take over • Only for small blood vessel or arteriole Tortora & Grabowski 9/e 2000 JWS 44
Platelet Plug Formation • Platelets store a lot of chemicals in granules needed for platelet plug formation – alpha granules • clotting factors • platelet-derived growth factor – cause proliferation of vascular endothelial cells, smooth muscle & fibroblasts to repair damaged vessels – dense granules • ADP, ATP, Ca+2, serotonin, fibrin-stabilizing factor, & enzymes that produce thromboxane A 2 • Steps in the process – (1) platelet adhesion (2) platelet release reaction (3) platelet aggregation Tortora & Grabowski 9/e 2000 JWS 45
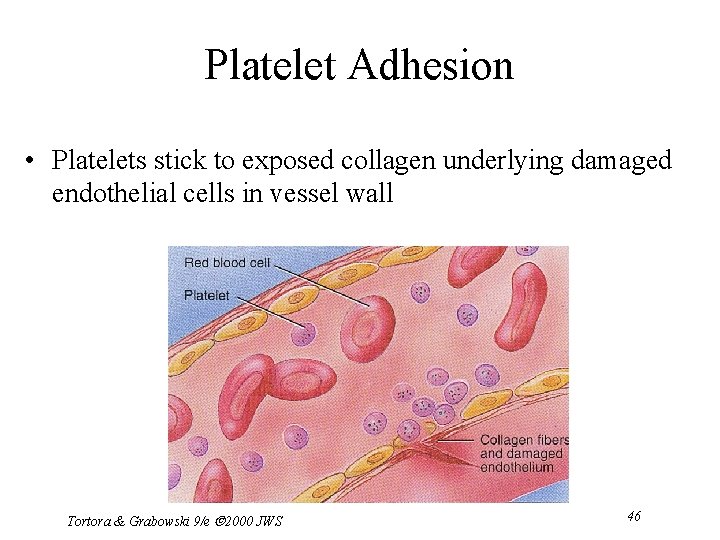
Platelet Adhesion • Platelets stick to exposed collagen underlying damaged endothelial cells in vessel wall Tortora & Grabowski 9/e 2000 JWS 46
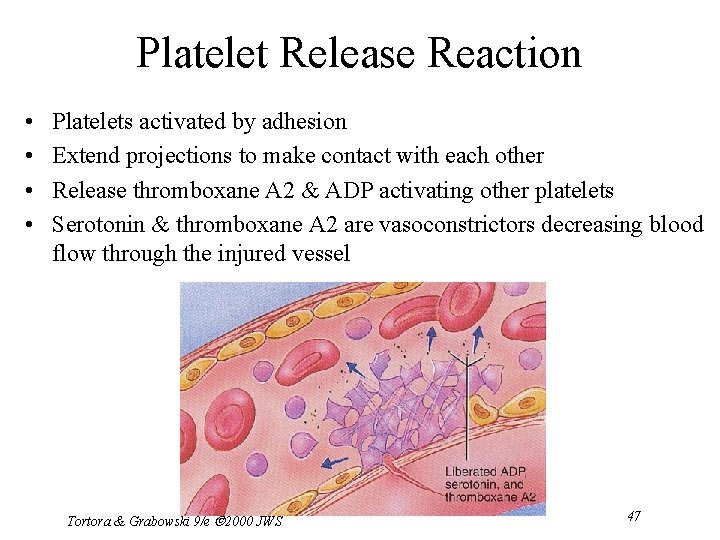
Platelet Release Reaction • • Platelets activated by adhesion Extend projections to make contact with each other Release thromboxane A 2 & ADP activating other platelets Serotonin & thromboxane A 2 are vasoconstrictors decreasing blood flow through the injured vessel Tortora & Grabowski 9/e 2000 JWS 47
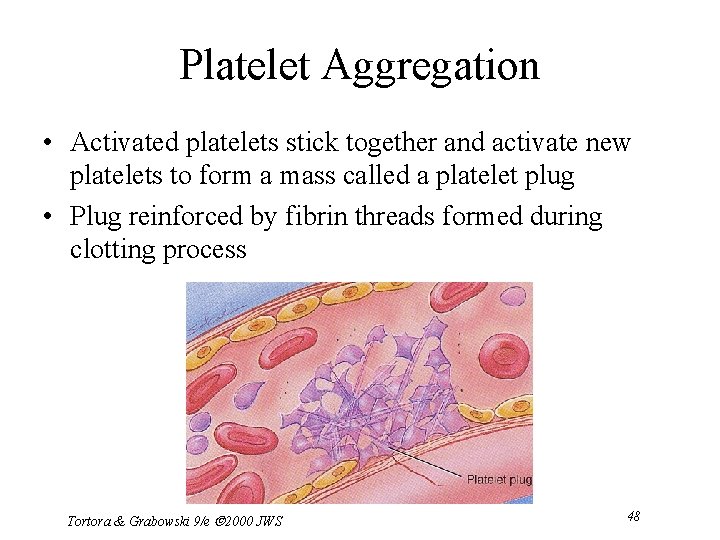
Platelet Aggregation • Activated platelets stick together and activate new platelets to form a mass called a platelet plug • Plug reinforced by fibrin threads formed during clotting process Tortora & Grabowski 9/e 2000 JWS 48

Blood Clotting • Blood drawn from the body thickens into a gel – gel separates into liquid (serum) and a clot of insoluble fibers (fibrin) in which the cells are trapped • If clotting occurs in an unbroken vessel is called a thrombosis • Substances required for clotting are Ca+2, enzymes synthesized by liver cells and substances released by platelets or damaged tissues • Clotting is a cascade of reactions in which each clotting factor activates the next in a fixed sequence resulting in the formation of fibrin threads – prothrombinase & Ca+2 convert prothrombin into thrombin – thrombin converts fibrinogen into fibrin threads Tortora & Grabowski 9/e 2000 JWS 49
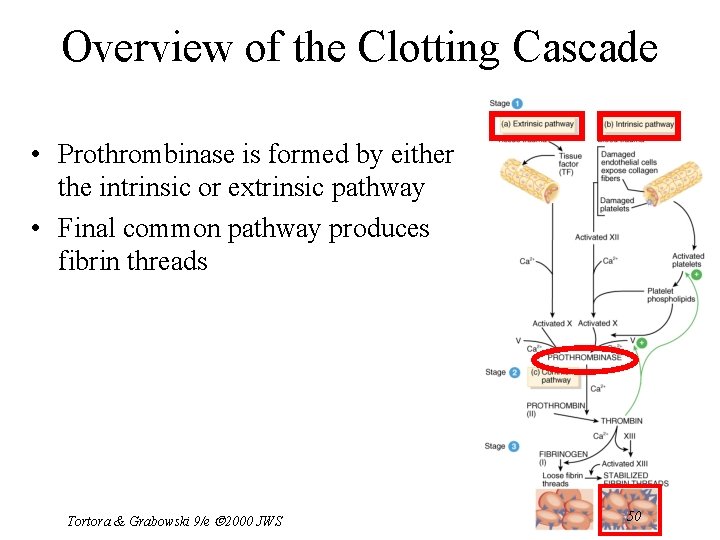
Overview of the Clotting Cascade • Prothrombinase is formed by either the intrinsic or extrinsic pathway • Final common pathway produces fibrin threads Tortora & Grabowski 9/e 2000 JWS 50

Extrinsic Pathway • Damaged tissues leak tissue factor (thromboplastin) into bloodstream • Prothrombinase forms in seconds • In the presence of Ca+2, clotting factor X combines with V to form prothrombinase Tortora & Grabowski 9/e 2000 JWS 51
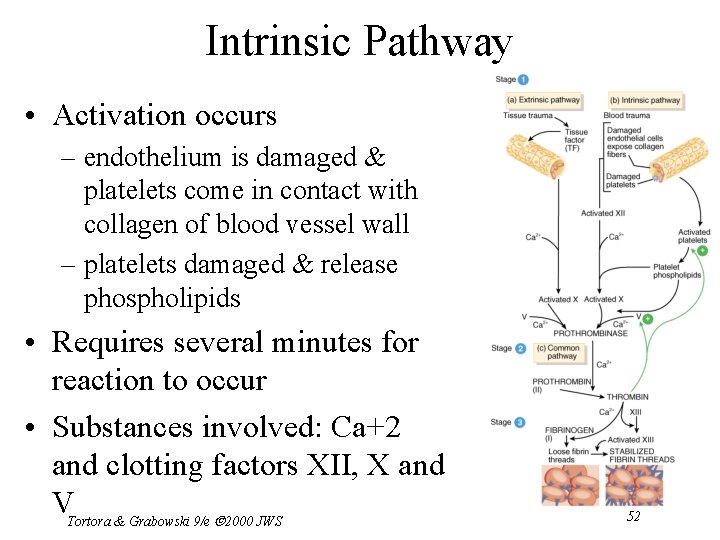
Intrinsic Pathway • Activation occurs – endothelium is damaged & platelets come in contact with collagen of blood vessel wall – platelets damaged & release phospholipids • Requires several minutes for reaction to occur • Substances involved: Ca+2 and clotting factors XII, X and VTortora & Grabowski 9/e 2000 JWS 52
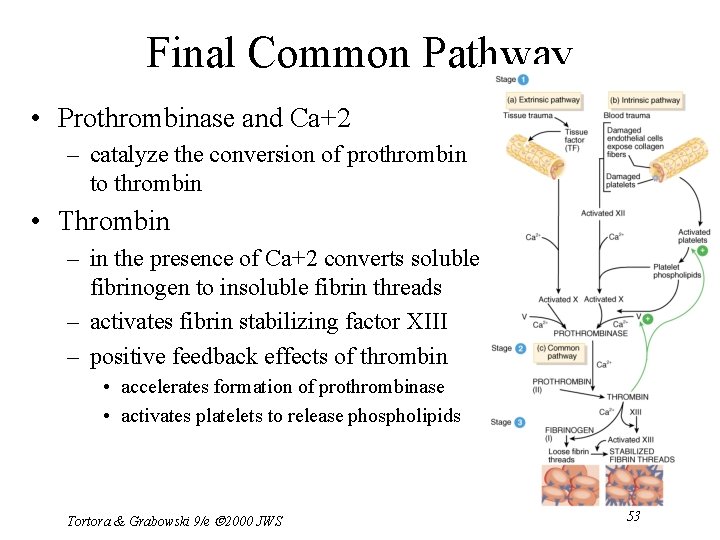
Final Common Pathway • Prothrombinase and Ca+2 – catalyze the conversion of prothrombin to thrombin • Thrombin – in the presence of Ca+2 converts soluble fibrinogen to insoluble fibrin threads – activates fibrin stabilizing factor XIII – positive feedback effects of thrombin • accelerates formation of prothrombinase • activates platelets to release phospholipids Tortora & Grabowski 9/e 2000 JWS 53
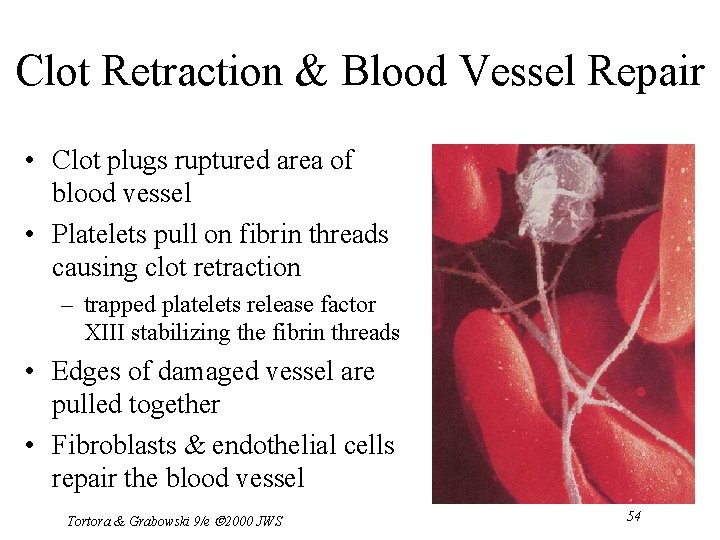
Clot Retraction & Blood Vessel Repair • Clot plugs ruptured area of blood vessel • Platelets pull on fibrin threads causing clot retraction – trapped platelets release factor XIII stabilizing the fibrin threads • Edges of damaged vessel are pulled together • Fibroblasts & endothelial cells repair the blood vessel Tortora & Grabowski 9/e 2000 JWS 54

Role of Vitamin K in Clotting • Normal clotting requires adequate vitamin K – fat soluble vitamin absorbed if lipids are present – absorption slowed if bile release is insufficient • Required for synthesis of 4 clotting factors by hepatocytes – factors II (prothrombin), VII, IX and X • Produced by bacteria in large intestine Tortora & Grabowski 9/e 2000 JWS 55
Hemostatic Control Mechanisms • Fibrinolytic system dissolves small, inappropriate clots & clots at a site of a completed repair – fibrinolysis is dissolution of a clot • Inactive plasminogen is incorporated into the clot – activation occurs because of factor XII and thrombin – plasminogen becomes plasmin (fibrinolysin) which digests fibrin threads • Clot formation remains localized – fibrin absorbs thrombin – blood disperses clotting factors – endothelial cells & WBC produce prostacyclin that opposes thromboxane A 2 (platelet adhesion & release) • Anticoagulants present in blood & produced by mast cells 56 Tortora & Grabowski 9/e 2000 JWS –

Intravascular Clotting • Thrombosis – clot (thrombus) forming in an unbroken blood vessel • forms on rough inner lining of BV • if blood flows too slowly (stasis) allowing clotting factors to build up locally & cause coagulation – may dissolve spontaneously or dislodge & travel • Embolus – clot, air bubble or fat from broken bone in the blood • pulmonary embolus is found in lungs • Low dose aspirin blocks synthesis of thromboxane A 2 & reduces inappropriate clot formation – strokes, TIAs and myocardial infarctions Tortora & Grabowski 9/e 2000 JWS 57
Anticoagulants and Thrombolytic Agents • Anticoagulants suppress or prevent blood clotting – heparin • administered during hemodialysis and surgery – warfarin (Coumadin) • antagonist to vitamin K so blocks synthesis of clotting factors • slower than heparin – stored blood in blood banks treated with citrate phosphate dextrose (CPD) that removes Ca+2 • Thrombolytic agents are injected to dissolve clots – directly or indirectly activate plasminogen – streptokinase or tissue plasminogen activator (t-PA) Tortora & Grabowski 9/e 2000 JWS 58
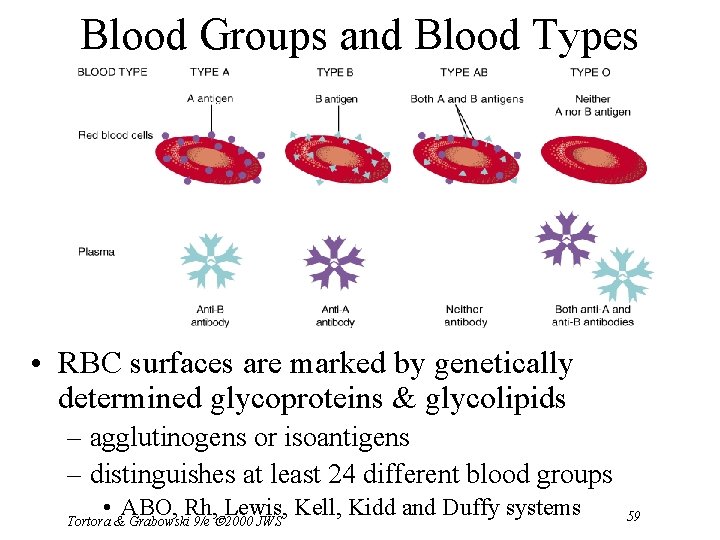
Blood Groups and Blood Types • RBC surfaces are marked by genetically determined glycoproteins & glycolipids – agglutinogens or isoantigens – distinguishes at least 24 different blood groups • ABO, Rh, Lewis, Kell, Kidd and Duffy systems Tortora & Grabowski 9/e 2000 JWS 59

ABO Blood Groups • Based on 2 glycolipid isoantigens called A and B found on the surface of RBCs – display only antigen A -- blood type A – display only antigen B -- blood type B – display both antigens A & B -- blood type AB – display neither antigen -- blood type O • Plasma contains isoantibodies or agglutinins to the A or B antigens not found in your blood – anti-A antibody reacts with antigen A – anti-B antibody reacts with antigen B Tortora & Grabowski 9/e 2000 JWS 60

RH blood groups • Antigen was discovered in blood of Rhesus monkey • People with Rh agglutinogens on RBC surface are Rh+. Normal plasma contains no anti-Rh antibodies • Antibodies develop only in Rh- blood type & only with exposure to the antigen – transfusion of positive blood – during a pregnancy with a positive blood type fetus • Transfusion reaction upon 2 nd exposure to the antigen results in hemolysis of the RBCs in the donated blood 61 Tortora & Grabowski 9/e 2000 JWS
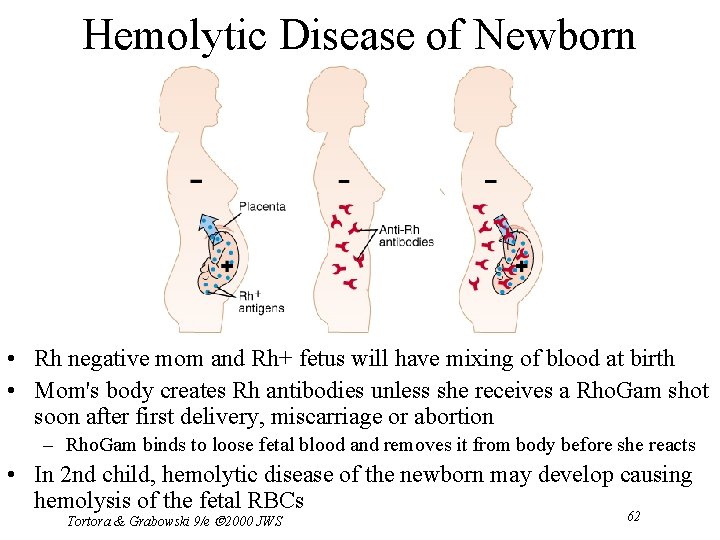
Hemolytic Disease of Newborn • Rh negative mom and Rh+ fetus will have mixing of blood at birth • Mom's body creates Rh antibodies unless she receives a Rho. Gam shot soon after first delivery, miscarriage or abortion – Rho. Gam binds to loose fetal blood and removes it from body before she reacts • In 2 nd child, hemolytic disease of the newborn may develop causing hemolysis of the fetal RBCs Tortora & Grabowski 9/e 2000 JWS 62
Transfusion and Transfusion Reactions • Transfer of whole blood, cells or plasma into the bloodstream of recipient – used to treat anemia or severe blood loss • Incompatible blood transfusions – antigen-antibody complexes form between plasma antibodies & “foreign proteins” on donated RBC's (agglutination) – donated RBCs become leaky (complement proteins) & burst – loose hemoglobin causes kidney damage • Problems caused by incompatibility between donor’s cells and recipient’s plasma • Tortora Donor plasma is too diluted to cause problems 63 & Grabowski 9/e 2000 JWS

Universal Donors and Recipients • People with type AB blood called “universal recipients” since have no antibodies in plasma – only true if cross match the blood for other antigens • People with type O blood cell called “universal donors” since have no antigens on their cells – theoretically can be given to anyone Tortora & Grabowski 9/e 2000 JWS 64

Typing and Cross-Matching Blood • Mixing of incompatible blood causes agglutination (visible clumping) – formation of antigen-antibody complex that sticks cells together – not the same as blood clotting • Typing involves testing blood with known antisera that contain antibodies A, B or Rh+ • Cross-matching is to test by mixing donor cells with recipient’s serum • Screening is to test recipient’s serum against known RBC’s having known antigens 65 Tortora & Grabowski 9/e 2000 JWS
Anemia = Not Enough RBCs • Symptoms – oxygen-carrying capacity of blood is reduced – fatigue, cold intolerance & paleness • lack of O 2 for ATP & heat production • Types of anemia – iron-deficiency =lack of absorption or loss of iron – pernicious = lack of intrinsic factor for B 12 absorption – hemorrhagic = loss of RBCs due to bleeding (ulcer) – hemolytic = defects in cell membranes cause rupture – thalassemia = hereditary deficiency of hemoglobin – aplastic = destruction of bone marrow (radiation/toxins) 66 Tortora & Grabowski 9/e 2000 JWS
Sickle-cell Anemia (SCA) • Genetic defect in hemoglobin molecule (Hb-S) that changes 2 amino acids – at low very O 2 levels, RBC is deformed by changes in hemoglobin molecule within the RBC • sickle-shaped cells rupture easily = causing anemia & clots • Found among populations in malaria belt – Mediterranean Europe, sub-Saharan Africa & Asia • Person with only one sickle cell gene – increased resistance to malaria because RBC membranes leak K+ & lowered levels of K+ kill the parasite infecting the red blood cells Tortora & Grabowski 9/e 2000 JWS 67

Hemophilia • Inherited deficiency of clotting factors – bleeding spontaneously or after minor trauma – subcutaneous & intramuscular hemorrhaging – nosebleeds, blood in urine, articular bleeding & pain • Hemophilia A lacks factor VIII (males only) – most common • Hemophilia B lacks factor IX (males only) • Hemophilia C (males & females) – less severe because alternate clotting activator exists • Treatment is transfusions of fresh plasma or concentrates of the missing clotting factor Tortora & Grabowski 9/e 2000 JWS 68

Disseminated Intravascular Clotting • Life threatening paradoxical presence of blood clotting and bleeding at the same time throughout the whole body – so many clotting factors are removed by widespread clotting that too few remain to permit normal clotting • Associated with infections, hypoxia, low blood flow rates, trauma, hypotension & hemolysis • Clots cause ischemia and necrosis leading to multisystem organ failure Tortora & Grabowski 9/e 2000 JWS 69

Leukemia • Acute leukemia – uncontrolled production of immature leukocytes – crowding out of normal red bone marrow cells by production of immature WBC – prevents production of RBC & platelets • Chronic leukemia – accumulation of mature WBC in bloodstream because they do not die – classified by type of WBC that is predominant--monocytic, lymphocytic. Tortora & Grabowski 9/e 2000 JWS 70
- Slides: 70