
Celiac Disease in Primary Care Dustin M Adkins






- Slides: 13
Celiac Disease in Primary Care Dustin M Adkins Spring 2007
Essentials of Celiac Disease n n n Autoimmune disorder triggered by gluten “Gluten” is a collective term for the storage proteins of wheat, rye, and barley. Adaptive/innate immune response damages villi in the proximal small intestine Not just GI complaints! A multisystem disorder with highly variable presentation Increased risk of Non Hodgkins Lymphoma (2. 7 -6. 3 x) and overall mortality (1. 9 -3. 4 x)
Epidemiology n n n Not as “rare” as once thought Affects 1: 100 in USA (AGA 2007) Underdiagnosed
Classical (Textbook) Celiac Disease n n n Symptoms and complications of malabsorption Hallmark: Diarrhea/steatorrhea (chronic) Abdominal distension, edema, extreme lethargy, weight loss, failure to thrive Onset at any age, gradual or rapid Often fulfills criteria for IBS. Be suspicious of refractory IBS-D especially with associated celiac symptoms! http: //www. pigur. co. il/imgceliac/celiac. jpg
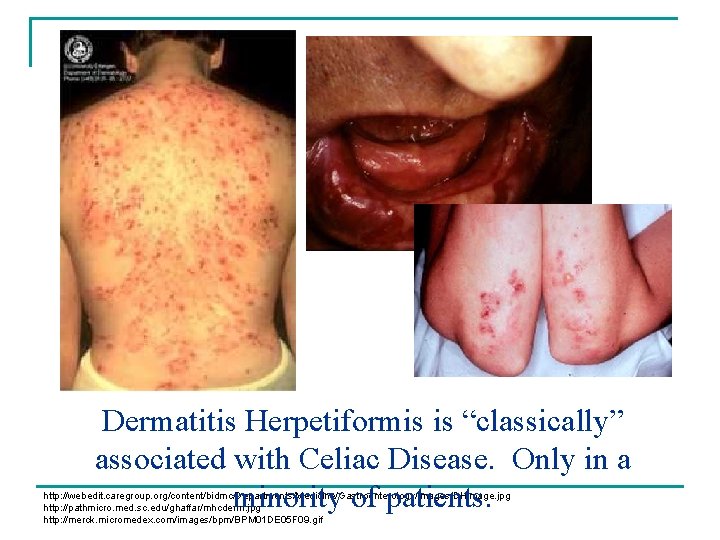
Dermatitis Herpetiformis is “classically” associated with Celiac Disease. Only in a minority of patients. http: //webedit. caregroup. org/content/bidmc/Departments/Medicine/Gastroenterology/images/DHimage. jpg http: //pathmicro. med. sc. edu/ghaffar/mhcderm. jpg http: //merck. micromedex. com/images/bpm/BPM 01 DE 05 F 09. gif
Atypical Celiac Disease n n n MOST COMMON presentation Extra-intestinal manifestations dominate Blood, Bones, & Babies q q q n Iron deficiency anemia: Unexplained or irontherapy-refractory (2. 3%-5. 0%) Osteoporosis: Premature onset (1. 0%-3. 4%) Infertility: Unexplained, recurrent fetal loss (2. 1%4. 1%) Many other S/Sx: short stature, fatigue, delayed puberty, vitamin deficiencies…
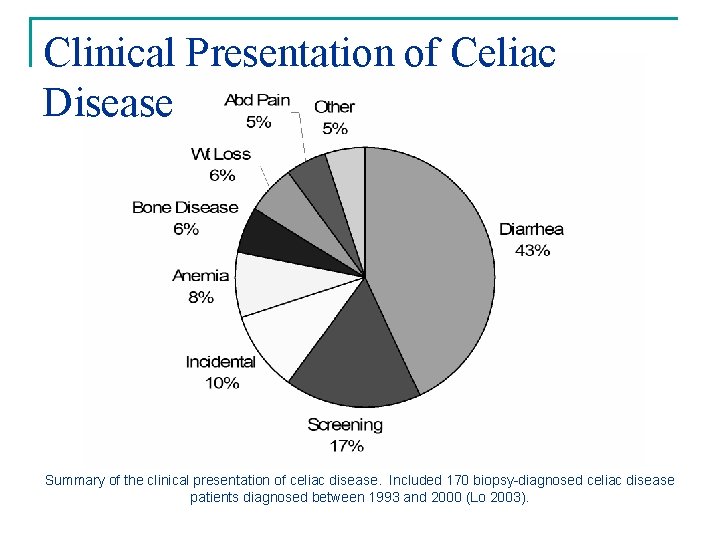
Clinical Presentation of Celiac Disease Summary of the clinical presentation of celiac disease. Included 170 biopsy-diagnosed celiac disease patients diagnosed between 1993 and 2000 (Lo 2003).
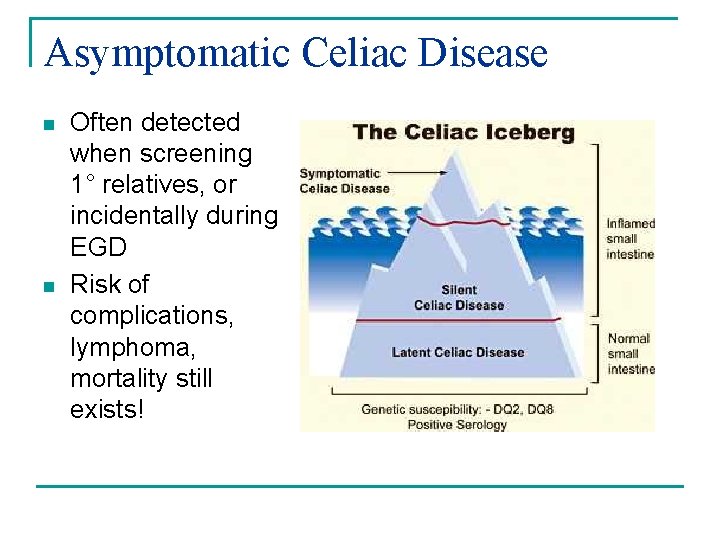
Asymptomatic Celiac Disease n n Often detected when screening 1° relatives, or incidentally during EGD Risk of complications, lymphoma, mortality still exists!
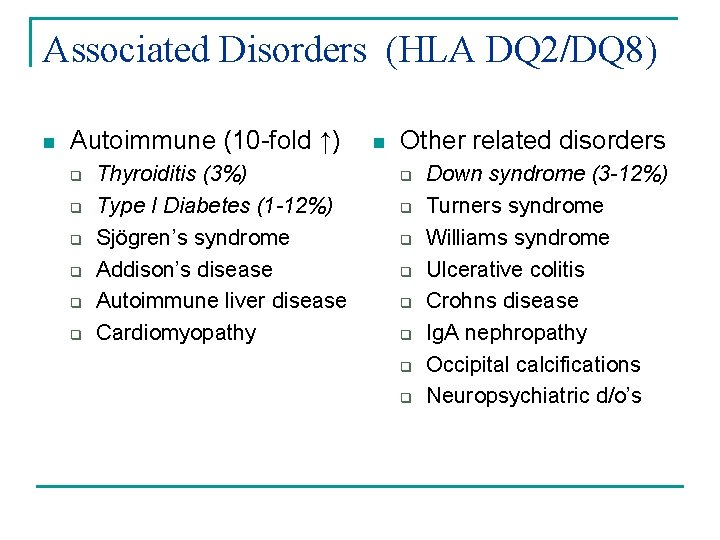
Associated Disorders (HLA DQ 2/DQ 8) n Autoimmune (10 -fold ↑) q q q Thyroiditis (3%) Type I Diabetes (1 -12%) Sjögren’s syndrome Addison’s disease Autoimmune liver disease Cardiomyopathy n Other related disorders q q q q Down syndrome (3 -12%) Turners syndrome Williams syndrome Ulcerative colitis Crohns disease Ig. A nephropathy Occipital calcifications Neuropsychiatric d/o’s
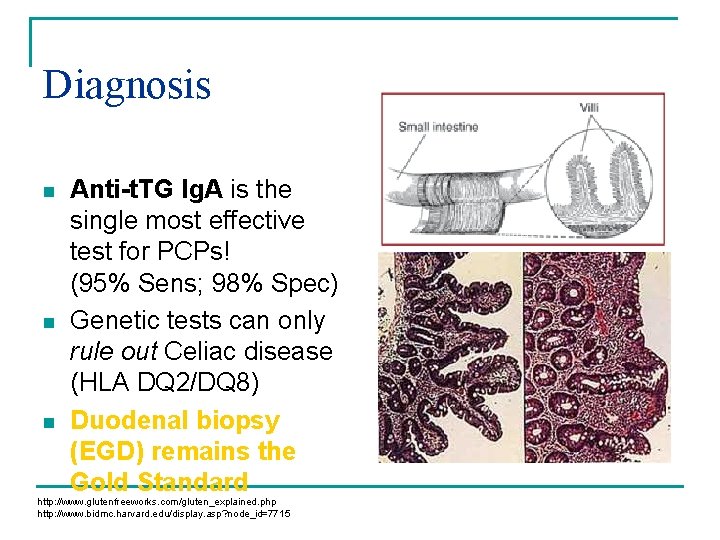
Diagnosis n n n Anti-t. TG Ig. A is the single most effective test for PCPs! (95% Sens; 98% Spec) Genetic tests can only rule out Celiac disease (HLA DQ 2/DQ 8) Duodenal biopsy (EGD) remains the Gold Standard http: //www. glutenfreeworks. com/gluten_explained. php http: //www. bidmc. harvard. edu/display. asp? node_id=7715
Treatment: Lifelong Gluten-Free Diet n Difficult task for the Never advise a patient. to start a Gluten-Free n Should see a registered Diet before biopsy! dietician Complicated by fastfood. Itlifestyles, hidden alters the ingredients, poor histopathology labeling, and requiring additional costly/unavailable specialty testingfoods. ($$$), n Lifelong diet normalizes and ticks off the mortality/comborbidity gastroenterologist! risks n
Lifelong care for the Celiac Patient n n Take a good history! Symptom improvement doesn’t mean all gluten has been removed from the diet. Make sure the patient has support q q n Work with pharmacist to avoid gluten in drugs q q n Celiac support groups Tons of online info on gluten-free dieting Nardil, Humira, Flonase, Claritin…look it up! Inactive ingredients (dextri-maltose, dusting powder, starches) Watch out for anemia, osteoporosis, infertility, and vitamin deficiencies
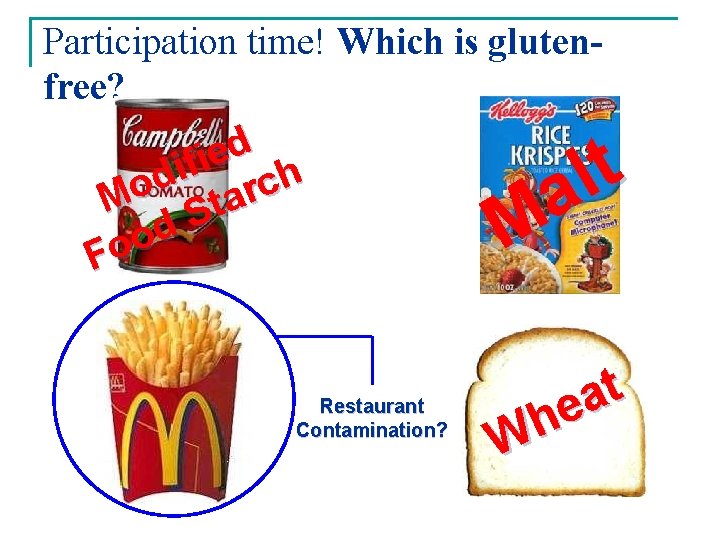
Participation time! Which is glutenfree? d e i f i h d c o M Star d o Fo Restaurant Contamination? t l a M t a e h W