
Cath Lab Financial Challenges in 2020 and How

Cath Lab Financial Challenges in 2020 and How to Deal with Them Michael Guiry, PA-C, MBA Vice President, Cardiovascular Service Line St. Luke’s University Health Network

Michael Guiry, PA-C, MBA I have no relevant financial relationships
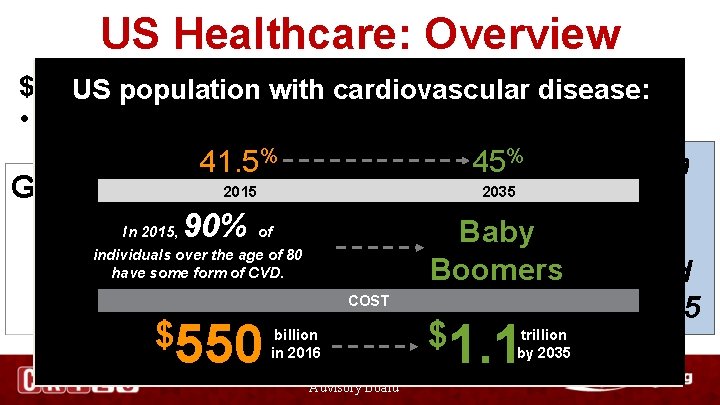
US Healthcare: Overview $3. 6 US trillion = cost of UScardiovascular Healthcare in 2018 population with disease: • ($11, 172 person, 4. 6% increase year over year) GDP 41. 5% 2018 US GDP: 45% $20. 5 Trillion 17. 7% 2015 90% 2035 Baby Boomers Healthcare spend projected COST to reach $5. 5 Trillion by 2025 In 2015, of individuals over the age of 80 have some form of CVD. $550 inbillion 2016 $1. 1 bytrillion 2035 CMS. gov, research/data statistics Advisory Board

Health Premiums Continue to Rise 2019 Health Premiums: Single Coverage = $7, 188 Family Coverage = $20, 576 More costs shifting to patients Source: Kaiser/HRET Survey of Employer-Sponsored Health Benefits.

Healthcare Reform Goals Access Quality Cost QUALITY = VALUE COST Cost
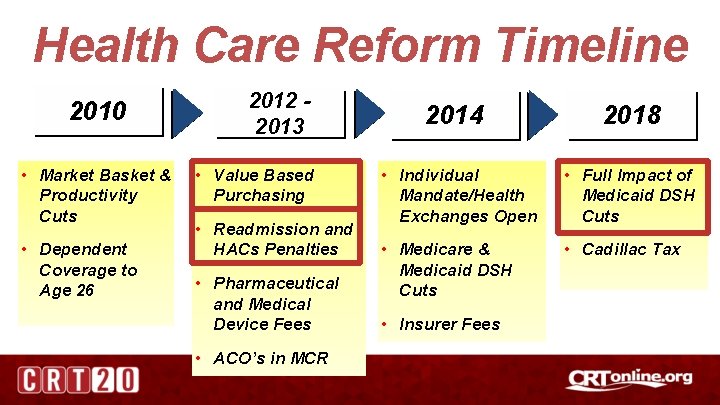
Health Care Reform Timeline 2010 • Market Basket & Productivity Cuts • Dependent Coverage to Age 26 2012 2013 • Value Based Purchasing • Readmission and HACs Penalties • Pharmaceutical and Medical Device Fees • ACO’s in MCR 2014 2018 • Individual Mandate/Health Exchanges Open • Full Impact of Medicaid DSH Cuts • Medicare & Medicaid DSH Cuts • Cadillac Tax • Insurer Fees
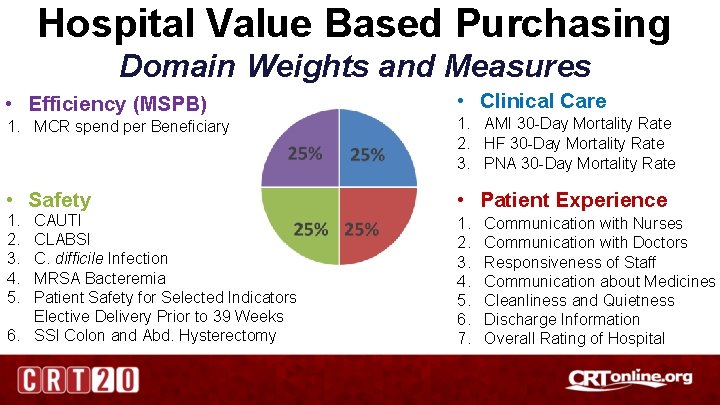
Hospital Value Based Purchasing Domain Weights and Measures • Efficiency (MSPB) • Clinical Care 1. MCR spend per Beneficiary 1. AMI 30 -Day Mortality Rate 2. HF 30 -Day Mortality Rate 3. PNA 30 -Day Mortality Rate • Safety • Patient Experience 1. 2. 3. 4. 5. CAUTI CLABSI C. difficile Infection MRSA Bacteremia Patient Safety for Selected Indicators Elective Delivery Prior to 39 Weeks 6. SSI Colon and Abd. Hysterectomy 1. 2. 3. 4. 5. 6. 7. Communication with Nurses Communication with Doctors Responsiveness of Staff Communication about Medicines Cleanliness and Quietness Discharge Information Overall Rating of Hospital
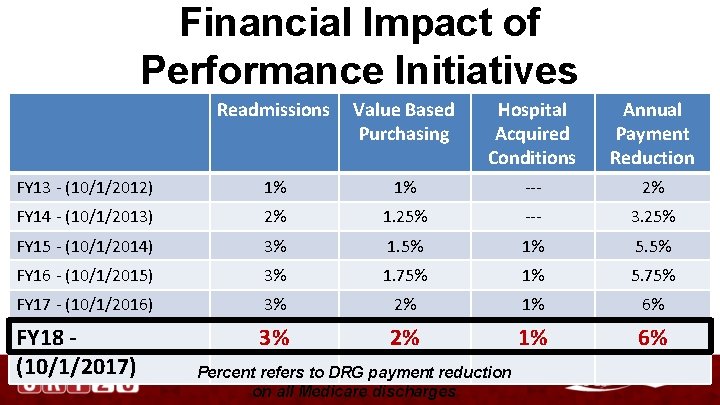
Financial Impact of Performance Initiatives Readmissions Value Based Purchasing Hospital Acquired Conditions Annual Payment Reduction FY 13 - (10/1/2012) 1% 1% --- 2% FY 14 - (10/1/2013) 2% 1. 25% --- 3. 25% FY 15 - (10/1/2014) 3% 1. 5% 1% 5. 5% FY 16 - (10/1/2015) 3% 1. 75% 1% 5. 75% FY 17 - (10/1/2016) 3% 2% 1% 6% FY 18 (10/1/2017) 3% 2% 1% 6% Percent refers to DRG payment reduction on all Medicare discharges
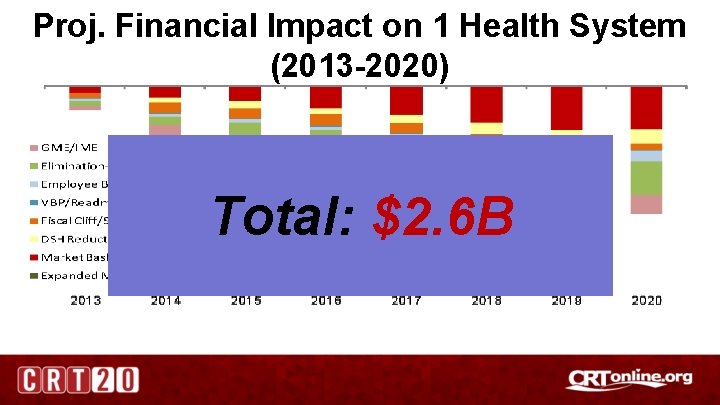
Proj. Financial Impact on 1 Health System (2013 -2020) Total: $2. 6 B

2020 Closures/Acquisitions/Mergers ▪ Financially Challenged ▪ Market Moving to Consolidation

New Entrants in the Healthcare Industry § Physician-owned centers § Urgent Care Centers § Narrow/tiered networks § ACOs § Integrated systems § Private Equity

US Healthcare Challenges “Old Formula” for success, increasing Price and Volume, will not continue to work. Why? Ø The public is increasingly becoming price sensitive and there is an emphasis on value. Ø Pressure from all stakeholders is increasing Ø Delivery models are changing
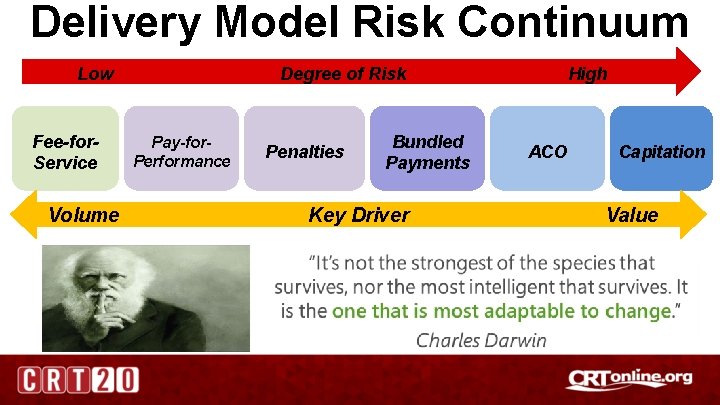
Delivery Model Risk Continuum Low Fee-for. Service Volume Degree of Risk Pay-for. Performance Penalties Bundled Payments Key Driver High ACO Capitation Value • 2019 MACRA/MIPS/APMS – driving physician alignment. • CV Bundled payments introduced voluntary bundles 2018
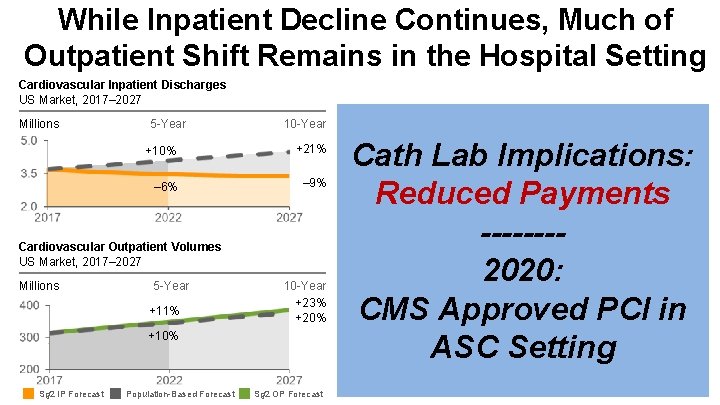
While Inpatient Decline Continues, Much of Outpatient Shift Remains in the Hospital Setting Cardiovascular Inpatient Discharges US Market, 2017– 2027 Millions 5 -Year 10 -Year +10% +21% – 6% – 9% Cardiovascular Outpatient Volumes US Market, 2017– 2027 Millions 5 -Year +11% 10 -Year +23% +20% +10% Sg 2 IP Forecast Population-Based Forecast Sg 2 OP Forecast Cath Lab Implications: Reduced Payments -------2020: CMS Approved PCI in ASC Setting

Bending the Medical Cost Curve Key Drivers ❖Decrease / Shift in Utilization ❖Decrease of Price / Rate Trends ❖Lower Ambulatory Price in Market ❖Network Design ❖Plan Design ❖Utilization Review ❖Medical Management ❖Disease Management ❖Wellness Programs Government and Private Payers are engaging providers to participate in value based plans in order to improve efficiency while demonstrating evidence of higher quality scores.

Align and Engage Front-line Staff to Lower Costs and Drive Quality

Opportunities Alignment • Create waste reduction strategy in the organization • Adopt integrated performance measurement systems • Redesign the system to achieve superior results in reduced costs, improved quality, and patient engagement • Align operations for the new reimbursement world

Opportunities Engagement • Engage staff in the what & why of value delivery • Engage patient & family perspective • Ensure a safe environment for sharing ideas • Develop and support new skills at all levels of the system

Clinical Resource Utilization • Goal: Monitor practice patterns to ensure standardization whenever possible • Choice Awareness • Price Transparency • Standardize Practices • Physician Metrics • Reprocessing • Bulk Opportunities • Standard Packs/Kits • Eliminate Waste/Overuse
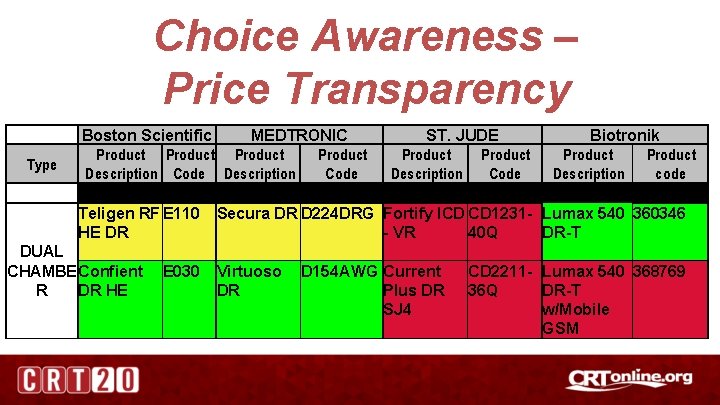
Choice Awareness – Price Transparency Type Boston Scientific MEDTRONIC Product Description Code Teligen RF E 110 HE DR DUAL CHAMBE Confient R DR HE E 030 ST. JUDE Product Description Code Biotronik Product Description code Secura DR D 224 DRG Fortify ICD CD 1231 - Lumax 540 360346 - VR 40 Q DR-T Virtuoso DR D 154 AWG Current Plus DR SJ 4 CD 2211 - Lumax 540 368769 36 Q DR-T w/Mobile GSM

Final Thoughts • Healthcare reform has fostered greater pressure to improve quality and change healthcare delivery • Competition along with advances in prevention, diagnosis, and technology are shifting the setting of care and paving the way for new healthcare initiatives • Transparency, engagement, and coordination with front -line staff are some of the key elements to improve quality, lower healthcare costs and improve the Cath Lab bottom line.

- Slides: 22