
Case taking PREPARED BY Dr PANCHAJANI R Case

Case taking PREPARED BY , Dr. PANCHAJANI. R

Case taking • • No hurry during conversation. Hear sympathetically. Behave patiently with the patient. Should show good bedside manners.

Case taking includes 1. 2. 3. 4. 5. 6. 7. 8. 9. 10. 11. 12. Particulars of the Patient Presenting complaints H/O Presenting complaints. Previous History Family history. Personal history. Physical examinations. Differential diagnosis Investigations. Final diagnosis. Management. Follow up.

Particulars of the patient • • Name Age Sex Religion Residence Occupation Social status

Presenting complaints • Main complaints with duration. ( location & sensation) • Recorded in the chronological order of occurrence. • Aggravating factors & Ameliorating factors. • Accompanying symptoms.

H/O Presenting complaints • Onset of the present disease until date. • Mode of Onset of symptom. (Sudden / gradual) • Progress of the disease. ( increasing/ decreasing etc. . ) • Related symptoms suggestive of complications of the disease. • Associated symptoms.

Previous History • Earlier diseases should be detailed in order with treatment taken. • History of earlier surgery/ trauma. • History of allergy. (medicine, food etc. ) • Long term drug intake. ( anti hypertensive, diabetic etc. . )

Personal History • Personal habits. (smoking/drinking/addictions with duration, quantity). • Diet • Appetite. • Thirst • Weight. • Bowel& Micturition habits. • Sleep. • Females menstrual history.

Family History • Genetic History. • Diseases runs in families. • Familial diseases. (paternal/ maternal relatives) • Marital status.

Physical Examination • GENERAL PHYSICAL EXAMINATION. • SYSTEMIC EXAMINATION.

General physical examinations • Examination of a patient with out referring to a particular system. • For Proper Diagnosis and differential diagnosis. •

General Physical Examination • • • • Gait Mental status Built & Nutritional status Attitude &Decubitus Stature & posture Facies Pigmentations Anaemia Jaundice Cyanosis Clubbing Oedema Visible veins Lymphadenopathy

Vital Signs • • • Pulse. Temperature. Respiration. Blood pressure. Height & weight.

Gait • Way of walking. • Important in neurological/ musculoskeletal disorder. • Note the way he moves.

Gait- Types 1. 2. 3. 4. 5. 6. High stepping gait – foot is lifted high & then falls on the ground. Seen in peripheral neuritis & tabes dorsalis. Waddling gait – abdomen is thrown forward due to lordosis. seen in pseudo hypertrophic paralysis , congenital dislocation of hip. Spastic gait – walks the toes do not bend at knee, foot is raised by tilting up the pelvis & the leg swang forward. Stiff leg due to spasticity. Found in UMNL. Festinant gait/ parkinsonian gaint – limbs are rigid & in a state of flexion, walks with short steps. Found in striated lesion. Stamping gait - raises the foot high & suddently brings this down, heels first. Found in tabes dorsalis. Reeling gait- stands on a broad base with leg wide apart, the foot is then raised high & when he walks. Reels like a drunkard

Mental status • Assess mental status & level of consciousness. • In Head injury, hepatic encephalopathy, septic shock etc. . • Grades – I - properly oriented in time, space, person. II - conscious but without orientation of time, space, person. III - Drowsy & semiconscious. IV-Unconscious but responding to painful stimuli. V- Unconscious & comatose and not responding to painful stimuli.
Built – structural development of body related to age & sex, race. • Under built – development poor(>food, vitamins) • Medium- average • Over build- more than normal. (hyper pituitarism, acromegaly)

Nutritional status • Nutrition- state of nourishment of the body • Proportion of soft tissue structures(muscles, soft tissues, fat) in relation to the bony structure. • Assessment – Body wt. in respect of ht. age, sex BMI(wt in kg/ ht. in m 2) Triceps skin fold thickness Mid arm muscle circumferance waist hip ratio(obesity) WHR- normal- < 0. 9 cm in M, < 0. 85 cm in F Serum – albumin, prealbumin, transferrin, retinol binding protein.

Nutrition • Quantitative& qualitative disorder. • Quantitative. Under nutrition/ starvation- wt. loss 10% less than normal. Over wt. - gains more than 10% Obesity – more than 20% of standard wt. (BMI>30, WHR>0. 9/0. 85 cm) • Qualitative – Malnutrition, overnutrition (food, vit. )
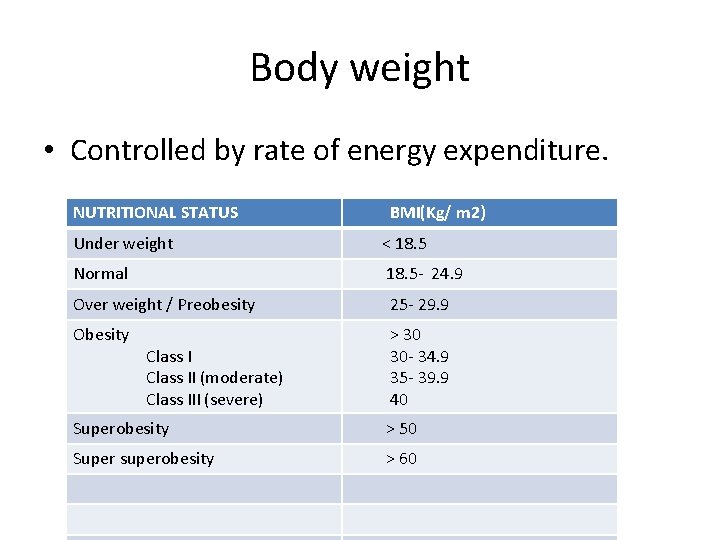
Body weight • Controlled by rate of energy expenditure. NUTRITIONAL STATUS BMI(Kg/ m 2) Under weight < 18. 5 Normal 18. 5 - 24. 9 Over weight / Preobesity 25 - 29. 9 Obesity > 30 30 - 34. 9 35 - 39. 9 40 Class II (moderate) Class III (severe) Superobesity > 50 Super superobesity > 60

Attitude • Attitude - changed position of the body or a part of the body. (posture of body as a result of disease)

Decubitus • Position of the patient in bed. • Types • Decubitus at ease • Restless D • Dorsal • Ventral • Lateral- Rt. &Lt. • Propped up • Opisthotonus • Emprosthotonus • Pleurosthotonus • Listless attitude
Stature & Posture • Stature – total height from vertex to soles. Short /Tall • Posture – Positional relationship of different regions of body. noted in standing, sitting , recumbent position. lordosis/ kyphosis /scoliosis

Facies Facial appearance & expression of pt. • Thyrotoxicosis face • Hippocratic face • Risus sardonicus • Mask face • Moon face(cushingoid) • Myxoedematous facies • Adenoid facies • Parkinsonian • Acromegaly • Mangolism
Pigmentations • • • Colour of skin(N-race, heriditory, climate) Generalised/ localised Increased/Depigmentation Color, texture, surface of skin Sites- face, palmar creases, skin, inside the oral cavity
Pigmentation • Increased – physiological- race, sunburn, preg. pathological- D. M, Ca, liver dis, v. vein, arsenic poisoning etc. . • Diminished – Vitiligo- patchy depigmentation Albinism – complete absence of pigmentation(skin, hair, iris , nystagmus , impaired vision ) Leprosy- anesthetic patches
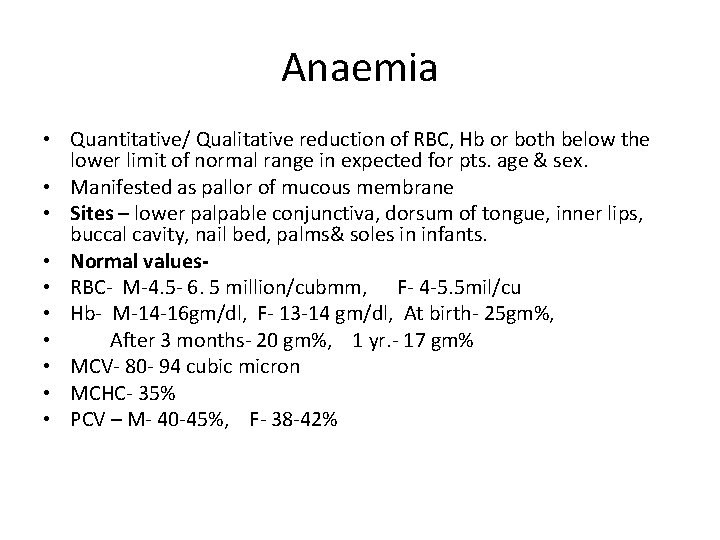
Anaemia • Quantitative/ Qualitative reduction of RBC, Hb or both below the lower limit of normal range in expected for pts. age & sex. • Manifested as pallor of mucous membrane • Sites – lower palpable conjunctiva, dorsum of tongue, inner lips, buccal cavity, nail bed, palms& soles in infants. • Normal values • RBC- M-4. 5 - 6. 5 million/cubmm, F- 4 -5. 5 mil/cu • Hb- M-14 -16 gm/dl, F- 13 -14 gm/dl, At birth- 25 gm%, • After 3 months- 20 gm%, 1 yr. - 17 gm% • MCV- 80 - 94 cubic micron • MCHC- 35% • PCV – M- 40 -45%, F- 38 -42%

Anaemia - classification Classification- RBC volume(mcv)/Hb content. • RBC- normocytic, microcytic, macrocytic • Hb- normochromic, hypochromic • Aetiological – hypo/aplastic, dyshaemopoitic, haemolytic, post haemorrhagic • Morphological- normochromic normocytic, N Ma cro, N micro, hypochromic macro, hypo micro

Jaundice • Yellowish discolouration of skin, sclera, mucous membrane, & other tissues resulting from an excess of bilirubin in blood. • Normal- 0. 2 - 0. 8 mg/dl (<1 mg/dl) • Conj- 0. 1 -0. 3, Unconj-0. 2 -0. 7 mg/dl • Clinical jaundice > 3 mg/dl • Latent jaundice -1 -3 mg/dl • Sites – sclera, under the tongue, soft palate, skin, palms& soles

Jaundice Types • Pre hepatic/ haemolytic • Hepato cellular/ infective • Post hepatic/ obstructive • Normal urinary urobilinogen-100 -200 mg/day • Normal foecal stercobilinogen -300 mg/day

CYANOSIS • Bluish/purple discolouration of skin & mucous membrane resulting from an abnormally increased amount of reduced Hb or presence of abnormal Hb in blood. • R. Hb- Exceeds 5 gm/dl • Types – Central, Peripheral, Enterogenous
Cyanosis Central- CHD, emphysema, COPD etc. . • Inadequate oxygenation of blood ( cardiac/ pulmonary) • oxygen unsaturation of arterial blood(arterial hypoxaemia). • detected for tongue, inner lips, palate • extremities not affected, not cold • associated with clubbing • oxygen inhalation may relieve

Cyanosis Peripheral – excessive reduction of oxy Hb in capillaries when the blood flow is slowed down. • happens on exposure to cold ( eg. Raynaud’s phenomena) • Peripheral vasoconstriction • pts. with reduced cardiac output • Looked for nail bed, tip of nose, skin of palms &soles, ear lobules. • Tongue unaffected • Limb cold, oxygen inhalation may not reduce. • warm application may relieve. • Not associated with clubbing Enterogenous- due to abnormal pigments or Hb. Arterial oxygen tension normal.

CLUBBING • Obliteration of the normal angle between the nail & nail bed( convexity of nails) • Hypervascularity & opening of anastamotic channels in the nail bed. • Distal end of the digit become expanded with nail curved excessively. • Nail bed becomes spongy & thickened. • Examination – both thumb nails are placed in opposition& viewed from side. normally there is a gap. In clubbing there is reduction in this gap.

Clubbing Grades Normal – Presence of normal angle between nail& nail bed • grade I - Obliteration of normal angle. • II – increase in the curvature of nail. • III – Increase in pulp tissue – drum stick appearance • IV - subperiosteal thickening of near joints(clubbing& hypertrophic pulmonary osteoarthropathy)

Clubbing Types • unilateral& bilateral • painless & painful - eg. Bronchial Ca • acute – eg- in lung abscess. causes due to persistent hypoxia & toxic conditions • cardiac • pulmonary • GIT • heriditory • subclavian aneurysm
Oedema • Accumulation of fluid in the tissue spaces. • Due to abnormal increase in the amount of interstitial fluid of the body. • Clinically evident when fluid accumulates more than 5 litres. • Clinically recognised by a diffuse swelling of subcutaneous tissues. • Types • Pitting/ Non Piting • Generalised/ Localised • Unilateral/ bilateral • It pits under pressure when firm pressure is applied on the part where there is minimum muscle between skin and underlying bone by using pulp of finger/ thumb for few seconds- Pitting oedema. • Non pitting/ solid oedema- donot pit under pressure.
Oedema • Depends on the formation & reabsorption of interstitial fluid. • Occurs in capillaries. It Depends on, • oncotic pressure/ osmotic suction force/ plasma protein pressure • blood pressure • amount of plasma protein • Lymphatics • Normal osmotic suction force/ oncotic pressure- 20 -25 mmof Hg. • Bp at the arteriolar end of capillary bed- 35 mmof Hg • Bp at venular end – 12 -15 mmof Hg. • Amount of plasma protein- about 7 gm/ 100 cc of plasma
Oedema Causes/ factors responsible • Hypoproteinemia- ↓plasma protein ↓osmotic pressure↓suction force→ oedema. cause general- effect general- generalised oedema Causes – starvation, ch. pancreatitis, renal dis, malabsorption, liver diseases etc. . Oedema pitting • Increase in Bp- venous pressure↑capillary pressure ↑ more water -→oedema Causes – external pressure on vein( tight bandage, plaster cast), venous thrombosis, CCF, Prolonged recumbency etc. . . Cause is local- local oedema. In CCF-cause general, oedema general, on dependent part , more in evening. pitting oedema Renal more in eye lids & face, then generalised. Morning.

Oedema • Causes; • Increase in capillary permeability Due to capillary damage / vaso dilatation Capillary permeability↑ out flow of fluid increases → oedema Causes- infla. , allergy, beri, anemia etc. . first 2 - cause local-oedema local- pitting type next 2 - cause general, oedema general. • Obstruction to lymphatic drainage no filteration of albumin from ISF affects Osmotic suction force, diminishes rate of absorption leads to oedema. cause local oedema local. early pitting later non pitting due to continued presence of excess protein in IS Space leads to fibrous tissue proliferation and hardness. • Sodium retension Seen in cushing syndrome due to excess of aldosterone causes sodium retension

Oedema Sites looked for, • Dependant part of body such as ankles, lumbosacral region(bed ridden pts. ), under thigh, legs etc. . • In anasarca abdominal wall, chest wall • Non pitting - angioneurotic, filariasis, myxoedema.
Lymphadenopathy • Normally palpable as a small firm nontender masses less than 0. 5 cm in diameter. • Some cases not palpable. • Pathologically – enlarge, palpable & visible • on drainage area • Primary & Secondary • generalised & localised • Painful/ painless.

Lymphadenopathy Points noted, • site • Size • Number • Consistency • Tenderness • Mobility • Matted / discrete • Fixity to the skin/overlying skin • Generalized/ localized • Adjacent group of nodes • Lesions at the area of drainage • Lymphoedema.

Lymphadenopathy Method of palpation • Palpate with tip of finger gently moved from side to side. Sites ; • Submandibular & submental- underneath the mandible • Cervical nodes • Supra clavicular- over the medial end of clavicle above the origin of the sternocleidomastoid. • Pretracheal- deep behind the sternocleidomastoid. • Axillary – apex, ante. , medial, late. , poste. , portion of axilla. • Supratrochlear • Inguinal • Poplitial- popliteal fossa • Abdominal • Mediastinal

Lymphadenopathy Causes • generalised ; infections, inflammations, neoplastic diseases. • Localised ; lesions in the drainage area Size ; small size(1 -2 cm) in secondary syphilis, infections etc. . large size- lymphomas, metastasis, diphtheria, lymphogranuloma venereum etc. .

Visible veins • Sites- over lower limbs, abdomen, trunk, neck. • Raised venous pressure causes enlargement of external jugular vein • Bilateral enlargement of neck veins/ external jugular vein in myocardial infarction, IV fluid infusion, retrosternal goitre, thoracic outlet obstruction. • Other causes- SVC & IVC obstruction • Normal JVP- 3 -4 cm of H 2 O, Better visible than felt. decreases during inspiration but becomes prominent during expiration. assessed on right side( vein on right side is in direct communication with the atrium) with 45 degree semirecumbent position with neck turned towards opposite side. Vertical distance from sternal angle to the top of blood column in the internal jugular vein is measured to get the JVP.

PULSE • Expansion of the arterial wall resulting from the pulse wave that is transmitted to it through the column of blood at each ventricular contraction. Points noted are, • Rate • Rhythm • Volume • Tension • Character • Condition of vessel wall • Equality on both sides

Pulse Rate ; number of beats per minute, count for 1 minute. • Normal – 60 - 100 b/ m( Av- 72/m) • Bradycardia – slow pulse rate below 60 b/m, found in physiological abnormality, heart block, 1 st wk. of typhoid, dengue, jaundice etc. . Below 40 b/m in mixoedema, heart block. • Relative bradycardia – tempt. Pulse ratio-1: 10 when rise is less than 10 b/m is R. B. Found in viral fever, meningitis, 1 st wk. of typhoid etc. . • Tacchycardia - increased pulse rate above 100 b/m. found in functional heart disease, thyrotoxicosis, cardiac failure, paroxysmal tacchycardia, atrial fibrillation or flutter, acute infections.

Pulse Rhythm – regularity in successive beats in time & equality of force. • Irregular rhythm – sinus arrhythmia, extrasystole, auricular fibrillation, flutter, pericarditis with effusion, heart block etc. . • Pulse deficit – difference between heart rate& pulse rate , by simultaneous auscultation of heart rate & Pulse rate. pulse rate being slow. Found in extrasystole, auricular fibrillation.

Pulse Volume – amplitude of the expansile movement of the vessel wall during the passage of pulse wave. (lift & duration) • Indicates cardiac output / beat(relates to the stroke volume) • Pulses parvus- small volume pulse • Pulses magnus- large volume pulse • Low volume indicates- peripheral failure, severe aortic stenosis, Pulm. hypertension, low cardiac output, pericardial effusion, constrictive pericarditis etc. . . • High volume- hypertension, mitral& aortic regurgitation, thyrotoxicosis, severe anaemia, cor pulmonale etc. . • In shock pulse is rapid & feeble.

Pulse Tension – amount of pressure required to obliterate the pulse wave with the palpating finger. • High tension- hypertension, thyrotoxicosis, constrictive pericarditis, polycythemia etc. . • Low tension- myocardial weakness, hypotension, peripheral failure, anaemia etc. .

Pulse Character; • Quick , small, low tension indicates mitral stenosis, • Thready –rapid, small wave pulse seen in shock, peripheral failure • Pulses alternans- regular pulse but big beats alternate with small beats. Found in LVF, myocardial ds, paroxysmal tacchycardia • Pulses paradoxus – pulse almost disappear during inspiration. Found in pericarditis with effusion, constrictive pericarditis etc. . • Pulses bigeminus/ trigeminus- pulse goes in 2 or 3 grouped together followed by a pause. Found in extra systole, heart block, digitalis toxicity etc. . • Bounding pulse- found in vasodilatation, preg. , increased cardiac output, thyrotoxicosis. • Corrigens/ water hammer/ collapsing pulse- short, sharp impact or tap during systole (large volume) & collapsing during diastole ( low tension)is felt. Pulse pressure increased. Found in aortic regurgitation, severe anaemia, thyrotoxicosis, aneurysm etc. .
Pulse Condition of vessel wall • Palpate the artery with three fingers. emptying the artery by pressing out the blood distally, with the middle finger rolls the artery over the underlying bone to assess thickness & consistency. • Normally palpate as a soft collapsing tube. • Thickening, irregularity& cord like feel suggest arteriosclerosis. • On auscultation of arteries normally no bruit , increased blood flow causes bruit.

Pulse Sites ; • Any superficial/ palpable artery. Common sites; • wrist over the radial artery( common) • Dorsum of foot over the dorsalis artery • Side of neck over the common carotid artery. • Inner aspect of arm over the brachial artery • Temporal fossa over the temporal artery • Epigastric & umbilical region for aortic pulse. • Femoral artery in the groin. • Popliteal artery in the popliteal fossa. • Posterior tibial behind the medial malleolus. Technique of exam. – pt. must take complete rest for some time before taking pulse. Put 3 fingers over the radial artery , with the distal finger stop the reflux, proximal finger apply variable amount of pressure& with middle finger feel the rate, tension etc. .

Respiration Includes inspiration& expiration. Clinical sign that represents ventilation. Points noted; • type • rate • Rhythm

Respiration Type ; indicates the condition of chest, abdomen & diaphragm. Normal types – on inspection • Abdomino- thoracic – abdomen moves more than the thorax. found in males & children. • Thoraco- abdominal- thorax moves more than the abdomen. found in females. Abnormal types; Abdominal resp. – only the abdomen moves with no or slight movement of thorax. Found in painful chest wall like fracture, paralysis of intercostal muscles, stiffness of chest wall, pneumothorax, emphysema etc. . Thoracic resp. – thorax moves with slight or no movement of abdomen. Found in acute inflammatory conditions of the abdomen, paralysis of diaphragm, full term preg. Etc. . On auscultation normal types; Vescicular breathing Bronchial Broncho vescicular

Respiration Rate – number of breaths / m • Normal (at rest) – 12 -18 b/m in an adult when the pulse rate is 72 b/m , tempt. 98. 4 F. ( resp. centre sets a rhythm of 2 sec. for inhalation & 3 sec. for exhalation) New born- 30 -60 b/m, infant(6 -12 m)- 24 -30 b/m, 1 -5 yrs- 20 -30 b/m, 6 -12 yrs- 12 -20 b/m • Pulse: Resp – 4: 1, Temp: Pul- 1: 10 temp: Resp-1: 2. 5/3 • Abnormal rate • Tacchypnoea – increased resp. rate in comparison to pulse& tempt. Found in pneumonia, acute bronchitis, nervousness, fever, excertion etc. . • Bradypnoea – slow resp. rate. Found in alcohol , poisoning, cerebral hge, meningitis, ureamia, diabetic coma, epilepsy, hysteria, shock, collapse etc. . • Apnoea – cessation of resp.

Respiration Rhythm; regularity ( breathing pattern) • Normal rhythm- ratio of inspiration & expiration is 1: 2 at rest. On exertion 1: 1. Abnormal/ altered rhythm: 1. Prolonged inspiration- due to narrowing of air passages. Found in laryngeal/ tracheal/ bronchial obstruction , laryngeal diphtheria, bronchopneumonia etc. . 2. Prolonged expiration- due to diminished elasticity of lungs & narrowing of bronchial tubes. Found in chronic bronchitis, bronchial asthma, emphysema, early pulm. TB, tropical eosinophilia etc. . 3. Hyperpnoea – depth of resp. increased , not rate 4. Hyperventilation – rate & depth of resp. increased.

RESPIRATION- rhythm 5. Periodic breathing ; 2 Types Cheynestokes resp. - gradual deepening of resp. alternates with short periods of apnoea. Hyperpnoea(3 m) alternates with apnoea(30 sec). Common in deep sleep, left ventricular failure, narcotics, pneumonia, head injury, resp. distress, ureamia, diabetic coma etc. . • Biots resp. - 2 or 3 quick deep& irregular resp. followed by a period of apnoea, then gradually falls. Found in cardiac failure, renal failure, TB meningitis etc. . 6. Short & interrupted breathing- resp. is broken& short due to some painful condition of chest. Found in dry pleurisy, fractured ribs, hysteria etc. . 7. Stridulous breathing – resp. makes a sound which resembles a sound produced by the friction of rough surfaces due to spasm or obstruction. Found in laryngismus stridulus, foreign bodies, tetanus, diphtheria etc.

Respiration- rhythm 8. Stertorous breathing - by a sonorous or snoring sound. Found in paralysis of soft palate, deep sleep, adenoids, epilepsy, diabetic coma etc. . 9. kussmaul’s breathing- deep sighing, rapid breathing and a regular rate. found in uraemia, diabetic coma, cerebral tumour etc. .

Blood pressure • Lateral pressure exerted on the vessel wall by the column of blood while flowing through it. • More in arteries near the heart than in the periphery. • Systolic & diastolic • Systolic- maximum pressure during the propogation of pulse wave. It indicates maximum work of heart. Occur during ventricular systole. due to stroke volume of heart &stiffness of vessels. liable to nervous influences. • Diastolic- during ventricular relaxation. constant pressure in the artery between each systole. due to peripheral resistance. More constant, more significant, less liable to nervous influences & external factors. • Pulse pressure; difference between systolic & diastolic pressure, normal – 40 -60 mm of Hg. • Bp depends on cardiac output, peripheral resistance, viscosity & volume of blood, elasticity of blood vessel, venous return, diameter of blood vessel.

Blood pressure • • • Sphygmomanometer- mercury, aneroid, digital. Methods ; Palpatory & auscultatory methods Rest for 5 minutes before checking Bp. Avoid exertion or meals 30 minutes prior to check Bp Width(40% of upper arm circumference) &length(80% of upper arm circumference) of inflatable bladder cuff is 12 x 23 cm (common). In thigh-18 x 24, obese – 12 x 35 cm. in infants width-3 cm children- width-8 cm. Cuff Placed 3 inches above the elbow Steth placed in the cubital fossa over the brachial artery. Usual position is supine lying down with arm supported to heart level. In sitting/ standing position arm should be horizontal at 4 th intercostal space of the sternum. If arm is not supported , arm with isometric contraction will elevate the diastolic Bp by 10%. In normal individual not much difference in Bp in standing , sitting or lying down. Bp in right arm is higher by up to 10 mm, if it is more than 10 mm , it should be analyzed carefully. Repeat inflation of cuff will raise the systolic &diastolic Bp & give false readings. so cuff should be inflated rapidly &deflated early & completely. Further readings are

Blood pressure • Phases in Bp measurement; • Phase I - Faint clear tapping sound which gradually increases in intensity • Phase II – softening of sounds • Phase III – return of sharp crisper sounds. • Phase IV – soft, blowing, mufling of sounds • Phase V - disappearance of sounds completely. • Phase I is systolic Bp , phase V is diastolic Bp.

Blood pressure • Normal Bp varies with age, mode of living, occupation, habits, emotional factors etc. . & time to time on the same day. • Normal in adults- 120/ 80 mmof Hg. • hypertension -Above 140/ 90 mm • hypotension- systolic Bp less than 90/60 diastolic • Malignant hypertension -Bp more than 200 mm • In shock Bp drops & reaches below 80/40 in adults • At birth- 55/35 mm. • Children nor – 90/ 60 mm of Hg • Adolescence- 105/65 mm of Hg

Blood pressure • Commonly Noting – brachial artery pressure • Femoral artery is in direct line with that of aorta so F. pressure is 10 mm of Hg higher than brachial. • In veins Bp lower – normal venous Bp is nearly 10 cm of water, in elbow it is 2 -10 mm • In capillaries between 20 -10 mm of hg • Ankle pressure is noted with knee semiflexed (45 degree)position & foot kept flat on the floor, placing the cuff around the calf with its lower edge is 2 -5 cm above the ankle(malleoli) ante. tibial & dorsalis pedes pulsation noted. Note both systolic & diastolic Bp noted. • Normally systolic Bp in the leg is 10 - 20% higher than the brachial Bp. • ABI- Highest of 2 ankle pressure/ highest of 2 brachial pressure(both). Normal value is >1. less than 0. 9 ischaemia, if less than 0. 3 critical ischaemia

Blood pressure Variations ; Physiological ; early morning- low, gradually increases & maximum at noon & low in evening. • Increase in few hrs. after meals. • Sleep- decrease up to 15 -20 mm during sleep& slight increase in sleep with dreams. • Exercise , anxiety increase- moderate exercise increase systolic Bp by 20 - 30 mm due to force of contraction/ stroke volume, not affect diastolic Bp because it depends on peripheral resistance.

Blood pressure Variations Pathological • High systolic with normal diastolic; - found in arterio-sclerosis of elderly person with diminished elasticity of vessels. • High systolic with low diastolic; - found in aortic regurgitation, thyrotoxicosis, severe anaemia. • Both systolic & diastolic high ; - found in essencial hypertension, renal ds, toxaemia of preg. , endocrine ds, coactation of aorta etc. . • Low systolic ; - myocardial insufficiency, infarction, malnutrition, cachexia, severe blood loss, burns, trauma, shock , heat stroke etc. . • High pulse pressure ; - hypertension, thyrotoxicosis, severe anaemia, PDA, regurgitations etc. . • Pulse pressure low; - cardiac dilatation, hypertension with decompensation, mitral & aortic stenosis, constrictive pericarditis.
Temperature • Normal body tempt. is a balance between heat gain & loss maintained by hypothalamus. • Tempt. of viscera & body tissues. • Degree / intensity of body heat measured by thermometer. • Axillary temp. is 1 F less than oral, Oral temp. is 1 F less than rectal. • Normal- 36. 7 -37. 5 degree C( 98 -99 F) – Av- 37 C/98. 6 F • Diurnal variation of 1 degree F(0. 5 C) is normal, not exceeds 1. 5 F • lowest in morning at 2 -4 am(mid night), • highest in afternoon(evening-6 pm). • Hypothermia- < 35 C/ 95 F • Hyperthermia- 101 - 104 F/ 38. 4 - 39. 9 C • Hyperpyrexia- > 40 - 41. 5 C/ 104 - 107 F • Fever- 37. 5 - 38. 3 C/ 100 - 101 F • Temp. raise of 1 F after 100 causes raise in pulse by 10, resp. rate by 4, BMR by 7, oxygen consumption by 13.

Temperature • fever –elevation of tempt. above the normal range due to increase in the body tempt. regulatory set point. Increase in set point triggers result in increased muscle tone& shivering. • Develop increase tempt. With activities but the set point is normal. • Fever can results from resetting of set point / from an abnormality in thermoregulatory system. • Grading of fever- mild- 99 - 100 F • moderate- 100 -103 F • High fever – 103 - 105 F

TEMPERATURE Fever Types; • Continuous; above normal through out the day and doesnot fluctuate more han 1 C in 24 hrs. • Remittent- tempt. Above normal throughout the day & fluctuates morethan 1 C in 24 hrs. • Intermittent- fever is present for only for certain hrs. of day and reaches to normal. Daily(24 hrs)- quotidian on alternate days(48 hrs)- tertian Every third day(72 hrs) – quartan • Pel ebstein fever – Tempt. high for 1 wk & low for next 1 wk. & so on. (febrile & afebrile periods in regular alternations) • Relapsing fever- febrile episodes are separated by normal temp. for more than 1 day. • PUO- Fever with temp. more than 101 F, morethan 3 wks of duration; failure to reach in to a diagnosis after 1 wk of inpatient investigation.

Systemic examination • Each system separately with, • Inspection(look)- Observing the diseased area carefully. • Palpation(feel) – done by feeling of affected part using hands and fingers. • Percussion(tap) – tapping the affected area directly using flexed finger or using pleximeter finger and percussion finger. • Auscultation (hear)- stethoscope is used to hear abnormal sounds.

Systemic examinations • • • Resp. CVS Abdominal Urogenital Musculoskeletal Endocrine Skin ENT Eye

Differential diagnosis • D/D is the distinguishing of a particular disease or condition from others that present similar clinical features. • List of possible conditions or diseases that causing pts. symptoms. • Most common possible diagnosis should be mentioned at first, then in descending order as per correlation of findings.

Investigations • • • Planned depending on clinical diagnosis Only relevant investigations are to be done. To confirm the diagnosis. Assess the severity of disease. To know the aetiology of disease. Plan & implement the treatment strategy To predict prognosis. Identify the associated illness As a preoperative preparation.

Investigations May be, • Non invasive – initial period of assessment. USG, Doppler, X-rays, ECG etc. . • Invasive - by means of invasive methods • Biopsy, endoscopies, IV contrast studies etc. .

Final Diagnosis • Identification/ determination of disease. • Based on proper investigations • For planning treatment.

Management&Treatment Management – general, accessory, medicinal, surgical Treatment • Medical attention given to a sick or injured person. • With regular follow up

Prognosis • Forecast of the probable outcome or course of a disease. • Predicting the likely or expected development of a disease. • Whether the signs and symptoms will improve or worsen or remain stable over

THANK YOU, DR. PANCHAJANI. R, Associate professor, Dept. of Surgery, SKHMC
- Slides: 79