
Case Presentation PK 1 12044099 Chief complaint O
















- Slides: 20
Case Presentation PK 1조 : : 12044099 조재완
Chief complaint 이O원 For colostomy repair M/7 mo Via OPD 2009. 02. 22
Past history 080715 via EM v Abd. Trans lat. : Initial anus imperforate • Foot X-ray : Lt. 배열이상, Rt – oligodactyly • Hand X-ray : Lt. polydactyly, Rt. Syndactyly • Abd U/S : – inf. Location of rectum – R/O fistula of urethara-rectum – Kidney, bladder normal config. • Spine U/S : thickened filum terminale • Chromosome analysis : normal karyote • PS consult : polydactyly, oligodactyly, F/U after 1 yr 6 mo OP 080716 : colostomy, loop sigmoid
081125 via OPD v Anal atresia & stenosis with recto-urethral fistula • VCUG : vesicourethral reflux both (Rt. II, Lt. IV) • Distal colostomy : imperforated anus with recto-periurethral fistula OP : 081127 : Pena OP
Family & Society histoy • FHx : none • Vaccination Hx – DTPx 3, 소아마비x 3, 간염백신x 3, MMR, BCG
Physical exam • V/S – HR : 124 – RR : 48 – BT : 36. 8 • Height : 76 cm (75%) • Weight : 9. 5 kg (75%)
Diagnosis Anal atresia & stenosis with recto-urethral fistula S/P colostomy (080716) S/P Pena OP (081127)
Plan Colostomy repair OP day : 090223 OP name : Colostomy repair
Progress note [POD #0] • Subject : 열이 나요. • Object : – – HR : 154 회/분 RR : 42 회/분 BT : 38. 8℃ I/O : 1000/1033 (L-tube 0) • Assessment : – Anal atresia & stenosis with recto-urethral fistula – S/P 3 stage OP – R/O Transfusional reacation – R/O Pul. atelecasis • Plan : Chest percussion, CXR, Suspen sup.
Progress note [POD #1] • Subject : 방귀 뀌었고 변도 봤어요. 자꾸 보채요. • Object : – – – HR : 138 회/분 RR : 40 회/분 BT : 38℃ I/O : 1300/1034 (L-tube 8 brownish color) Gas out : + Defication : 1회 • Assessment : – Anal atresia & stenosis with recto-urethral fistula – S/P 3 stage OP • Plan : Pechidine, CXR
Progress note [POD #2] • Subject : 많이 좋아졌어요. • Object : – – – HR : 120 회/분 RR : 40 회/분 BT : 37℃ I/O : 1200/990 (L-tube 0) Defication : 3회 • Assessment : – Anal atresia & stenosis with recto-urethral fistula – S/P 3 stage OP • Plan : PD & UR Follow up, L-tube remove
Book review Anorectal malformation
Epidemiology • Incidence : 1 in 4000~5000 birth • Male : Female = 56 : 44 • Associated syndrome – VATER or VACTERL syndrome (Vertebral, Anal, Cardiac, Tracheo-esophageal, Renal and Limb anomaly) – – – Townes-Brocks syndrome Currarino triad FG syndrome Cat-eye syndrome Lowe syndrome
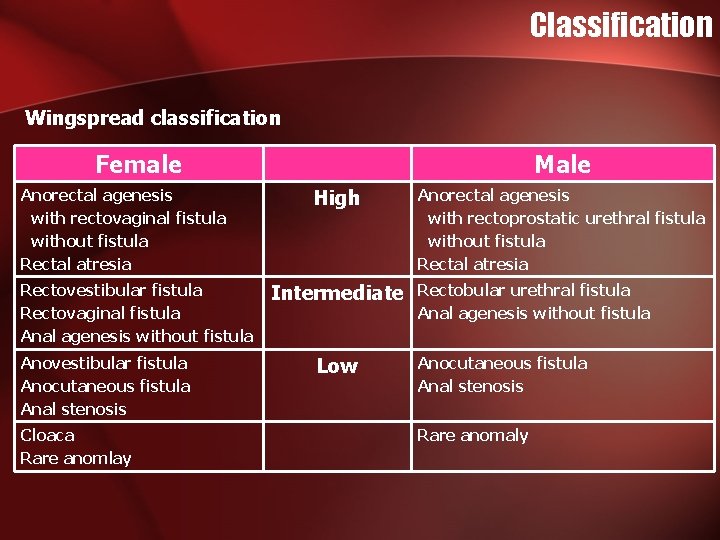
Classification Wingspread classification Female Anorectal agenesis with rectovaginal fistula without fistula Rectal atresia Rectovestibular fistula Rectovaginal fistula Anal agenesis without fistula Anovestibular fistula Anocutaneous fistula Anal stenosis Cloaca Rare anomlay Male High Intermediate Low Anorectal agenesis with rectoprostatic urethral fistula without fistula Rectal atresia Rectobular urethral fistula Anal agenesis without fistula Anocutaneous fistula Anal stenosis Rare anomaly
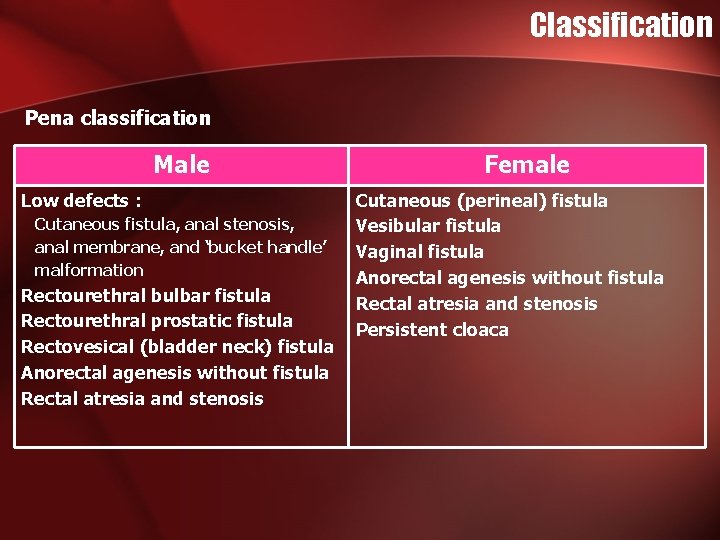
Classification Pena classification Male Low defects : Cutaneous fistula, anal stenosis, anal membrane, and ‘bucket handle’ malformation Rectourethral bulbar fistula Rectourethral prostatic fistula Rectovesical (bladder neck) fistula Anorectal agenesis without fistula Rectal atresia and stenosis Female Cutaneous (perineal) fistula Vesibular fistula Vaginal fistula Anorectal agenesis without fistula Rectal atresia and stenosis Persistent cloaca
Diagnosis • Anatomy – Location of anorectum – Location of fistula • Another anomaly • • • Wangensteen invertogram Cross-table lateral x-ray Urine anlalysis Chest X-ray Abdominal & Pelvic U/S VCUG Distal loopogram or dital colostogram CT & MRI
Treatment v Usually requires immediate surgery to open a passage for faeces • M/ Low anomaly (at birth) – Cut-back anoplasty • F/ Low anomaly (after 2~3 mo) – Cut-back anoplasty or Jump-back anoplasty • Intermediate & High anomaly 1. At birth : Colostomy 2. 3~6 mo : Posterior sagittal anorectoplasty, Pena OP 3. After 2~3 mo from Pena OP : Colostomy repair
Prognosis • With a high lesion – Uncontrolling bowel function – Constipation • With a low lesion – Good bowel control – Constipation • Poor outcome for continence and constipation – Further surgery - Angle between the anus and the rectum Remove that dilated segment • Malone stoma – An antegrade enema for appendix to the skin