
Case based discussion Pankaj Malhotra PGIMER Chandigarh India

Case based discussion Pankaj Malhotra PGIMER, Chandigarh, India
Case History • A 43 -year old gentleman presented with weakness and fatigability x 3 months • Hb 13. 4 gm/dl, WBC 220, 000 cells/mm 3, Plat 679000 cells/mm 3 • Spleen 10 cm • BM: Hypercellular, 8% blasts, Ph 20/20 positive, Q RT PCR for BCR ABL m. RNA 80% • Sokal High-risk
Case History • A 43 -year old gentleman presented with weakness and fatigability x 3 months • Hb 13. 4 gm/dl, WBC 220, 000 cells/mm 3, Plat 679000 cells/mm 3 • Spleen 10 cm • BM: Hypercellular, 8% blasts, Ph 20/20 positive, Q RT PCR for BCR ABL m. RNA 80% • Sokal High-risk • Availability of Imatinib/Dasatinib/Nilotinib

Choice of first line therapy Feb 2013 1. 2. 3. 4. 5. 6. Imatinib 400 mg OD Imatinib 800 mg OD Dasatinib 100 mg OD Nilotinib 300 mg BD Nilotinib 400 mg BD Bosutinib 500 mg OD Would Sokal high-risk score have impact on the choice of first line therapy?
Choice of first line therapy Feb 2013 1. 2. 3. 4. 5. 6. Imatinib 400 mg OD Imatinib 800 mg OD Dasatinib 100 mg OD Nilotinib 300 mg BD Nilotinib 400 mg BD Bosutinib 500 mg OD Does enough finances/insurance coverage impact on choice of first line therapy
Case History • A 43 -year old gentleman presented with weakness and fatigability x 3 months • Hb 13. 4 gm/dl, WBC 220, 000 cells/mm 3, Plat 679000 cells/mm 3 • Spleen 10 cm • BM: Hypercellular, 8% blasts, Ph 20/20 positive, Q RT PCR for BCR ABL m. RNA 80% • Sokal High-risk • Active coronary artery disease and AF

Choice of first line therapy Feb 2013 1. 2. 3. 4. 5. 6. Imatinib 400 mg OD Imatinib 800 mg OD Dasatinib 100 mg OD Nilotinib 300 mg BD Nilotinib 400 mg BD Bosutinib 500 mg OD Would active coronary artery disease & AF impacts your decision making?
Case History • A 43 -year old gentleman presented with weakness and fatigability x 3 months • Hb 13. 4 gm/dl, WBC 220, 000 cells/mm 3, Plat 679000 cells/mm 3 • Spleen 10 cm • BM: Hypercellular, 8% blasts, Ph 20/20 positive, Q RT PCR for BCR ABL m. RNA 80% • Sokal High-risk • Past history of pulmonary tuberculosis
Choice of first line therapy Feb 2013 1. 2. 3. 4. 5. 6. Imatinib 400 mg OD Imatinib 800 mg OD Dasatinib 100 mg OD Nilotinib 300 mg BD Nilotinib 400 mg BD Bosutinib 500 mg OD Would a past history of lung infection impacts your decision making?

Choice of first line therapy depends upon 1. 2. 3. 4. 5. Available finances/Full insurance Side effect profile of the drugs Co-morbid conditions of the patient Phase of the disease(Acc or BC) Sokal score (? )
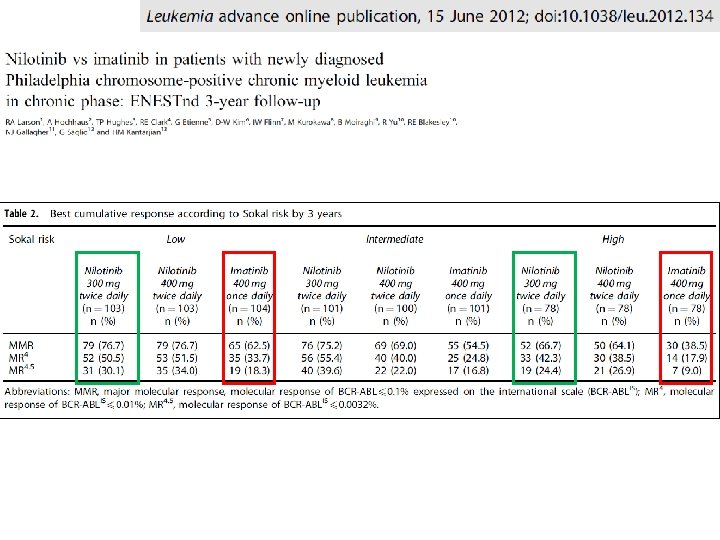

Choice of first line therapy depends upon 1. 2. 3. 4. 5. 6. Available finances/Full insurance Side effect profile of the drugs Co-morbid conditions of the patient Phase of the disease(Acc or BC) Sokal score (? ) Physician preference/Patient preference (? )
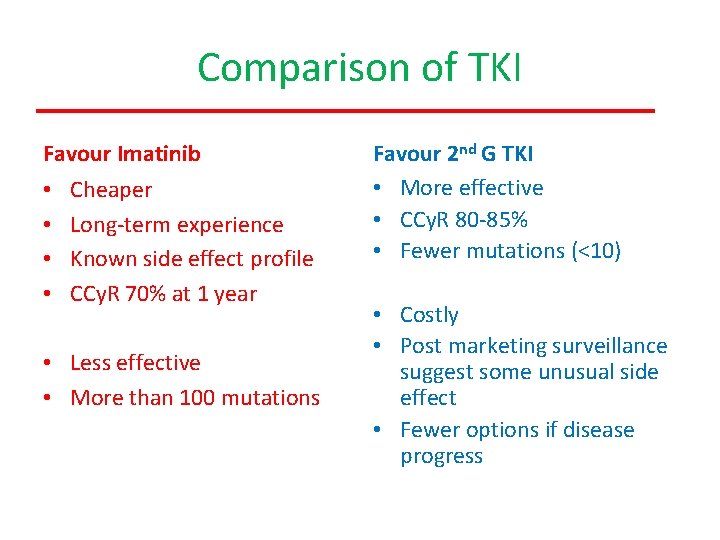
Comparison of TKI Favour Imatinib • • Cheaper Long-term experience Known side effect profile CCy. R 70% at 1 year • Less effective • More than 100 mutations Favour 2 nd G TKI • More effective • CCy. R 80 -85% • Fewer mutations (<10) • Costly • Post marketing surveillance suggest some unusual side effect • Fewer options if disease progress


The patient was started on Imatinib 400 mg/day
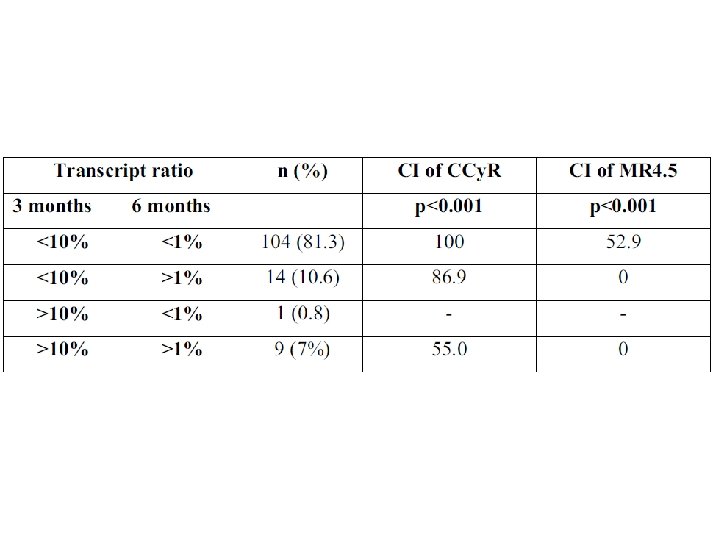
Progress • Achieved CHR by 2 months • RQ PCR for BCR-ABL at 3 months 22% IS What are the long-term chances of PFS of this gentleman? ( RQ PCR >10% at 3 months)? 1. High 2. Low
Progress • Achieved CHR by 2 months • RQ PCR for BCR-ABL at 3 months 12% IS What are the long-term chances of PFS of this gentleman? ( RQ PCR >10% at 3 months)? 1. High 2. Low



The patient was started on Dasatinib 100 mg/day
Progress • Achieved CHR by 2 months • RQ PCR for BCR-ABL at 3 months 12% IS What are the long-term chances of PFS of this gentleman? ( RQ PCR >10% at 3 months)? 1. High 2. Low

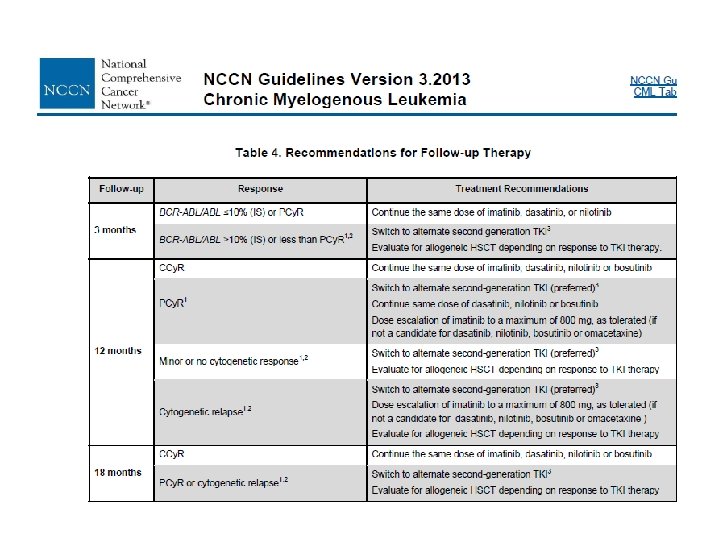


Thus with 2 nd G TKI, you expect more rapid response, may be CCy. R at 3 months/BCR ABL <2% at 3 months


Assessment at 6 -months • Glivec 400 mg/day continued • Hb 10. 0 gm/dl MCV 102 WBC 3500 cells/mm 3 Plat 100, 000 cells/mm 3 • BM: Mild hypocellular • Cytogenetics 2/20 = MCy. R • Q PCR 1% IS What is your assessment and would you consider change in your strategy?


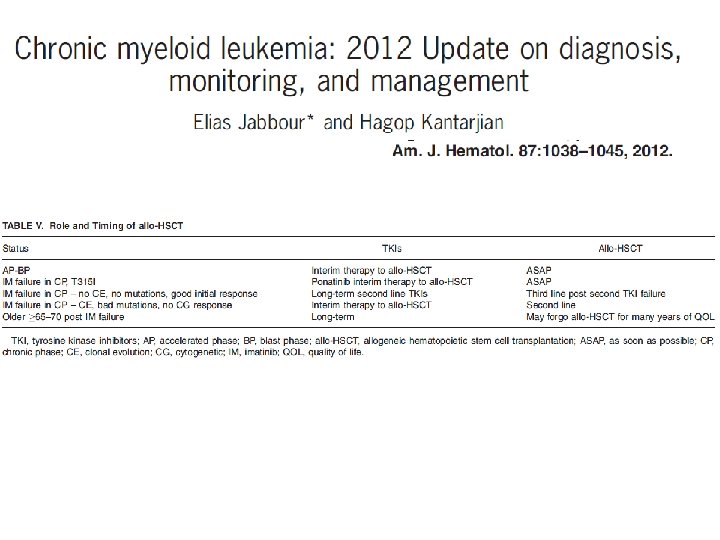
Current role of Allo HSCT

Conclusions • Rapid advancement taking place in the field of CML • Availability of many drugs have made life easy as well as difficult both for the physician as well as the patient • Need to continue update our knowledge on CML on the basis of continuously emerging data
- Slides: 33