
CASE 8 MADE BY REHAM TALAL KHALIL ASMAA

CASE 8 : MADE BY: REHAM TALAL KHALIL ASMAA MOHAMED ALGHEFARI


• a 64 -y. o o comes to your office of pain in the chest & coughing you ordered a roentgenogram showed a “mass” in the mediastinum. an excisional biopsy was performed diffuse large b-cell lymphoma on farther investigation multiple inguinal & iliac lymphadenopathy
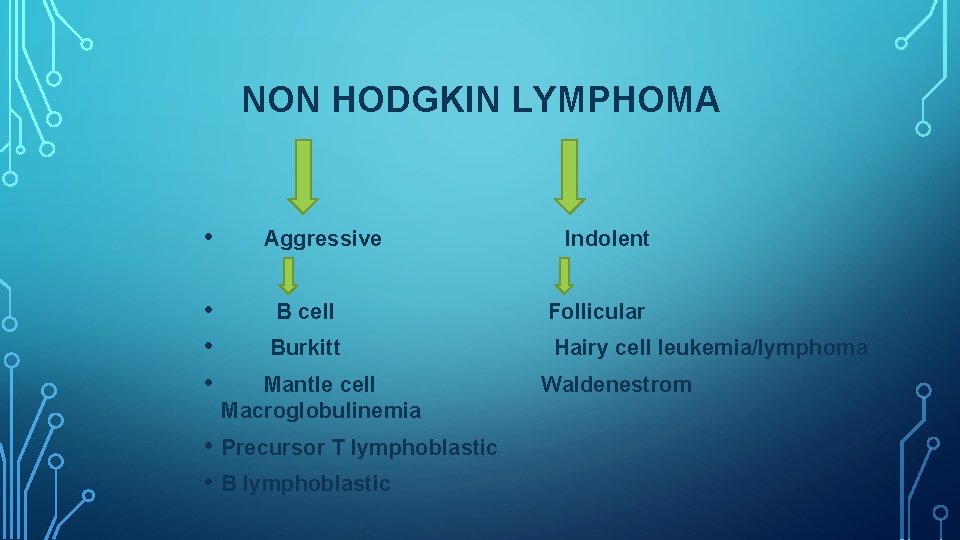
NON HODGKIN LYMPHOMA • Aggressive Indolent • B cell Follicular • Burkitt Hairy cell leukemia/lymphoma • Mantle cell Waldenestrom Macroglobulinemia • Precursor T lymphoblastic • B lymphoblastic

* Aggressive Can Be Trait By Chemotherapy * Non Aggressive Can Be Trait By Observe (Watch, Wait).

- B cell lymphoma The most common aggressive lymphoma - Could Be: * De novo * From abreviously indolent lymphoma Some are Associated EBV - Can be nodel and extranodel - Median age 65 Y. O

When CLL becomes DLBCL Richter syndrome due to rapid cell turnover in DLBCL can have tumor lysis syndrome high ka , ureic acid in the blood but, low ca, LDH usually high.

How diagnose LDBCL - excisional biopsy the architecture of the node and cell appearance - CBC and blood chemistry (LDH) will be high uric acid will BE high > high grade NHL - HIV testing - staging physical exam and CT scan -pet scan. help diagnose and follow up - if use immunobiological stain. cd 20

THANK YOU
- Slides: 9