
CARCINOMA OESOPHAGUS DR B Ramdas Rai Prof Unit

CARCINOMA OESOPHAGUS DR. B. Ramdas Rai Prof. & Unit Chief YMCH
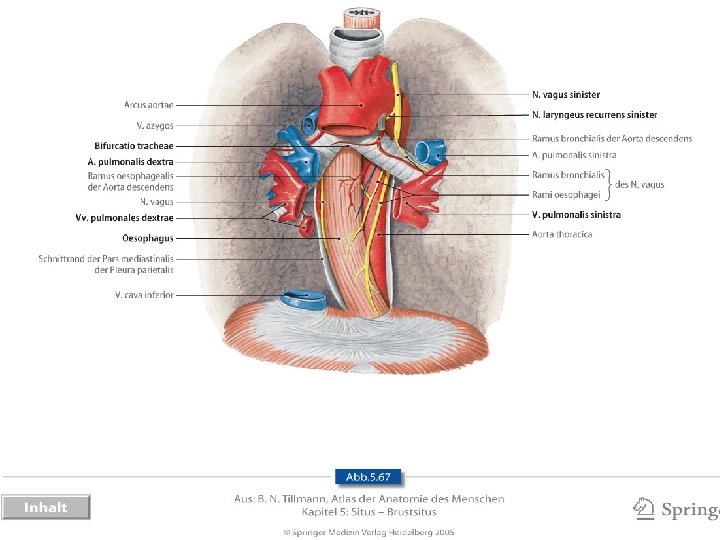

ETIOLOGY…. Alcohol Tobacco Nitrosamines Malnutrition Vitamin deficiency(A, C, Riboflavin) Anaemia Poor oral hygiene Ingestion of hot foods and Beverages

Premalignant conditions… Achalasia Cardia Oesophageal webs Corrosive strictures Reflux esophagitis Hiatus hernia Barrett’s esophagus

Plummer-Vinson syndrome Leukoplakia Esophageal diverticula Ectopic gastric mucosa Familial ---Tylosis keratosis palmaris & plantaris

Clinical Featrures. . . Male to female ratio is 3: 1 Age: - 6 th or 7 th decade of life. Recurrent onset of dysphagia is the commonest feature. For the dysphagiato develop, 2/3 rd of the lumen should be occluded. Regurgitation Anorexia & loss of weight(severe), cachexia

Contd. . Pain-substernal or in the abdomen Liver secondaries, ascites Bronchopneumonia, malena Features of broncho-oesophageal fistula in Ca of upper third of oesophagus Left supraclavicular lymph nodes may be palpable

Contd Hiccough due to phrenic nerve invovement Hoarseness of voice due to involvement of RLN Back pain – due to nodal spread (paraoesophageal/coeliac nodes)

PATHOLOGY Squamous cell carcinoma— 95% Adenocarcinoma— 2. 5 -5%
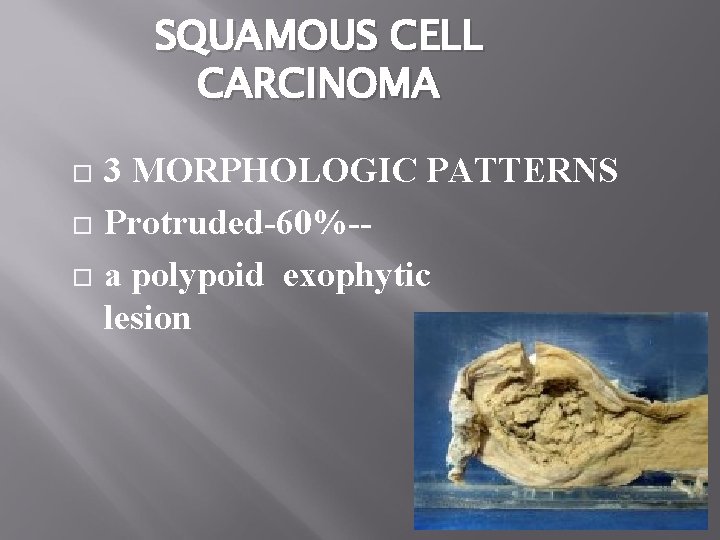
SQUAMOUS CELL CARCINOMA 3 MORPHOLOGIC PATTERNS Protruded-60%-a polypoid exophytic lesion

Flat-15% *diffuse infiltrative form *spread within wall of esophagus *thickening, rigidity, narrowing of lumen
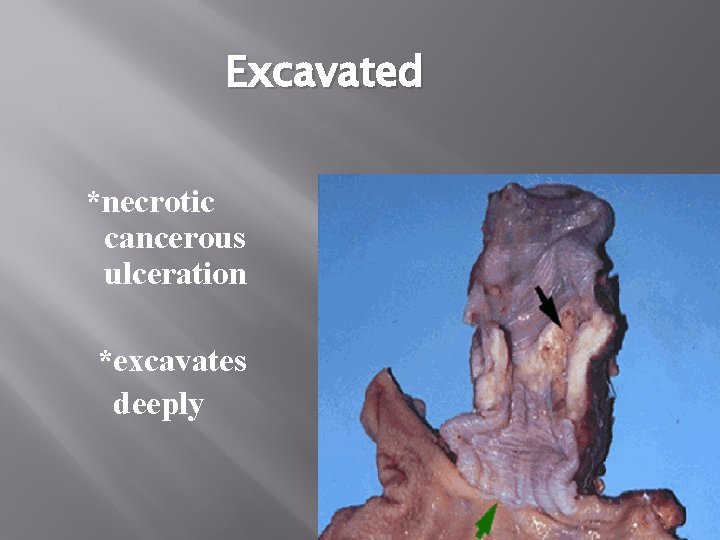
Excavated *necrotic cancerous ulceration *excavates deeply
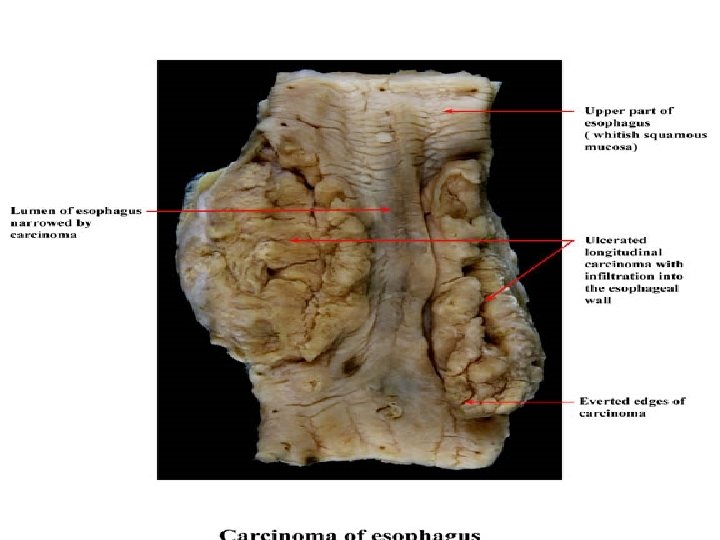

MOST ARE MODERATE TO WELL DIFFERENTIATED 50% in middle 1/3… 30% in lower 1/3 20% in upper 1/3

ADENOCARCINOMA Increasing in frequency Distal 1/3 Male : female = 3: 1 Origin---1)Barrett mucosa 2)Esophageal submucosal glands 3)Heterotropic islands of columnar epithelium
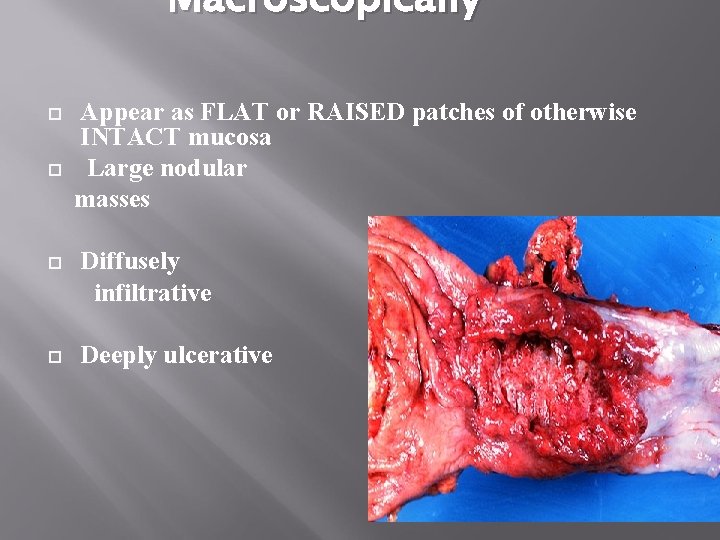
Macroscopically Appear as FLAT or RAISED patches of otherwise INTACT mucosa Large nodular masses Diffusely infiltrative Deeply ulcerative

Microscopy: : Mucin-producing glandular. Showing intestinal type feat. Diffusely infiltrative signet-ring cells of gastric type
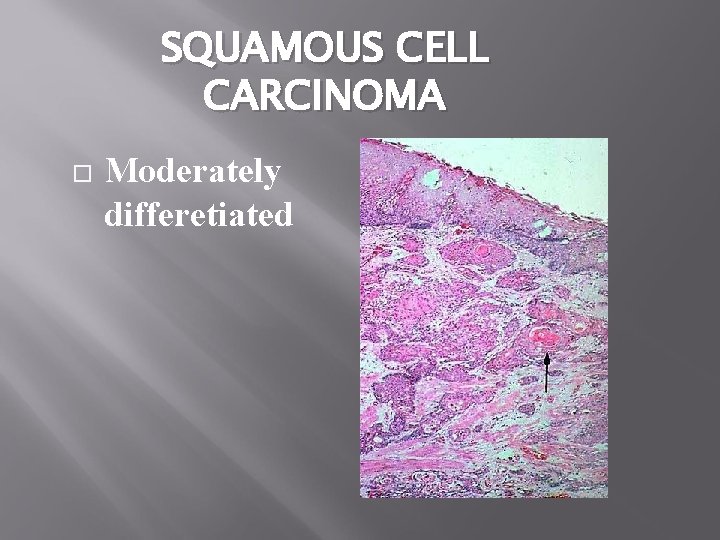
SQUAMOUS CELL CARCINOMA Moderately differetiated
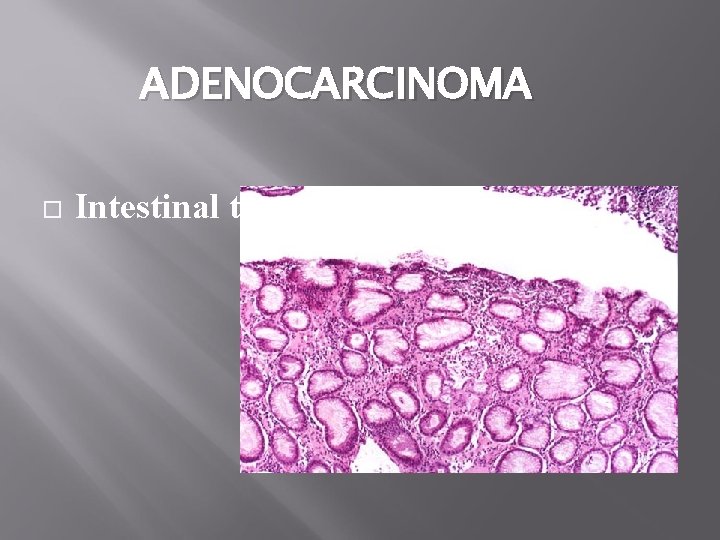
ADENOCARCINOMA Intestinal type

SPREAD Locoregional Upper 1/3 and middle 1/3 --tracheobronchial tree , aorta , left RLN Lower 1/3 ---diaphragm, pericardium , stomach

LYMPHATICS CERVICAL deep cervical paraesophageal posterior mediastinal tracheobronchial LOWER paraesophageal coeliac splenic hilar

Distant spread Liver Lungs

INVESTIGATIONS Barium swallow Chest X-ray Esophagoscopy with biopsy and brushings CT chest and abdomen Bronchoscopy

Additional… MRI Bone and brain scan Staging mediastinoscopy if specific symptoms or findings…. .
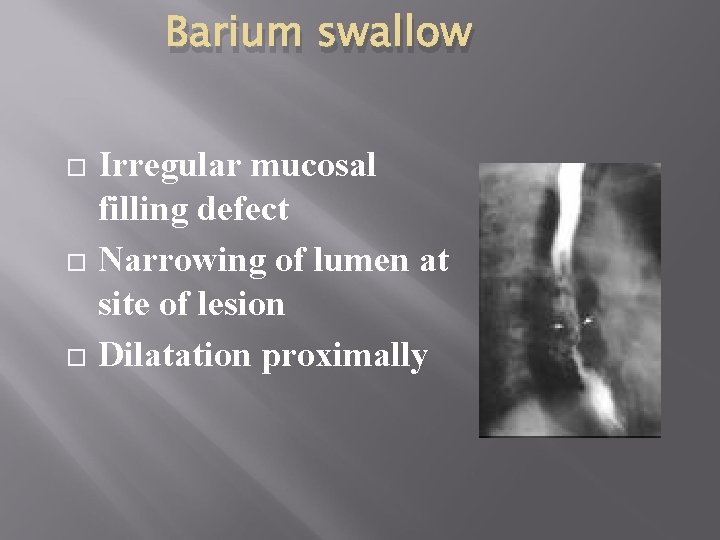
Barium swallow Irregular mucosal filling defect Narrowing of lumen at site of lesion Dilatation proximally
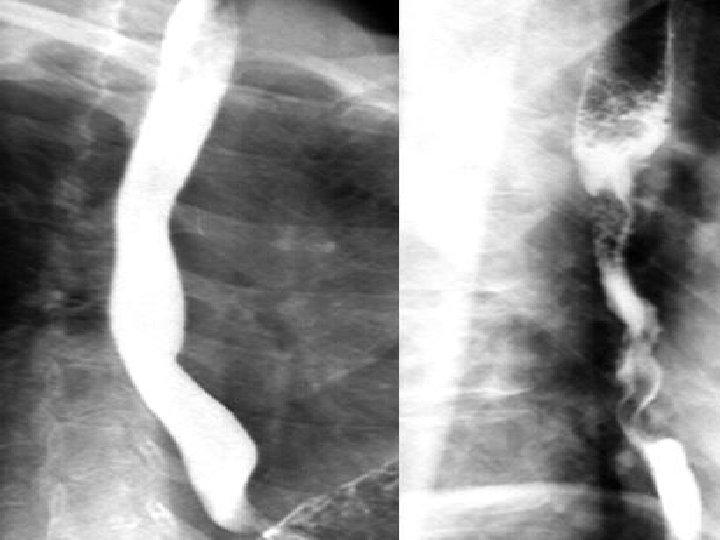

Upper border resembling shelf Annular lesion—narrowed lumen irregular mucosal outline Angulation of axis of tumor above and below tumor---spread to extraesophageal sites
CHEST X-RAYS Air-fluid level in the obstructed esophagus in the postr. Mediastinum Dilated esophagus Abnormal mediastinal soft tissue— adenopathy

Pleural effusion Pneumonitis Lung abscess Pulmonary metastasis CAN BE NORMAL EVEN IN ADVANCED DISEASE
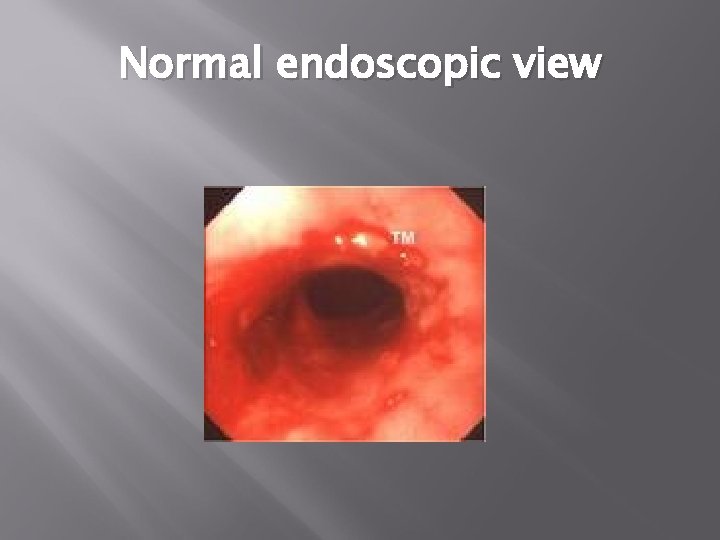
Normal endoscopic view
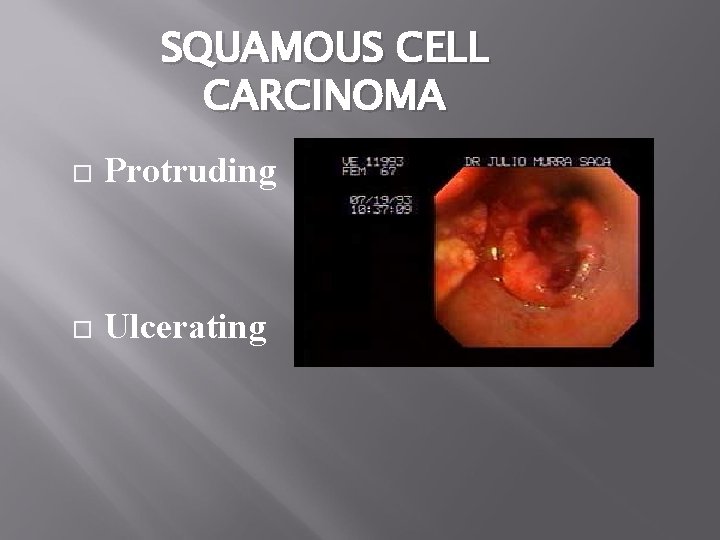
SQUAMOUS CELL CARCINOMA Protruding Ulcerating
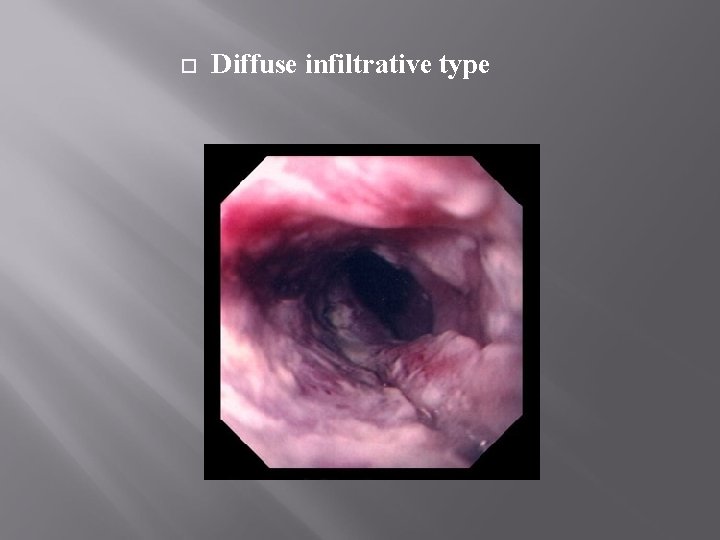
Diffuse infiltrative type
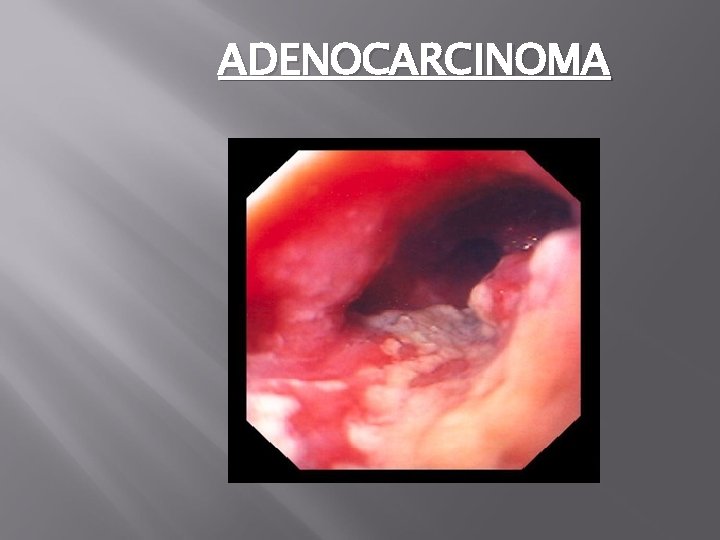
ADENOCARCINOMA
CT CHEST AND UPPER ABDOMEN Usually used for staging of the disease Wall thickness (5 mm) Direct mediastinal invasion by tumor Regional lymphadenopathy

Metastasis –lung liver adrenal and distant nodes ESOPHAGEAL ENDOSONOGRAPHY To determine wall penetration and mediastinal invasion—more accurate

BRONCHOSCOPY Upper and mid esophagus may invade tracheobronchial tree Positive findings *distortion of bronchial lumen *blunting of carina *intra –bronchial tumor
TNM STAGING Done using CT DIVIDES ESOPHAGUS INTO 4 SECTIONS 1)CERV ICAL-15 -18 cm. lower border of cricoid cartilage to thoracic inlet 2)UPPER THORACIC— 24 cm. inlet to carina thoracic

Contd…. …. 3)MIDDLE THORACIC— 32 cm. carina to ½ the distance to the esophagogastric junction 4)LOWER THORACIC— 40 cm. to the esophagogastric junction REGIONAL LYMPH NODES CERVICAL --cervical and supraclavicular nodes

THORACIC --mediastinal and perigastric LN along lesser curvature , fundus, left gastric artery

PRIMARY TUMOR (T) TX---- can not be assessed T 0 ---no evidence of primary tumor Tis---high-grade dysplasia T 1 ---invades lamina propria (T 1 a) muscularis mucosa(T 1 a) submucosa(T 1 b) Does not breach submucosa

T 2 ---invades muscularis propria T 3 ---invades periesophageal tissues T 4 ---invades adjacent structures
REGIONAL LYMPH NODES (N) Nx ---regional nodes cannot be assessed N 0 ---no regional node metastases N 1 ---regional node metastases

DISTANT METASTASIS (M) Mx ---mets cannot be assessed M 0 ---no distant metastases M 1 a ---non-regional lymph node metastases M 1 b ---other distant metastases

STAGING Stage 0 ---Tis N 0 M 0 Stage l--- T 1 N 0 M 0 Stage lla--T 2 N 0 M 0 T 3 N 0 M 0 Stage llb—T 1 N 1 M 0 T 2 N 1 M 0

Stage lll –T 3 N 1 M 0 T 4 any N M 0 Stage l. Va –any T any N M 1 l. Vb –any T any N M 1 b

DIFFERENTIAL DIAGNOSIS Benign strictures Benign papillomas Polyps Granulomatous masses

TREATMENT Surgery Radiotherapy Chemotherapy Combination

UNRESECTABILITY Direct spread to tracheobronchial tree or aorta Esophageal fistula Hoarseness of voice Primary tumor >10 cm.

CHEMOTHERAPY Combination chemo: Cisplatin, bleomycin, vindesine or methotrexate

Cisplatin, mitoguazone, vindesi ne or vinblastine Cisplatin, 5 -fluorouracil

Used for metastatic and unresectable esophageal ca 11% to 55%for 3 -9 months Doesn’t cure the disease Best responses with squamous cell carcinoma

RADIOTHERAPY Squamous cell ca is radiosensitive 3 objectives: 1. Palliation 2. Cure 3. An adjunct to esophagectomy 5 -year survival rate— 3%-9%

Cause 1. local tumor not controlled 2. stricture formation 3. continued progression of tumor outside field of irradiation

TREATMENT OPTIONS Intramucosal (T 1 a)cancers Surgery alone – Transhiatal esophagectomy T 1 b N 0 M 0 and T 2 N 0 M 0 esophagectomy with thoracotomy

*Clinically N 0 and found to have LN metastases at surgery— post operative adjuvant therapy *T 3 or N 1 or M 1 a induction therapy followed by surgery *Stage 4 - palliative usually nonoperative
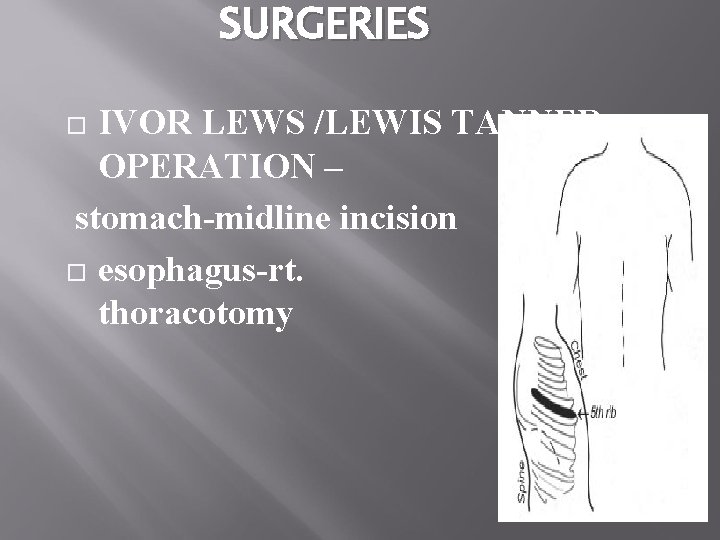
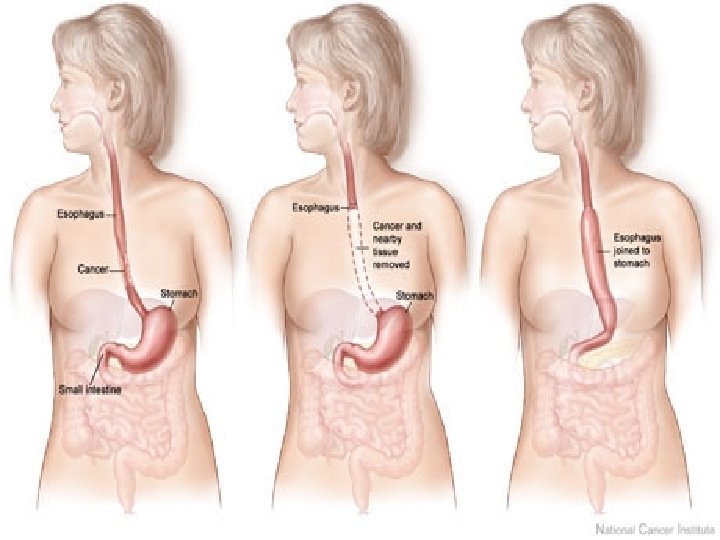
SURGERIES IVOR LEWS /LEWIS TANNER OPERATION – stomach-midline incision esophagus-rt. thoracotomy
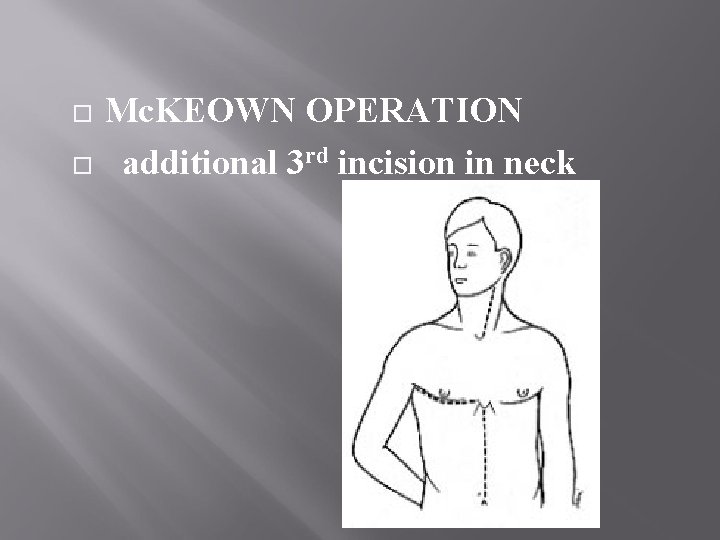
Mc. KEOWN OPERATION additional 3 rd incision in neck
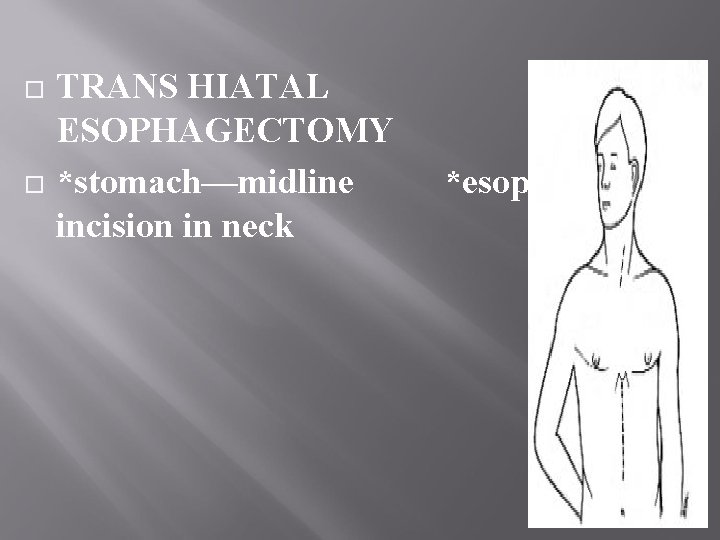
TRANS HIATAL ESOPHAGECTOMY *stomach—midline incision in neck *esophagus-

3 FIELD LYMPH NODE DISSECTION – extensive removal of regional lymph nodes in – abdomen, chest, neck
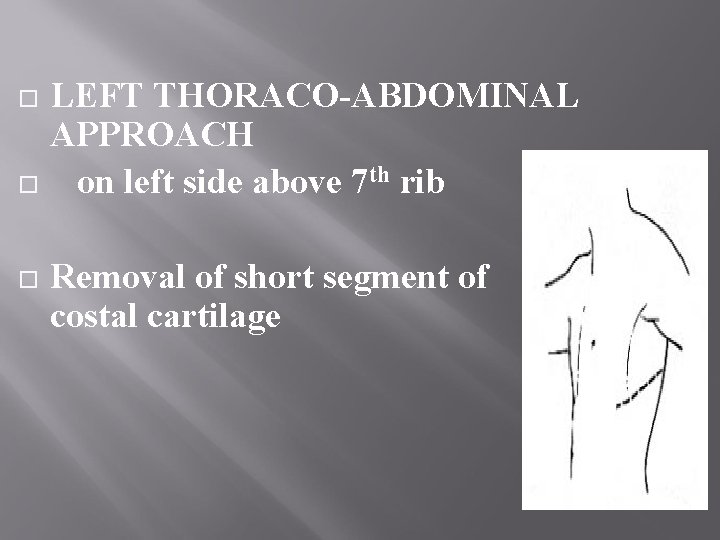
LEFT THORACO-ABDOMINAL APPROACH on left side above 7 th rib Removal of short segment of costal cartilage
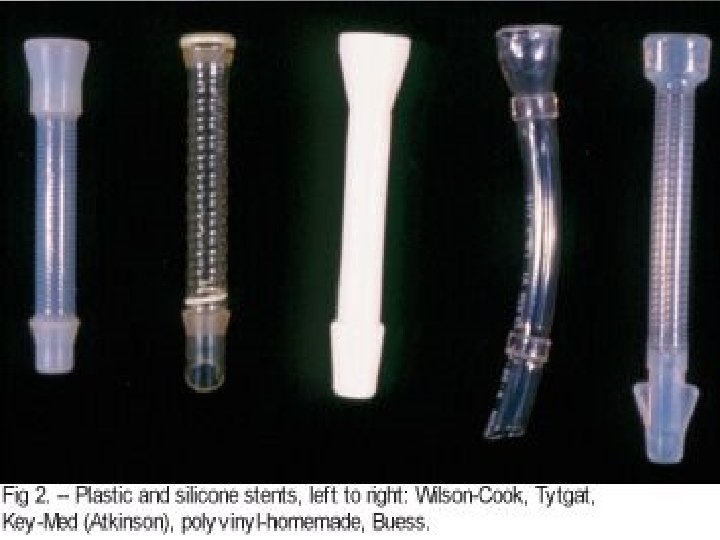
PALLIATIVE TREATMENT INTUBATION *celestine tube *souttar tube *atkinson tube *Procter-Livingston tube 2 TYPES pulsion – passed from above traction –pulled into place
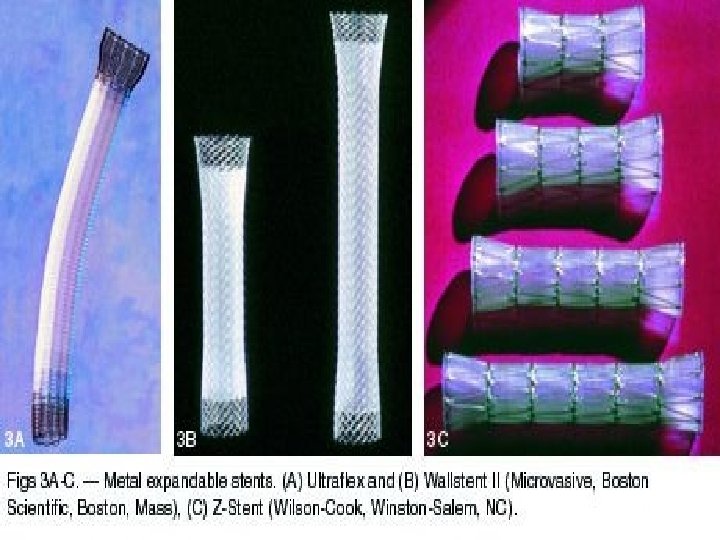
METAL EXPANDABLE STENTS

ENDOSCOPIC LASER BRACHYTHERAPY OTHERS bipolar diathermy argon-beam plasma coagulation alcohol injection

COMPLICATION OF SURGERY INTRAOPERATIVE: bleeding tracheobronchial injury hydropneumothorax RLN palsy

POSTOPERATIVE: * anastomotic leaks * respiratory complications * chylothorax * anastomotic strictures * gastro esophageal reflux

- Slides: 68