
Bioidentical SexSteroid Restoration For Women Henry Lindner MD

Bioidentical Sex-Steroid Restoration For Women Henry Lindner, MD Hormonerestoration. com

Topics If time: Hormones and Aging Bioidentical vs. Pharmaceutical Estradiol/Progesterone Complementarity Breast Cancer Osteoporosis Atherosclerosis and Clotting The Problems with Hormone Substitutes The Information War Pharmacy Compounding
Main Points Estradiol replacement is medically necessary. Estradiol replacement is safe when accompanied by sufficient progesterone. Testosterone and DHEA should be restored to youthful levels. Problems caused by hormone substitutes have not been seen with transdermal bioidenticals.
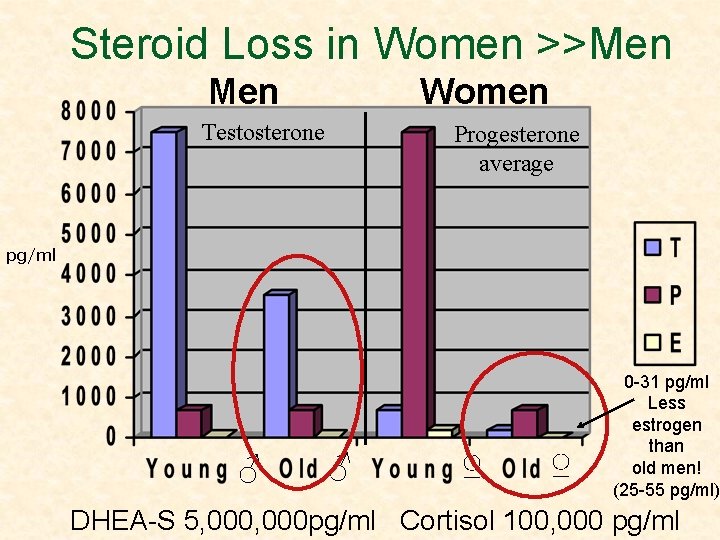
Steroid Loss in Women >>Men Women Testosterone Progesterone average pg/ml ♂ ♂ ♀ ♀ 0 -31 pg/ml Less estrogen than old men! (25 -55 pg/ml) DHEA-S 5, 000 pg/ml Cortisol 100, 000 pg/ml

Hormone Loss with Age Common Assumption: Youthful levels good for hunting, fighting and reproduction but cause heart attacks and cancer later. Hormone loss with age is adaptive— lengthens our lives. But: sex-organ cancers, heart attacks, osteoporosis occur years after hormone levels start to decline! And: these diseases occur more often

So Why do we Lose our Hormones? We are genetically programmed to die. Nature kills us, deterioration starts at age 25! Aging is dying; the universal “underlying disease”. Hormone loss is caused by and contributes to other mechanisms of aging. Age-related hormone loss both natural and deleterious. The symptoms of menopause are warning

The Solution: Hormone Restoration If a hormone is missing, replace it! If present but insufficient, optimize it! Optimal levels improve both health and quality of life Bioidentical=correct chemical structure Bioidentical=Standard of Care: insulin, T 4, growth hormone, cortisol, oxytocin, HCG, etc.

Bioidentical Hormones are not Drugs Non-toxic, inherently safe No allergic or idiosyncratic reactions No “side effects”, only effects! Proper fit in receptors, elimination Monitor dose with normal blood tests! (not so with Premarin , Provera , prednisone, etc. ) Potential problems with bioidenticals: Excessive dose Lack of balance with other hormones

Not Just “Sex Hormones” Estradiol, progesterone, testosterone and DHEA required for the function, growth, and maintenance, of all tissues in both sexes! Maintain brain function and health— modulators of mood, cognition, memory, pain, etc. Maintain the immune system—progesterone and testosterone are immunosuppressants Maintain connective tissue: skin, hair, bone, muscle Improve insulin sensitivity Reduce blood pressure—improve endothelial function

The Female Burden of Reproduction Female organs and cyclic hormonal system exist for reproduction, not for the woman’s health! Breast, uterine and ovarian tissues undergo a monthly cycle of proliferation, differentiation, and breakdown Defects in this cycle can lead to cancers in female organs and to many medical disorders.

Historical Perspective Throughout history, women were usually pregnant or breast feeding. Only 4 years of cycling on average Today, women may experience 35 years of cycling Much greater risk of progesterone deficiency and other hormonal disorders

Estradiol Angel of Life—stimulates growth of female organs necessary for reproduction; maintains female health and quality of life Angel of Death—promotes cancer and other medical disorders– if not balanced with progesterone androgens

Estradiol-Progesterone Complementarity Estradiol promotes uterine and breast tissue proliferation and growth Progesterone stops proliferation and promotes maturation and differentiation. Progesterone withdrawal sloughing and necrosis of uterine lining and breast duct epithelium. Jun; 10(6): 382 -93 Longacre TA, Am J Surg Pathol. 1986 High persistent progesterone/estradiol ratio suppresses proliferation and prevents cancers. Inadequate progesterone=estrogen

Progesterone’s Anti-Estrogenic Actions in Uterus and Breast Decreases synthesis of estradiol receptors Increases conversion of estradiol to estrone (weak estrogen) by inducing 17βhydroxysteroid dehydrogenase Type 2 Reduces conversion of estrone to estradiol by inhibiting 17β-hydroxysteroid dehydrogenase Type 1 Increases sulfation (inactivation) of estrogens Williams Text. of Endocrinology, 10 th Ed. , p. 612
Postmenopausal Breast tissue produces estradiol from adrenal androgens (DHEA, androstenedione) Compared to the premenopausal breast, postmenopausal breast nipple aspirate fluid has: Same estradiol concentration Much lower progesterone concentration Chatterton RT Clin Endocrinol Metab. 2005 Mar; 90(3): 1686 -91 Postmenopausal breast is in state of estrogen dominance ’d risk of cancer.

Perimenopause and Progesterone Deficiency With aging, fewer oocytes of lower quality are left Reduced progesterone production beginning as early as age 30 estrogen dominance Luteal phase insufficiency estrogen dominance Anovulation estrogen dominance

Estrogen Dominance Allergies Autoimmune diseases Anxiety, irritability Insomnia Depression Bloating and edema Fibrocystic breasts Uterine fibroids Breast cancer Ovarian cancer Uterine cancer Thyroid dysfunction Gallbladder disease Menorrhagia Migraines Seizures Progesterone restoration is the only effective treatment.

Menopause—Estradiol Deficiency Irritability, insomnia, depression Poor memory, ’d risk of Alzheimer’s dementia Fatigue, aches and pains Osteoporosis fractures, loss of teeth Genital atrophy, vaginal dryness Atrophy of skin and connective tissue Endothelial dysfunction, in blood pressure Atherosclerotic heart disease Surgical menopause 2 -7 x risk of heart attacks, earlier age at surgery greater risk 30; 316(18): 1105 -10 Jan; 139(1): 47 -51. Colditz GA, Engl J Med 1987 Apr Rosenberg L, Am J Obstet Gynecol. 1981

Women Killers and Hormones Cardiovascular disease (CVD), breast cancer and osteoporosis are rare in premenopausal women All related to hormone deficiency/imbalance Youthful/healthy hormonal milieu is protective. Breast cancer rise begins in perimenopause with decreasing progesterone production. After menopause, women’s rate of CVD rises faster than men’s! Higher risk than men after 65, and higher mortality after 70!
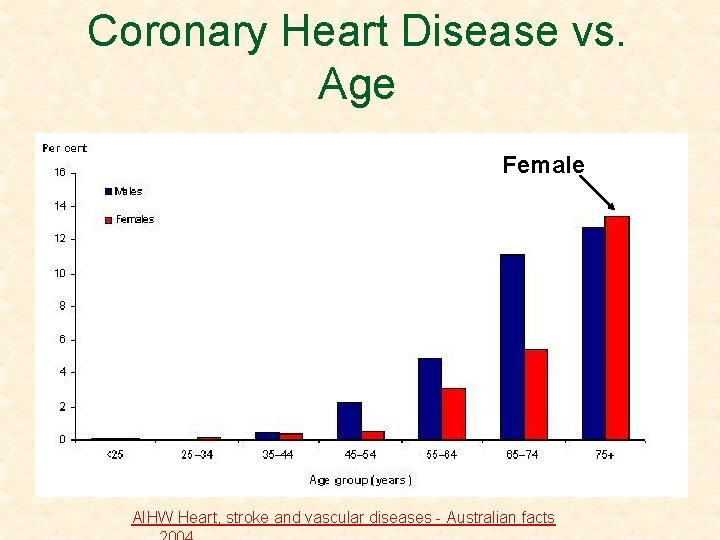
Coronary Heart Disease vs. Age Female AIHW Heart, stroke and vascular diseases - Australian facts
Estrogen Replacement and CAD Oral conjugated equine estrogens (CEE) shown to reduce risk of heart disease in 40 observational and casecontrol studies, and one randomized study Four angiographic studies: Estrogen reduced atherosclerosis 50 -80%. EPAT: RPC trial showed less increase in carotid intimal thickness with CEE vs. placebo.
30 Speroff L, Fritz M Clinical Gynecologic Endocrinology and Fertility, 7 th Ed.

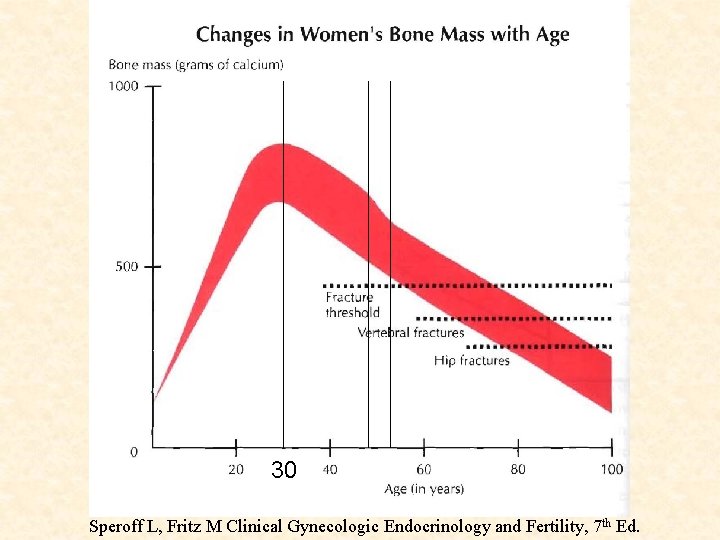
Osteoporosis—Impact Menopause: 5% bone loss/year for first 5 years=25%—due to loss of estradiol! 20 yrs. post menopause— 50% reduction in trabecular bone, 30% in cortical bone 50% of women >65 yrs. old have spinal compression fractures 14% lifetime risk of hip fracture for 50 yr. old woman, 30% for 80 yr. old. Speroff L, Fritz M Clinical Gynecologic Endocrinology and Fertility, 7 th Ed.

Osteoporosis—Prevention and Treatment A hormone deficiency disease—the proper prevention and treatment is hormone restoration. Estradiol prevents resorption of old bone while testosterone, progesterone, DHEA and GH build new bone. Raisz LG, J Clin Endo Metab. 1996; 81: 37 -43 Dec; 44(12): 1012 -20 Barrett-Connor E, J Reprod Med. 1999 Hormone restoration increases measured bone density better than biphosphonates and preserves normal bone remodeling (no “rotting jaw”, Ca++, or suppression of bone formation poor diaphyseal fracture healing,
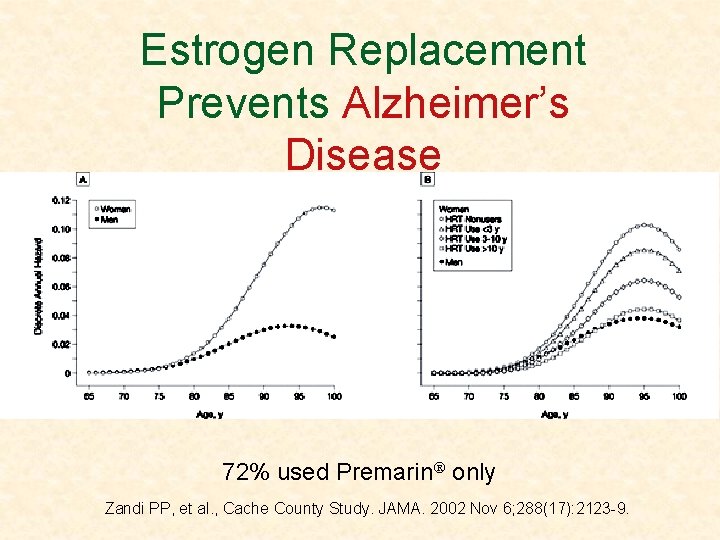
Estrogen Replacement Prevents Alzheimer’s Disease 72% used Premarin only Zandi PP, et al. , Cache County Study. JAMA. 2002 Nov 6; 288(17): 2123 -9.

Estradiol Restoration Eliminates hot flashes, restores sleep Protects cognitive function, improves mood Maintains thickness, fullness of skin and hair Protects against colon cancer and macular degeneration Prevents atherosclerosis, hypertension Maintains genital/pelvic health Improves insulin sensitivity—helps diabetes

Estrogen Therapies and Breast Cancer Bulk of evidence shows increase in breast cancer with unopposed estrogen (RR~1. 2) Risk increased with estrogen/progestin combinations (RR~1. 4 -2. 0) Beral V, Million Women Study. Lancet. 2003 Aug 9; 362(9382): 41927 No ’d risk of breast cancer in Premarin -only arm of WHI Risk may be higher with unopposed

Progesterone is Innocent! “The balance of the in vivo evidence is that progesterone does not have a cancer-promoting effect on breast tissue. ” Campagnoli C. Progestins and progesterone in hormone replacement therapy and the risk of breast cancer. J Steroid Biochem Mol Biol. 2005 Jul; 96(2): 95 -108. That’s the conservative way of putting it!

Progesterone and Breast Cancer Premenopausal women with low progesterone levels had 5. 4 x risk of early breast cancer 17 Cowan LD, Am J Epidem 1981; 114: 209 - Breast cancer victims have signs of progesterone resistance Simpson HW, Br J Obstet Gynaecol. 1998 Mar; 105(3): 345 -51 Progesterone decreased cell proliferation and cell cycle progression and induced apoptosis in breast cancer cell lines. Feb; 25(1 A): 243 -8 Ansquer Y, Anticancer Res. 2005 Jan- Progesterone receptor + predicts better
Progesterone and Breast Cancer—the Evidence cont. Estradiol cream applied to the breast induces proliferation, adding progesterone reduces proliferation to baseline Chang KJ, Fertil Steril 1995; 63: 785 -91 Estradiol is carcinogenic in breast cell cultures unless progesterone is present -25 Russo J, J Steroid Biochem Mol Biol. 2003 Oct; 87(1): 1 Breast cells proliferate after E 2 treatment, but become quiescent when P is added to E 2. Malet C, J Steroid Biochem Mol Biol. 2000 Jun; 73(3 -4): 171 -81 Estrogen upregulates cancer-promoting gene bcl-2, progesterone downregulates it.
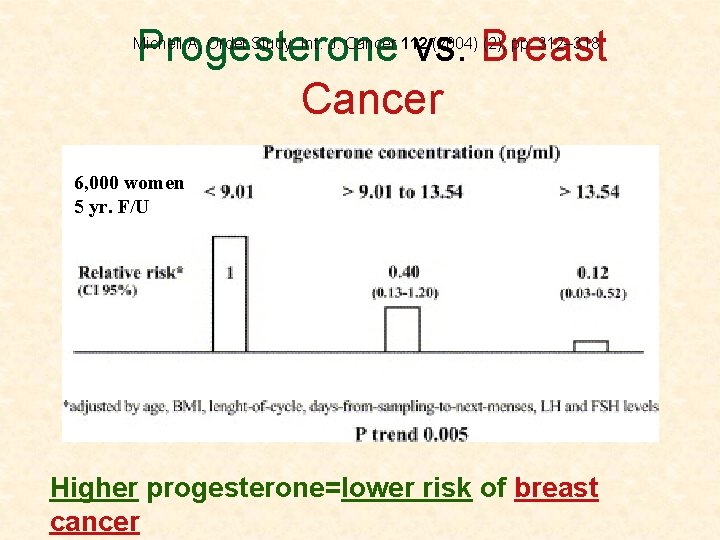
Progesterone vs. Breast Cancer Micheli A, Ordet Study: Int. J. Cancer 112 (2004) (2), pp. 312– 318. 6, 000 women 5 yr. F/U Higher progesterone=lower risk of breast cancer
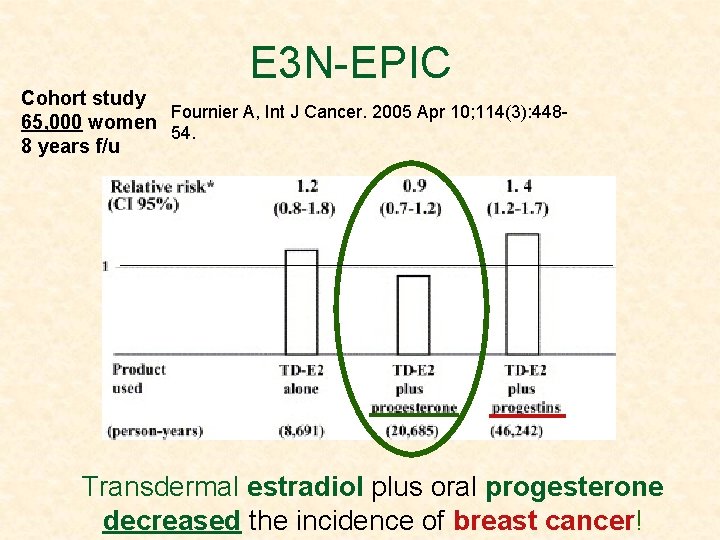
E 3 N-EPIC Cohort study Fournier A, Int J Cancer. 2005 Apr 10; 114(3): 44865, 000 women 54. 8 years f/u Transdermal estradiol plus oral progesterone decreased the incidence of breast cancer!

Top Researchers’ Conclusion “The hypothesis of progesterone and some progesterone-like progestins decreasing the proliferative effect of estradiol in the postmenopausal breast remains highly plausible and should be, until the coming of new evidences, the first choice for symptomatic postmenopausal women. ” Modena MG, Sismondi P, Mueck AO, Kuttenn F, Lignieres B, Verhaeghe J, Foidart JM, Caufriez A, Genazzani AR; The TREAT. New evidence regarding hormone replacement therapies is urgently required transdermal postmenopausal hormone therapy differs from oral hormone therapy in risks and benefits Maturitas. 2005 Sep 16; 52(1): 1 -10.

Cancer in Estradiol-Replete Women Testosterone opposes estradiol-induced breast stimulation. Dimitrakakis C, Menopause. 2003 Jul. Aug; 10(4): 292 -8 Somboonporn W, Endocr Rev. 2004 Jun; 25(3): 37488 Zhou J, FASEB J. 2000 Sep; 14(12): 172530 Addition of testosterone to estrogen/progestin reduces breast cancer incidence to baseline. 508 women; 8 yrs. Dimitrakakis C, Menopause. 2004 Sep-Oct; 11(5): 531 - 5 Testosterone and DHT inhibit in vitro growth of breast cancer cells. Ortmann J, Gynecol Endocrinol 2002;
Endogenous Hormones and Breast Cancer Some studies show increased breast cancer risk with ’d testosterone and DHEAS levels. 18; 97(10): 755 -65 Kaaks R (EPIC). J Natl Cancer Inst. 2005 May Key T, . J Natl Cancer Inst. 2002 Apr 17; 94(8): 606 -16 DHEAS and testosterone are converted into estradiol within tissues. Confounder: Premenopausal disorders causing ’d testosterone and DHEAS are associated with low progesterone levels (PCOS). Postmenopause: DHEAS and testosterone can be converted into estrogen and increase risk of breast cancer unless progesterone is

Female Andropause Young woman’s free testosterone level in serum is 2 x her free estradiol Female testosterone levels decline 50% between age 20 and 45. ERT testosterone and DHEAS levels (42% & 23% rsp. ) 8 Casson PR, Obstet Gynecol. 1997 Dec; 90(6): 995 - DHEAS declines with age—main source of androgens in women.

Testosterone for Women Improves energy, mood Improves sexual desire and sensation Increases muscle strength With estradiol, greater in bone density Dec; 44(12): 1012 -20 Barrett-Connor E, J Reprod Med. 1999 Probably decreases risk of heart attack Sep; 7(7): 825 -9 Rako S, J Womens Health. 1998 Opposes estradiol-induced breast stimulation and reduces risk of breast cancer.

DHEA Most abundant steroid hormone; yet ignored Cells make testosterone and estradiol from it Levels decline with age, stress and disease Lower levels assoc. with disease, mortality Anabolic—builds tissues, improves immunity Anti-cortisol effect, reduces abdominal fat Reduces pain—restores natural endorphins Reduces inflammation ( IL-6, TNF- , IL-2) Anti-atherosclerotic, prevents oxidation of LDL Improves fertility in older women-egg# and
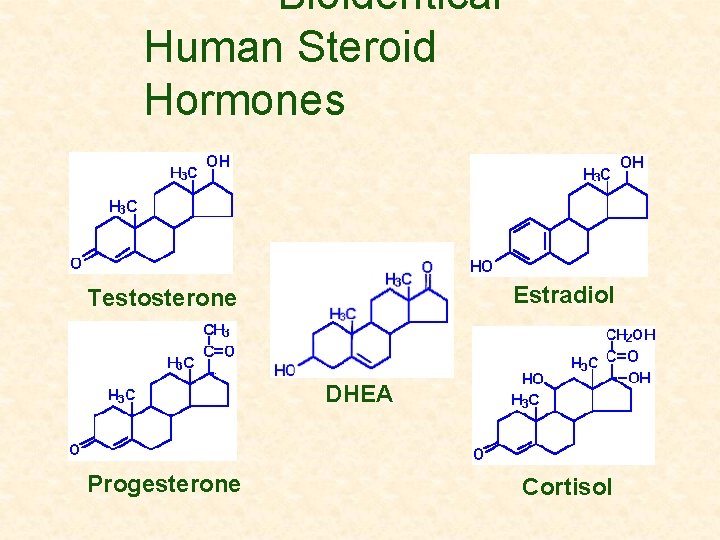
Bioidentical Human Steroid Hormones Estradiol Testosterone DHEA Progesterone Cortisol

Pharmaceutical “Hormone Replacement Therapy” Horse-urine Premarin approved in 1942 Synthesis of first human steroid hormone, progesterone, in 1942. Poorly absorbed orally Progesterone altered to make “progestins” —among the first drugs to be patented “HRT” came to mean the use of alien molecules that had hormone-like effects. Drug Co. s became dependent on HRT profits. Drug Co. s pushed doctors to use hormone

Conventional “HRT” is really Hormone Substitution Therapy. Progesterone substitutes: medroxyprogesterone acetate (MPAProvera ) and 30+ other “progestins” Estradiol substitutes: CEE-Premarin and ethinyl estradiol Testosterone substitute: methyltestosterone (metabolizes to super-potent estrogen and ’s breast cancer) Patented drugs—not human
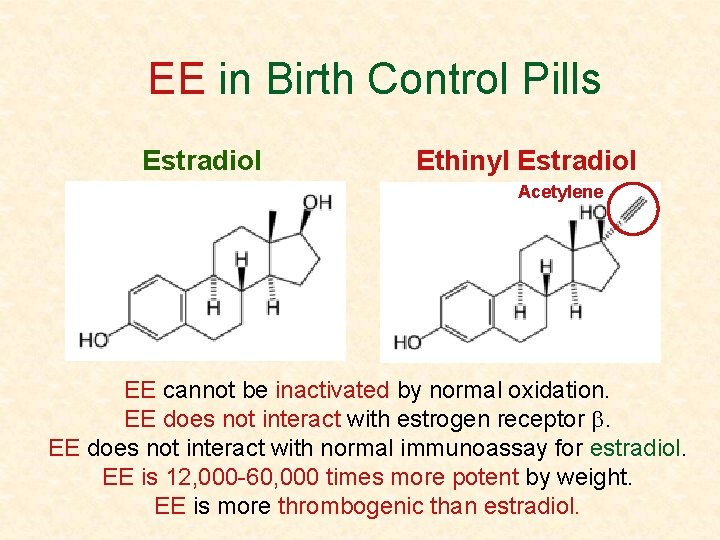
EE in Birth Control Pills Estradiol Ethinyl Estradiol Acetylene EE cannot be inactivated by normal oxidation. EE does not interact with estrogen receptor . EE does not interact with normal immunoassay for estradiol. EE is 12, 000 -60, 000 times more potent by weight. EE is more thrombogenic than estradiol.
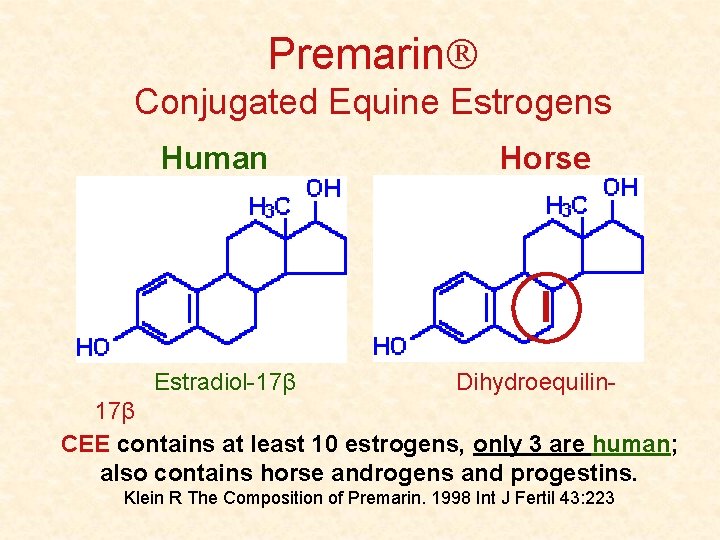
Premarin Conjugated Equine Estrogens Human Estradiol-17β Horse Dihydroequilin- 17β CEE contains at least 10 estrogens, only 3 are human; also contains horse androgens and progestins. Klein R The Composition of Premarin. 1998 Int J Fertil 43: 223
Oral Estrogen Replacement is Dangerous First-pass effect on the liver IGF-1, SHBG, CRP, clotting factors blood clots, strokes, heart attacks in the first year Transdermal estradiol has none of these effects! “Oral but not transdermal estrogen is associated with an increased VTE risk. ” 20; 115(7): 840 -5 Canonico M, ESTHER study. Circulation. 2007 Feb Transdermal estradiol improves insulin senstivity, oral estrogens do
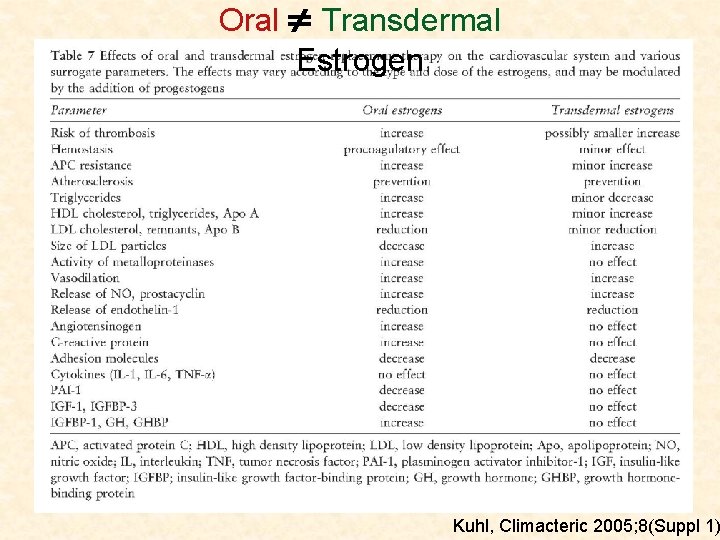
Oral Transdermal Estrogen Kuhl, Climacteric 2005; 8(Suppl 1)
2002 WHI Study—Premarin or Prempro given to older women (mean age 63), many >20 yrs post menopause Premarin alone had adverse effects in the first year (strokes, blood clots), but reductions in CHD afterwards (anti-atherosclerotic effect). Premarin alone did not increase risk of breast CA ( IGF-1, SHBG, horse progestins? ) Premarin reduced CHD and mortality in 5059 yr olds, but increased both in 70 -79 yr olds. Premarin reduced hip fractures by 39%
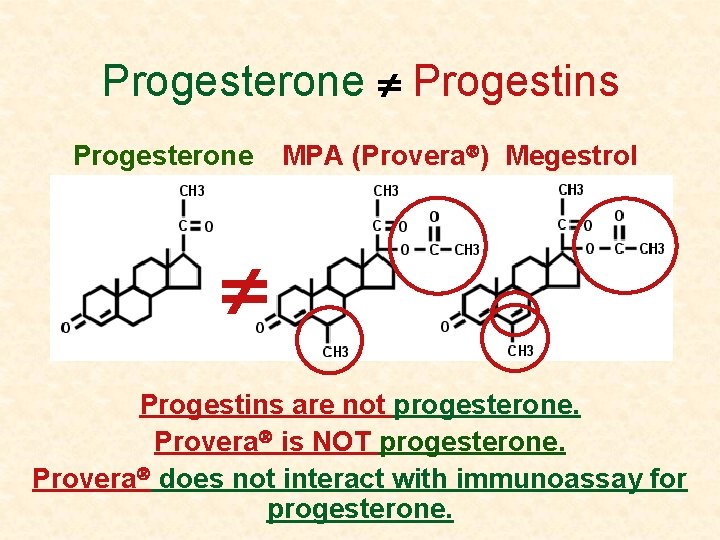
Progesterone Progestins Progesterone MPA (Provera ) Megestrol Progestins are not progesterone. Provera is NOT progesterone. Provera does not interact with immunoassay for progesterone.
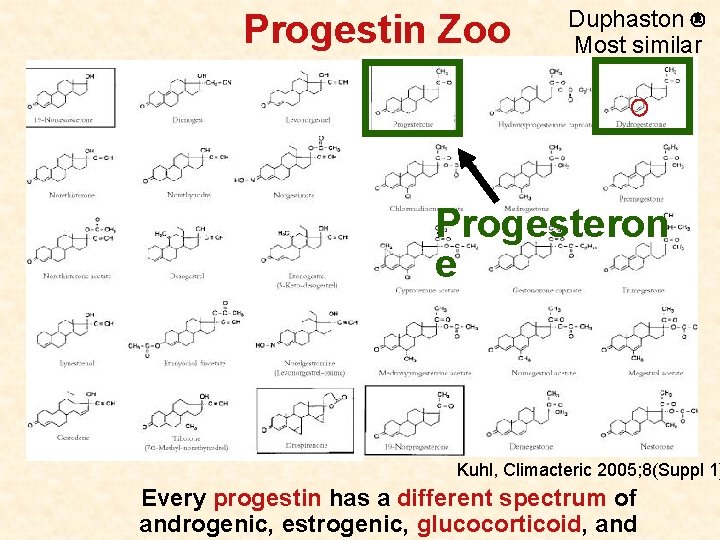
Progestin Zoo Duphaston Most similar Progesteron e Kuhl, Climacteric 2005; 8(Suppl 1) Every progestin has a different spectrum of androgenic, estrogenic, glucocorticoid, and

Scientific studies show that : Provera Progesterone • • • • Causes birth defects • Can cause depression • Insomnia, irritability • Reduces neuroprotection • Fluid retention • Raises blood sugar • Vasoconstriction • Increases SM • proliferation • Increases blood clotting • Worsens lipid profile • Causes heart attacks • Increases MMP activity • Increases estrogenic stimulation of breasts • Maintains pregnancy Improves mood Improves sleep Neuroprotective Diuretic Lowers blood sugar Arterial vasodilation Decreases SM proliferation No increase in clotting Improves lipid profile No evidence of CVD Reduces MMP activity Reduces estrogenic stimulation of breasts Prevents breast cancer

Atherosclerosis and Clotting “In both peripheral and cerebral vasculature (of live animals), synthetic progestins caused endothelial disruption, accumulation of monocytes in the vessel wall, platelet activation and clot formation, which are early events in atherosclerosis, inflammation and thrombosis. Natural progesterone or estrogens did not show such toxicity. ” Thomas T, Progestins initiate adverse events of menopausal estrogen therapy. Climacteric. 2003 Dec; 6(4): 293301 “In addition, our data suggest that norpregnane derivatives may be thrombogenic, whereas micronized progesterone and pregnane derivatives appear safe with respect to thrombotic risk. ” Canonico M, ESTHER study. Circulation. 2007 Feb

WHI Study—Prempro Adding Provera caused more vascular events. With Prempro , CHD RR <1 for women <10 yrs post menopause, 1. 7 if >20 yrs p. m. Prempro caused a large increase in dementia (vascular? , lack of neuroprotection? ). Prempro caused an increase in breast cancer. Thousands of lawsuits pending—drug companies running legal-protection

Hormones and Cardiovascular Disease Youthful levels of hormones are protective. Oral, not transdermal, estradiol increases the risk of thrombi (DVT, stroke, heart attack). Some progestins cause persistent endothelial inflammation, atherosclerosis, and clotting. Both oral and transdermal estradiol reduce atherosclerosis in the long term. Ideal Approach: Restore youthful hormonal milieu with transdermal bioidentical estradiol, testosterone, progesterone, and DHEA

Hormones and Breast Cancer Unopposed estradiol promotes breast cancer. Some progestins also promote breast cancer. When estradiol and progesterone are deficient, testosterone and DHEA may risk. When estradiol is present in youthful quantities, progesterone, DHEA and testosterone prevent breast cancer. Estradiol restoration is safe if given with progesterone, testosterone, and DHEA to

Conclusions Women’s hormones are not dangerous; the loss of women’s hormones is dangerous! Keeping a woman premenopausal by restoring hormones in the most physiological way and in natural balance must be considered beneficial until proven otherwise. Many well-known benefits; No proof of harm. Since menopausal hormone deficiencies are known to be harmful, those who would deny bioidentical hormone restoration to women have the burden of proving that

Hormone Restoration Unresolved issues—more investigation needed Methods of delivery, dosage, monitoring Need more long-term randomized studies to study long-term results (KRONOS, etc. ) Medical profession should be studying bioidentical hormone restoration instead of pharmaceutical hormone substitution!

For More Information www. hormonerestoration. com Essays on all aspects of hormone restoration Abstracts for all articles quoted can be found under “The Evidence” Contact me: Henry@hormonerestoration. com

Why So Much Confusion? As women switch to pharmacy-compounded bioidentical hormones, the North American Menopause Society (NAMS) publishes an anti-bioidentical hit piece—confounding bioidentical hormone replacement with questions surrounding compounding and saliva testing: Boothby L, Bioidentical hormone therapy: a review Menopause 2004 Vol. 11, No. 3, pp. 356 -367 NAMS advises that progesterone AND progestins both be called “progestogens”! NAMS tells women and their doctors: “Use any FDA-approved progestogen, but don’t use natural progesterone cream”.

ACOG Caves In to Pressure October 31, 2005, ACOG NEWS RELEASE No Scientific Evidence Supporting Effectiveness or Safety of Compounded Bioidentical Hormone Therapy Washington, DC – “There is no scientific evidence to support claims of increased efficacy or safety for individualized estrogen or progesterone regimens prepared by compounding pharmacies, …Furthermore, hormone therapy does not belong to a class of drugs with an indication for individualized dosing…ACOG recommends that all of them should be considered to have the same safety issues as those hormone products that are approved by the FDA and may also have additional risks unique to the compounding process. ” ACOG quotes NAMS article repeatedly ACOG is funded by Pharmaceutical Corporations

Wyeth Piles On October 2005 Wyeth (Prempro ) petitions the FDA to impose restrictions on physicians’ ability to prescribe and pharmacists’ ability to compounded bioidentical hormones! Demands same warnings for bioidentical hormone compounds as the FDA requires for Wyeth’s dangerous hormone substitutes Demands that compounding pharmacies cease promoting bioidenticals as more natural (? ? ) or safer (? ? ) than their dangerous hormone substitutes!

Wyeth//NAMS/ACOG Argument Hormone-substitution therapy has been proven to be dangerous: SO bioidentical hormone restoration is dangerous too! Non Sequitur! The Losers—Women!

FDA-Approved Bioidenticals Estradiol patch (Climara , Vivelle , etc. ) Estradiol gel (Estrogel ) Estradiol vaginal ring (Femring ) Progesterone capsules (Prometrium ) Progesterone vaginal gel (Crinone ) Testosterone gel (Androgel )

Compounded Bioidentical Hormones USP- certified micronized hormones (powder) Standardized compounding practices via PCCA (Professional Compounding Centers of America). Customized delivery system and concentrations Testosterone cream and sublingual progesterone not available commercially. Inexpensive—only $15 -40/mo for each hormone.
- Slides: 62