
ASPERGILLOSIS A variety of diseases pulmonary external ears


















- Slides: 53
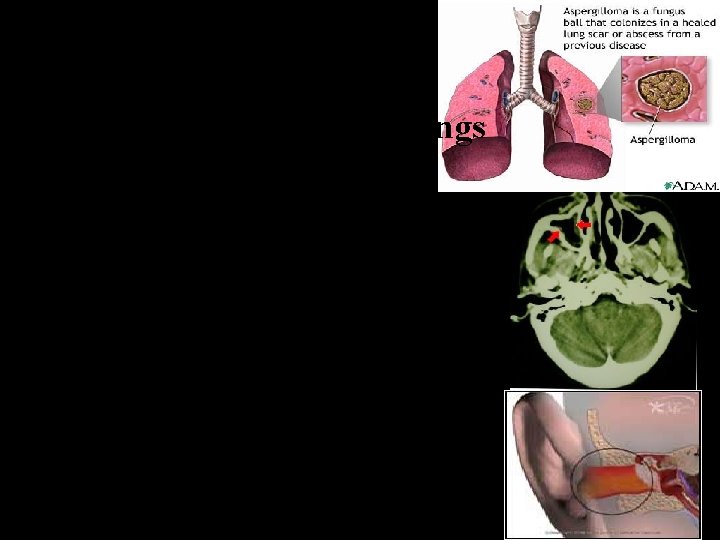
ASPERGILLOSIS A variety of diseases: pulmonary, external ears, eyes, meninges, sinuses or blood stream
1. ALLERGIC 2. FUNGUS BALL 3. INVASIVE
Difficult to diagnose 1. 2. 3. 4. 5. Clinical symptoms are not specific Radiography not specific (except fungus ball) Blood cultures seldom positive Serology seldom positive (early) Need invasive procedures for early detection
• • • A. FUMIGATUS A. NIGER A. FLAVUS
GEOGRAPHIC DISTRIBUTION WORLD-WIDE
• • • SOIL DECAYING VEGETATION FOOD MEDICATION AIR VENTS DISINFECTANTS
• • More than 900 species Slow growing Various gross colors Spores – Size – Shape – Texture – color
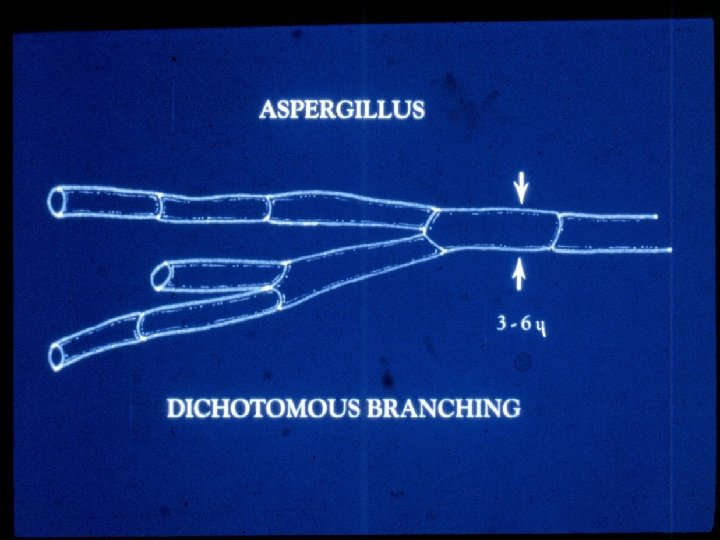
• DICHOTOMOUS BRANCHING • WIDE, SEPTATE HYPHAE
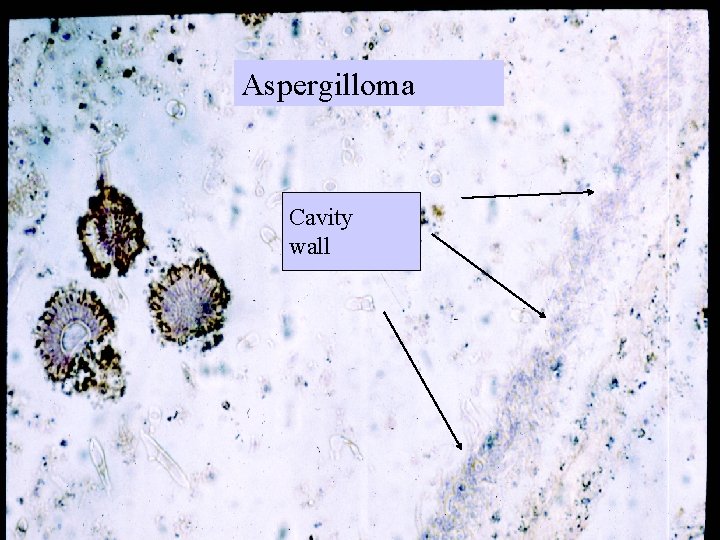
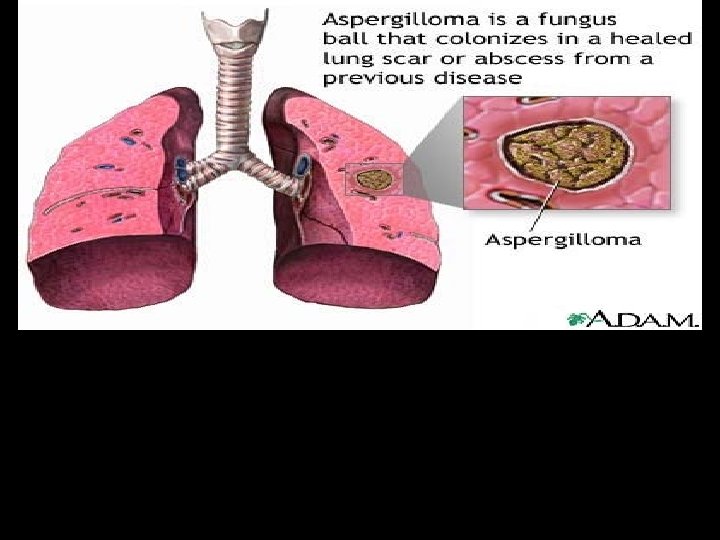
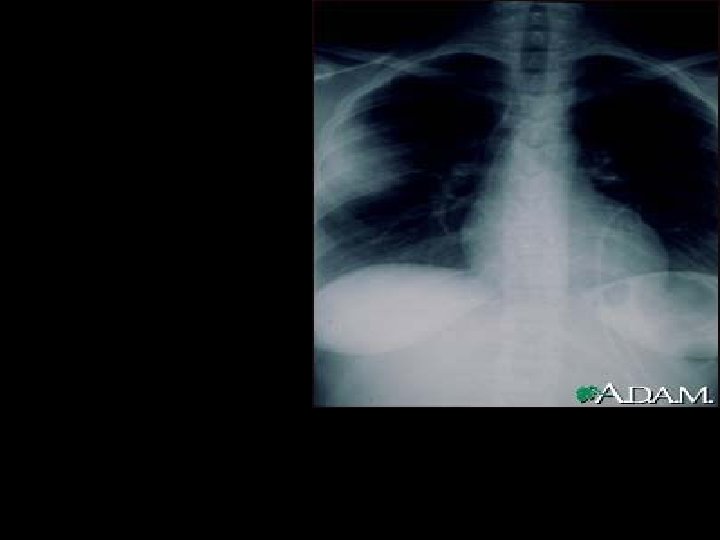
Aspergilloma Cavity wall
Aspergillosis is a spectrum of diseases of humans and animals caused by members of the genus Aspergillus. These include (1) mycotoxicosis due to ingestion of contaminated foods; (2) allergy to the presence of conidia or transient growth of the organism in body orifices; (3) colonization without extension in preformed cavities and debilitated tissues; (4) invasive, inflammatory, granulomatous, necrotizing disease of lungs, and other organs; and rarely (5) systemic and fatal disseminated disease. The type of disease and severity depends upon the physiologic state of the host and the species of Aspergillus involved. Distribution: World-wide. Aetiological Agents: Aspergillus fumigatus, A. flavus, A. niger, A. nidulans and A. terreus.
Verycommon: compost heaps, airbone dust�� Usuallyaffects the lungs and sinuses�� Less often: very agressive, spread trough outthelungs and bloodstream to brain and kidneys
Aspergillosis– Symptoms& Diagnosis �� May cause no symptoms fungus ball Rx) Reapeted coughing up of blood (severebleeding) �� Fever �� Chestpain �� Difficulty breathing
Aspergillosis-Symptoms& Diagnosis �� Can affect deepertissues: 1. Renalfailure 2. Liverfailure 3. Shock 4. Delirium 5. Boodclots 6. Deathcanoccurquickly �� Chestx-ray �� Computedtomography(CT) �� Wheneverpossible : sendmaterialto a laboratoryto confirmidentification
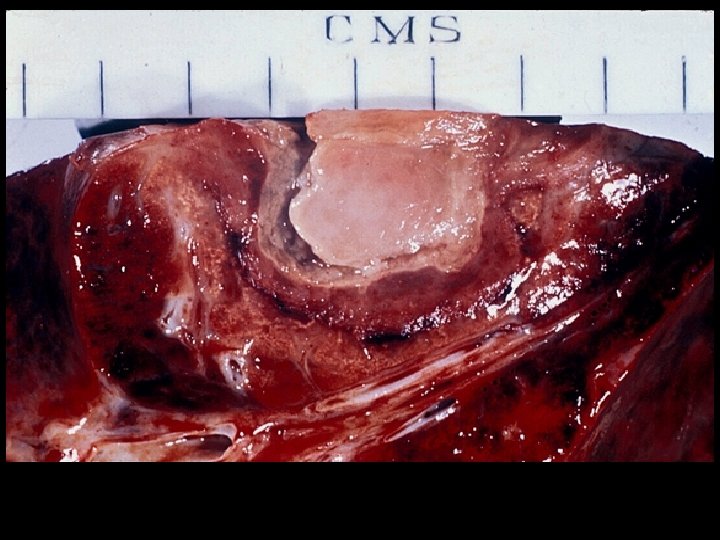
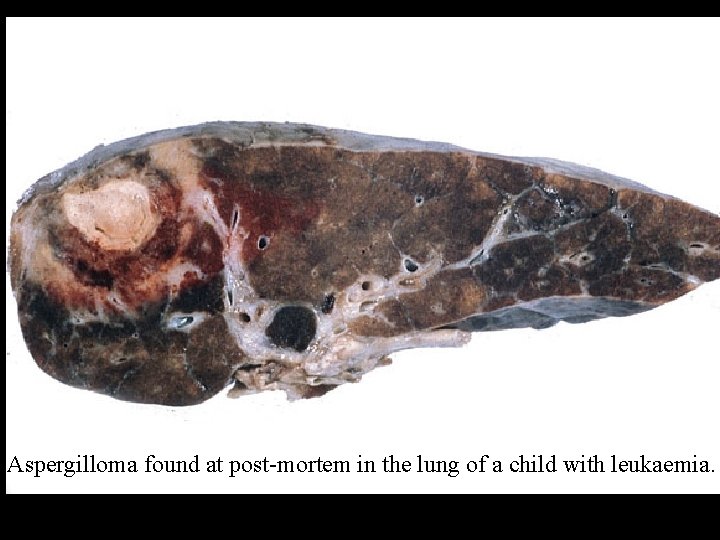
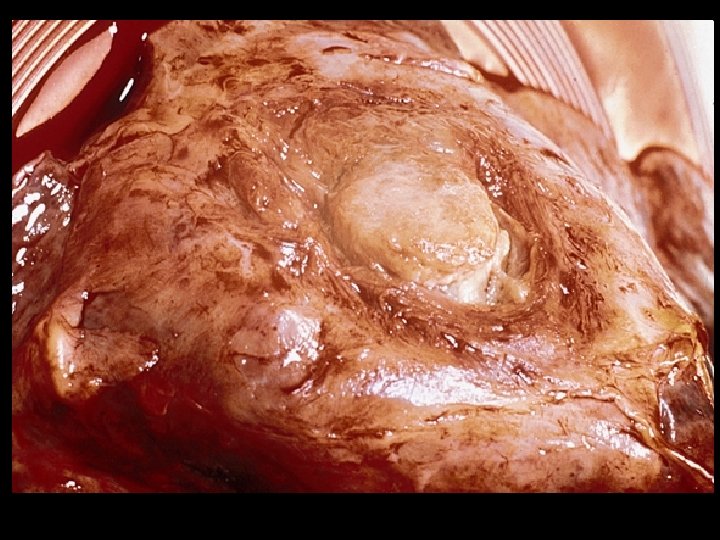
Aspergilloma found at post-mortem in the lung of a child with leukaemia. Note fungus ball occupying cavity.
Aspergilloma found at post-mortem in the lung of a child with leukaemia.
Aspergilloma found at post-mortem in the lung of a child with leukaemia.
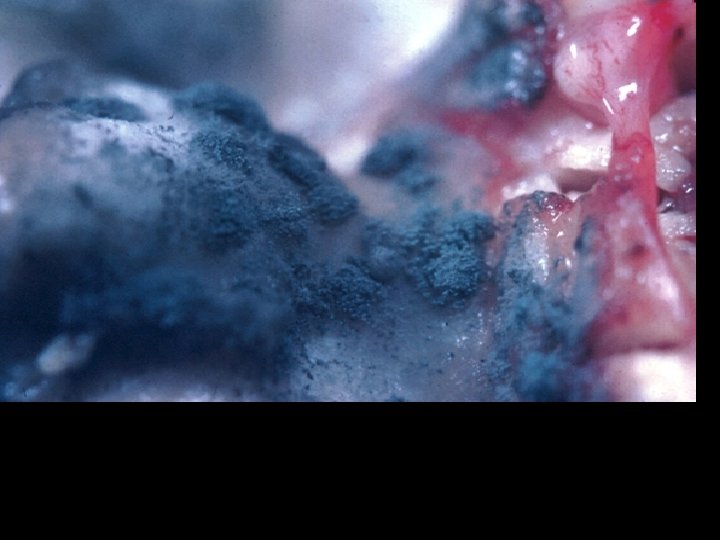
Aspergillosis in air sacs of a hen during an epidemic of aspergillosis in poultry.
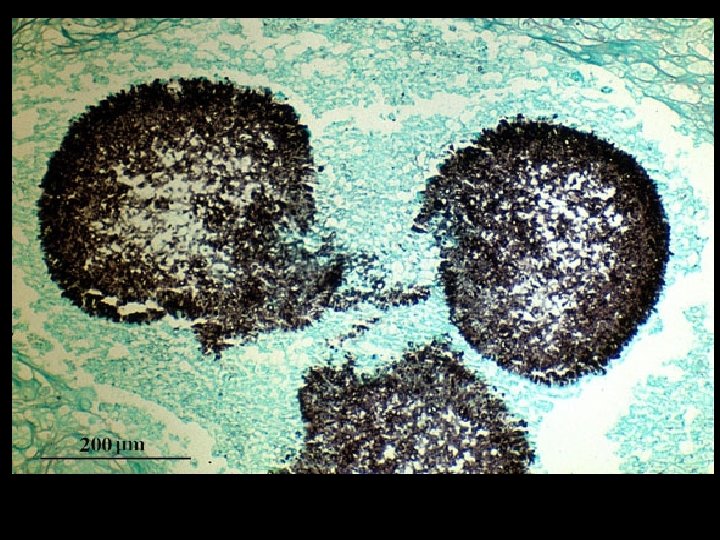
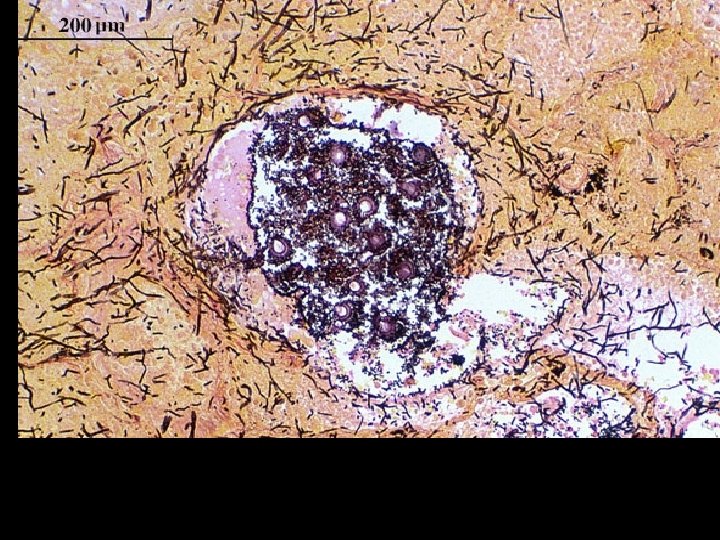
Grocott’s methenamine silver (GMS) stained tissue section of lung showing fungal balls of hyphae of Aspergillus fumigatus.
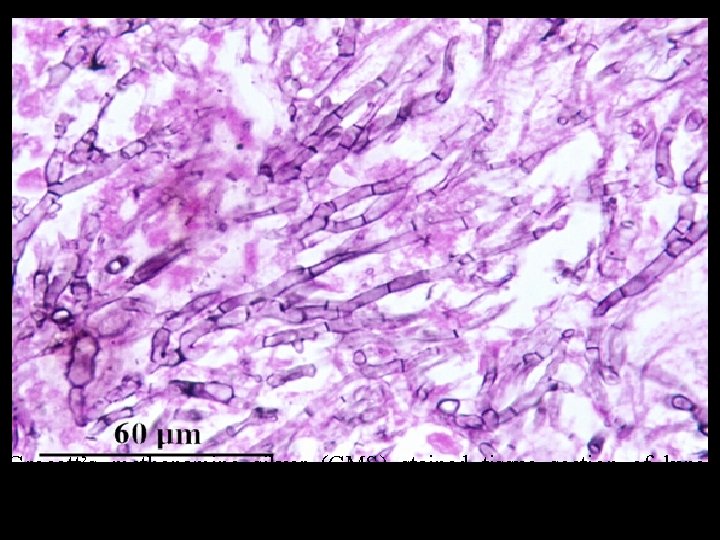
Grocott’s methenamine silver (GMS) stained tissue section of lung showing dichotomously branched, septate hyphae of Aspergillus fumigatus.
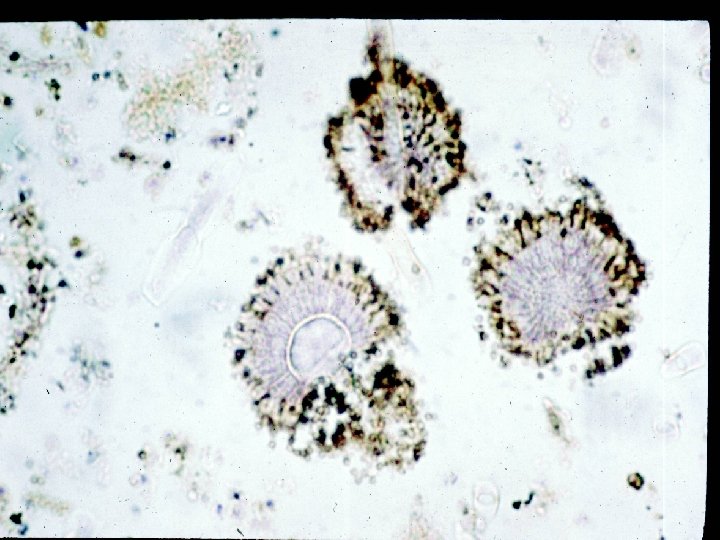
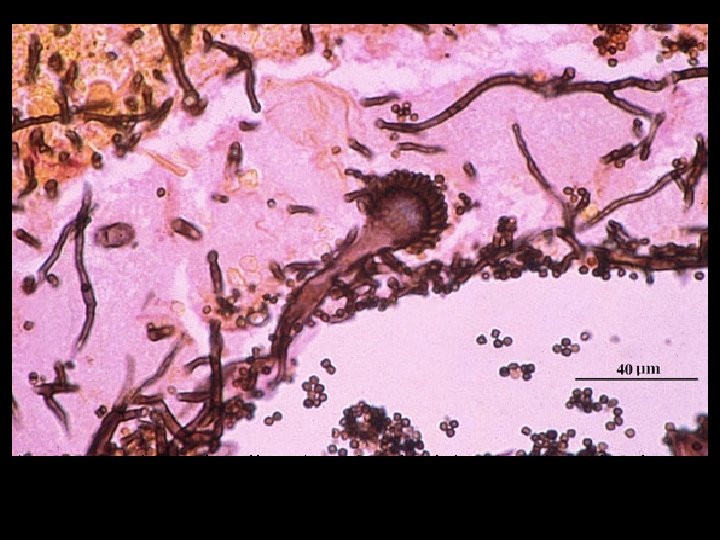
Grocott’s methenamine silver (GMS) stained tissue sections showing Aspergillus fumigatus in lung tissue, note conidial heads forming in an alveolus.
Grocott’s methenamine silver (GMS) stained tissue sections showing Aspergillus fumigatus in lung tissue, note conidial heads forming in an alveolus.
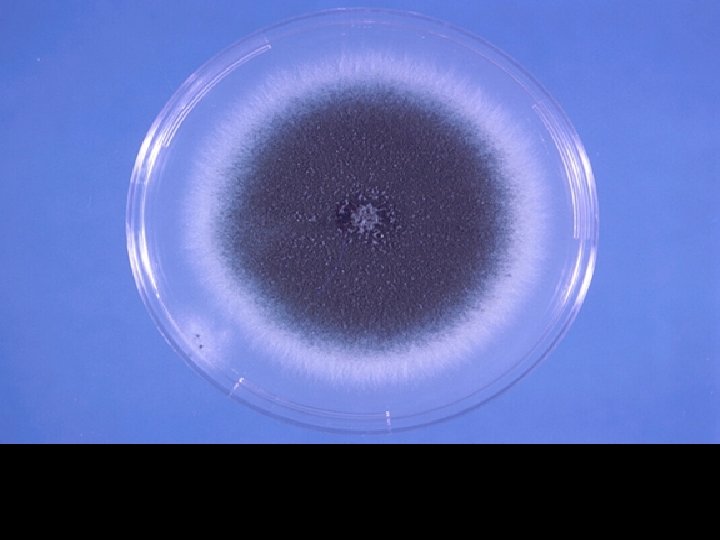
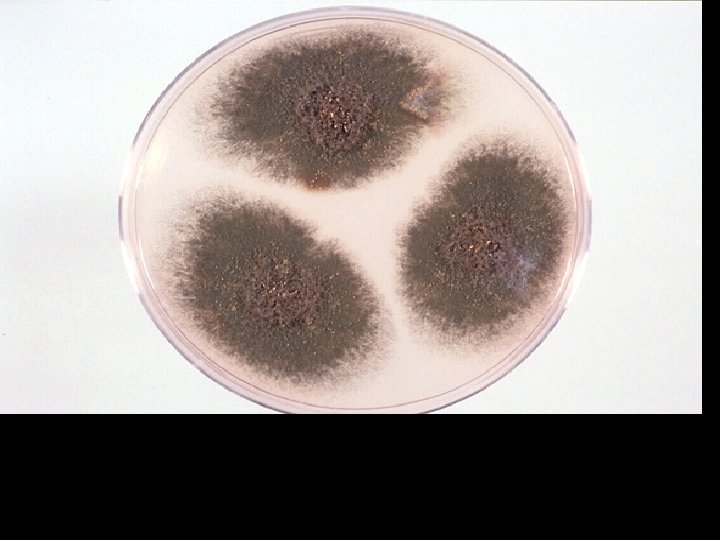
Aspergillus fumigatus on Czapek dox agar showing typical blue-green surface pigmentation consisting of a dense felt of conidiophores.
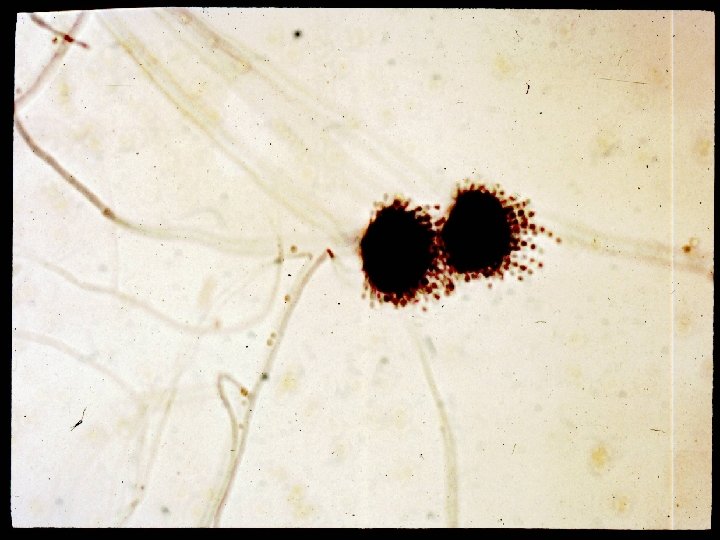
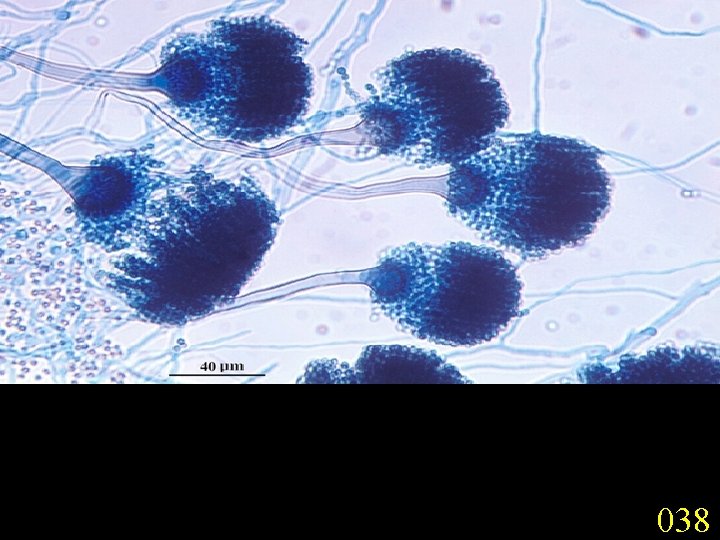
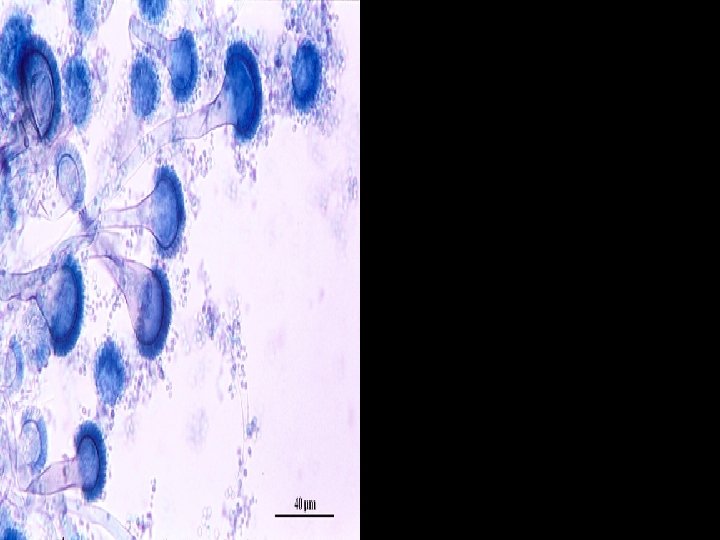
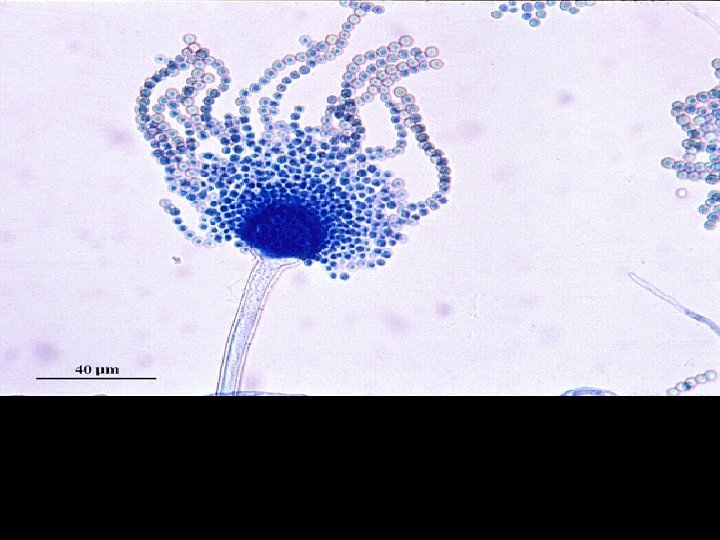
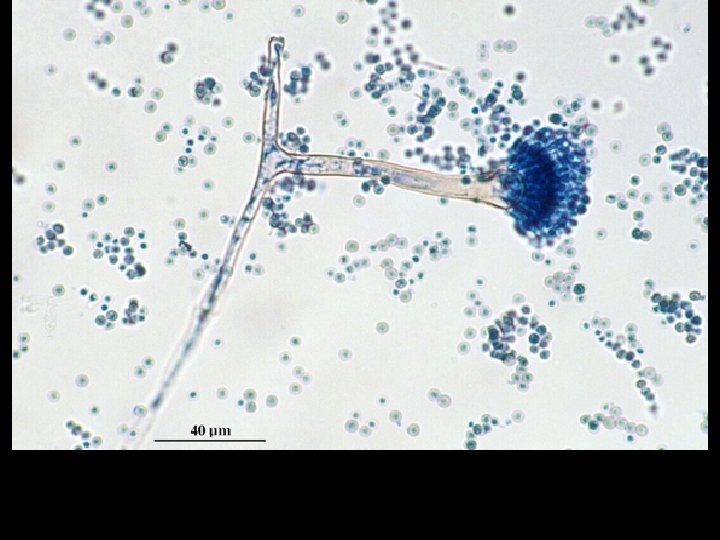
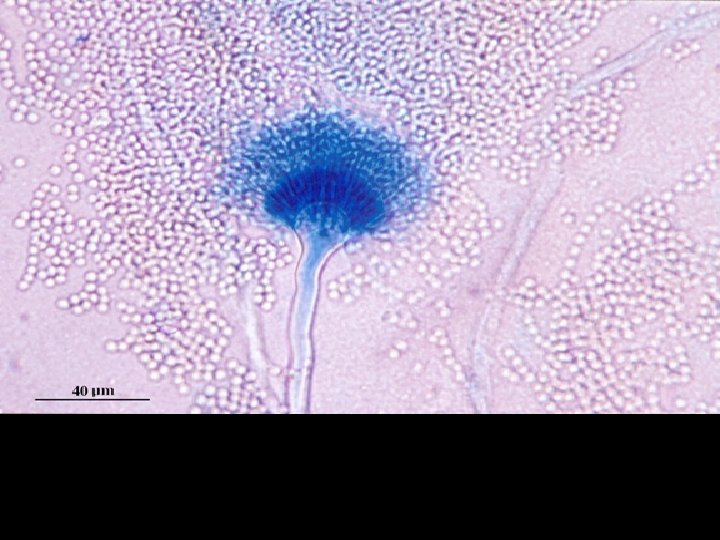
Microscopic morphology of Aspergillus fumigatus showing typical columnar, uniseriate conidial heads. Conidiophores are short, smooth-walled and have conical shaped terminal vesicles, which support a single row of phialides on the upper two thirds of the vesicle. Conidia are produced in basipetal succession forming long chains (slide 038), however, during preparation of slides the conidial chains are usually disrupted giving the more typical microscopic appearance seen in slide 039. Conidia are globose to subglobose, green and rough-walled to echinulate 038
Microscopic morphology of Aspergillus fumigatus showing typical columnar, uniseriate conidial heads. Conidiophores are short, smooth-walled and have conical shaped terminal vesicles, which support a single row of phialides on the upper two thirds of the vesicle. Conidia are produced in basipetal succession forming long chains (slide 038), however, during preparation of slides the conidial chains are usually disrupted giving the more typical microscopic appearance seen in slide 039. Conidia are globose to subglobose, green and roughwalled to echinulate.
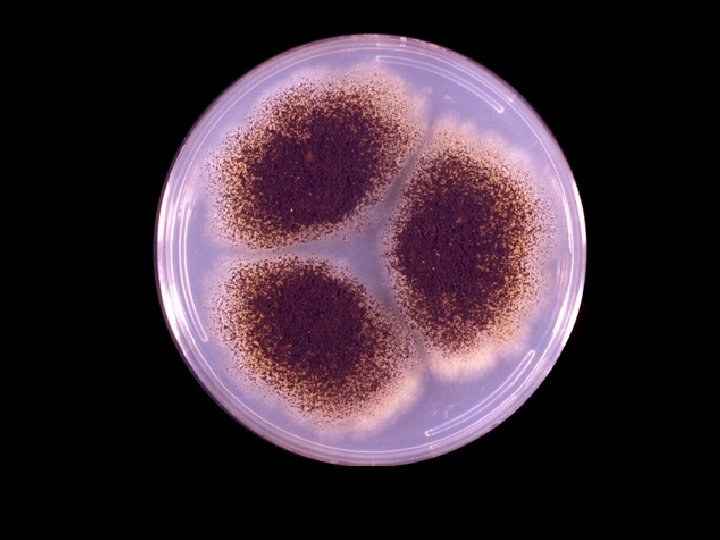
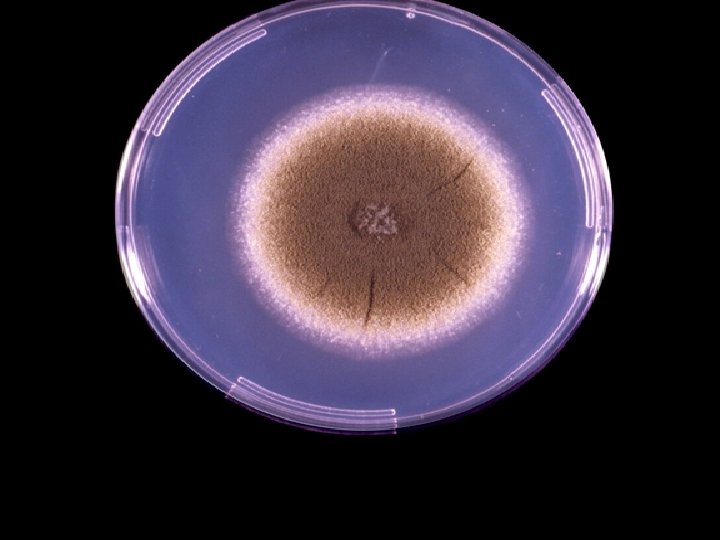
Aspergillus niger on Czapek dox agar. Colonies consist of a compact white or yellow basal felt covered by a dense layer of dark-brown to
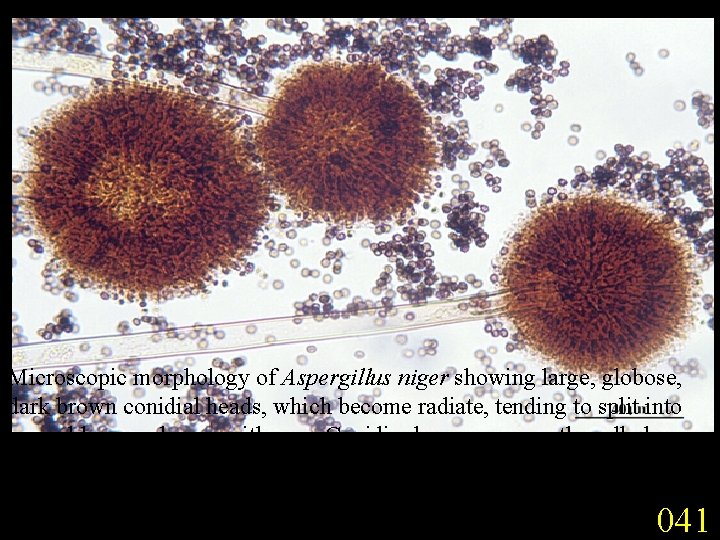
Microscopic morphology of Aspergillus niger showing large, globose, dark brown conidial heads, which become radiate, tending to split into several loose columns with age. Conidiophores are smooth-walled, hyaline or turning dark towards the vesicle. Conidial heads are biseriate with the phialides borne on brown, often septate metulae. Conidia are globose to subglobose, dark brown to black and rough-walled. 041
Aspergillus flavus on Czapek dox agar. Colonies are granular, flat, often with radial grooves, yellow at first but quickly becoming bright to dark yellow-green with age.
Microscopic morphology of Aspergillus flavus. Conidial heads are typically radiate, later splitting to form loose columns, biseriate but having some heads with phialides borne directly on the vesicle. Conidiophores are hyaline and coarsely roughened, often more noticeable near the vesicle. Conidia are globose to subglobose, pale green and conspicuously echinulate. Some strains produce brownish sclerotia.
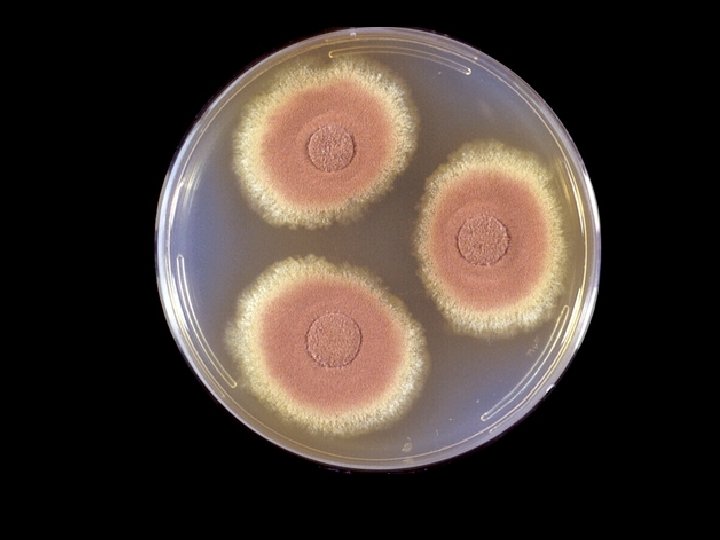
Aspergillus nidulans on Czapek dox agar showing typical plain green colony with dark red-brown cleistothecia developing within and upon the conidial layer. Reverse may be olive to drab-grey or purple-brown.
Microscopic morphology of Aspergillus nidulans. Conidial heads are short columnar and biseriate. Conidiophores are usually short, brownish and smooth-walled. Conidia are globose and rough-walled.
Aspergillus terreus on Czapek dox agar showing typical suede-like cinnamon-buff to sand brown colonies. Reverse yellow to deep dirty
Conidial head of Aspergillus terreus. Conidial heads are compact, columnar and biseriate. Conidiophores are hyaline and smooth-walled. Conidia are globose to ellipsoidal, hyaline to slightly yellow and smoothwalled.
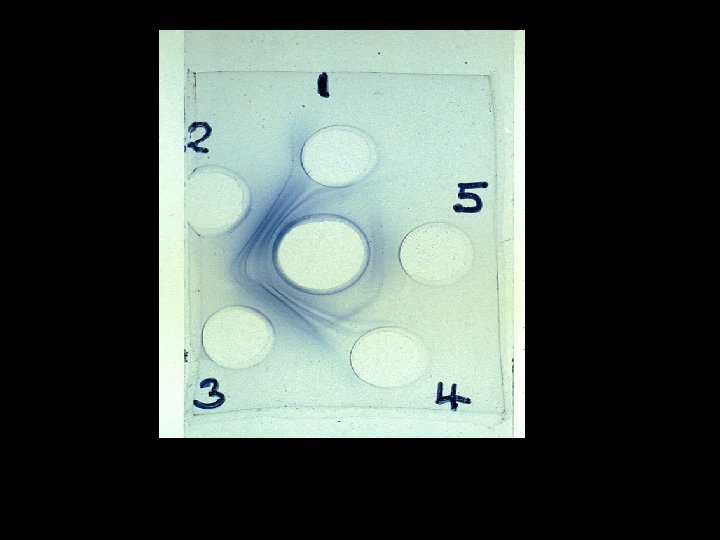
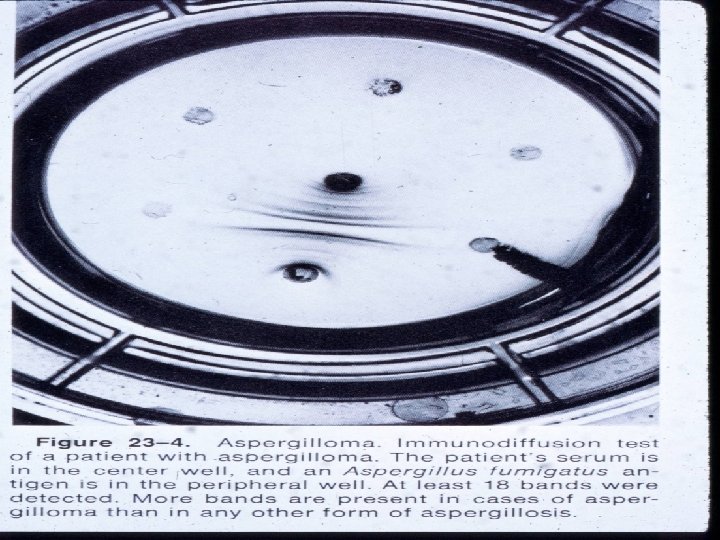
Immunodiffusion test showing precipitins against Aspergillus.
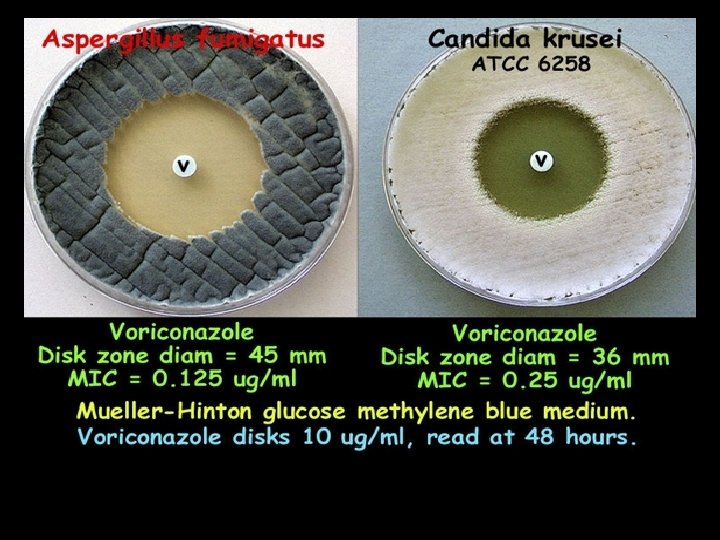
Antifungal susceptibility disk test showing the in vitro activity of voriconazole against Aspergillus fumigatus with Candida krusei as a control.
Aspergillosis-Prognosis& Treatment Whenpresentin a sinus or single spot in the lung progresses SLOWLY Requires treatment, but no immediatedanger If infection widespread: patient isseriously ill Voriconazole Amphotericinb Itraconazole Capsofungin
If fungus balls grow near lungs. Blood vessels removed surgically Sinuses aspergillosis removed surgically Ear canal infection scrapingout the fungus and topics antifungal drops
New (and newer) antifungals invasive aspergillosis Polyenes Azoles • ABLC, ABCD, • itraconazole (i. v. ) Am. Bisome • voriconazole • liposomal nystatin • posaconazole • inhaled amphotericin B • ravuconazole • BAL 8557/4815 Note: Blue text, earlier stage development Note: ABLC=amphotericin B lipid complex; ABCD= amphotericin B colloidal dispersion for Echinocandins • caspofungin • micafungin • anidulafungin • aminocandin
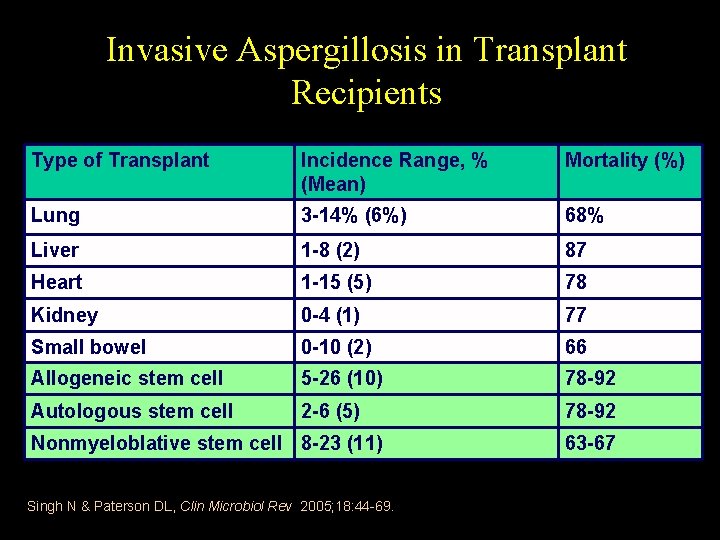
Invasive Aspergillosis in Transplant Recipients Type of Transplant Incidence Range, % (Mean) Mortality (%) Lung 3 -14% (6%) 68% Liver 1 -8 (2) 87 Heart 1 -15 (5) 78 Kidney 0 -4 (1) 77 Small bowel 0 -10 (2) 66 Allogeneic stem cell 5 -26 (10) 78 -92 Autologous stem cell 2 -6 (5) 78 -92 Nonmyeloblative stem cell 8 -23 (11) Singh N & Paterson DL, Clin Microbiol Rev 2005; 18: 44 -69. 63 -67
Aspergillus spp. Isolates Submitted to San Antonio Fungus Testing Laboratory 918 Isolates; Jan. 2001 -July 2004 Am. B MFC >16 § A. fumigatus Am. B MIC>2 § A. terreus § A. flavus A. nidulans 3% § A. ustus Am. B=Amphotericin B; MFC=Minimum Fungicidal Concentration; MIC=Minimum Inhibitory Concentration Sutton D et al, Advances Against Aspergillus 2004 (Abstract 16) 24% 90% 51% 50%
Lipid Preparations of Amphotericin B: Rationale for Use • Polyene: broad spectrum of activity • Lipid formulations of amphotericin B – Reduced toxicities of intravenous amphotericin B deoxycholate – Improved therapeutic index: ≥ 5 mg/kg/d well tolerated • Salvage therapy (limited efficacy 40% responded) • Empiric therapy (reduced efficacy vs moulds at lower doses) • Limited data for primary therapy; most studies in empirical use • Target use for patients with documented need (eg Zygomycosis, intolerance or progressive infection) – Cost remains significant obstacle to use!
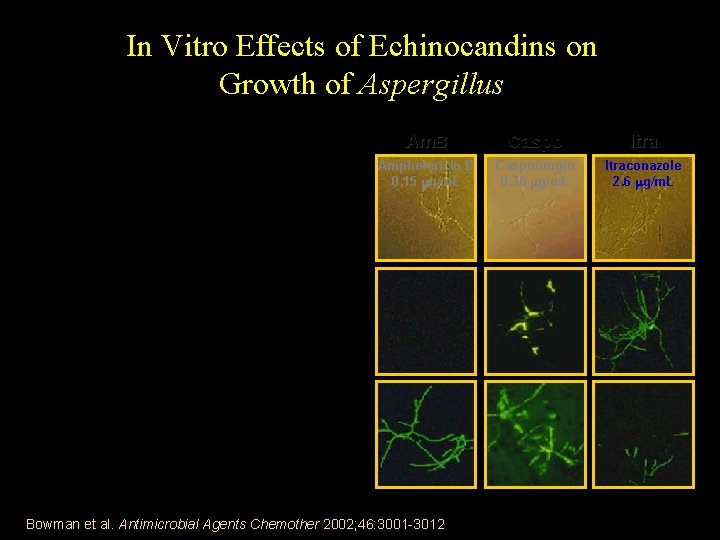
In Vitro Effects of Echinocandins on Growth of Aspergillus In vitro activity: • Not classically fungicidal or fungistatic • Activity against other Aspergillus spp. (A terreus) • Animal models prolonged survival Am. B Caspo Itra Amphotericin B 0. 15 g/m. L Caspofungin 0. 30 g/m. L Itraconazole 2. 6 g/m. L Control Cells Living Cells Dead Cells Bowman et al. Antimicrobial Agents Chemother 2002; 46: 3001 -3012
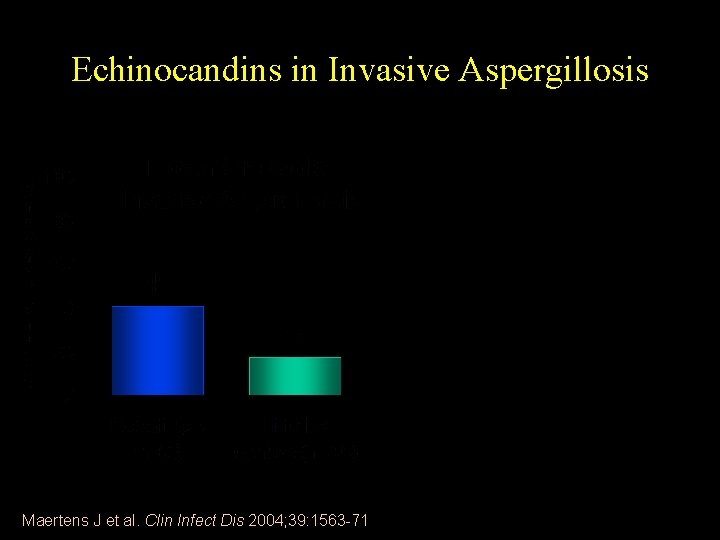
Echinocandins in Invasive Aspergillosis • Study conducted in patients • – – % % • • – – Maertens J et al. Clin Infect Dis 2004; 39: 1563 -71 with well-documented, refractory infection Efficacy Progressive infection Multiple prior antifungals Excellent tolerability Clinical utility for moulds Combination therapy (not primary therapy) Activity: Aspergillus (not Zygomycetes or other moulds)
Diagnostic Strategies in Invasive Aspergillosis • Consideration of risk • Role of mycological diagnosis – Predictive value of positive cultures in high risk patients • Utility of radiological procedures • Non-culture based diagnostics – – Impact of antifungal therapies Value of serial samples Significance of false negative/false positive results Role of testing in other body fluids, including CSF & BAL • Role of surrogate markers in decision making & impact on mortality
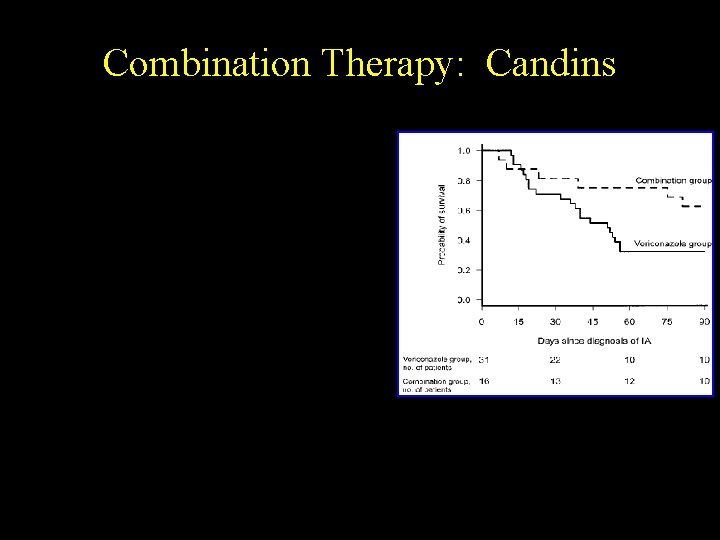
Combination Therapy: Candins • In vitro – Most interactions show synergy / additive effects (Perea, 2002) – Poor correlation between in vitro results and in vitro efficacy (Johnson, 2004) • Experimental infections – Candin plus polyene (Kohno, 2000; Nakajima, 2000) – Candin plus azole (Kirkpatrick, 2002; Petraitiene, 2002) • Improved sterilization of tissues • Reduced tissue burden • Anecdotal clinical series – Candin+polyene (Aliff, 2003; Kontoyiannis, 2003; Ratanatharathorn, 2002) – Candid plus azole (Marr, 2004)
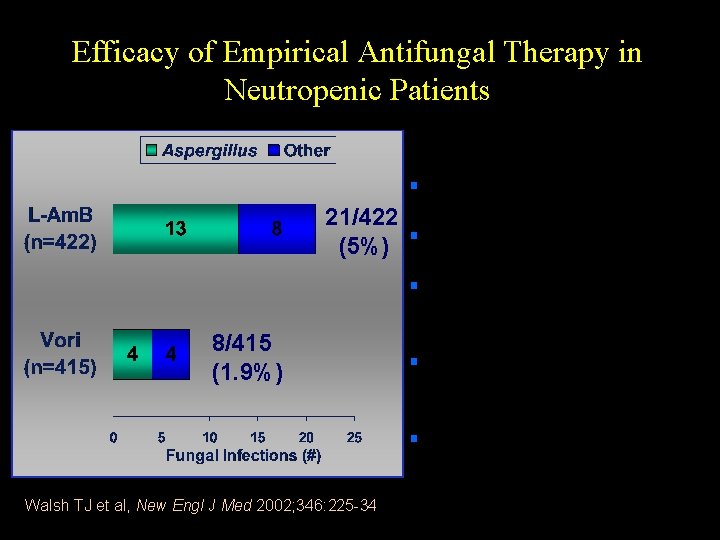
Efficacy of Empirical Antifungal Therapy in Neutropenic Patients • § 21/422 (5%) § § 8/415 (1. 9%) § • Voriconazole vs liposomal amphotericin B Composite success: 26% vs 31% High risk patients: 18% allogeneic BMT Similar survival, fever resolution, toxicity or lack of efficacy Fewer breakthrough infections Efficacy in high risk: § Breakthrough infections: 2/143 (2%) vs 13/143 (9%) Walsh TJ et al, New Engl J Med 2002; 346: 225 -34
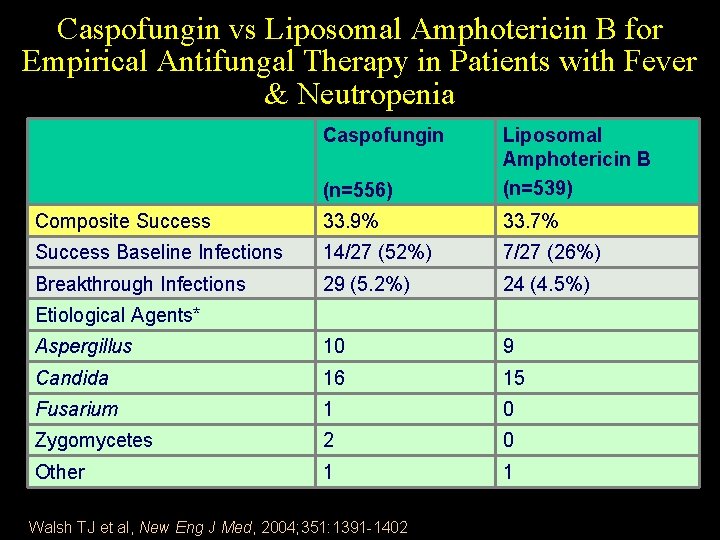
Caspofungin vs Liposomal Amphotericin B for Empirical Antifungal Therapy in Patients with Fever & Neutropenia Caspofungin (n=556) Liposomal Amphotericin B (n=539) Composite Success 33. 9% 33. 7% Success Baseline Infections 14/27 (52%) 7/27 (26%) Breakthrough Infections 29 (5. 2%) 24 (4. 5%) Aspergillus 10 9 Candida 16 15 Fusarium 1 0 Zygomycetes 2 0 Other 1 1 Etiological Agents* *Patients may have had more than one organism Walsh TJ et al, New Eng J Med, 2004; 351: 1391 -1402
Invasive Aspergillosis: Polyenes, Azoles or Echinocandins? • Importance of early detection – Role of radiological diagnosis – Non-culture based diagnostics • Importance of serial samples • Impact of prior therapy – Poorer outcomes with extensive disease • Poor efficacy of amphotericin B in high risk patients – Improved responses with early effective therapy – Utility of early targeted therapy • Role of new agents in invasive aspergillosis – Efficacy of voriconazole as primary therapy – Options for salvage therapy: posaconazole, echinocandins, lipid amphotericin formulations • Clinical trials needed combination therapy