
Approach to the patient with Myopathy Medicine II








































- Slides: 68
Approach to the patient with Myopathy Medicine II Dr. Abubacarr Jagne
Outline Basics Clinical manifestations Diagnostic approach Individual myopathies Approach to the patient
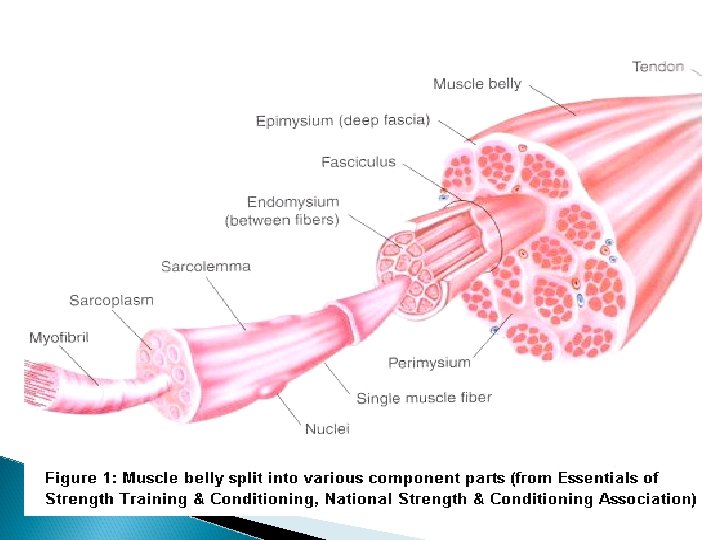
Skeletal muscle Composed of muscle fibers that contract when stimulated by a motor neuron Skeletal muscle: covered by connective tissue sheath( epimysium) : composed of many columns( fascicles) Fascicles: surrounded by perimysium : composed of many muscle fibers Muscle fibers: covered by cell membrane ( sarcolemma) and surrounded by endomysium. : anatomic and physiologic unit. Two types : 1. Type - I / slow twitch/ red fibers : richer in oxidative but poorer in glycolytic enzymes. 2. Type- II/ fast twitch/ white fibers : richer in glycolytic but poorer in oxidative enzymes. : composed of nuclei, cytoplasm ( sarcoplasm), myofibrils, ribosomes, mitochondria, stored fat, many enzymes, glycogen, myoglobin.
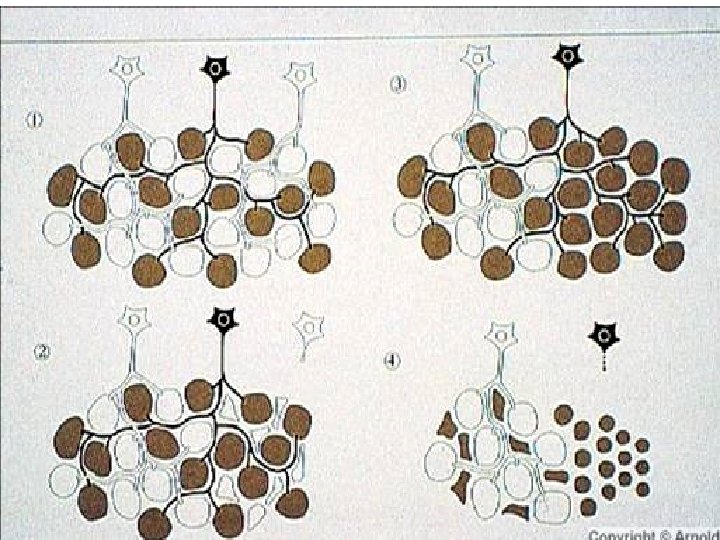
Myofibril : longitudinally oriented interdigitating filaments of contractile proteins ( Actin, Myosin) & regulatory proteins ( Troponin, tropomyosine, nebuline). : Thick filaments: composed of protein, Myosin. : Thin filaments: composed of protein , Actin. : enveloped by a membranous net ( sarcoplasmic reticulum) Motor unit : each somatic motor neuron together with all of the muscle fibers it innervates. : each neuron innervates muscle fibers of one type only. : Neuromuscular junction( NMJ) : junction of the terminal of the motor neuron with the muscle fiber. : Motor end plate: specialized region of the sarcolemma of the muscle fiber at the NMJ.
courtesy : Prof. Janzer
Muscle contraction: sliding of thin filaments over and b/n thick filaments by the action of numerous cross bridges that extend out from the myosine toward the actin. ◦ : muscle fiber stimulation by motor neuron → ca+2 moves from its store site in the sarcoplasmic reticulum to the sarcoplasm→ attaches to troponine → conformational change that moves the troponin complex and its attached tropomyosine out of the way so that cross bridges can attach to actin→ sliding of filaments and thus muscle tension and shortening. ▪ Energy source : fatty acids , glycogen and blood glucose, aminoacids : skeletal muscles generate ATP through anaerobic and aerobic respirations and phosphate groups donated by creatine phosphate. ATP : serves as the immediate source of energy for 1. movement of cross bridges for muscle contraction 2. pumping of ca+2 in to the sarcoplasmic reticulum for muscle relaxation.
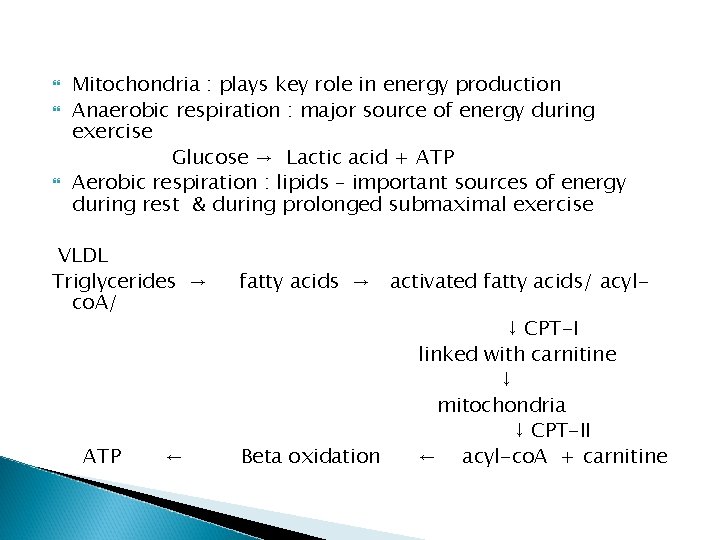
Mitochondria : plays key role in energy production Anaerobic respiration : major source of energy during exercise Glucose → Lactic acid + ATP Aerobic respiration : lipids – important sources of energy during rest & during prolonged submaximal exercise VLDL Triglycerides → co. A/ ATP ← fatty acids → activated fatty acids/ acyl- Beta oxidation ↓ CPT-I linked with carnitine ↓ mitochondria ↓ CPT-II ← acyl-co. A + carnitine
Myopathy Defn. : disorders with structural changes or functional impairment Classification : of a muscle; unrelated to any disorder of innervation or NMJ. 1. Acquired 2. Hereditary/ genetic : mutations or deletions of genes coding for parts of a muscle ( filament proteins, mitochondrial enzymes, sarcoplasmic reticulum, specialized channels for entry of ca+2 , Na+2, Cl- , K+1 transverse tubules, sarcolemma ) : affect structure or biochemical processes which convert chemical energy derived from cell metabolism in to mechanical energy in a controlled manner.
Etiology Inflammatory Metabolic Toxic Congenital /inherited Endocrinopathies Chanellopathies Muscular dystrophies
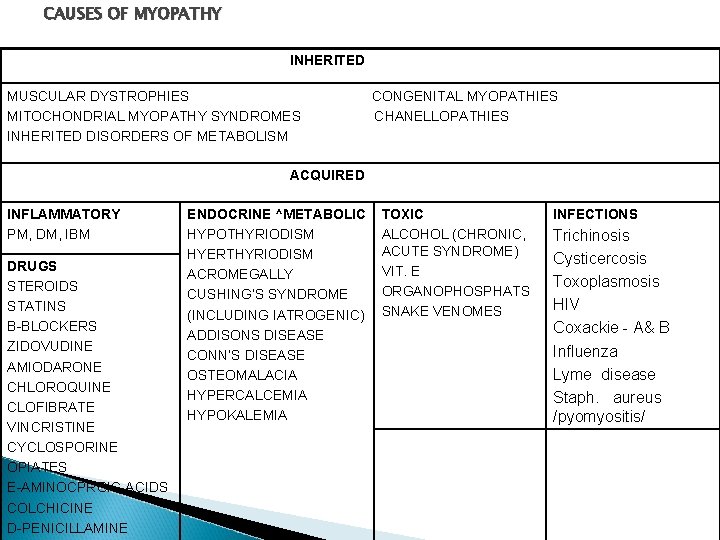
CAUSES OF MYOPATHY INHERITED MUSCULAR DYSTROPHIES MITOCHONDRIAL MYOPATHY SYNDROMES INHERITED DISORDERS OF METABOLISM CONGENITAL MYOPATHIES CHANELLOPATHIES ACQUIRED INFLAMMATORY PM, DM, IBM DRUGS STEROIDS STATINS B-BLOCKERS ZIDOVUDINE AMIODARONE CHLOROQUINE CLOFIBRATE VINCRISTINE CYCLOSPORINE OPIATES E-AMINOCPROIC ACIDS COLCHICINE D-PENICILLAMINE ENDOCRINE ^METABOLIC HYPOTHYRIODISM HYERTHYRIODISM ACROMEGALLY CUSHING’S SYNDROME (INCLUDING IATROGENIC) ADDISONS DISEASE CONN’S DISEASE OSTEOMALACIA HYPERCALCEMIA HYPOKALEMIA TOXIC ALCOHOL (CHRONIC, ACUTE SYNDROME) VIT. E ORGANOPHOSPHATS SNAKE VENOMES INFECTIONS Trichinosis Cysticercosis Toxoplasmosis HIV Coxackie - A& B Influenza Lyme disease Staph. aureus /pyomyositis/
Clinical presentation Muscle weakness Fatigue Muscle pain( myalgia), cramps and stiffness Muscle contracture myoglobinuria Myotonia Muscle enlargement and atrophy Manifestations of specific illnesses
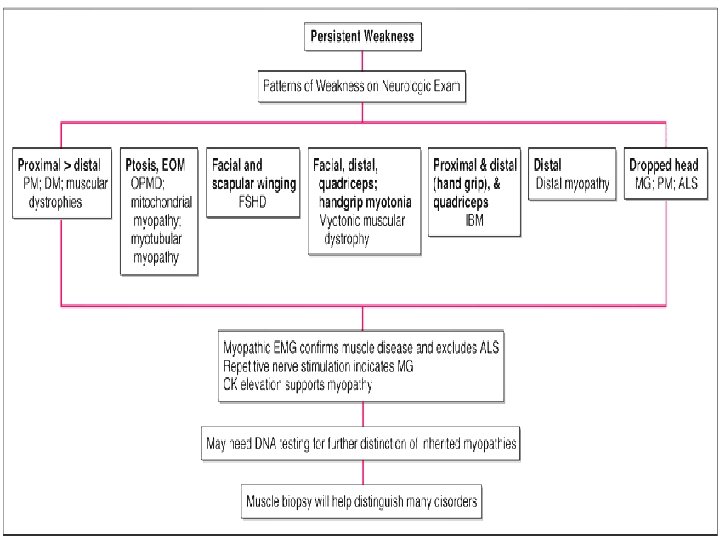
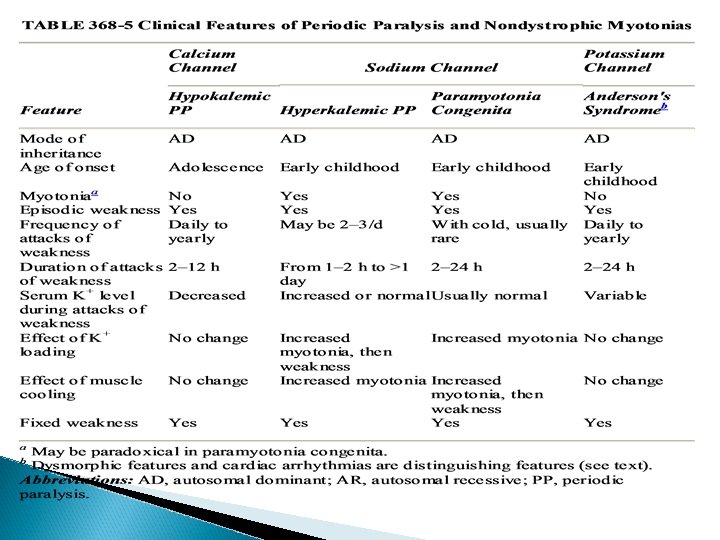
Muscle weakness Symptoms: Proximal – difficulty in combing hair, getting up from a chair, climbing stairs, getting up from a squatting position. : Distal – difficulty buttoning, writing, knitting. Types: Intermittent ( periodic)- proximal > distal ( limb- girdle pattern ) - Hypo. KPP, Hyper. KPP, paramyotonia congenita - metabolic energy deficiencies of glycolysis - abnormalities in fatty acid metabolism - myasthenia gravis: NCS~ repetitive nerve stimulation decremental response : Persistent ( fixed) - most muscle disorders - limb - girdle pattern /face spared/ is common - some patterns are restricted to certain diseases.
fatigue Inability to maintain or sustain a force Pathologic fatiguability -Disorders of neuromuscular transmission, disorders altering energy metabolism ( glycolysis, lipid metabolism), disorders in mitochondrial energy production - Chronic myopathies - Accompanied by abnormal clinical or laboratory findings Asthenia - a type of fatigue caused by excess tirdeness or lack of energy - a tendency to avoid physical activities - complaints of daytime sleepiness - necessity for frequent naps - difficulty concentrating on activities such as reading - feelings of overwhelming stress & depression
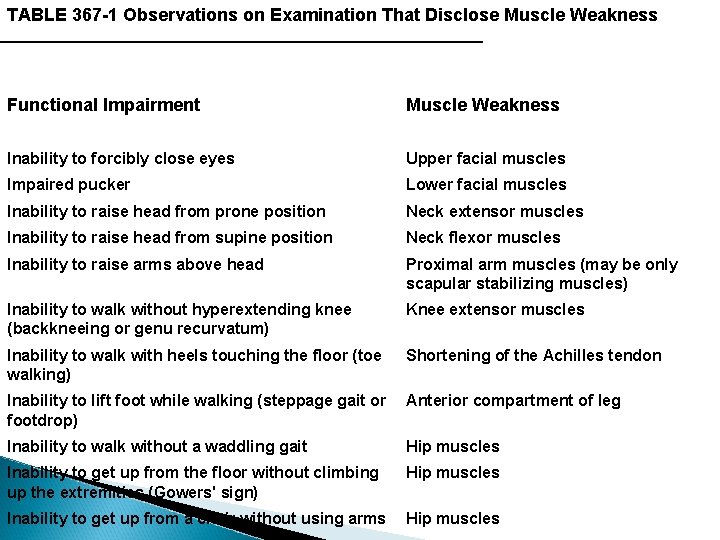
TABLE 367 -1 Observations on Examination That Disclose Muscle Weakness Functional Impairment Muscle Weakness Inability to forcibly close eyes Upper facial muscles Impaired pucker Lower facial muscles Inability to raise head from prone position Neck extensor muscles Inability to raise head from supine position Neck flexor muscles Inability to raise arms above head Proximal arm muscles (may be only scapular stabilizing muscles) Inability to walk without hyperextending knee (backkneeing or genu recurvatum) Knee extensor muscles Inability to walk with heels touching the floor (toe walking) Shortening of the Achilles tendon Inability to lift foot while walking (steppage gait or footdrop) Anterior compartment of leg Inability to walk without a waddling gait Hip muscles Inability to get up from the floor without climbing up the extremities (Gowers' sign) Hip muscles Inability to get up from a chair without using arms Hip muscles
Muscle pain (myalgia), cramps, and stiffness - not a feature of most primary muscle diseases Cramp: painful, involuntary, localized, muscle contraction with a visible or palpable hardening of the muscle. : often occur in neurogenic disorders/ motor neuron diseases, radiculopathies, polyneuropathies/ : common in patients with Duchenne MD : firing of MUAPs at a rate of 40 -60 Hz, with abrupt onset & cessation Myalgia: localized or generalized and may be accompanied by tenderness & swelling. : should be differentiated from myofascial pain syndromes Fibromyalgia ▪ polymyalgia rheumatica - have specific trigger points - in patients > 50 yrs of age - easy fatiguability - stiffness & pain in the shoulders, - sleep disturbances lower back, hips, and thighs - serum CK & ESR are normal - ESR elevated - CK, EMG & muscle biopsy are N
stiffness Uncommon Joint inflammation Hyperexcitable motor nerves( spinal cord, peripheral nerves) contracture Muscle unable to relax after an active muscle contraction EMG shows complete electrical silence ( firing of motor neurons in a cramp) Uncommon in most muscle diseases Fixed contracture occurs early in patients with Emery- Dreifuss MD & Bethlem myopathy.
▪ dark or dark- brown urine myoglobinuria Myotonia prolonged muscle contraction followed by slow muscle relaxation voluntary contraction, mechanical stimulation ( percussion myotonia) DM, myotonia congenita, paramyotonia congenita Muscle enlargement and atrophy Size of muscle is usually not affected. Enlarged cuff muscles are typical Duchenne & Becker MDs. Can also result from infiltration by sarcoid granulomas , amyloid deposits, bacterial and parasitic infections, and focal myositis.
Laboratory evaluation v Diagnose myopathy Serum enzymes - ALT, AST, LDH, Aldolase : found in both skeletal muscle & liver : elevated GGT helps to establish a liver origin. - CK ( CKMM) : preferred enzyme to measure in the evaluation of myopathies. Electrodiagnostic studies - NCS, Repetitive nerve stimulation : help to differentiate myopathies from neuropathies & NMJ disorders. - EMG : diagnose myopathy, helps also to choose an appropriately affected muscle for biopsy. - Myopathic EMG: low amplitude, short duration & polyphasic MUPs - inflammatory myopathies : increased spontaneous activity, irritability on needle placement. - myotonic discharges : sustained run of positive sharp waves : sustained run of negative spikes
v Diagnose specific types of myopathies Forearm exercise test - place a small indwelling catheter in to an antecubital vein & obtain baseline blood sample for lactic acid and ammonia. - the fore arm muscles are exercised by asking the patient to vigorously squeeze a sphygmomanometer bulb for 1 min. -blood is then obtained at intervals of 1, 2, 4, 6 & 10 min. for comparison with the baseline. Both rise with exercise. - Glycolytic defects : lactic acid rise is absent or below normal while rise in ammonia will reach control values. - myoadenylate deaminase deficiency: selective failure to increase ammonia.
DNA analysis - for definite diagnosis of certain muscle disorders associated with gene defects ( deletions or mutations ). Muscle biopsy - safe diagnostic procedure in establishing the final diagnosis of suspected myopathy. - different techniques of microscopic evaluation ( histochemistry, immunohistochemistry with a battery of antibodies, electron microscopy) - site : muscle selected for biopsy should have mild to moderate muscle weakness. : not performed on a muscle that has been injured by a previous trauma, injections, EMG needles( within 4 -6 weeks after EMG ) - common muscles used for biopsy : proximal – Biceps, Triceps, Quadriceps : Distal – Extensor carpi radialis, Anterior tibialis
Approach to the patient Emergency: manage acute life threatening complications Respiratory insufficiency : mechanical ventilator Dysphagia : endotracheal intubation Rhabdomyolysis : hydration, diuresis Heart block : pace maker insertion Hypo. KPP : iv. Or oral potassium replacement Non-emergency : identify a disorder as a myopathy : identify a specific etiology for the myopathy v History - symptoms : muscle weakness, presence or absence of sensory complaints , acuity of symptom onset - family history of muscle weakness, frontal baldness - personal history of autoimmune disease , endocrinopathy, renal insufficiency, alcoholism - Previous history of severe weakness, particularly any that occurred after exercise, exposure to cold temperatures, eating high CHO diets - history of medication use
v Physical examination rash - objective weakness fever ( polymyositis ) muscle tenderness muscle mass : atrophy is a very late sign skin examination : Gottron’s papule, heliotrope - level of consciousness : usually normal - sensory perception : normal - DTR : usually normal : may be absent or diminished in Hypo. KPP v Laboratory tests : CBC, ESR, CK isoenzymes, electrolytes, U/A serum myoglobin, RFT, TFT Definitive diagnosis : EMG, Genetic testing, ANA, Muscle enzyme muscle biopsy
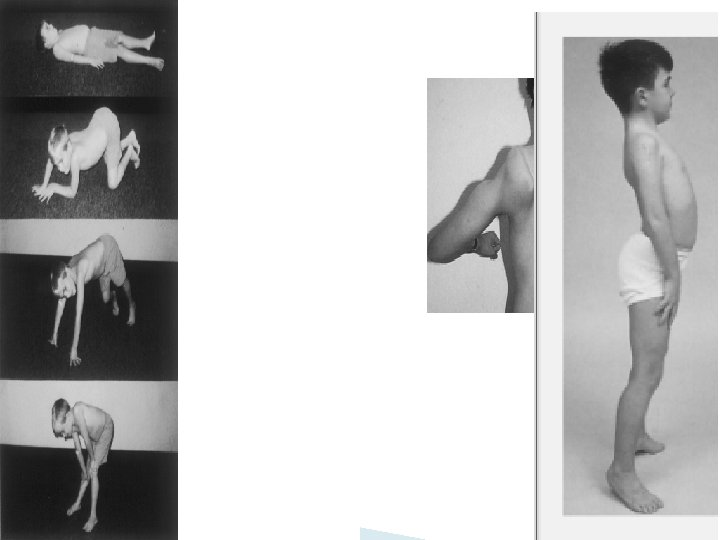
Muscular dystrophies Group of inherited disorders characterized by progressive degeneration of groups of muscles, sometimes with involvement of the heart muscle or conducting tissue, and other parts of the nervous system. Classified based on the age at onset, distribution of affected muscles and pattern of inheritance. Duchenne muscular dystrophy Inheritance- X- linked recessive disorder Defective gene- Dystrophin Onset- usually b/n 3 -5 yrs age C/F – progressive weakness of the girdle muscles - difficulty running , jumping, hopping, unable to get up from the floor (Gower’s maneuver) - toe walking is associated with lordotic posture - contractures( hip, knee, elbow, wrist) with chest deformities →severe pulmonary infections → death at age 16 -18 yrs
Others : cardiomyopathy , mental retardation Lab. – Serum CK : elevated 20 -100 x normal - EMG : myopathic features - Muscle biopsy: muscle fibers of varying size as well as small groups of necrotic and regenerating fibers. : deficiency of dystrophin seen on western blot analysis & immunohistochemical staining. - DNA analysis : mutation of gene that encodes dystrophin Treatment : prednisolone 0. 75 mg/kg/day increases muscle strength & slows the progression of disease for up to 3 yrs.
Becker muscular dystrophy Inheritance – X- linked recessive disorder Defective gene – dystrophin Onset- experience difficulty b/n 5 - 15 yrs of age C/F – proximal muscles especially of lower extremities are prominently involved. - hypertrophy of muscles , particularly the calves, is an early & prominent finding. - cardiomyopathy may occur , MR is less common Lab. – CK : elevated - EMG : myopathic - muscle biopsy : similar to DMD : reduced amount or abnormality of dystrophin( Dx) - DNA analysis : deletions or duplications( Dx) Treatment – supportive Survival : survive in to the 4 th to 5 th decade
Limb- girdle muscular dystrophy/ LGMD / Inheritance : Autosomal dominant/ recessive Defective gene : several genes M: F – 1: 1 Onset – late 1 st to 4 th decade C/F – progressive weakness of pelvic & shoulder girdle muscles - diaphragmatic weakness & cardiomyopathy may also occur - intellectual function is intact Treatment - supportive
Emery- Dreifuss muscular dystrophy/EDMD/ Inheritance- X-linked recessive/ Autosomal dominant Defective gene : Emerin/ Lamins A/C Onset – early childhood & teenage years C/F – prominent and early contractures ( elbows, neck) often preceding muscle weakness. - muscle weakness is in a limb- girdle distribution - dilated cardiomyopathy may occur and may result in sudden death, arrhythmia, & conduction defects. ▪ Lab. - CK : 2 -10 x ed - EMG : Myopathic - Biopsy : non-specific dystrophic features Treatment - supportive : Ambulatory aid : manage cardiomyopathy & arrhythmia
Fascioscapulohumeral /FSH/ muscular dystrophy Inheritance: AD Onset : childhood or young adulthood Defective gene: deletion, distal 4 q C/F- facial weakness: initial manifestation - weakness of shoulder girdle muscles : weak arm elevation : scapular winging - weak wrist extension > wrist flexion - foot drop : weakness of anterior compartment muscles of the legs - weakness of the pelvic girdle muscles : 20% - other organ ( rarely) : labile HTN, nerve deafness Lab. – CK : N or elevated - EMG: myopathic pattern - biopsy: non-specific features of myopathy Treatment – no specific treatment is available - ankle foot orthoses may help for foot drops - scapular stabilization procedures may improve scapular winging
Oculopharyngeal dystrophy Inheritance: AD with complete penetrance Defective gene: expansion, poly-A-RNA binding protein Onset – usually late onset ( 4 th – 5 th decade ) C/F – progressive external ophthalmoplegia ( slowly progressive ptosis, limitation of eye movements with sparing of pupillary rxns. - dysphagia : can be life threatening : may result in repeated episodes of aspiration - mild weakness of the neck and extremities Lab. – EMG: myopathic features - CK : 2 -3 x N - biopsy : distinct features – presence of tubular filaments in muscle cell nuclei. Treatment- Dysphagia : cricopharyngeal myotomy may improve swallowing - Ptosis : eyelid crutches may improve vision
Distal myopathies Notable for their preferential distribution of muscle weakness in contrast to most muscle conditions associated with proximal weakness Four types : mode of inheritance, age of onset, pattern of weakness 1. Welander DM : AD 2. Tibial MD : AD - late onset, usually after age 40; start in the hands 3. Nonanka DM: AR 4. Miyoshi myopathy : AR - early onset in late teens or twenties; start in the lower limbs Lab. – CK : only slightly elevated except in Miyoshi myopathy - Biopsy : non- specific dystrophic changes - EMG : myopathic Treatment – occupational therapy for loss of hand function - Ankle - foot orthoses to support distal lower limbs
Myotonic dystrophy/ DM / Inheritance : AD Defective gene: two types with distinct molecular genetic defects -DM 1 : expansion CTG repeat - DM 2 ( proximal myotonic myopathy – PROMM ): CCTG repeat C/F – myotonia : usually appears by age 5 yrs - Hatchet- faced appearance: temporalis , masseter , facial muscle atrophy & weakness - frontal baldness in men - foot drop : ankle dorsiflexor weakness - weakness of wrist extensors , finger extensors, & intrinsic hand muscles - early involvement of neck muscle flexors, sternocleidomastoids - dysarthritic speech, nasal voice, swallowing problems due to palatal , pharyngeal, and tongue involvement - respiratory insufficiency : diaphragm & intercostal muscle involvement - cardiac disturbances : conduction block with sudden death
Cont, d Hatchet-faced appearance
- other system manifestations : intellectual impairment, hypersomnia, cataract, gonadal atrophy, insulin resistance, reduced esophageal & colonic motility Lab. – Dx ; usually based on clinical findings - CK : N or mildly elevated - EMG : evidence of myotonia - Biopsy : atrophy which selectively involves type – 1 fibers in 50% Treatment – treat myotonia : membrane stabilizing agents : phenytoin is preferred - pacemaker for advanced conduction block - molded ankle foot - orthoses help prevent foot drop in patients with distal lower extremity weakness.
Congenital myopathy Rare disorders distinguished from muscular dystrophies by the presence of specific histochemical & structural abnormalities in muscle fibers. Onset : infancy or childhood Three types: pattern of inheritance & type of structural abnormality in muscle fibers -central core disease : AD - Nemaline (rod ) myopathy: AD - Myotubular( centronuclear ) myopathy : AD , XR C/F - progressive muscle weakness ( proximal> distal, legs> arms) & limpness, hypotonia & delayed milestones /walking/ - skeletal deformities (kyphoscoliosis, club foot, hip dislocation) Lab. - CK: usually N or slightly elevated - EMG : myopathic/ mostly/; positive sharp waves, myotonic discharges - Biopsy : features specific to each type Treatment – no specific treatment
Disorders of muscle membrane excitability/chanellopathies/ Inherited abnormalities (mutations) of the Na+, Ca+2, K+, Cl- ion channels in striated skeletal muscles. C/F- various syndromes of familial periodic paralysis affecting proximal muscles more than distal, mostly sparing ocular , bulbar and respiratory muscles. : long term repeated attacks may result in fixed proximal weakness. - myotonia : paradoxic in PC (aggravated by exercise ) : Hyper. KPP ( K+ -aggravated myotonia) , few cases of Hypo. KPP Inheritance – AD except few sporadic cases Recognized by their : clinical characteristics : provocation by exercise, eating , cold exposure, and associated changes : serum potassium concentration during an attack
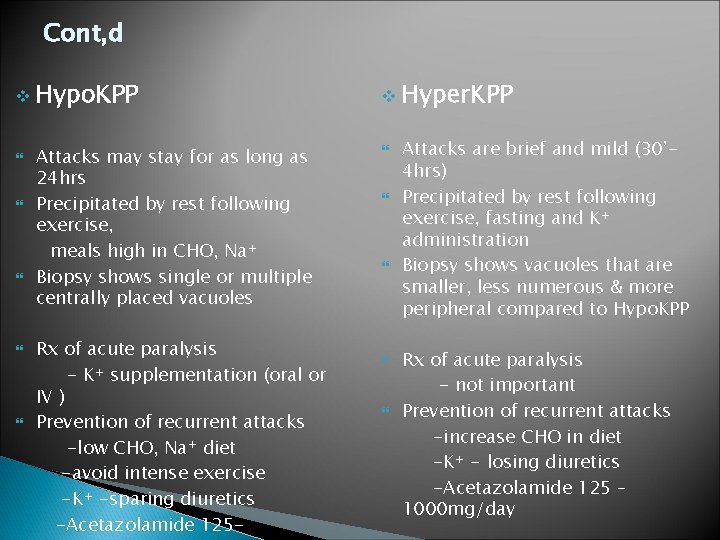
Cont, d v Hypo. KPP Attacks may stay for as long as 24 hrs Precipitated by rest following exercise, meals high in CHO, Na+ Biopsy shows single or multiple centrally placed vacuoles Rx of acute paralysis - K+ supplementation (oral or IV ) Prevention of recurrent attacks -low CHO, Na+ diet -avoid intense exercise -K+ -sparing diuretics -Acetazolamide 125 - v Hyper. KPP Attacks are brief and mild (30’ 4 hrs) Precipitated by rest following exercise, fasting and K+ administration Biopsy shows vacuoles that are smaller, less numerous & more peripheral compared to Hypo. KPP Rx of acute paralysis - not important Prevention of recurrent attacks -increase CHO in diet -K+ - losing diuretics -Acetazolamide 125 – 1000 mg/day
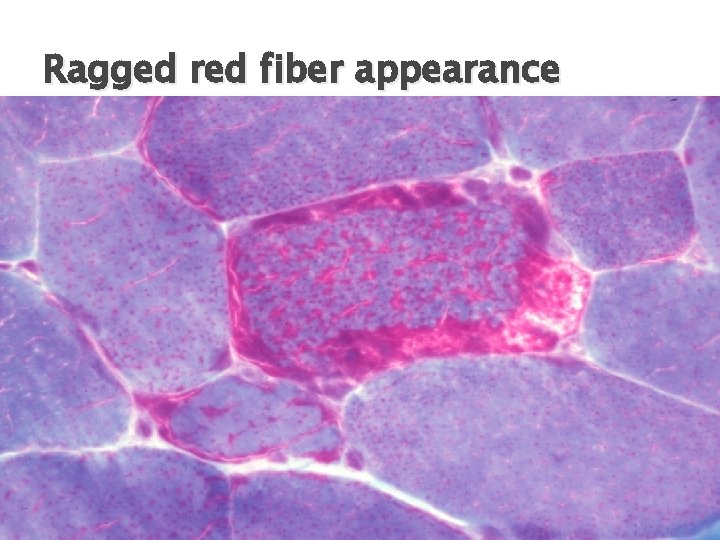
Mitochondrial myopathies Mitochondria plays a key role in energy production Inherited disorders of the oxidative pathways of the respiratory chain. Onset : most in childhood or early adulthood Lab. - CK : usually N or slightly ed - Serum lactate : usually ed - EMG : myopathic - NCS : neuropathic features in some with peripheral neuropathy - Biopsy : modified trichrome stain - ‘ragged red fiber ‘ appearance : electron microscopy - muscle fibers with significant numbers of abnormal mitochondria Structures affected: skeletal muscles, CNS, endocrine glands, heart Course : progressive & downhill Treatment : supportive - exercise - pace maker insertion for heart block - treat epilepsy
Ragged red fiber appearance courtesy : Prof. Janzer
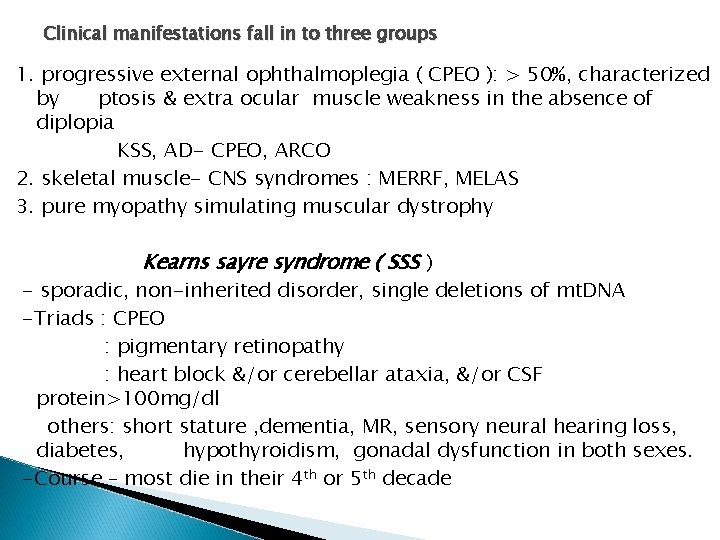
Clinical manifestations fall in to three groups 1. progressive external ophthalmoplegia ( CPEO ): > 50%, characterized by ptosis & extra ocular muscle weakness in the absence of diplopia KSS, AD- CPEO, ARCO 2. skeletal muscle- CNS syndromes : MERRF, MELAS 3. pure myopathy simulating muscular dystrophy Kearns sayre syndrome ( SSS ) - sporadic, non-inherited disorder, single deletions of mt. DNA -Triads : CPEO : pigmentary retinopathy : heart block &/or cerebellar ataxia, &/or CSF protein>100 mg/dl others: short stature , dementia, MR, sensory neural hearing loss, diabetes, hypothyroidism, gonadal dysfunction in both sexes. -Course – most die in their 4 th or 5 th decade
Cont, d Myoclonic Epilepsy with Ragged Red Fibers/ MERRF/ Point mutation of mitochondrial transfer RNA C/F - myoclonic epilepsy: integral part & may be the initial symptom - cerebellar ataxia : progressive, both trunks & the limbs - progressive muscle weakness : limb- girdle distribution others: dementia, optic atrophy, peripheral neuropathy, hearing loss , Diabetes Rx- supportive with special attention to epilepsy
Cont, d Mitochondrial myopathy, Encephalopathy, Lactic acidosis, Stroke-like episodes / MELAS / Most common encephalomyopathy Maternally inherited point mutations of mt. RNA gene C/F - partial or generalized seizures : could be the 1 st sign - stroke- like Sxs- hemiparesis, hemianopia, cortical blindness - serum lactic acid : typically ed others : dementia, hearing loss, hypothyroidism, diabetes, hypothalamicpituitary dysfunction Neuroimaging : basal ganglia calcifications in high percentage of cases Treatment – supportive , fatal outcome
Cont, d Pure myopathy syndrome C/F – muscle weakness and fatigue which makes differentiation from muscular dystrophies difficult. Onset - usually neonatal, occasionally at a later age - weakness, hypotonia, delayed milestones & death before age 2 yrs Treatment – supportive care similar to muscular dystrophies
Disorders of muscle energy metabolism Abnormalities in either glucose or lipid utilization Presentation : acute painful syndromes with rhabdomyolysis & myoglobinuria dystrophies : chronic progressive muscle weakness simulating
v Disorders of glycogen storage causing progressive muscle weakness C/F – usually present during infancy - severe muscle weakness, delayed milestones, , cardiomegally, hepatomegally, respiratory insufficiency - death usually occurs by 1 yr of age Three types: 1. Debranching enzyme deficiency 2. Branching enzyme deficiency 3. Acid maltase deficiency – commoner, AR inheritance -can present during adulthood ( heart & liver not involved) -respiratory failure & diaphragmatic weakness are often initial manifestations, heralding progressive proximal weakness Dx- membrane bound & free tissue glycogen on electron microscopy - definitive diagnosis through enzyme determination in muscle Rx. – recombinant enzyme replacement may improve muscle weakness & prolong life.
v Disorders of glycolysis causing exercise intolerance Defects in genes encoding the abnormal proteins. Effects: failure to support energy production at the initiation of exercise Onset : adolescence C/F – painful muscle contractures followed by myoglobinuria - Sxs are precipitated by brief bursts of high intensity exercise such as running or lifting heavy objects 5 types : Myophosphorylase deficiency ( Mc. Ardle’s disease ) - most common , AR inheritance Lab. - CK : >100 x elevated accompanying myoglobinuria - U/A : myoglobinuria - Fore arm exercise test : impaired rise in venous lactate Definitive diagnosis : muscle biopsy Treatment : exercise tolerance can be enhanced by training / warmup to brief periods of rest / : training allows start of ‘ 2 nd wind’ phenomenon / switching to utilization of fatty acids/
v Disorders of lipid metabolism Oxidation of fatty acids occurs through a multi-step process Carnitine deficiency Primary: AD Secondary : ↓ed synthesis/cirrhosis/, insufficient intake /parentral nutrition/, excessive loss/renal dialysis/ Onset: childhood C/F- progressive generalized proximal muscle weakness - severe cardiomyopathy may occur Lab. – CK : mildly or markedly ed - Biopsy : striking lipid accumulation Treatment : not satisfactory : supplementation, steroid may help some Ø
Ø Carnitine palmitoyltransferase deficiency Most common cause of recurrent myoglobinuria Cause : CPT-II deficiency Inheritance : AR ; but commoner in men / 5: 1 / Onset – teenage years or early childhood C/F – muscle pain & myoglobinuria : following prolonged exercise, some times following fasting : doesn’t occur until the limits of utilization have been exceeded & muscle breakdown has already begun unlike glycolytic defects - strength is normal in b/n attacks unlike carnitine deficiency. Lab. - CK, EMG usually N b/n attacks - forearm exercise test : normal rise of venous lactate - muscle biopsy : usually N Dx. - direct measurement of muscle CPT-II Rx. - frequent meals /low fat, high CHO/ may prolong exercise tolerance
Endocrine and metabolic myopathies Many cause weakness Fatigue is more common than weakness Cause : not well defined : ? Disease of muscle or ? another part of the motor unit - CK : usually N , except in hypothyriodism - muscle histology : atrophy rather than destruction of the muscle fibers Rx- nearly all respond to treatment
Thyroid disorders Hypothyroidism -muscle weakness with muscle cramps, pain & stiffness in 1/3 rd - prolonged relaxation phase of muscle stretch reflexes -Hoffman’s syndrome: muscle enlargement ( unknown cause), &weakness with muscle stiffness -CK- usually >10 x ed -Biopsy : normal Hyperthyroidism -proximal weakness with atrophy -sometimes bulbar, respiratory & esophageal muscle involvement : dysphagia, dysphonia, aspiration -muscle stretch reflexes are often brisk -CK: usually N -Biopsy : atrophy of fibers Others: - thyrotoxic periodic paralysis - Grave’s ophthalmopathy : progressive ophthalmopathy, with proptosis
Cont, d Hyperparathyoidism -proximal muscle weakness, muscle wasting, brisk stretch reflexes -CK : usually N -Biopsy : varying degrees of atrophy Hypoparathyoidism - Hypocalcemia resulting in sustained tetany & muscle damage - Hypo- or areflexia - CK : may be ed Diabetes mellitus - myopathy is uncommon - rarely ischemic infarction of the thigh muscles - abrupt onset of pain, tenderness, & edema of one thigh - hard & indurated area on palpation Dx- imaging / CT, MRI / -focal abnormality in muscle Vitamin deficiency - myopathy is rare - proximal muscle weakness - CPEO - Vit. D , Vit. E deficiency
Adrenal disorders Cushing’s disease - Steroid excess causes various degrees of muscle weakness - proximal limb muscle weakness - striking muscle atrophy - Associated cushingoid appearance - CK: Usually N -Biopsy : atrophy of fibers ▪ Acromegally - Mild proximal muscle weakness without muscle atrophy Adrenal insufficiency - mild weakness with prominent fatigue - Conn’s syndrome due to persistent hypokalemia Persistent muscle weakness muscle wasting if long standing CK : may be elevated Biopsy : degenerating fibers
Toxic myopathies Direct toxicity : common : muscle breakdown, rhabdomyolysis & myoglobinuria may occur Ex. - lipid lowering agents, glucocorticoids - common Drug induced autoimmune myopathy Ex. – D-penicillamine : features similar to polymyositis Ø Lipid lowering agents all classes Sx - proximal weakness - myalgia, malaise, muscle tenderness - severe rxns : rhabdomyolysis & myoglobinuria Lab. - CK: elevated - EMG : myopathic - Biopsy : muscle necrosis Rx – cessation of drugs
cont, d Ø Glucocorticoid related Flourinated steroids ( triamcinolone, dexamethasone, bethametasone) Chronic use of steroids ( prednisolone > 30 mg/day ) Respiratory muscles could be involved Presentation 1. Chronic : proximal muscle weakness associated with cushingoid appearance : Lab. - CK , EMG are usually N - Biopsy – preferential atrophy of type – II muscle fibers : Rx – drug withdrawal 2. Acute : associated with high dose iv. glucocorticoid use ( severe asthma, COPD) : acute quadriplegia : Biopsy – distinctive loss of thin filaments by electron microscopy : Rx- drug withdrawal, supportive care, rehabilitation - recovery is slow
Cont, d Ø Zidovudine / AZT / related myopathy Mitochondrial myopathy Occurs in 17% of patients treated with doses of 1200 mg/day for 6 months. Sx. - myalgias, muscle weakness & atrophy affecting the thigh & cuff muscles Lab. - CK : elevated - EMG : myopathic - Biopsy : ragged red fibers with minimal inflammation Ø HIV- related myopathy : marked inflammation Rx – reduce dose or withdraw drug
Inflammatory myopathies Largest group of acquired & potentially treatable causes of skeletal muscle weakness Prevalence : 1 in 100, 000 Types : - Polymyositis ( PM ) - Dermatomyositis ( DM ) - Inclusion body myositis ( IBM ) Pathogenesis : Autoimmune diseases - Humeral ( autoantibodies ) : DM - nuclear antigens ( ANAs ) - cytoplasmic antigens * Anti-jo-1 antibody - T - cell mediated myotoxicity ( CD 8 cells) : PM, IBM Results – complement mediated microangiopathy & muscle ischemia → necrosis , degeneration & phagocytosis of fibers - direct injury to fibers → necrosis & phagocytosis Triggering agent - ? Endogenous antigens - ? Exogenous Ags. : viruses / HIV, CMV, EBV, Coxackie …/
Cont, d C/F – progressive , often symmetrical proximal muscle weakness - early distal muscle weakness in IBM - quadriceps atrophy with repeated falling : common in IBM - dysphagia & head drop : pharyngeal & neck flexor muscles are often involved - ocular muscles are spared - facial muscles often not involved : mild weakness common in IBM - myalgia & muscle tenderness : rarely - respiratory muscle weakness : rare - muscle wasting : untreated & long standing disease Disease progression - sub acute / weeks – months/ : DM, PM - chronic / years / : IBM
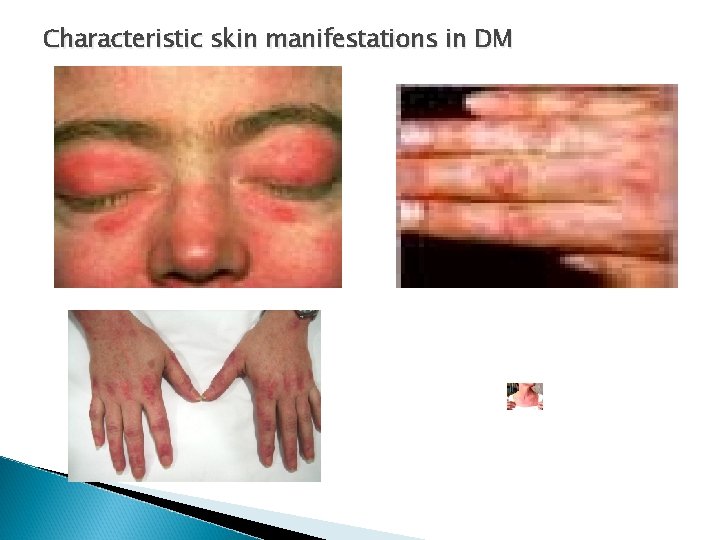
Cont, d Extramuscular manifestations - skin manifestations : DM , worsen after sun exposure * heliotrope rash * gottron’s rash * V- sign * shawl sign - systemic symptoms: fever, malaise, wt. loss, arthralgia, Raynaud’s Phen. : myopathies associated with connective tissue diseases - joint contractures : mostly in DM - dysphagia : DM, IBM - cardiac disturbances : cardiomyopathy, arrhythmias, conduction defects - subcutaneous calcifications : DM - pulmonary dyfunction : PM, DM : due to thoracic muscle weakness, ILD, drug induced pneumonitis : SOB, dry cough, aspiration pneumonia
Characteristic skin manifestations in DM
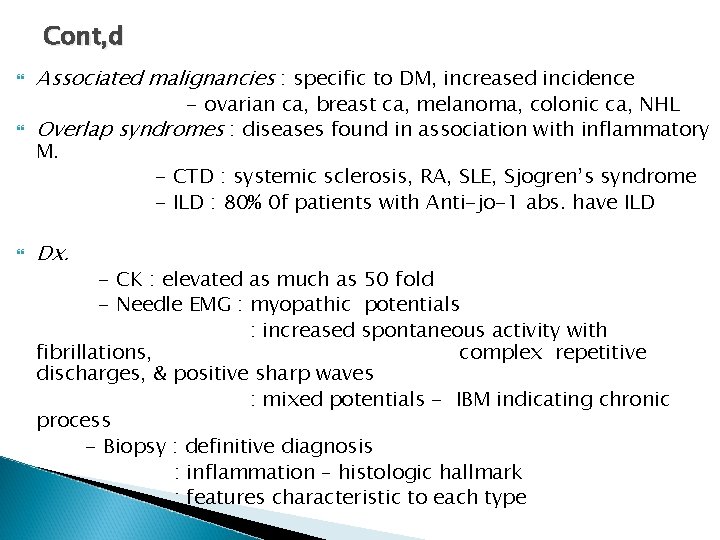
Cont, d Associated malignancies : specific to DM, increased incidence - ovarian ca, breast ca, melanoma, colonic ca, NHL Overlap syndromes : diseases found in association with inflammatory M. - CTD : systemic sclerosis, RA, SLE, Sjogren’s syndrome - ILD : 80% 0 f patients with Anti-jo-1 abs. have ILD Dx. - CK : elevated as much as 50 fold - Needle EMG : myopathic potentials : increased spontaneous activity with fibrillations, complex repetitive discharges, & positive sharp waves : mixed potentials - IBM indicating chronic process - Biopsy : definitive diagnosis : inflammation – histologic hallmark : features characteristic to each type
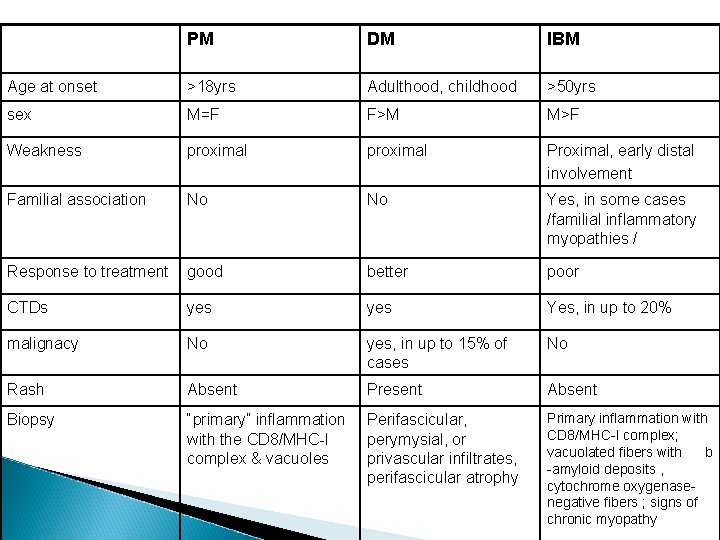
PM DM IBM Age at onset >18 yrs Adulthood, childhood >50 yrs sex M=F F>M M>F Weakness proximal Proximal, early distal involvement Familial association No No Yes, in some cases /familial inflammatory myopathies / Response to treatment good better poor CTDs yes Yes, in up to 20% malignacy No yes, in up to 15% of cases No Rash Absent Present Absent Biopsy “primary” inflammation with the CD 8/MHC-I complex & vacuoles Perifascicular, perymysial, or privascular infiltrates, perifascicular atrophy Primary inflammation with CD 8/MHC-I complex; vacuolated fibers with b -amyloid deposits , cytochrome oxygenasenegative fibers ; signs of chronic myopathy
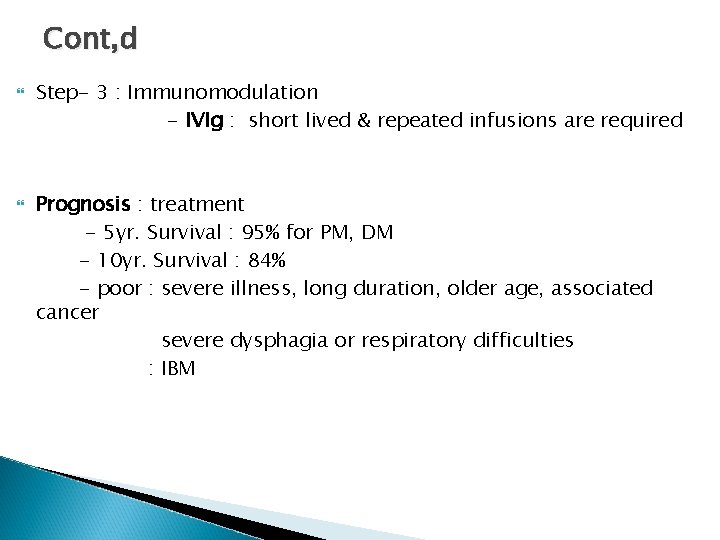
Cont, d Treatment Goal : improve muscle strength, thereby improving function in activities of daily living, and ameliorate the extramuscular manifestations( rash, dysphagia, dyspnea, fever) Response : clinical improvement : CK might remain elevated Step- 1 : high- dose prednisolone - 1 mg/kg/day : taper gradually based on the response until the lowest possible dose that controls the disease is reached Step- 2 : immunosuppressive drugs : if a patient fails to respond adequately to glucocorticoids after a 3 month trial. Ø Azathioprine – 3 mg/kg/day Ø Methotrexate – 7. 5 mg weekly with gradual dose escalation Ø Cyclophosphamide – 0. 5 mg-1 mg IV. Monthly for 6 months Ø Chlorambucil Ø Cyclosporine
Cont, d Step- 3 : Immunomodulation - IVIg : short lived & repeated infusions are required Prognosis : treatment - 5 yr. Survival : 95% for PM, DM - 10 yr. Survival : 84% - poor : severe illness, long duration, older age, associated cancer severe dysphagia or respiratory difficulties : IBM
References Harrison’s principles of internal medicine, 16 th ed. Human physiology, stuart IRA Fox, 7 th ed. Internet : E- medicine