
APLASTK ANEM Dr Yahya Bykak I HEMATOPOEZ PLURIPOTENT
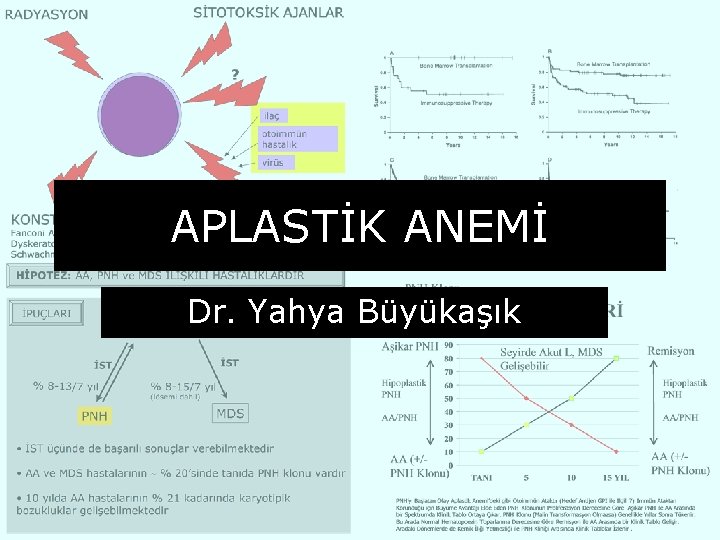
APLASTİK ANEMİ Dr. Yahya Büyükaşık

I. HEMATOPOEZ
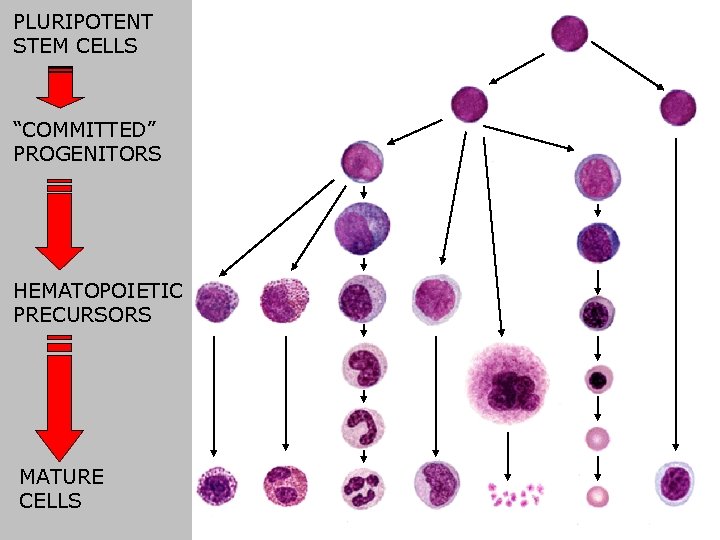
PLURIPOTENT STEM CELLS “COMMITTED” PROGENITORS HEMATOPOIETIC PRECURSORS MATURE CELLS
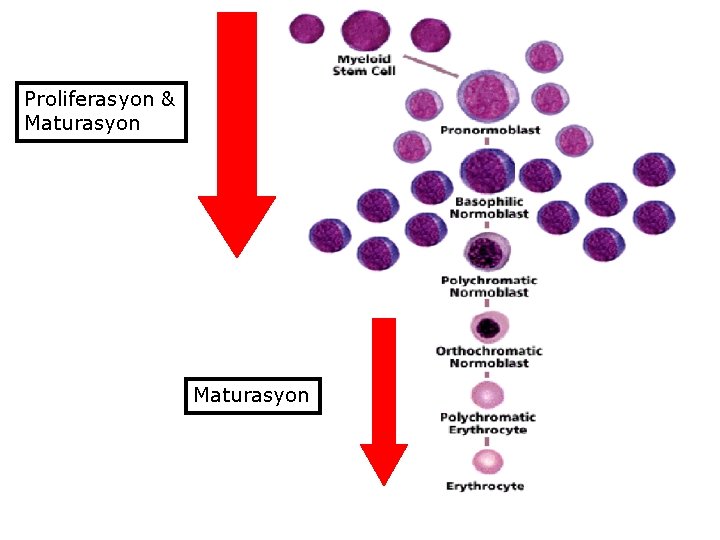
Proliferasyon & Maturasyon
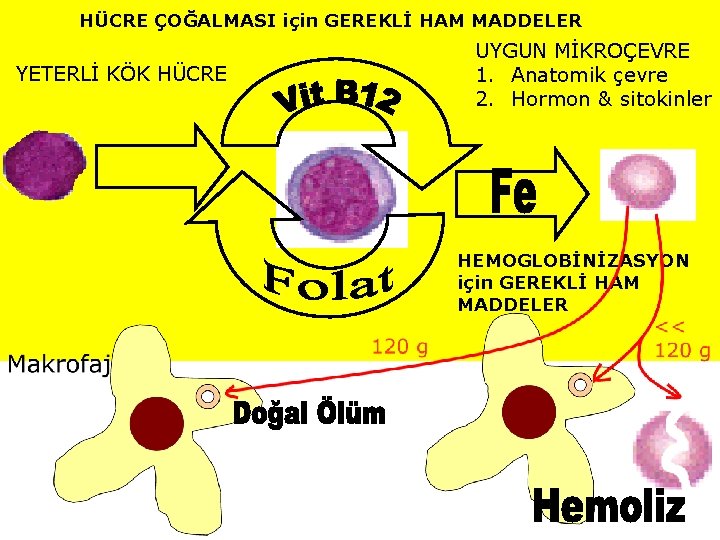
HÜCRE ÇOĞALMASI için GEREKLİ HAM MADDELER YETERLİ KÖK HÜCRE UYGUN MİKROÇEVRE 1. Anatomik çevre 2. Hormon & sitokinler HEMOGLOBİNİZASYON için GEREKLİ HAM MADDELER

II. EDİNSEL KÖK HÜCRE BOZUKLUKLARI
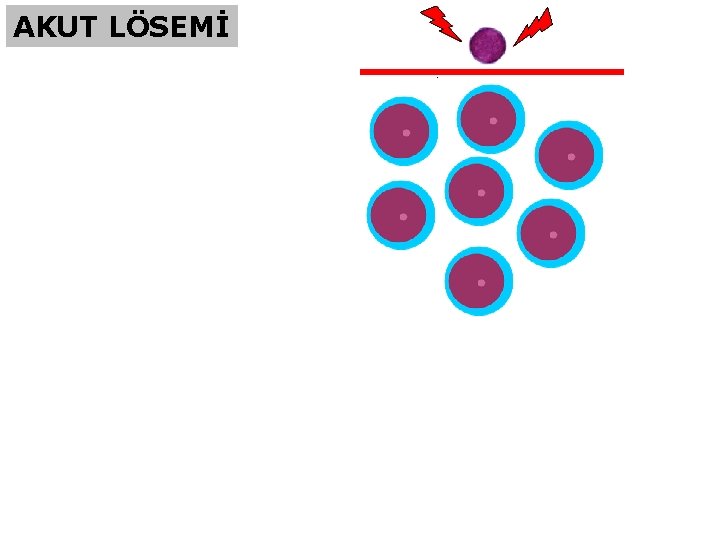
AKUT LÖSEMİ
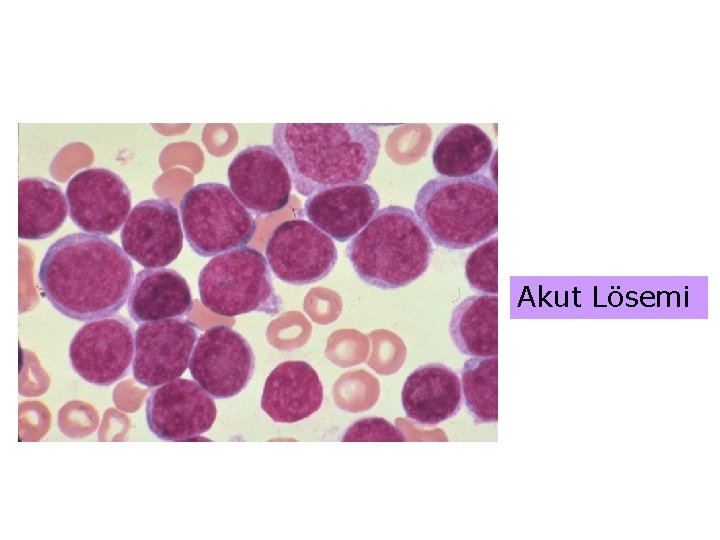
Akut Lösemi
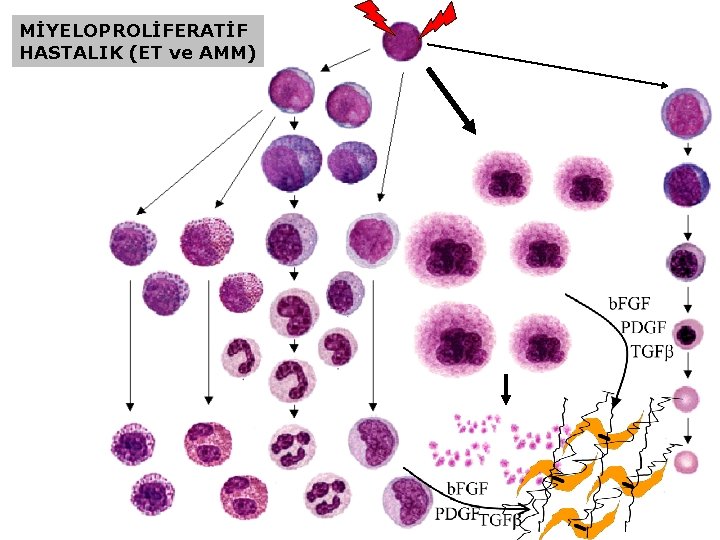
MİYELOPROLİFERATİF HASTALIK (ET ve AMM)
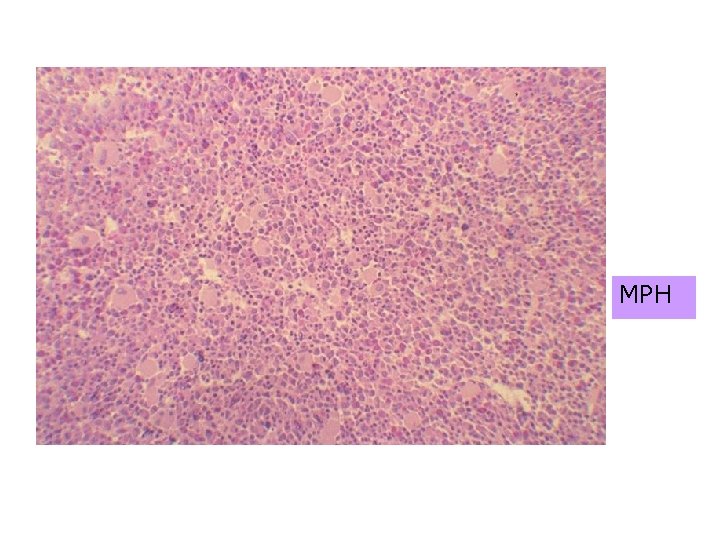
MPH

APLASTİK ANEMİ
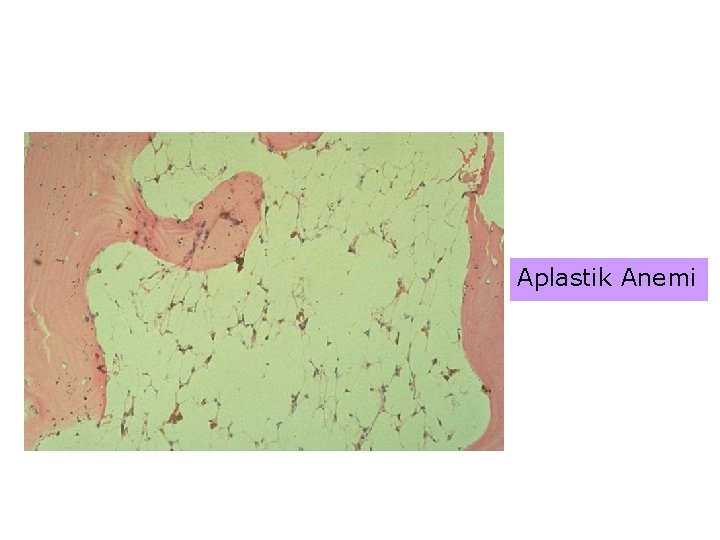
Aplastik Anemi

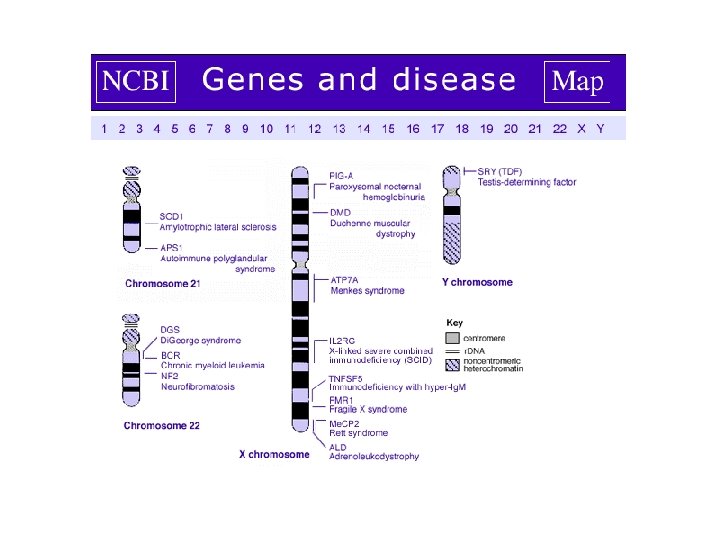
PNH ve MDS (? )

II. APLASTİK ANEMİ PATOGENEZİ

İnsidans: 2/milyon/yıl (Doğu Asya’da 2 -3 kat daha) sık
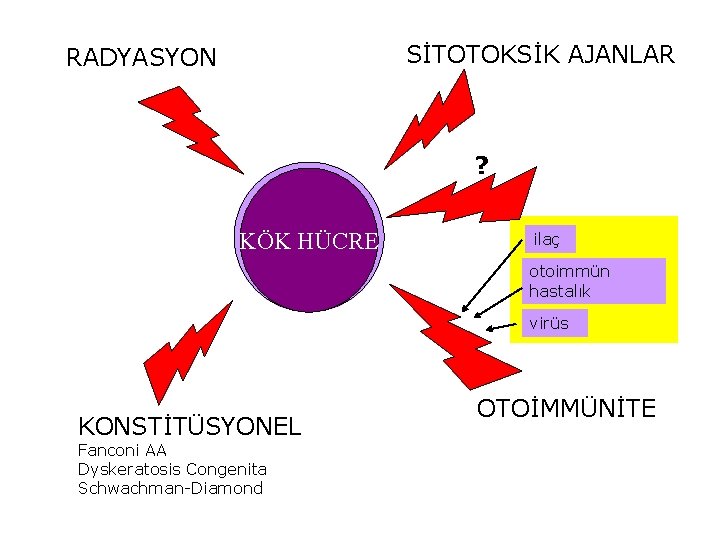
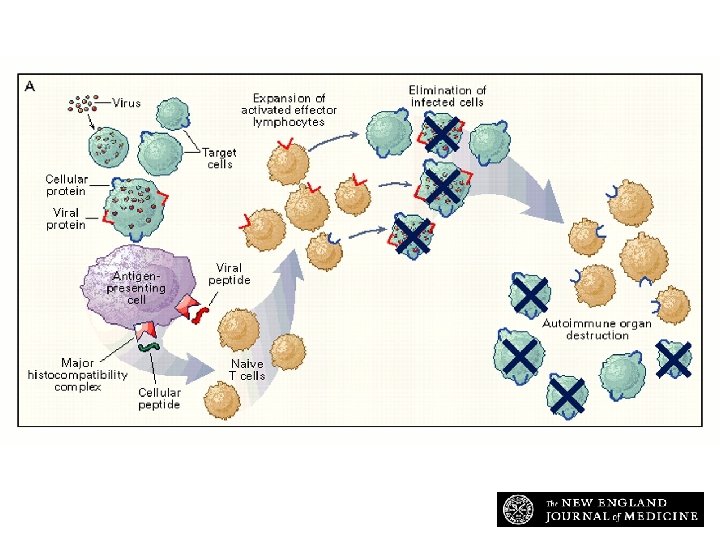
SİTOTOKSİK AJANLAR RADYASYON ? KÖK HÜCRE ilaç otoimmün hastalık virüs KONSTİTÜSYONEL Fanconi AA Dyskeratosis Congenita Schwachman-Diamond OTOİMMÜNİTE
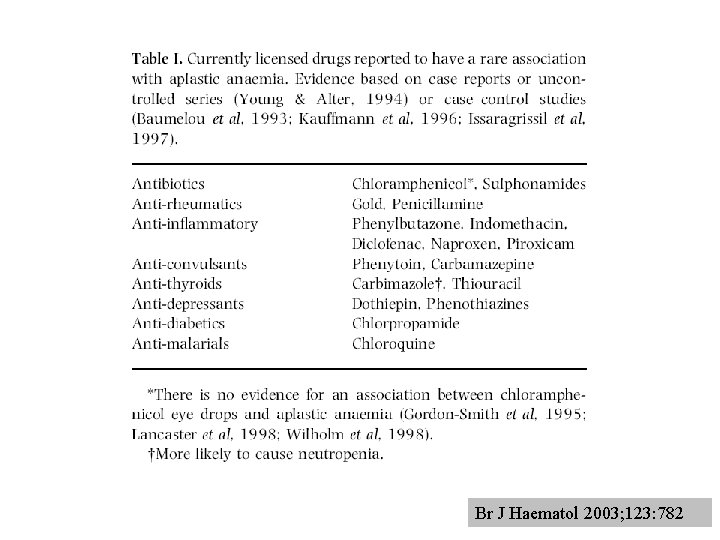
Br J Haematol 2003; 123: 782

Br J Haematol 2003; 123: 782
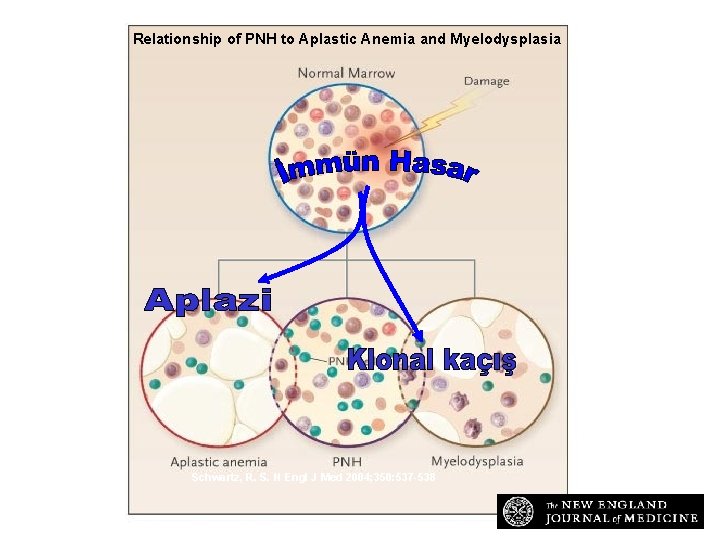
Relationship of PNH to Aplastic Anemia and Myelodysplasia Schwartz, R. S. N Engl J Med 2004; 350: 537 -538
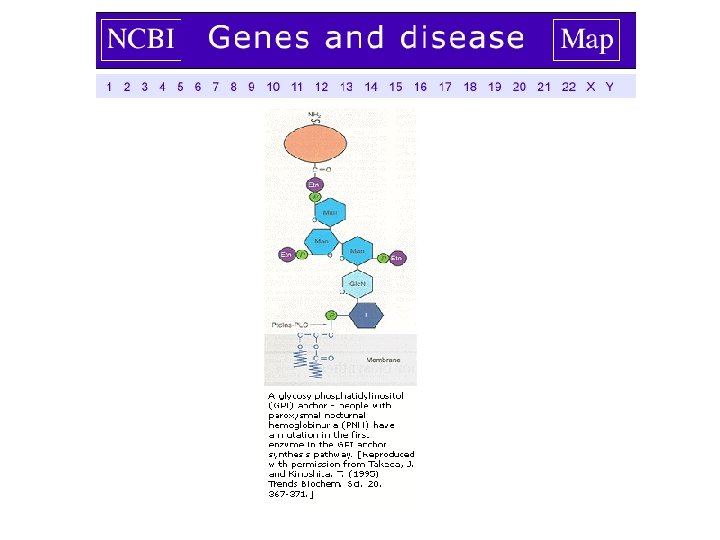
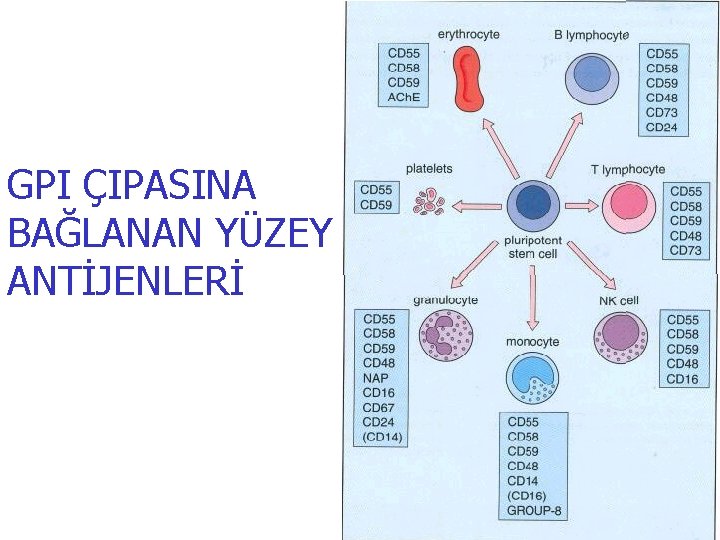
GPI ÇIPASINA BAĞLANAN YÜZEY ANTİJENLERİ
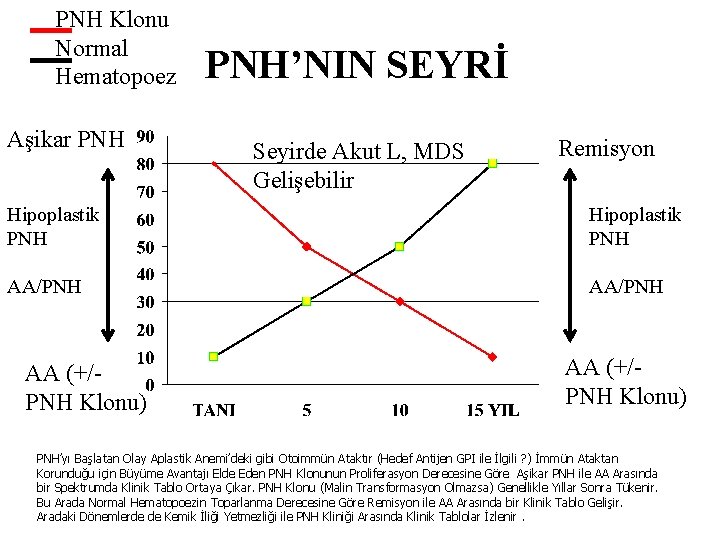
PNH Klonu Normal Hematopoez Aşikar PNH’NIN SEYRİ Seyirde Akut L, MDS Gelişebilir Remisyon Hipoplastik PNH AA/PNH AA (+/PNH Klonu) PNH’yı Başlatan Olay Aplastik Anemi’deki gibi Otoimmün Ataktır (Hedef Antijen GPI ile İlgili ? ) İmmün Ataktan Korunduğu için Büyüme Avantajı Elde Eden PNH Klonunun Proliferasyon Derecesine Göre Aşikar PNH ile AA Arasında bir Spektrumda Klinik Tablo Ortaya Çıkar. PNH Klonu (Malin Transformasyon Olmazsa) Genellikle Yıllar Sonra Tükenir. Bu Arada Normal Hematopoezin Toparlanma Derecesine Göre Remisyon ile AA Arasında bir Klinik Tablo Gelişir. Aradaki Dönemlerde de Kemik İliği Yetmezliği ile PNH Kliniği Arasında Klinik Tablolar İzlenir.
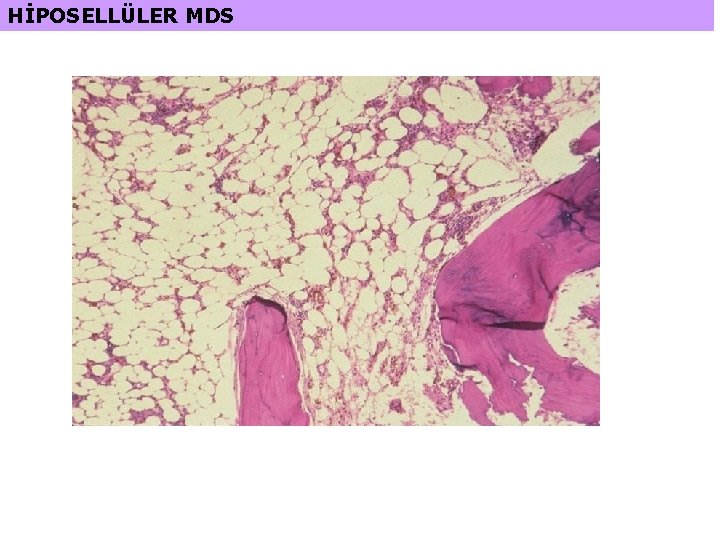
HİPOSELLÜLER MDS
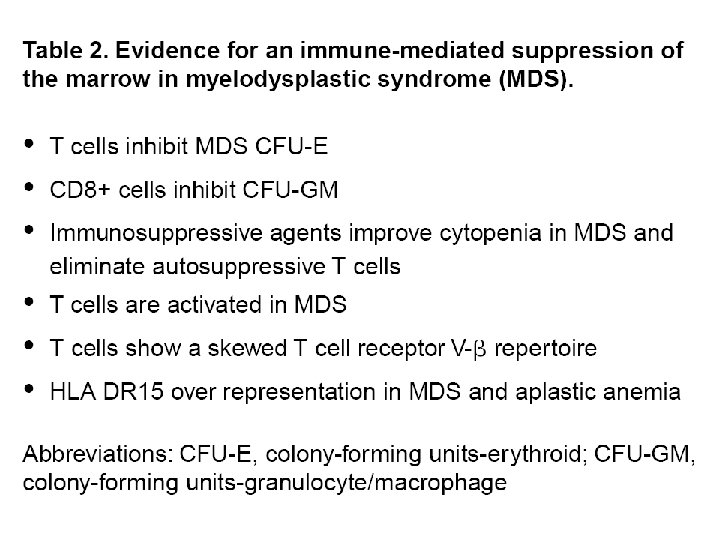
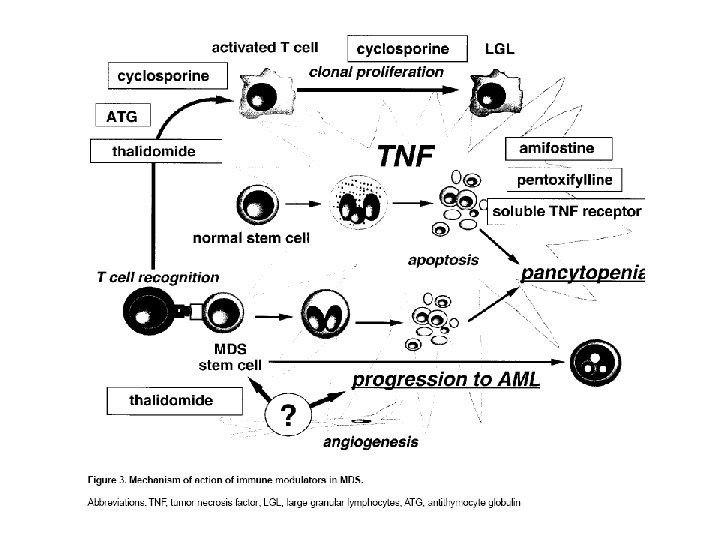
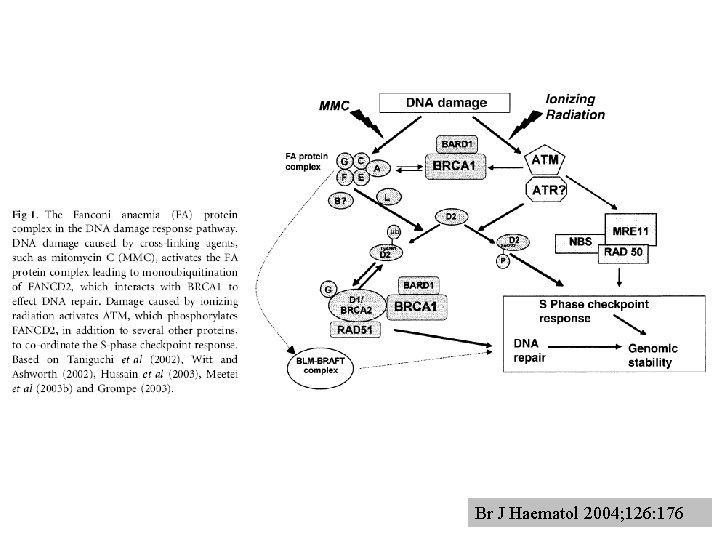
Br J Haematol 2004; 126: 176
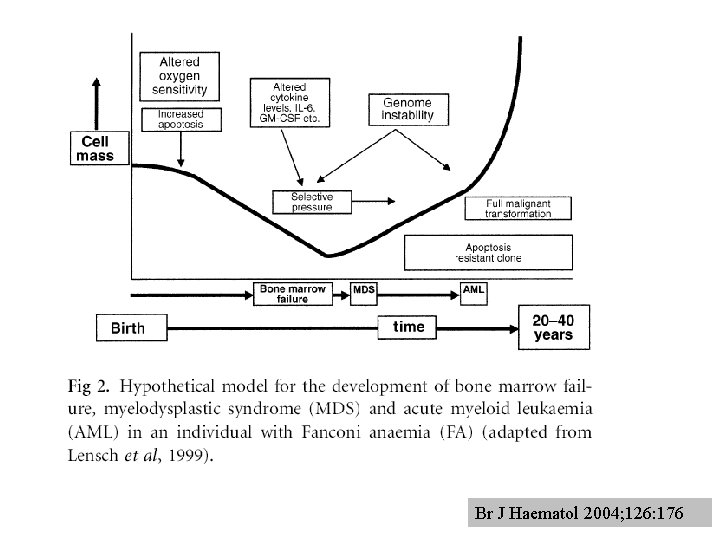
Br J Haematol 2004; 126: 176

III. NASIL TANI KONUR ?
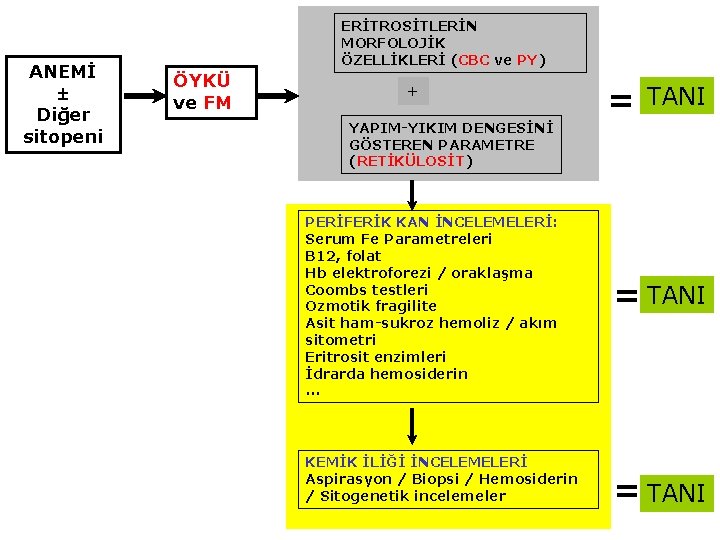
ANEMİ Diğer sitopeni ERİTROSİTLERİN MORFOLOJİK ÖZELLİKLERİ (CBC ve PY) ÖYKÜ ve FM + YAPIM-YIKIM DENGESİNİ GÖSTEREN PARAMETRE (RETİKÜLOSİT) PERİFERİK KAN İNCELEMELERİ: Serum Fe Parametreleri B 12, folat Hb elektroforezi / oraklaşma Coombs testleri Ozmotik fragilite Asit ham-sukroz hemoliz / akım sitometri Eritrosit enzimleri İdrarda hemosiderin. . . KEMİK İLİĞİ İNCELEMELERİ Aspirasyon / Biopsi / Hemosiderin / Sitogenetik incelemeler = TANI
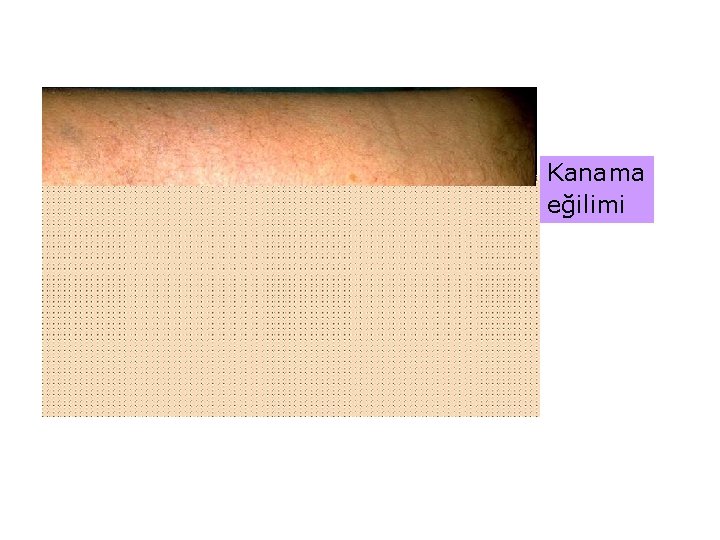
Kanama eğilimi
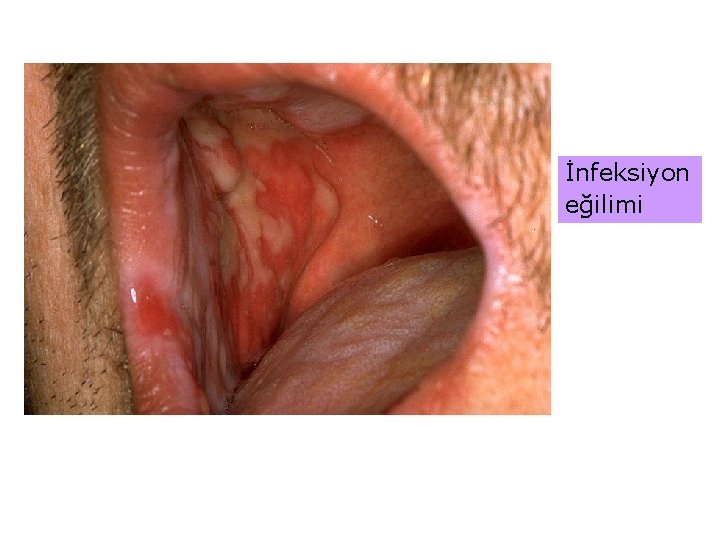
İnfeksiyon eğilimi

Solukluk

Fanconi Aplastik Anemisi • APLASTİK ANEMİ • SOMATİK BOZUKLUKLAR Büyüme geriliği Hiperpigmentasyon İskelet bozuklukları Kalp-böbrek-göz defektleri Mikrosefali Hipogonadizm • ARTMIŞ KANSER RİSKİ
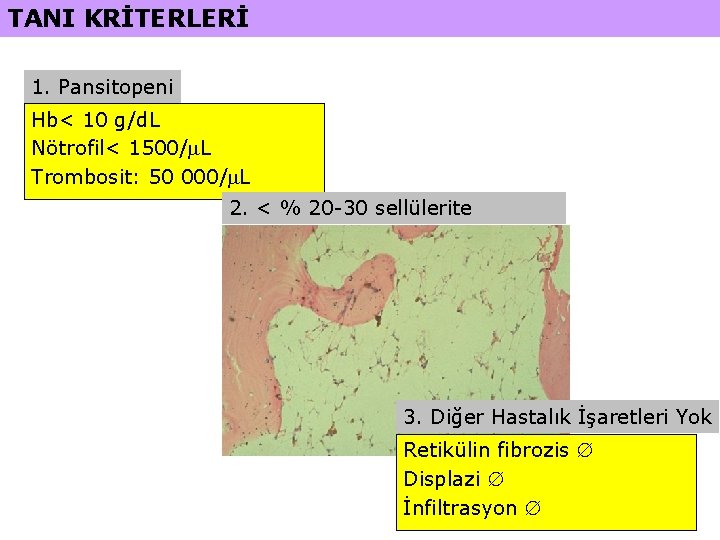
TANI KRİTERLERİ 1. Pansitopeni Hb< 10 g/d. L Nötrofil< 1500/m. L Trombosit: 50 000/m. L 2. < % 20 -30 sellülerite 3. Diğer Hastalık İşaretleri Yok Retikülin fibrozis Displazi İnfiltrasyon

KLASİK ASOSİYASYONLAR • TA-GVHD • Hemofagositik Sendrom/Aplazi • Hepatitis/Aplazi

APLASTİK ANEMİ ŞİDDETİNİN TANIMLANMASI TANIM KRİTERLER AĞIR APLASTİK ANEMİ Periferik Kanda Aşağıdakilerden İkisi: • Granülosit< 500/mm 3 • Trombosit< 20 000/mm 3 • Retikülosit< %1 (hematokrite göre düzeltilmiş) ya da <40 000/mm 3 Kemik İliği Biyopsisinde: • < % 25 sellülerite • Ya da % 25 -50 sellülerite (ancak hematopoietik hücrelerin oranları < % 30) ÇOK AĞIR Ek olarak granülosit< 200/mm 3 ve infeksiyon APLASTİK ANEMİ var
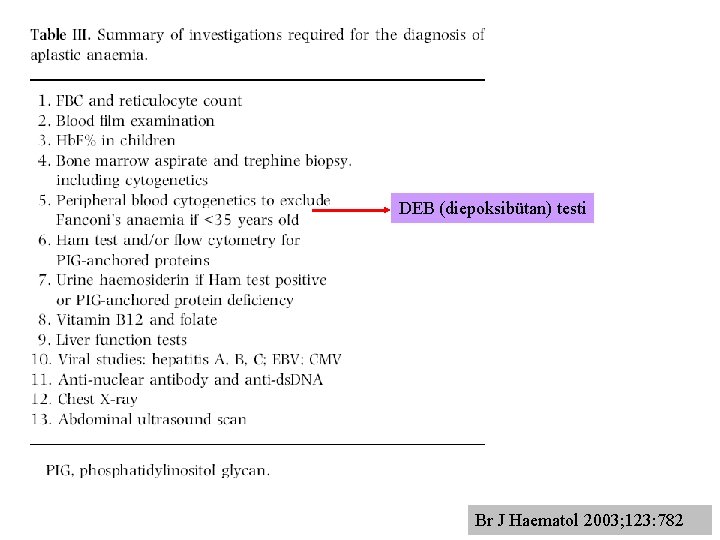
DEB (diepoksibütan) testi Br J Haematol 2003; 123: 782

IV. AYIRICI TANI
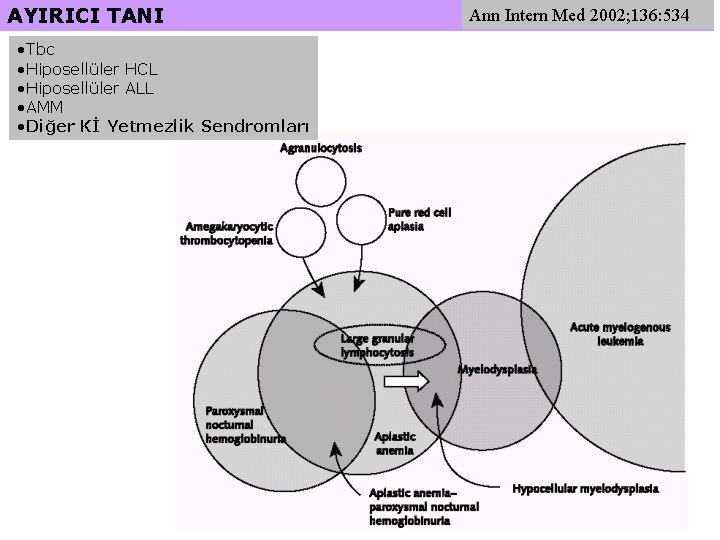
AYIRICI TANI • Tbc • Hiposellüler HCL • Hiposellüler ALL • AMM • Diğer Kİ Yetmezlik Sendromları Ann Intern Med 2002; 136: 534
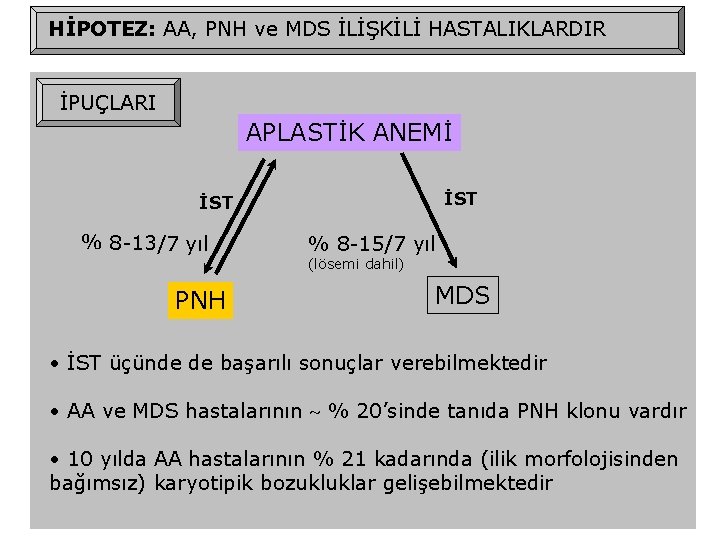
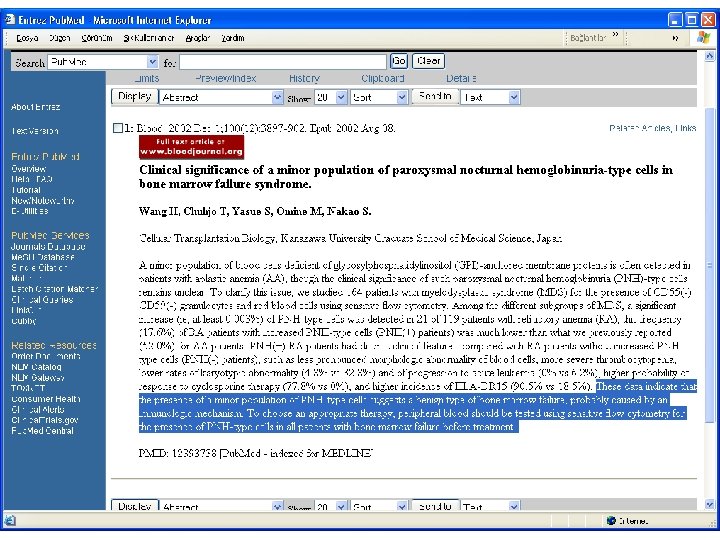
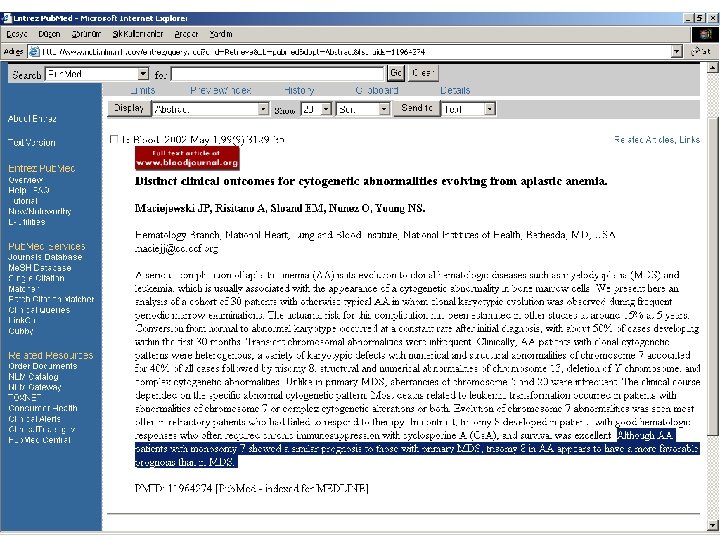
HİPOTEZ: AA, PNH ve MDS İLİŞKİLİ HASTALIKLARDIR İPUÇLARI APLASTİK ANEMİ İST % 8 -13/7 yıl % 8 -15/7 yıl (lösemi dahil) PNH MDS • İST üçünde de başarılı sonuçlar verebilmektedir • AA ve MDS hastalarının % 20’sinde tanıda PNH klonu vardır • 10 yılda AA hastalarının % 21 kadarında (ilik morfolojisinden bağımsız) karyotipik bozukluklar gelişebilmektedir
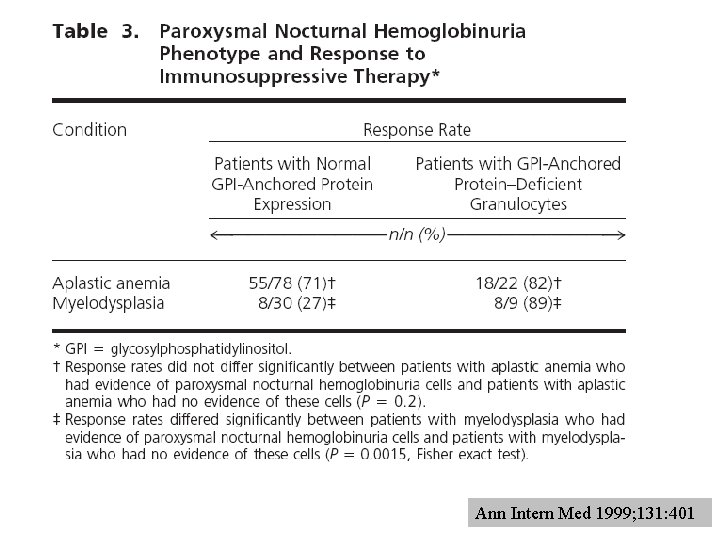
Ann Intern Med 1999; 131: 401

V. TEDAVİ: TRANSPLANTASYON ? İMMÜN SÜPRESİF TEDAVİ ?
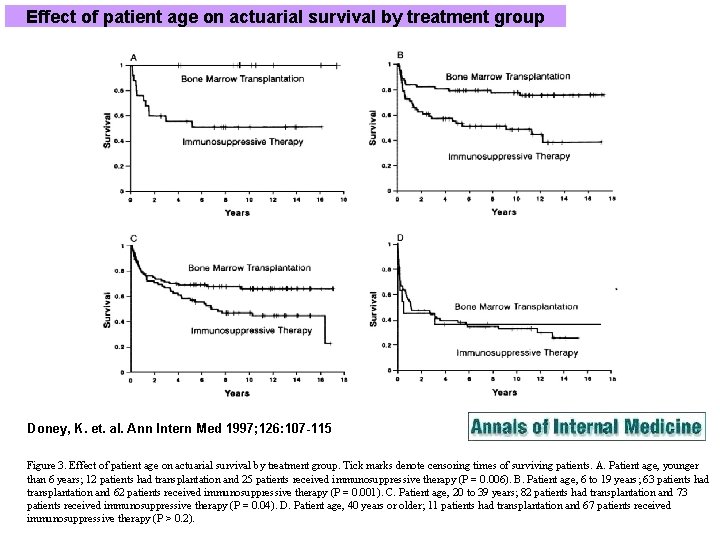
Effect of patient age on actuarial survival by treatment group Doney, K. et. al. Ann Intern Med 1997; 126: 107 -115 Figure 3. Effect of patient age on actuarial survival by treatment group. Tick marks denote censoring times of surviving patients. A. Patient age, younger than 6 years; 12 patients had transplantation and 25 patients received immunosuppressive therapy (P = 0. 006). B. Patient age, 6 to 19 years; 63 patients had transplantation and 62 patients received immunosuppressive therapy (P = 0. 001). C. Patient age, 20 to 39 years; 82 patients had transplantation and 73 patients received immunosuppressive therapy (P = 0. 04). D. Patient age, 40 years or older; 11 patients had transplantation and 67 patients received immunosuppressive therapy (P > 0. 2).
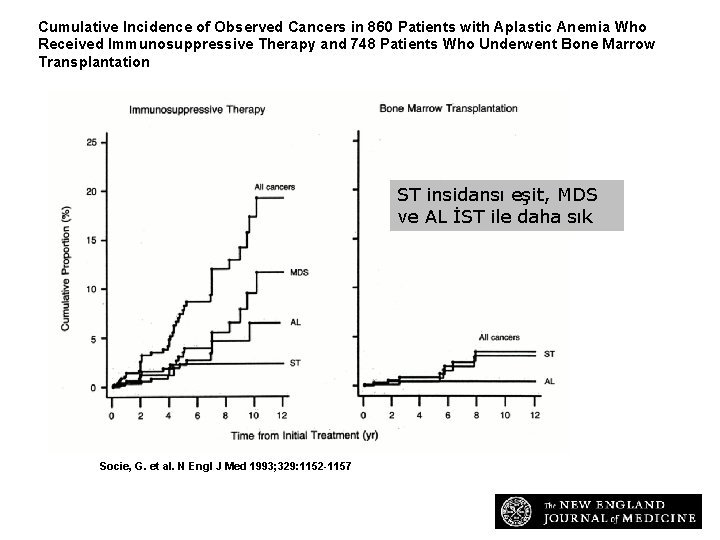
Cumulative Incidence of Observed Cancers in 860 Patients with Aplastic Anemia Who Received Immunosuppressive Therapy and 748 Patients Who Underwent Bone Marrow Transplantation ST insidansı eşit, MDS ve AL İST ile daha sık Socie, G. et al. N Engl J Med 1993; 329: 1152 -1157
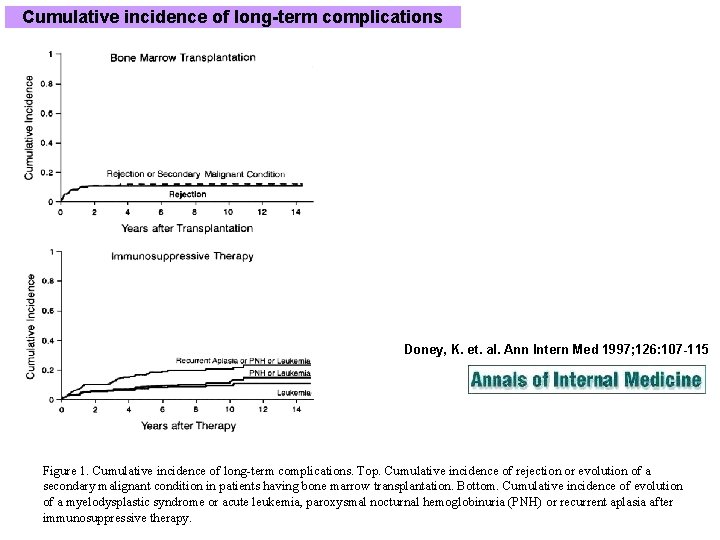
Cumulative incidence of long-term complications Doney, K. et. al. Ann Intern Med 1997; 126: 107 -115 Figure 1. Cumulative incidence of long-term complications. Top. Cumulative incidence of rejection or evolution of a secondary malignant condition in patients having bone marrow transplantation. Bottom. Cumulative incidence of evolution of a myelodysplastic syndrome or acute leukemia, paroxysmal nocturnal hemoglobinuria (PNH) or recurrent aplasia after immunosuppressive therapy.
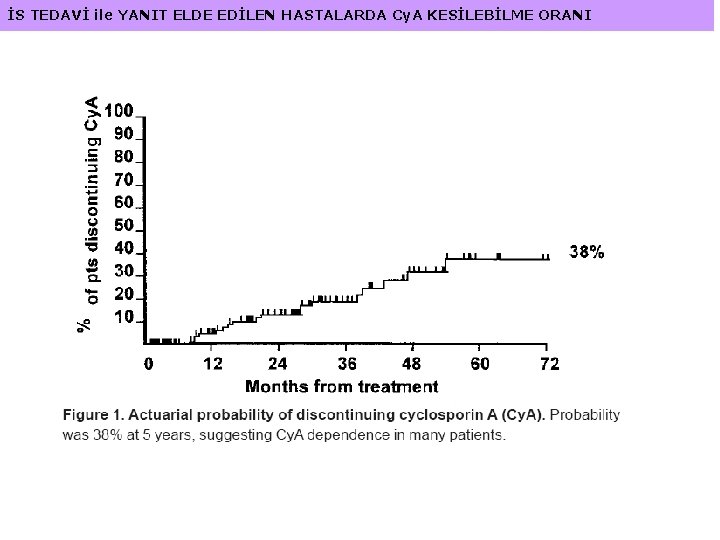
İS TEDAVİ ile YANIT ELDE EDİLEN HASTALARDA Cy. A KESİLEBİLME ORANI
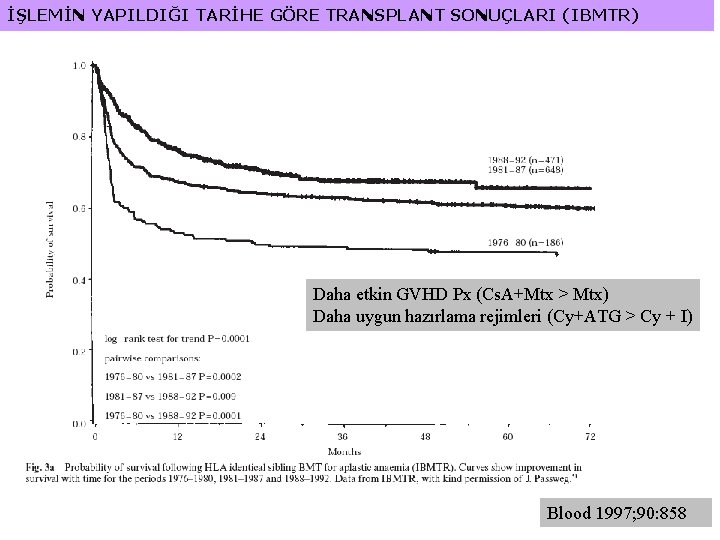
İŞLEMİN YAPILDIĞI TARİHE GÖRE TRANSPLANT SONUÇLARI (IBMTR) Daha etkin GVHD Px (Cs. A+Mtx > Mtx) Daha uygun hazırlama rejimleri (Cy+ATG > Cy + I) Blood 1997; 90: 858
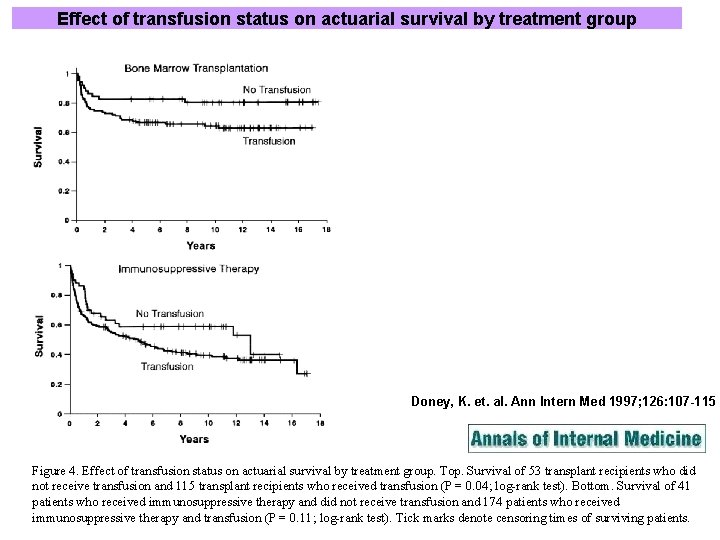
Effect of transfusion status on actuarial survival by treatment group Doney, K. et. al. Ann Intern Med 1997; 126: 107 -115 Figure 4. Effect of transfusion status on actuarial survival by treatment group. Top. Survival of 53 transplant recipients who did not receive transfusion and 115 transplant recipients who received transfusion (P = 0. 04; log-rank test). Bottom. Survival of 41 patients who received immunosuppressive therapy and did not receive transfusion and 174 patients who received immunosuppressive therapy and transfusion (P = 0. 11; log-rank test). Tick marks denote censoring times of surviving patients.
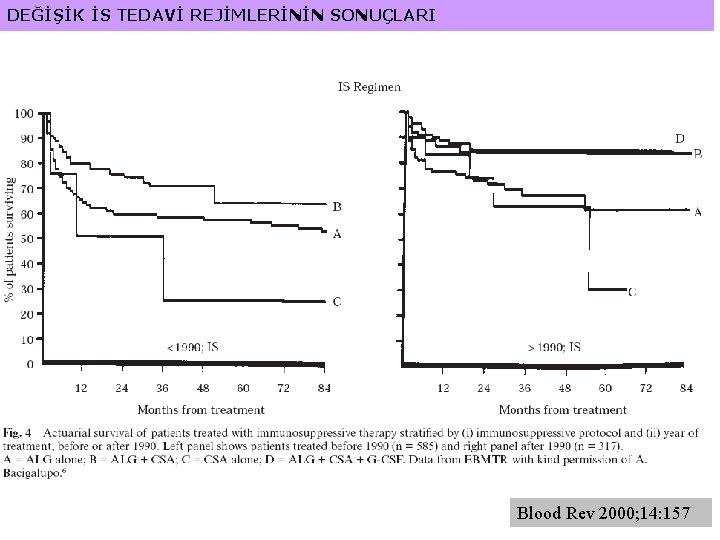
DEĞİŞİK İS TEDAVİ REJİMLERİNİN SONUÇLARI Blood Rev 2000; 14: 157
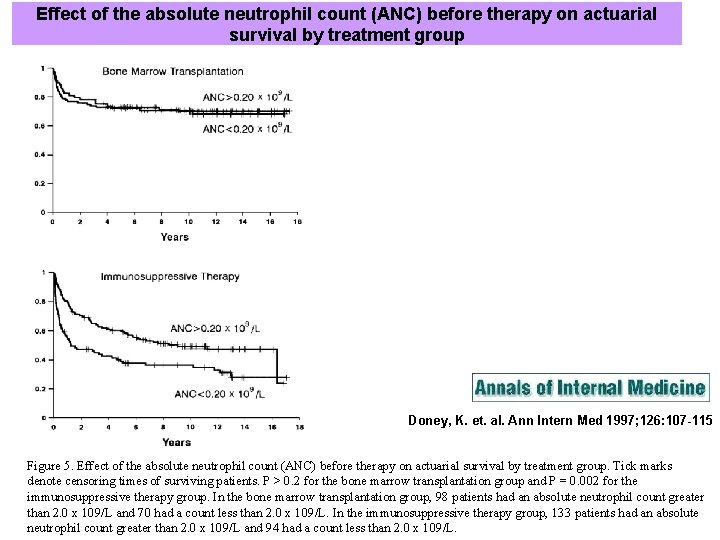
Effect of the absolute neutrophil count (ANC) before therapy on actuarial survival by treatment group Doney, K. et. al. Ann Intern Med 1997; 126: 107 -115 Figure 5. Effect of the absolute neutrophil count (ANC) before therapy on actuarial survival by treatment group. Tick marks denote censoring times of surviving patients. P > 0. 2 for the bone marrow transplantation group and P = 0. 002 for the immunosuppressive therapy group. In the bone marrow transplantation group, 98 patients had an absolute neutrophil count greater than 2. 0 x 109/L and 70 had a count less than 2. 0 x 109/L. In the immunosuppressive therapy group, 133 patients had an absolute neutrophil count greater than 2. 0 x 109/L and 94 had a count less than 2. 0 x 109/L.
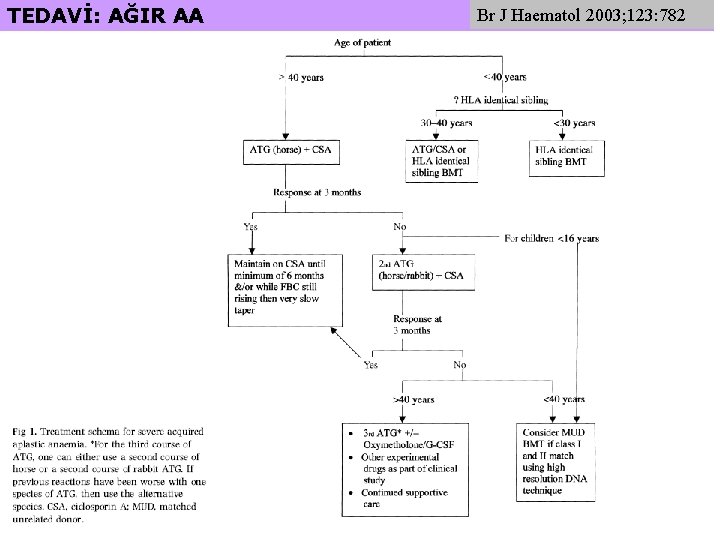
TEDAVİ: AĞIR AA Br J Haematol 2003; 123: 782
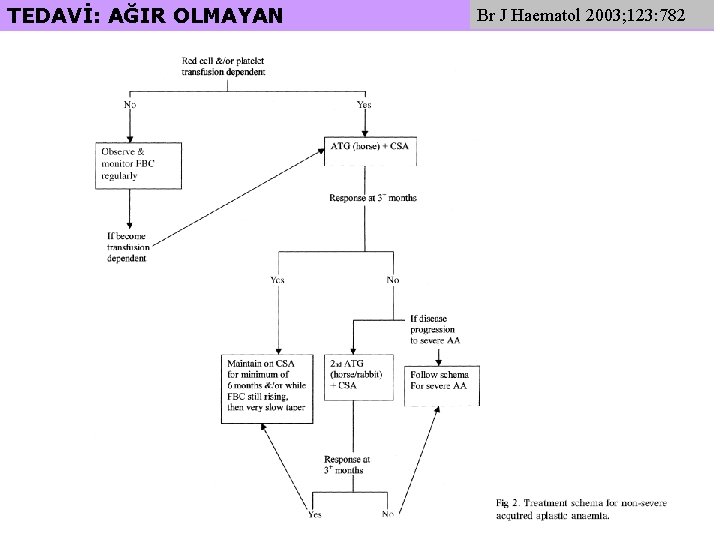
TEDAVİ: AĞIR OLMAYAN Br J Haematol 2003; 123: 782
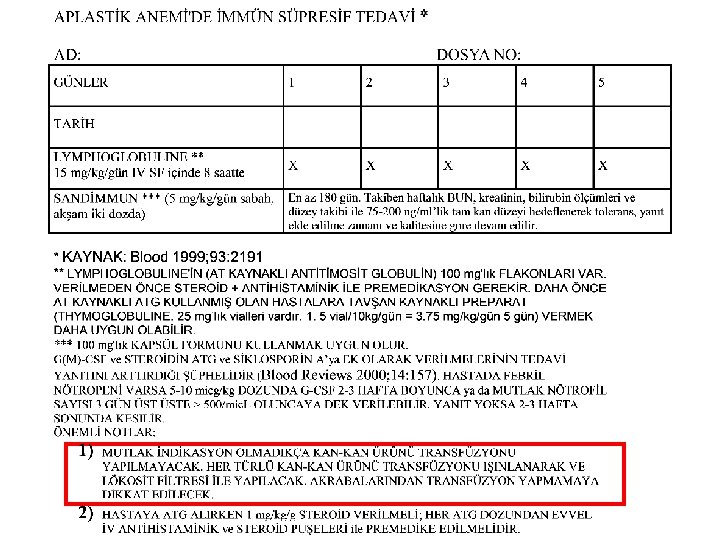
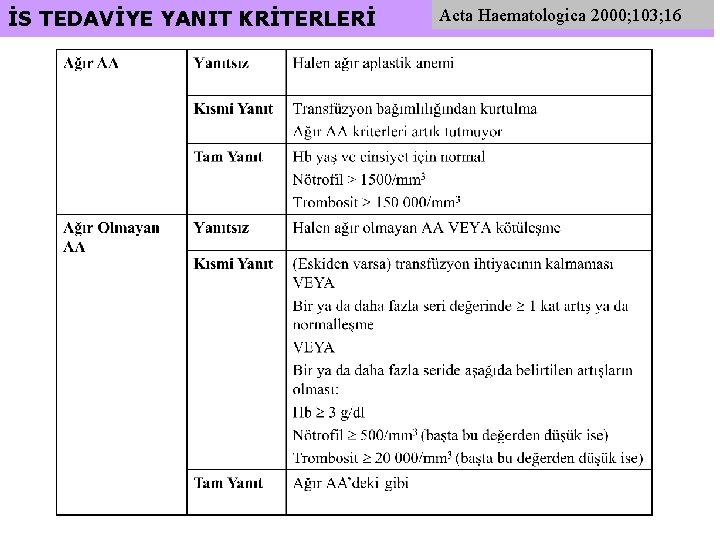
İS TEDAVİYE YANIT KRİTERLERİ Acta Haematologica 2000; 103; 16

VI. PROGNOZ
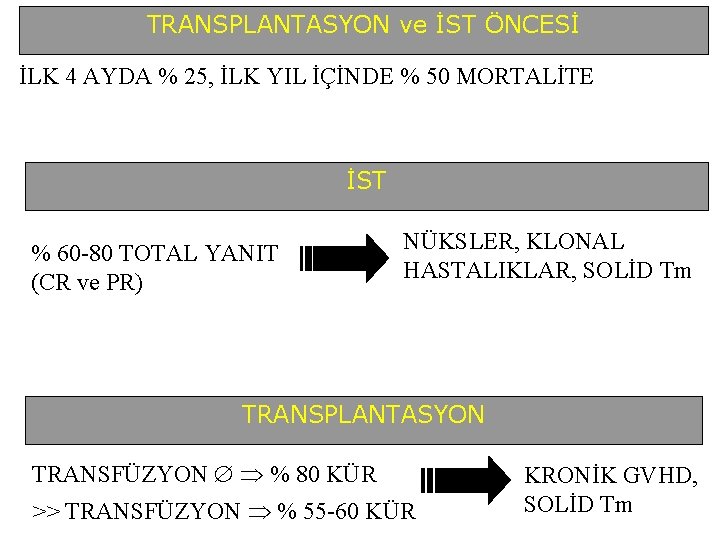
TRANSPLANTASYON ve İST ÖNCESİ İLK 4 AYDA % 25, İLK YIL İÇİNDE % 50 MORTALİTE İST % 60 -80 TOTAL YANIT (CR ve PR) NÜKSLER, KLONAL HASTALIKLAR, SOLİD Tm TRANSPLANTASYON TRANSFÜZYON % 80 KÜR >> TRANSFÜZYON % 55 -60 KÜR KRONİK GVHD, SOLİD Tm
- Slides: 62