
Anabolic Steroids Mac Gregor Brown Bryce Inman Psyc

Anabolic Steroids Mac. Gregor Brown & Bryce Inman Psyc 472 1

History of Performance Drug Abuse w Greeks reported using certain mushrooms and plant seed to increase performance. w Romans used drugs to increase performance of horses and gladiators to increase crowd response. w Steroids first developed in the 1930’s w Used by the Germans on their soldiers and animals during WW 2 to make up for a lack of nutrition. w 1950’s first used for athletic purposes in Russia and Europe. n Primarily for weightlifting. w Mid 1950’s it was discovered that testosterone was the driving force behind increased athletic performance. w Used in all levels of sports, in the 1972 Olympics 68% of athletes reported using anabolic steroids. w 1991 the Federal Anabolic Control Act classified steroids as a schedule 3 drug. 2

Performance Enhancing Drug Statistics w 3. 6% of high school students abuse steroids. n Risen nearly 2% in 2002, only drug other than ecstasy to show an increase. w Men that abuse steroids have a high incidence of some form of opioid abuse. w Over 3, 000 people in the USA have reported the use of steroids. w 1997 175, 000 women reported steroid use. w 15% of NCAA athletes use performance enhancing drugs. w 90% of athletes reported have used some form of performance enhancing drugs during there career. 3
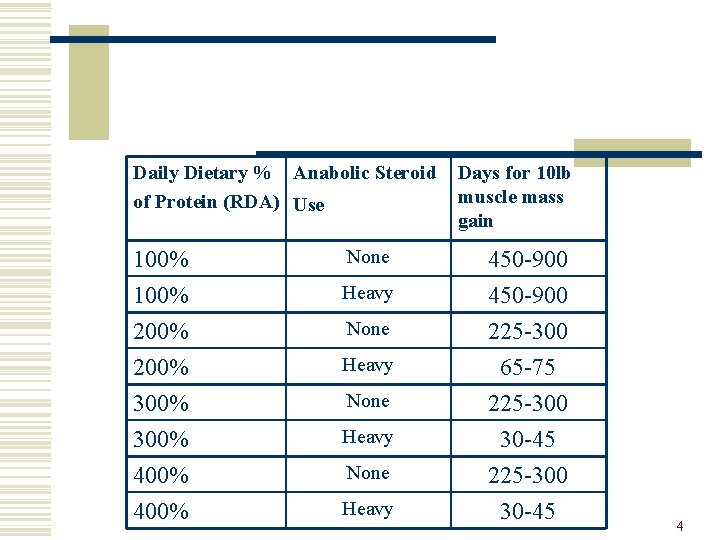
Daily Dietary % Anabolic Steroid of Protein (RDA) Use 100% 200% 300% 400% None Days for 10 lb muscle mass gain None 450 -900 225 -300 65 -75 225 -300 30 -45 225 -300 Heavy 30 -45 Heavy None Heavy 4
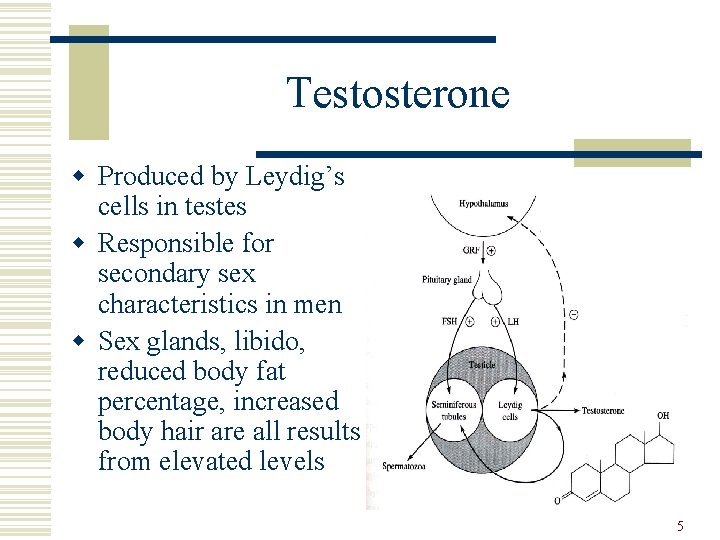
Testosterone w Produced by Leydig’s cells in testes w Responsible for secondary sex characteristics in men w Sex glands, libido, reduced body fat percentage, increased body hair are all results from elevated levels 5
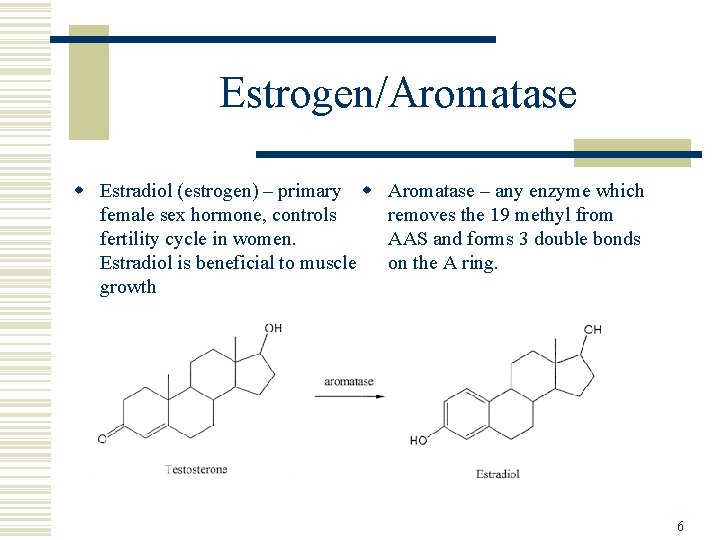
Estrogen/Aromatase w Estradiol (estrogen) – primary w female sex hormone, controls fertility cycle in women. Estradiol is beneficial to muscle growth Aromatase – any enzyme which removes the 19 methyl from AAS and forms 3 double bonds on the A ring. 6

DHT w Through 5 -alpha reductase, testosterone is converted to a hormone 4 X as potent, dihydrotestosterone w DHT binds to receptors much more avidly than testosterone w 5 -alpha reductase is present in high amounts in tissues of the prostate, skin, scalp, liver, and central nervous system 7

What are steroids? w Fat soluble molecule which contains a system of 4 rings made up of 17 carbon atoms w E. g. cholesterol, estrogen, testosterone, progesterone, cortisol, etc. w Anabolic steroid (DEA) – Any hormonal substance, chemically and pharmacologically, related to testosterone that promotes muscle growth 8

Anabolic/Androgenic w Anabolic – “building”, increased skeletal muscle mass, bone density, hemoglobin, nitrogen retention and protein synthesis w Androgenic – androgens are sex hormones that can induce male traits (e. g. growth of sex organs, increased body hair, libido, skin oil, and change in voice) w Anabolic/Androgenic steroids (AAS) seek to maximize the anabolic effects while minimizing the androgenic effects. The ratio of these anabolic/androgenic effects is called therapeutic index. Testosterone is the baseline at 1. 9
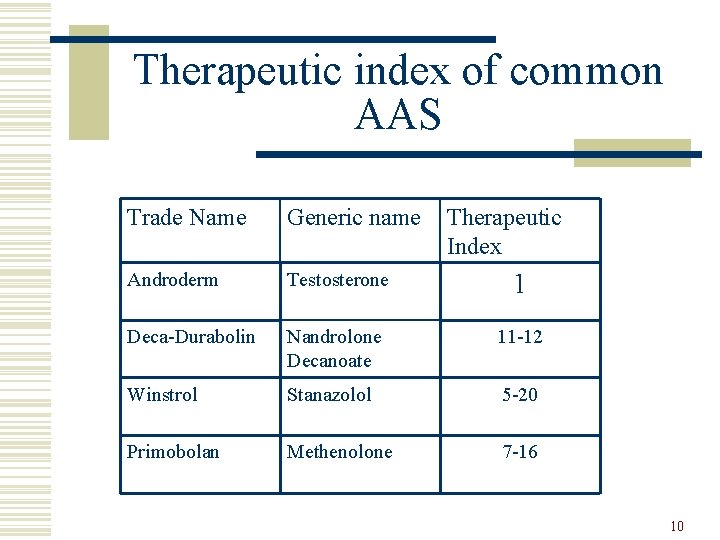
Therapeutic index of common AAS Trade Name Generic name Therapeutic Index Androderm Testosterone 1 Deca-Durabolin Nandrolone Decanoate 11 -12 Winstrol Stanazolol 5 -20 Primobolan Methenolone 7 -16 10

Basic modifications of Testosterone w 17 alpha – Remove the H with a methyl or ethyl group, producing an oral steroid w 17 beta – Add carbon atoms to this position and increase solubility in lipids w Other modifications at the carbon 2, 3 9, & 19 positions – slow receptor degradation, increase steroid’s affinity for binding to receptor sites, inhibit enzymatic conversion to a weaker androgen 11

Do anabolic steroids work? w Most research has shown that anabolic steroids produce no effect on muscle growth. Why? w Fowler (1965) – Nibal 20 mg/day Results: No increase in muscle mass (MM) w Johnson (1968) – D-bol 10 mg/day. No increase in MM w Casner(1971) – Winstrol 6 mg/day. No increase in MM w Hervey (1976) – D-bol 100 mg/day. No increase in MM 12

AAS Administration w Oral preparations – 17 methyl alklayted to survive acidic gastric secretions, short half life (e. g. dianabol, winstrol) w Injectable solutions – prepared in water or oil. Longer release times for oil. (e. g. Nandrolone Decanoate) w Patch and gel – provides steady and constant testosterone delivery (e. g. Trenbolone) w Aerosol propellant – rapid effects, very hard to detect in drug tests w Sublingual preparations – absorbed directly into blood stream so avoid digestive system, rapid effects 13
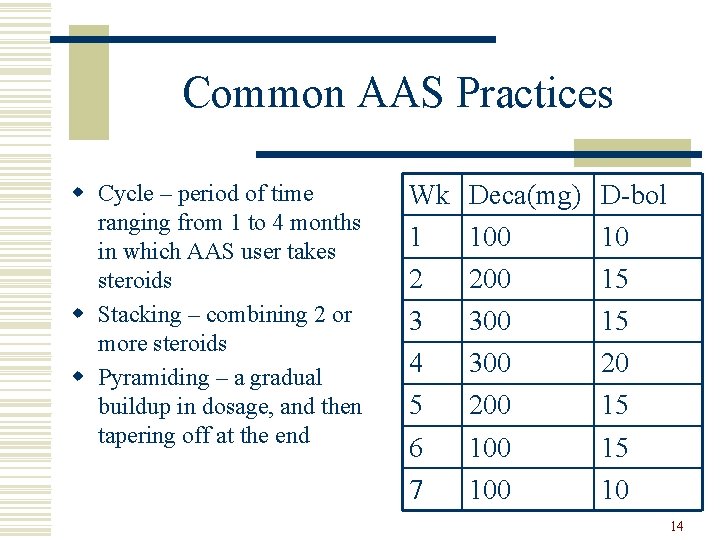
Common AAS Practices w Cycle – period of time ranging from 1 to 4 months in which AAS user takes steroids w Stacking – combining 2 or more steroids w Pyramiding – a gradual buildup in dosage, and then tapering off at the end Wk Deca(mg) D-bol 1 100 10 2 200 15 3 300 15 4 300 20 5 200 15 6 7 100 15 10 14
15

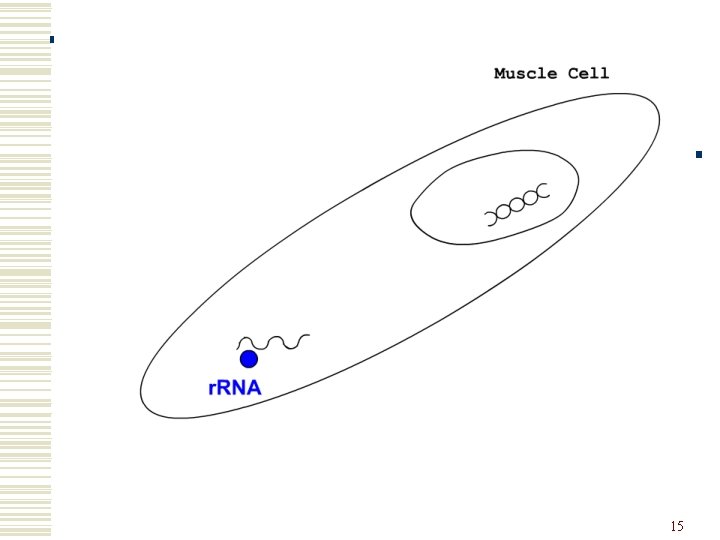
Why AAS produce muscle w Activation of r. RNA resulting in protein synthesis w Anticatabolic effect – block action of natural cortisone w Increase free testosterone levels w Stimulates activity of IGF-1 (Insulin-like growth factor) 16

Positive side effects of AAS w Enhanced muscle mass/strength w Enhanced blood volume and hemoglobin concentration w Enhanced bone density and strength w Hastened healing of muscular injuries w Decreased body fat w Increased immune response w Elevated mood 17

Clinical Applications w Bone metabolism conditions – osteoporosis w Testosterone deficiency conditions – male hypogonadism, andropause w Cardiovascular conditions – reduces angina pectoris, hypertension, coronary artery disease w AIDS – reduces AIDS wasting 18

Common AAS w Approved in U. S. w Illegal in U. S. -Testosterone Cypionate -Nandrolone Decanoate -Fluoxyymesterone -Stanozolol -Testosterone enanthate -Methandrostenolone -Oxandrolone -Oxymesterone Veterinary Steroids -Equipoise (Boldenone undecyclate) -Trenbolone 19

Deca Durabolin w Nandrolone decanoate - Long acting ester w Most widely used w Side effects: Water retention, endogenous test. suppression, other mild effects w Detectable for over 1 year in drug screenings 20
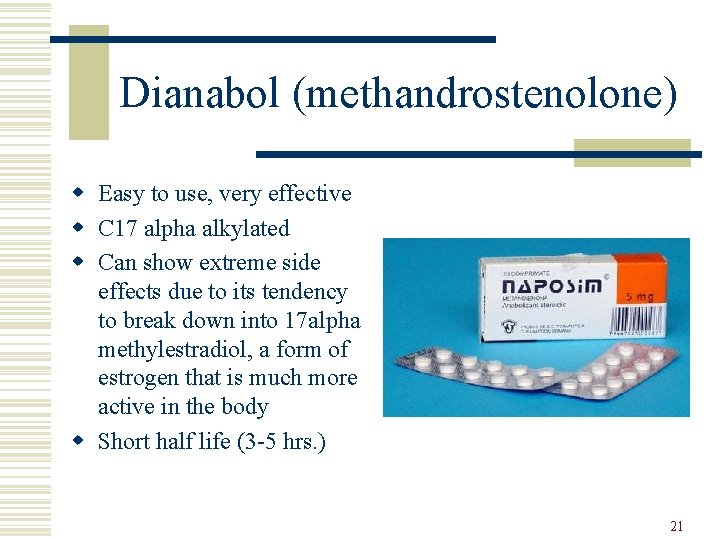
Dianabol (methandrostenolone) w Easy to use, very effective w C 17 alpha alkylated w Can show extreme side effects due to its tendency to break down into 17 alpha methylestradiol, a form of estrogen that is much more active in the body w Short half life (3 -5 hrs. ) 21

Winstrol (stanozolol) w Not capable of converting into estrogen due to modifications at the 9 th C position w Prepared in both oral and injectable forms w Aside from C 17 methylation, relatively few side effects. 22

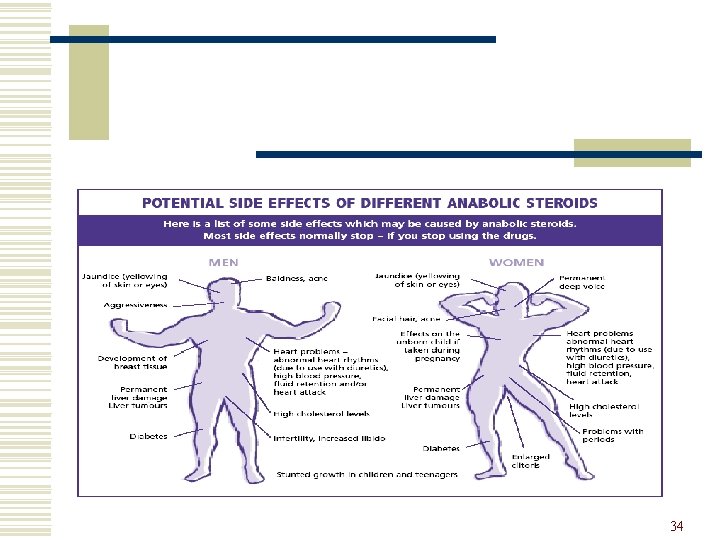
Side Effects Hypertension, acne, fluid retention, hypogonadism, gynecomastia, sleep disturbances, increased aggression, epistaxis (nose bleeds), withdrawal depression, prostate enlargement, heart enlargement, virilization, abnormal blood clotting, libido reduction, appetite stimulation, benign prostate enlargement 23

Acne and hair loss w Acne w Hair loss Ø Sebaceous glands Ø Highly androgenic (responsible for oil steroids that convert to secretion) are DHT will aggravate stimulated by balding. androgens Ø Bad acne may develop Ø DHT chokes the hair follicle, eventually on the shoulders, back, killing it and face 24

Gynecomastia w Female breast tissue resulting from high levels of estrogen w Estrogen acts upon receptors in the breast and stimulates the growth of mammary tissue w Removed only by surgery 25

Stunted Growth w If taken during adolescence or before, AAS may halt growth. This occurs because they stimulate epiphyseal plates on long bones to fuse prematurely. Once fused, no growing can occur w Stunted growth caused not by AAS, but the conversion of AAS to estrogen. AAS that do not convert to estrogen will actually promote height growth 26
Cardiovascular disease w AAS have a strong effect on LDL and HDL levels w HDL is the “good” cholesterol because it removes cholesterol deposits from the arteries w LDL has the opposite effect w AAS increase LDL levels and lower HDL levels. w Oral compounds much more likely to promote this adverse effect. 27

Testosterone and Aggression w Testosterone associated with social dominance w Test. exacerbates “fight or flight” response w Studies indicate an increase in aggression in animals treated with AAS w Prison studies, situational studies AAS - pronounced effects on the limbic system Ø AAS can act as neurotransmitters Ø In supraphysiologic doses, AAS can alter function of and increase the number of receptors Ø Can also modulate other NT in the brain 28

Permanent Steroid-Induced Rage Behavior? w Animal studies show alterations to the test. receptors in the brain. They’ve also shown modifications to other receptors w The most bothersome alterations in the brain are the increase in androgen receptors and the increased binding capacity of these receptors. After cessation of AAS use, these receptors are thought to be “hungry” for elevated androgen levels. Other NT’s recognize this deficit and may remain low (similar to andropause) resulting in depression, self esteem problems, and a greater tendency to lash out 29

Cancer w AAS are just a synthetic version of The only exception to this hormones that are is the use of c 17 alpha already present in the alkylated compounds body, so the stress on organs is not very high. which are liver toxic. They have been known w As such, cancer to induce liver damage resulting from AAS is and cancer extremely rare 30
Sexual Dysfunction Impotence Testicular atrophy Male reproductive system Production of test. is depends largely on the turned off (along with level of androgenic spermatogenesis) hormones. Rebound resulting in a effect occurs after AAS noticeable change in use in which no size of the testicles. androgens are present in the body. 31

Body Dysmorphia AAS often produce addiction and body image disorders that have been labeled as § Megorexia or bigorexia § Reverse anorexia § Adonis complex § Muscle dysmorphia 32

Women and AAS w Large amounts of test. in women can produce very noticeable side effects Virilization Women develop masculine characteristics such as a deepening of the voice, changes in skin texture, acne, libido, hair loss, body hair, and enlargement of the clitoris 33
34

AAS & the Gateway Phenomenon After AAS, over 50% used drugs such as: • 31% estrogen receptor inhibitors • 22% HCG • 17% diuretics and/or “uppers” • 15% pain killers 35
Aromatase inhibitors/Estrogen Blockers w Aromatase Inhibitors w Estrogen Blockers Blocks the aromatase enzyme, Binds to free floating estrogen molecules, preventing test. from estrogen from attaching to converting to estrogen androgen receptors Slows muscle growth, May also stimulate FSH and suppresses HDL LH endogenous test. cholesterol, prevents water production retention e. g. Nolvadex (Tamoxifen e. g. Arimidex (anastrozole) citrate) 36
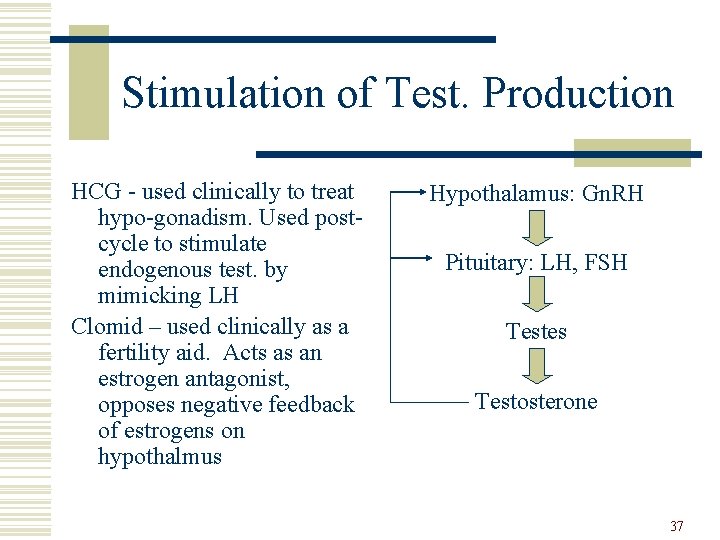
Stimulation of Test. Production HCG - used clinically to treat hypo-gonadism. Used postcycle to stimulate endogenous test. by mimicking LH Clomid – used clinically as a fertility aid. Acts as an estrogen antagonist, opposes negative feedback of estrogens on hypothalmus Hypothalamus: Gn. RH Pituitary: LH, FSH Testes Testosterone 37

Insulin w Regulates glucose levels in the blood , its role in the body is to control the uptake, utilization, and storage of amino acids, carbohydrates, and fatty acids in the body. w Insulin is both anti-catabolic and anabolic because it stimulates the use and retention of nutrients in muscle cells (specifically glycogen) w Cannot be detected in drugs tests w Hypoglycemia one possible outcome of use. Can also result in immediate death, coma, or insulin dependent diabetes. 38
Cutting compunds Clenbuterol • Beta-2 sypathomimetic, used as a bronchodilator. • Animal studies indicate anabolic properties, but used primarily as a thermogenic compound by directly stimulating fat cells and breaking down triglycerides. Effects are temporary due to down regulation Thyroid hormone • Used to treat thyroid deficiency, obesity, and other metabolic disorders • Synthetic version of T 3 which stimulates thyroid gland resulting in; acceleration of cellular reactions, increase in metabolism & cardiovascular functions. • Rebound effect 39

Steroid Precursors/Prohormones w Androstenedione w Androstenediol w Dehydroepiandrosterone (DHEA) 40

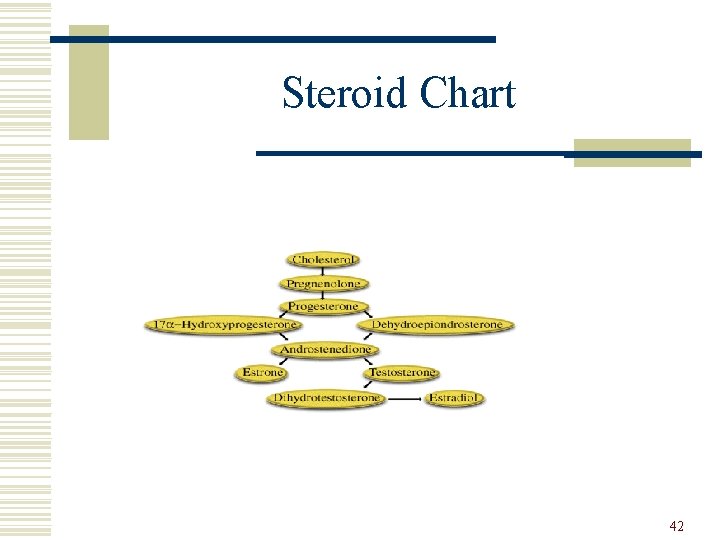
Androstenedione w Produced by the adrenal glands n 17 alpha-hydroxyprogesterone & DHEA. w Once produced it is one step away from testosterone and estrogen w Missing the a hydrogen atom in the 17 th position. w Processed by the liver where the hydrogen atom is added. 41
Steroid Chart 42

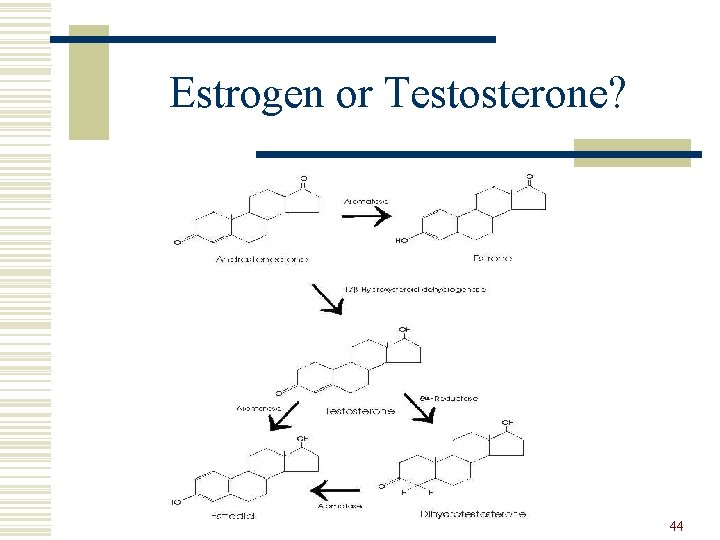
Estrogen or Testosterone? w Testosterone n Androstenedione is converted into testosterone by 17 beta-hydroxysteroid dehydrogenase, which is activated by luteinizing hormone secreted by the hypothalamus and pituitary gland w Estrogen n Androstenedione may also be converted to the estrogen, by the enzyme aromatase. 43
Estrogen or Testosterone? 44

Androstenediol w Similar to Androstenedione w Lacks a 3 -keto group that enables the conversion into estrogen w A much more androgenic compound (produces much more male based effects) 45

Why Androstenediol? w Has higher conversion rates to testosterone. w Doesn’t convert into estrogen. w Does not convert into DHT (cause of balding). 46

DHEA w 2 steps away w A precursor to testosterone that is produced in the adrenal glands. w Aids in producing Androstenedione which produces testosterone and estrogen w DHEA>Andro>Testosterone/Estrogen 47

Why Take a Steroid Precursor w Increase lean muscle mass? w Decrease body fat? w Increase strength ? w Increase libido? n Only temporarily increases blood levels of testosterone, does not cause body to naturally produce testosterone. 48

Negative Side Effects w w w w Balding Acne Enlarged prostate Reduced sperm count Increased aggression Kidney & Liver damage Disrupt the menstrual cycle Decrease levels of HDL cholesterol 49

Creatine 50

What is Creatine? w An amino acid taken into the body through meats and animal products. 51

What does Creatine do in the body? w Once ingested creatine is synthesized into phosphocreatine in the kidneys, liver, and the pancreas. w Creatine is synthesized by the three amino acids arginine, glycine, and methionine. w Once synthesized into phosphocreatine it is transported to skeletal muscles, the heart, and the brain for energy usage. 52

What Does Creatine do in the Body Cont. ? w Assists with the production of ATP, which is used for short term energy exertion. 53

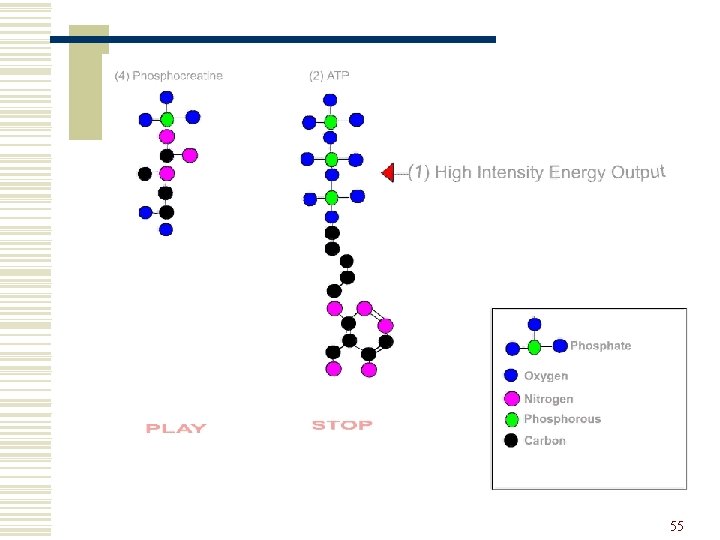
What is ATP? w Adenosine triphosphate (ATP). w ATP is used during short-term high intensity energy output. 54
55

How Does Creatine Assist with the Production of ATP? w When ATP is broken down during exercise, energy is produced with the loss of a phosphate ion. w During high intensity exercise, ATP is constantly broken down to ADP and Phosphorous and reproduced to provide maximum energy output. w When this occurs, phosphocreatine donates one of its phosphate ions to facilitate the resynthesis of ATP. 56

Results of this Process. w Reduced muscle fatigue - the rate at which ATP is broken down does not exceed the rate at which it can be resynthesized. w Decreased Lactic Acid w Faster Recovery 57

Side Effects w There is no pure evidence that creatine causes actual physical harm. w Possible Risks n n n Weight gain of 1 -2 kgs, due to the increase of fluid stores. Increased risk for muscle cramps, and tears due to the increased water retention Damage to kidneys. Usage may lead to cancer causes cancer. Excessive use may decrease the bodies natural ability to produce creatine. 58

How is Creatine Taken? w Powder form w Pill w Serum 59

Typical Dosage w 5 g daily – regular usage w 20 g daily – During loading period to build up creatine supply in the body 60

Growth Hormone (GH) w A naturally occurring hormone in the body. w Signaled release from the hypothalamus. w Release from the pituitary gland regulated by two hormones. n n n Somatostatin (SS) – decreases GH output. Growth Hormone-Releasing Hormone (GHRH) – Increase GH output. Can also be regulated by the amount of GH and Insulin Like Growth Factor 1 (ILGF-1) that is circulated back through the body. 61
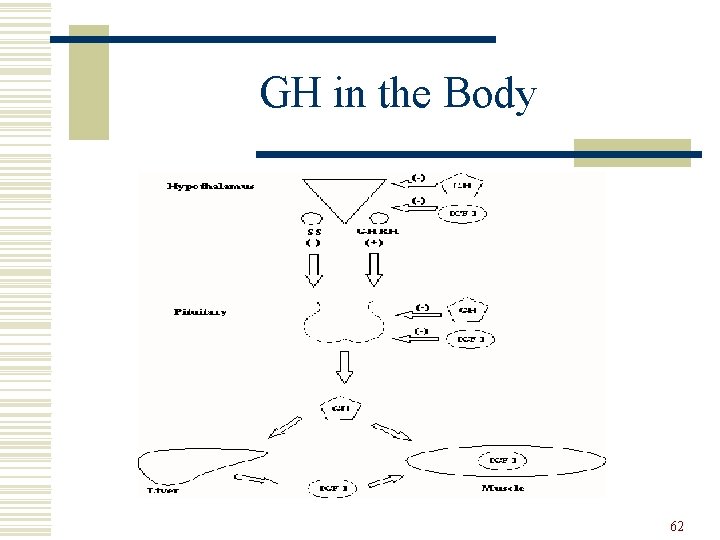
GH in the Body 62

Other Factors that Increase GH w Decreased blood glucose during exercise and sleep trigger the release of GH. w High protein increase small amounts GH release. w Some amino acids such as L-arginine can increase GH by decreasing the release SS from the hypothalamus. w Niacin has been shown to increase exercise induced GH release by 300 - 600% (Murray, 1995). 63

Theories about GH w Somatomedin hypothesis (Daughaday, 1972). 1. GH is released from the pituitary gland. 2. Travels to the liver where it is converted into ILGF. 3. ILGF enters the blood stream and stimulates muscle growth. 64

Theory 2 w Dual Effector Theory - Similar to the Somatomedin hypothesis except it is believed that GH alone has anabolic effects without ILGF. w Studies in mice have shown that mice injected with GH are significantly larger than those that were solely injected with ILGF. 65

How does GH Cause Muscle Growth? w Once converted into ILGF, ILGF stimulates the production of, and the conversion of satellite cells into muscle cells. w Satellite cells – Cells that lie dormant around muscle tissue until stimulated by ILGF. Have the ability to replicate the genetic makeup of muscle cells. 66

Side Effects w One of the most common side effects of GH abuse is acromegaly. n overgrowth of bone and connective tissue which leads to a change in physical appearance such as a protruding jaw and eyebrow bones. w Metabolic dysfunction n Glucose intolerance 67

How is GH Administered w Must have a prescription. w IM injections. w Dosage - A weekly dosage of 0. 30 mg/kg of body weight. w Very expensive! n Can be over $20, 000 for an annual supply of Growth Hormone. 68
Beta Blockers w Medically used to: n n n Reduce blood pressure Migraine headaches Heart arrhythmia Alcohol withdrawals Anti-anxiety 69

Athletic Uses w Reduces anxiety, jitters, and slows the heart rate. w Commonly used in sports that require a steady hand. n n n Golf Archery Bowling Pool Biathlon Rifle shooting 70
Physiological Effects 1. During heightened arousal adrenaline is produced 2. Heart rate increases and blood pressure is increased 3. Beta Blockers block the beta receptor on the muscles of the heart which reduces these effects. 71

Side Effects w Impotence w Low Blood Pressure w Insomnia w Cardiac failure w Poor circulation w May reduce performance capacity 72

Diuretics w Increase the amount of urine formation and the rate at which it is excreted. w Used in sports that require reduced weight such as: n n Wrestling Horse racing Bodybuilding Boxing w Also used to mask the use of other performance enhancing drugs. 73
Side Effects w Dehydration w Decreased circulation of blood volume w Muscle cramps w Renal disorders w Dizziness w Disrupted Heart rhythm 74

Blood Doping/Erythropoietin w Blood Doping n n Adding additional blood to the system to increase the amount of red blood cells in the system. Increased red blood cells increases the amount of oxygen that the body can carry. l n Thus, increasing the performance during endurance sports. Illegal, but hard to detect! 75

Erythropoietin w A naturally occurring hormone released from the kidneys. w Causes increased production of red blood cells. n n Increased oxygen capacity Increased tolerance to lactic acid. 76

Side Effects w w w w Can be very dangerous Bacterial infection Induce shock Hypertension Stroke May receive the wrong blood type Increased blood viscosity n n n Increased workload Increased risk for blood clots Increased risk for heart attack 77

Additional Performance Enhancing Drugs w GHB n Enables athlete to reach deeper state when sleeping l n Body produces more growth hormone Highly abused among athletic community as a recreational drug because it produces similar intoxication to alcohol without the caloric intake and hangover. 78

Additional Performance Enhancing Drugs w GHB n Enables athlete to reach deeper state when sleeping l n Body produces more growth hormone Highly abused among athletic community as a recreational drug because it produces similar intoxication to alcohol without the caloric intake and hangover. 79
- Slides: 79