
An Approach to Abnormal LFTs Robert C Lowe

An Approach to Abnormal LFTs Robert C. Lowe, M. D. Boston Medical Center July 17, 2013

R N ALP I T S A T. B IL T L A AL B GGT

Chessboard
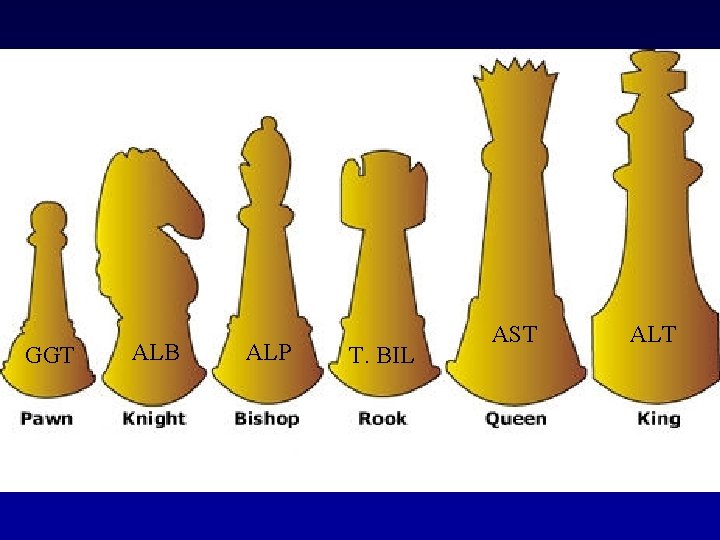
GGT ALB ALP T. BIL AST ALT

Case 1 30 year old woman 4 days of malaise, fevers to 101, nausea 1 day of RUQ pain and jaundice Exam - T 100. 5 Icteric sclerae and jaundice Tender hepatomegaly, no spleen tip

Case 1 AST 1535 ALT 1602 ALP 128 T. Bil 7. 3 Albumin 3. 9 WBC 8. 1 HCT 41 PLT 353

Transaminases AST - aspartate aminotransferase ALT - alanine aminotransferase Released when hepatocytes are injured a sign of necrosis.

AST - less specific for liver disease Muscle (skeletal and cardiac) Kidney Erythrocytes ALT - very little outside of liver. A better marker of liver disease.

Differential Diagnosis Sky high transaminases > 15 x normal
Differential Diagnosis Sky high transaminases > 15 x normal Virus Drug Ischemia } >80% of cases

AST/ALT>1000 Virus Toxin Ischemia History and Exam Points

AST/ALT>1000 History and Exam Points Virus IVDU Sexual partners Travel Food exposures Toxin Ischemia Arthralgias Urticaria Herpetic lesions Stigmata of liver dz


AST/ALT>1000 History and Exam Points Virus IVDU Sexual partners Travel Food exposures Toxin Ischemia Arthralgias Urticaria Herpetic lesions Stigmata of liver dz

AST/ALT>1000 History and Exam Points Virus IVDU Sexual partners Travel Food exposures Toxin Ischemia Arthralgias Urticaria Herpetic lesions Stigmata of liver dz Meds OTC meds Herbs and supplements

AST/ALT>1000 History and Exam Points Virus IVDU Sexual partners Travel Food exposures Toxin Ischemia Arthralgias Urticaria Herpetic lesions Stigmata of liver dz Meds OTC meds Herbs and supplements Recent surgery Hypotension Cardiac arrest CMP

AST/ALT>1000

AST/ALT>1000 Autoimmune Wilson Disease Bile Duct Obstruction Budd-Chiari

AST/ALT>1000 Autoimmune Wilson Disease Bile Duct Obstruction Budd-Chiari Clinical Clues Female gender Personal or Family Hx of autoimmune dz

AST/ALT>1000 Autoimmune Wilson’s Disease Bile Duct Obstruction Budd-Chiari Clinical Clues Female gender Personal or Family Hx of autoimmune dz ANA ASMA Ig levels

AST/ALT>1000 Autoimmune Wilson’s Disease Bile Duct Obstruction Budd-Chiari

AST/ALT>1000 Autoimmune Wilson’s Disease Bile Duct Obstruction Budd-Chiari Clinical Clues Male gender < age 40 Neuropsychiatric syndrome Psychosis Movement disorder

AST/ALT>1000 Autoimmune Wilson’s Disease Bile Duct Obstruction Budd-Chiari Clinical Clues Male gender < age 40 Neuropsychiatric syndrome Psychosis Movement disorder Low ALP Hemolysis Ceruloplasmin less useful in acute disease

KF Rings
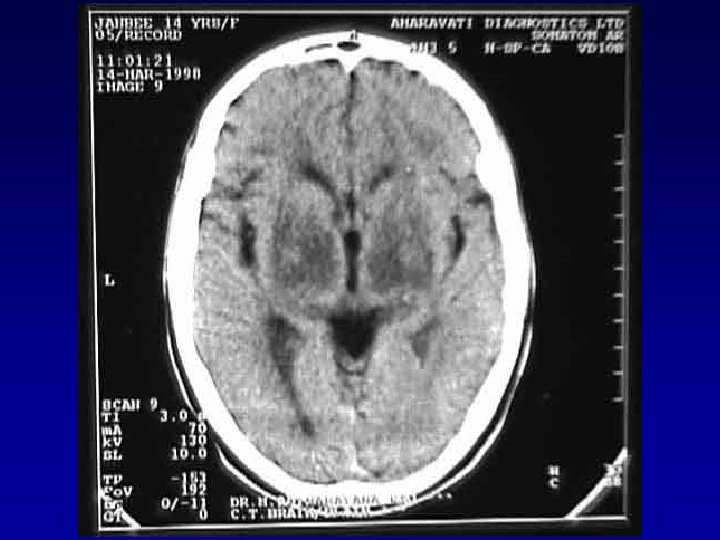
Head CT

AST/ALT>1000 Autoimmune Wilson Disease Bile Duct Obstruction Budd-Chiari

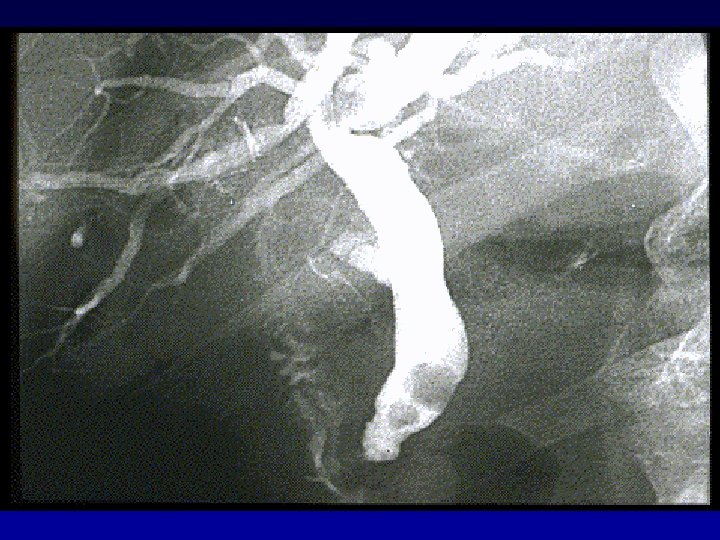
AST/ALT>1000 Clinical Clues Autoimmune H/O biliary colic or GS disease FH of gallstones Wilson Disease RUQ pain N/V Bile Duct Obstruction Transaminases fall rapidly - over 1 -3 days Budd-Chiari U/S often diagnostic, but may need further imaging with MRCP/ERCP

AST/ALT>1000 Autoimmune Wilson Disease Bile Duct Obstruction Budd-Chiari

AST/ALT>1000 Clinical Clues Autoimmune Wilson Disease OCP use Prior venous thrombosis Myeloproliferative disorder Malignancy Bile Duct Obstruction Abdominal Pain Ascites Budd-Chiari

Laboratory Testing • • • Hepatitis A - Ig. M and Ig. G Hepatitis B - s. Ag, c. Ab, e. Ag, HBV DNA Hepatitis C - RNA level ANA, ASMA, Ig levels RUQ U/S with Doppler Study • Consider other viral serologies, ceruloplasmin, MRCP

Prognostic Features

Prognostic Features • Coagulopathy – INR elevation • Encephalopathy – Mental Status – Asterixis – Apraxia



Case 2 • • • Asymptomatic 45 year-old woman Cholesterol 245, Trig 266 No significant FH No meds Works as an accountant
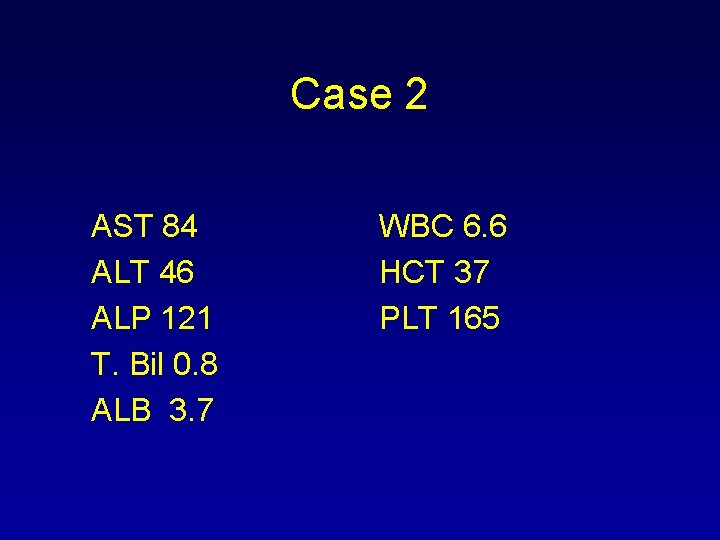
Case 2 AST 84 ALT 46 ALP 121 T. Bil 0. 8 ALB 3. 7 WBC 6. 6 HCT 37 PLT 165

Alcoholic LFT Pattern • AST/ALT > 2: 1 • Absolute AST and ALT < 300 • GGT elevation is helpful, but nonspecific.

Alcoholic LFT Pattern WHY? ALT synthesis is decreased in Et. OH hepatitis. Partially due to pyridoxine deficiency may correct with B 6 therapy.
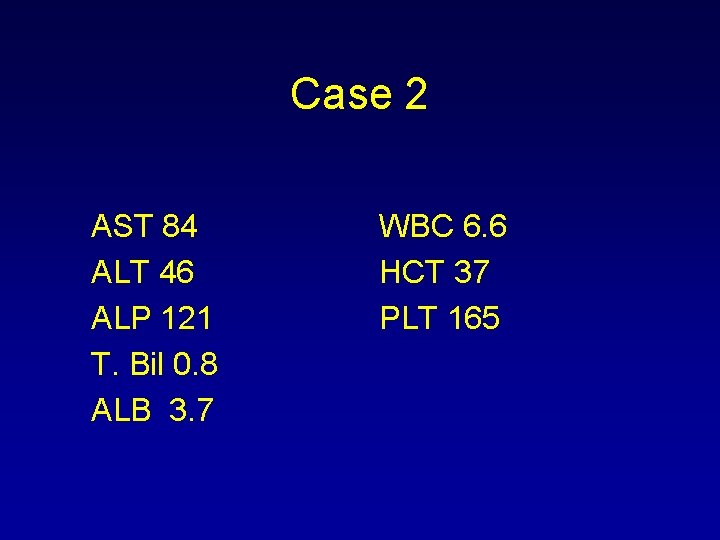
Case 2 AST 84 ALT 46 ALP 121 T. Bil 0. 8 ALB 3. 7 WBC 6. 6 HCT 37 PLT 165
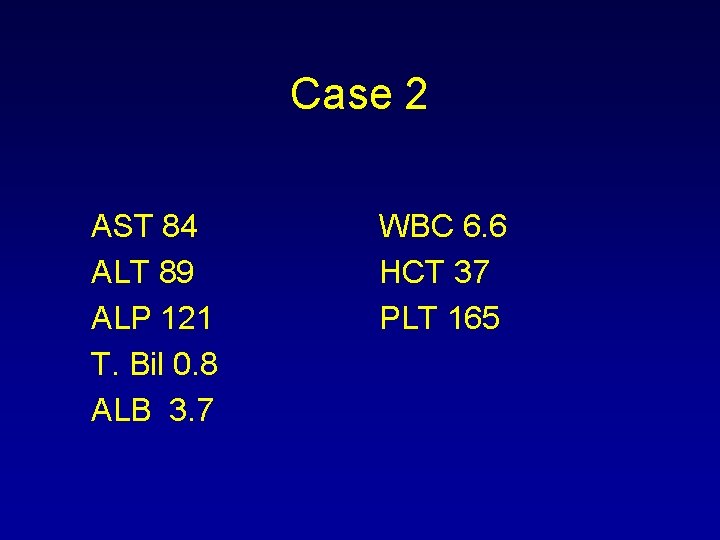
Case 2 AST 84 ALT 89 ALP 121 T. Bil 0. 8 ALB 3. 7 WBC 6. 6 HCT 37 PLT 165

Mildly Elevated Transaminases A B C D E F G H

Mildly Elevated Transaminases Alcohol / Autoimmune B Hepatitis C Hepatitis Drug Exotic Wilson Disease Alpha-1 -antitrypsin deficiency Fatty liver Gluten sensitive enteropathy Hemochromatosis

Mildly Elevated Transaminases Alcohol / Autoimmune B Hepatitis C Hepatitis Drug Exotic Wilson Disease Alpha-1 -antitrypsin deficiency Fatty liver Gluten sensitive enteropathy Hemochromatosis Thyroid disease, myopathies

Mildly Elevated Transaminases Alcohol / Autoimmune Alcohol Hx B Hepatitis HBs. Ag, HBc. Ab, HBs. Ab C Hepatitis HCV Ab Drug Hx Exotic Wilson Disease Alpha-1 -antitrypsin deficiency Fatty liver RUQ U/S, TG Gluten sensitive enteropathy Hemochromatosis Thyroid disease, myopathies
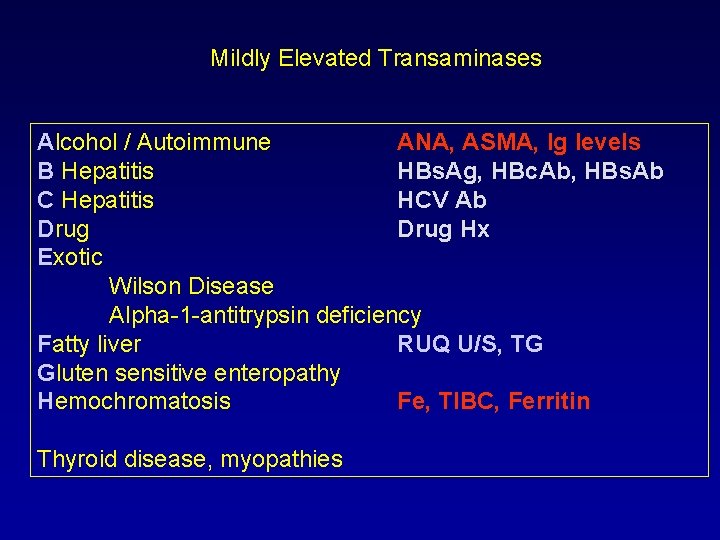
Mildly Elevated Transaminases Alcohol / Autoimmune ANA, ASMA, Ig levels B Hepatitis HBs. Ag, HBc. Ab, HBs. Ab C Hepatitis HCV Ab Drug Hx Exotic Wilson Disease Alpha-1 -antitrypsin deficiency Fatty liver RUQ U/S, TG Gluten sensitive enteropathy Hemochromatosis Fe, TIBC, Ferritin Thyroid disease, myopathies
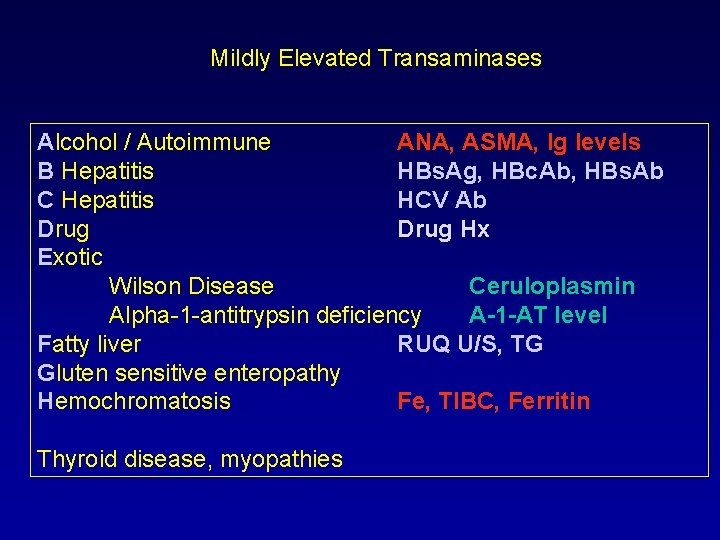
Mildly Elevated Transaminases Alcohol / Autoimmune ANA, ASMA, Ig levels B Hepatitis HBs. Ag, HBc. Ab, HBs. Ab C Hepatitis HCV Ab Drug Hx Exotic Wilson Disease Ceruloplasmin Alpha-1 -antitrypsin deficiency A-1 -AT level Fatty liver RUQ U/S, TG Gluten sensitive enteropathy Hemochromatosis Fe, TIBC, Ferritin Thyroid disease, myopathies
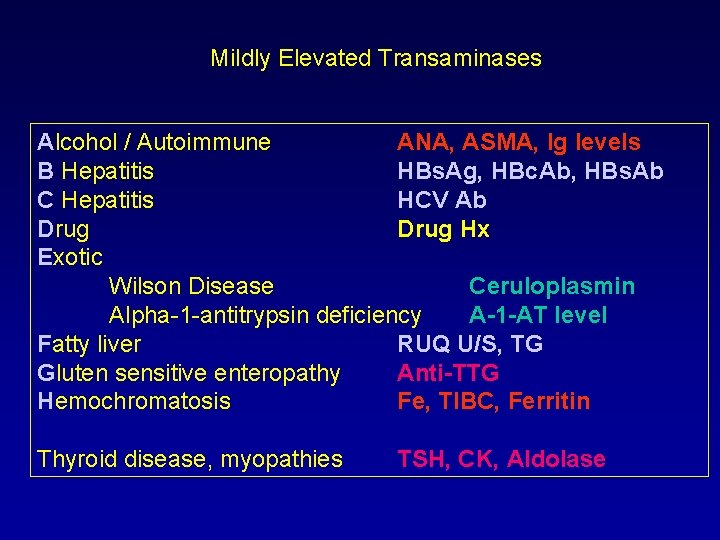
Mildly Elevated Transaminases Alcohol / Autoimmune ANA, ASMA, Ig levels B Hepatitis HBs. Ag, HBc. Ab, HBs. Ab C Hepatitis HCV Ab Drug Hx Exotic Wilson Disease Ceruloplasmin Alpha-1 -antitrypsin deficiency A-1 -AT level Fatty liver RUQ U/S, TG Gluten sensitive enteropathy Anti-TTG Hemochromatosis Fe, TIBC, Ferritin Thyroid disease, myopathies TSH, CK, Aldolase
Liver Biopsy 1124 pts referred for elevated ALT --81 cases with negative serologic workup
Liver Biopsy 1124 pts referred for elevated ALT --81 cases with negative serologic workup Biopsies -- 41 pts with steatosis 26 pts with NASH 8% normal biopsies Daniel, et al. Am J Gastro, 1999
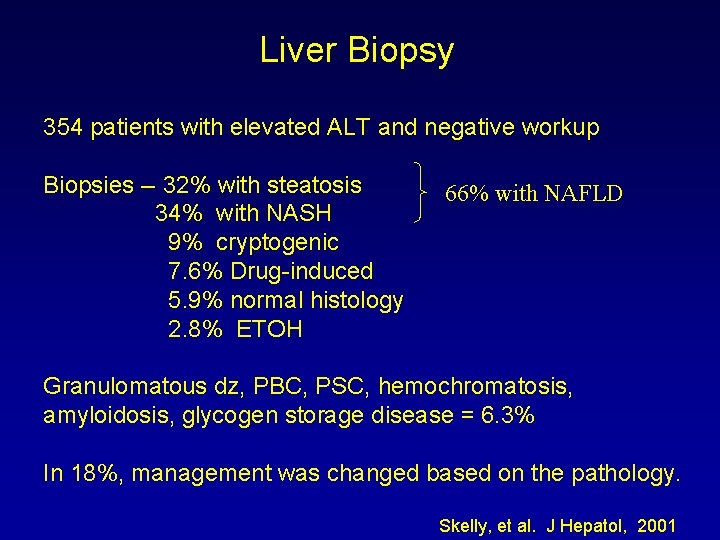
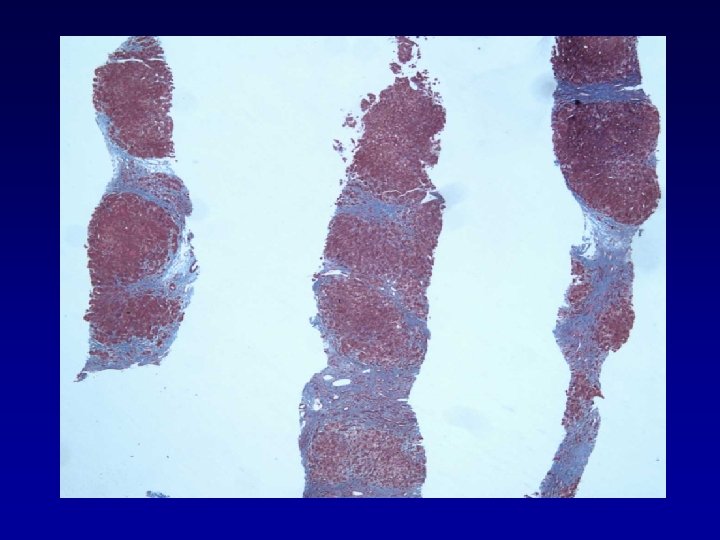
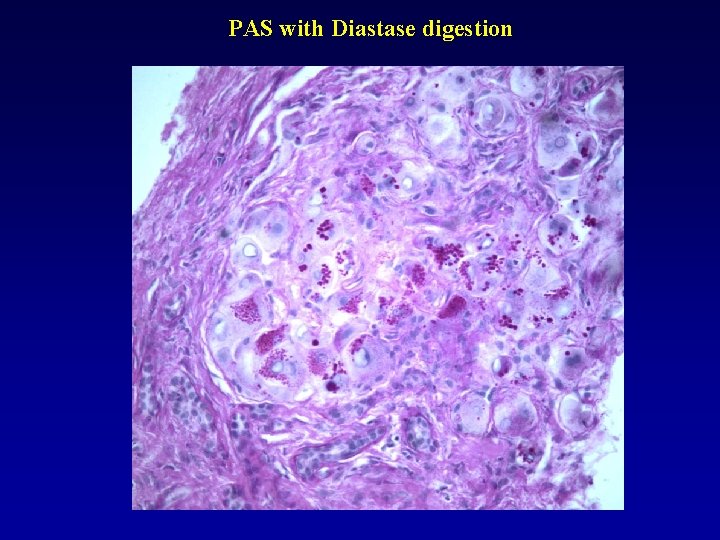
Liver Biopsy 354 patients with elevated ALT and negative workup Biopsies -- 32% with steatosis 34% with NASH 9% cryptogenic 7. 6% Drug-induced 5. 9% normal histology 2. 8% ETOH 66% with NAFLD Granulomatous dz, PBC, PSC, hemochromatosis, amyloidosis, glycogen storage disease = 6. 3% In 18%, management was changed based on the pathology. Skelly, et al. J Hepatol, 2001
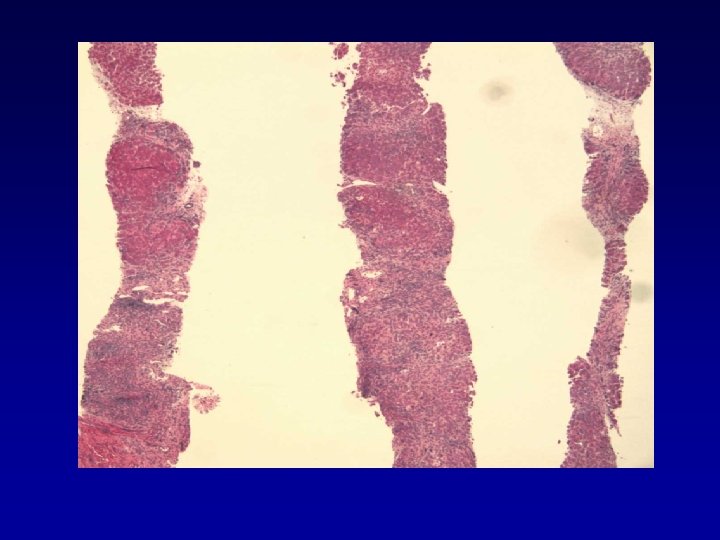
PAS with Diastase digestion

An Approach to Abnormal LFTs Robert C. Lowe, M. D. Boston Medical Center July 17, 2013


An Approach to Abnormal LFTs Part 2 Robert C. Lowe, M. D. Boston Medical Center July 25, 2013

AST/ALT>1000 Virus Toxin Ischemia

AST/ALT>1000 Autoimmune Virus Toxin Ischemia Wilson’s Disease Bile Duct Obstruction Budd-Chiari

Alcohol / Autoimmune B Hepatitis C Hepatitis Drug Exotic Wilson’s Disease Alpha-1 -antitrypsin deficiency Fatty liver Gluten sensitive enteropathy Hemochromatosis Thyroid disease, myopathies

Case 3 35 year old woman Mild fatigue No significant PMH No meds Exam - cervical LAN 0. 5 cm, nontender Liver 3 cm below RCM

Case 3 AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0

Case 3 AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0 GGT = 650

Alkaline Phosphatase Produced in liver, bone, placenta, intestine. Blood group O and B may release intestinal ALP after a fatty meal. Elevations up to 2 x normal are very nonspecific. Up to 1/3 have no disease.

Elevated ALP Bone disease -- Paget’s Metastases Myeloma Use GGT or 5’NT to distinguish bone from liver.

GGT and 5’ NT GGT - not found in bone, present in biliary epithelium. Problems - induced by Et. OH, anticonvulsants, warfarin, so specificity is a problem. GGT/ALP > 2. 5 suggests Et. OH, but only 33% sensitive!

5’ Nucleotidase More specific than GGT Rises over several days after bile duct obstruction, slower than GGT.

Elevated ALP

Elevated ALP Biliary obstruction Tumor masses - primary or metastatic Drug Effect

Elevated ALP Special circumstances Malignancy without liver involvement -tumors produce Regan isoenzyme of ALP (gonadal and urologic) Hodgkin’s Disease and RCC - can cause nonspecific hepatitis with elevated ALP

Workup of ALP Elevation 1) Confirm liver origin with 5’-NT or GGT
Workup of ALP Elevation 1) Confirm liver origin with 5’-NT or GGT 2) U/S or CT to R/O mass and dilated ducts Mass -- biopsy Dilated ducts -- MRCP/ERCP
AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0
Pruritus for 4 months with no rash AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0
Pruritus for 4 months with no rash AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0 AMA = 1: 2500

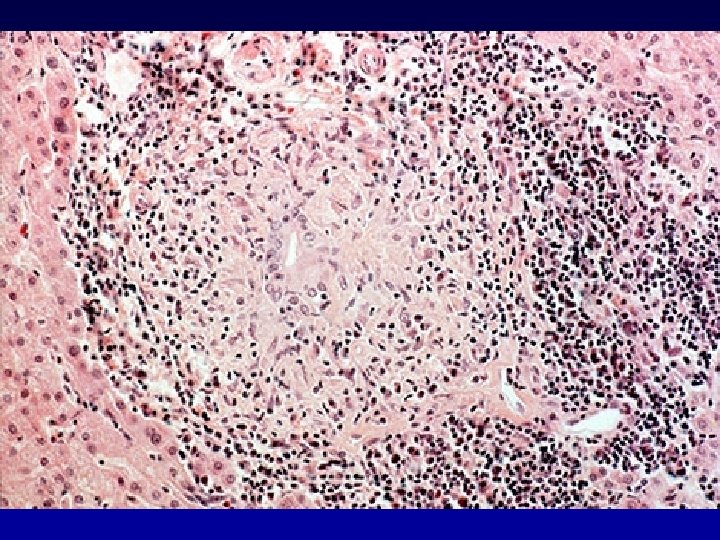
Primary Biliary Cirrhosis • • • F: M = 8 -9: 1 Classic = fatigue, itching, elevated ALP Common = asyx elevated ALP NO jaundice until end-stage AMA is diagnostic (95% positive) Treat with ursodiol
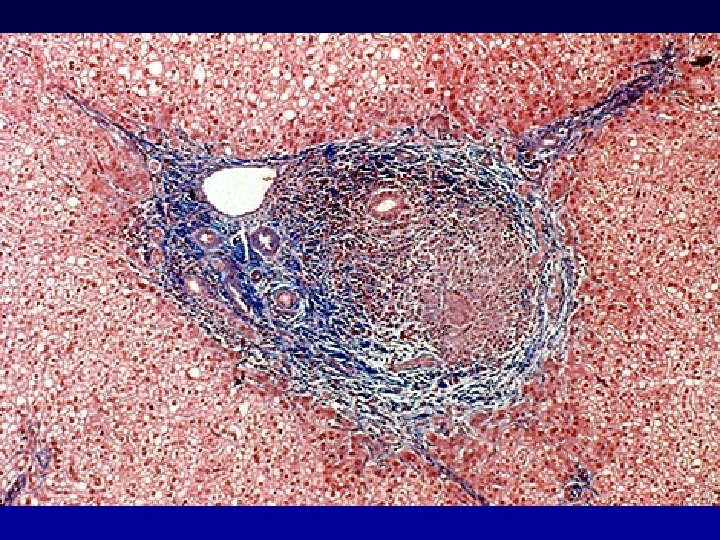
AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0
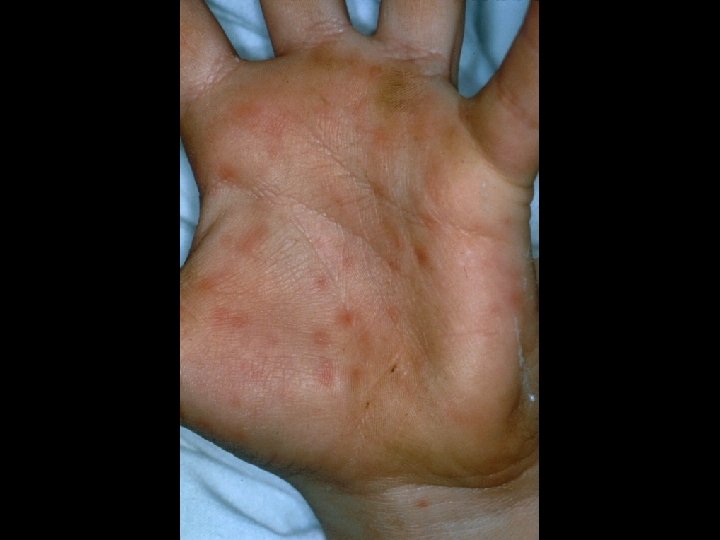
AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0

Patient reveals a 12 year history of ulcerative colitis AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0
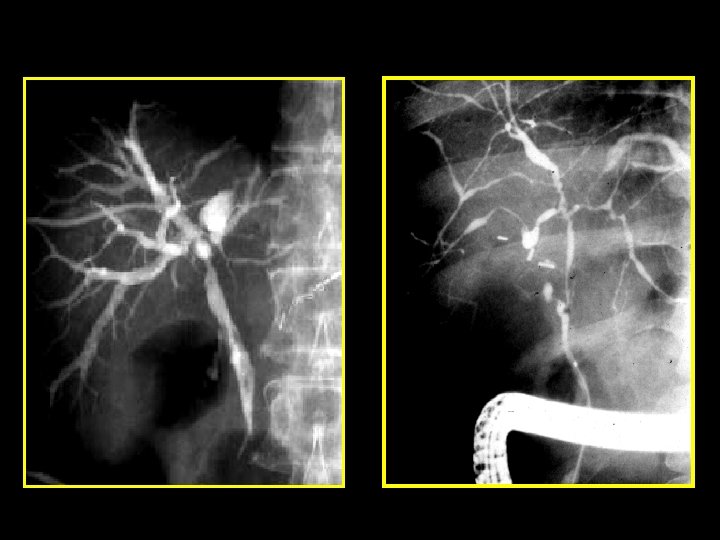
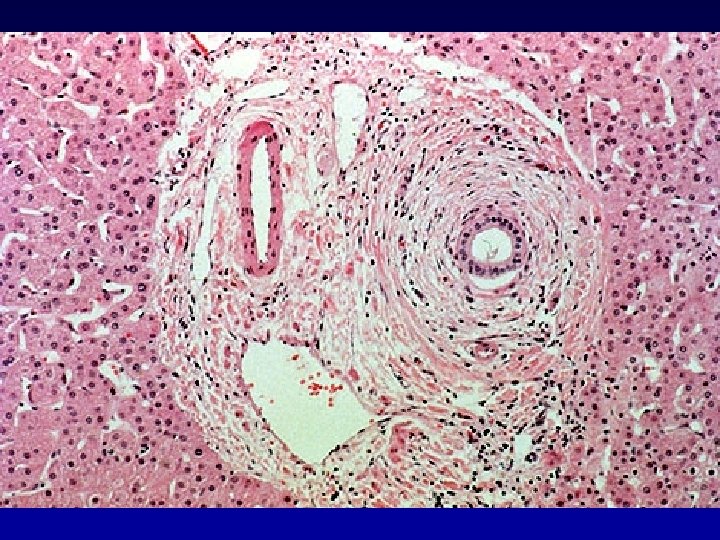
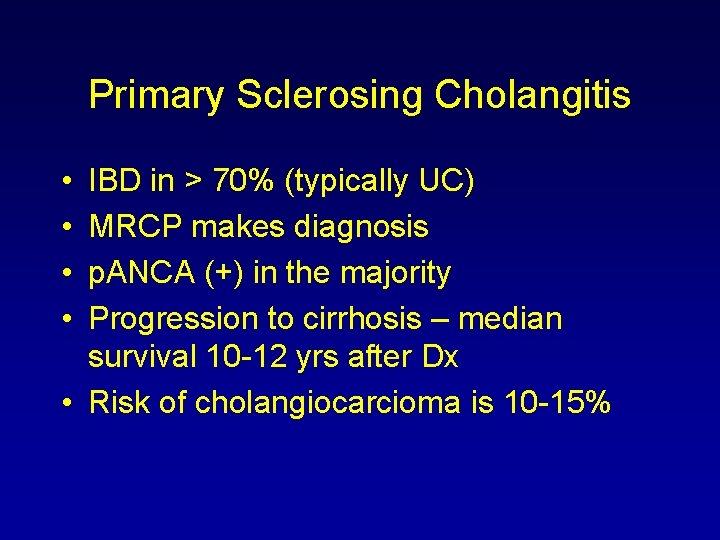
Primary Sclerosing Cholangitis • • IBD in > 70% (typically UC) MRCP makes diagnosis p. ANCA (+) in the majority Progression to cirrhosis – median survival 10 -12 yrs after Dx • Risk of cholangiocarcioma is 10 -15%
AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0

Patient with Cr. 2. 0 and significant proteinuria AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0
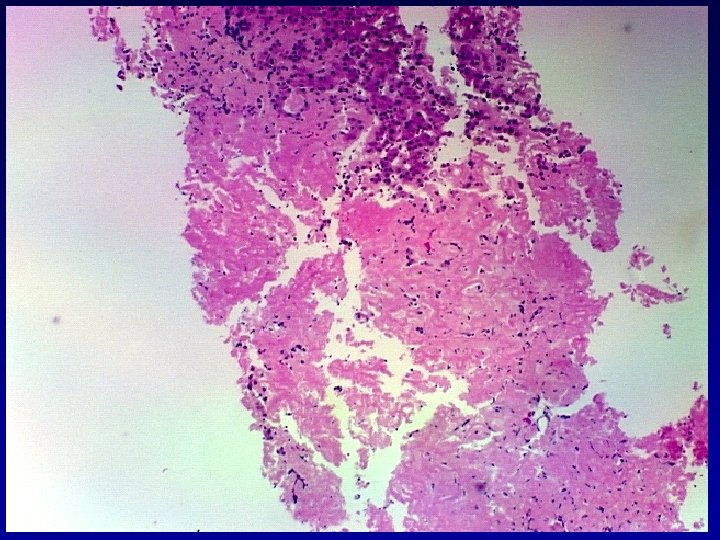
Liver biopsy
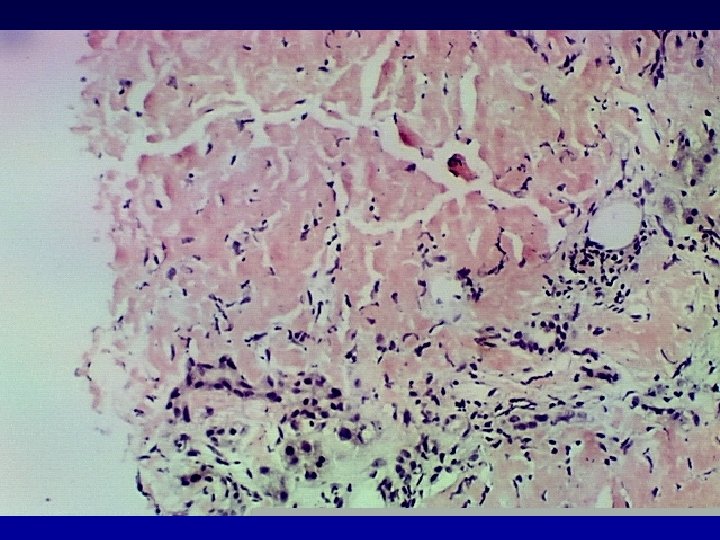
Liver biopsy
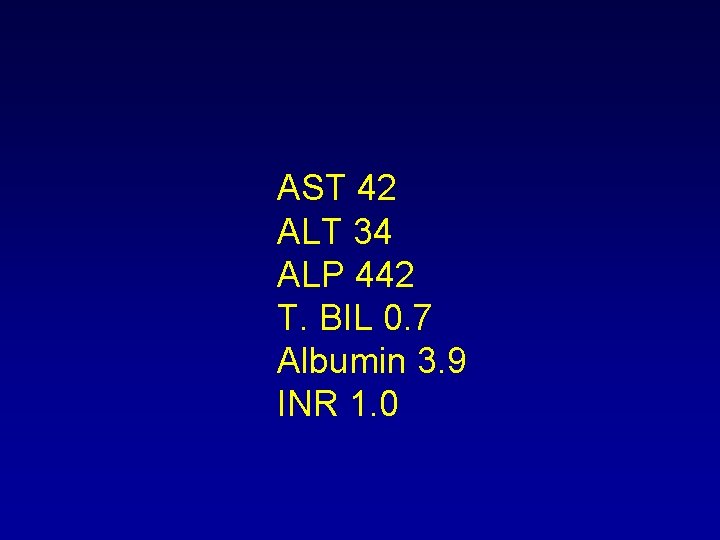
AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0

41 M with advanced HIV – CD 4 27 AST 42 ALT 34 ALP 442 T. BIL 0. 7 Albumin 3. 9 INR 1. 0
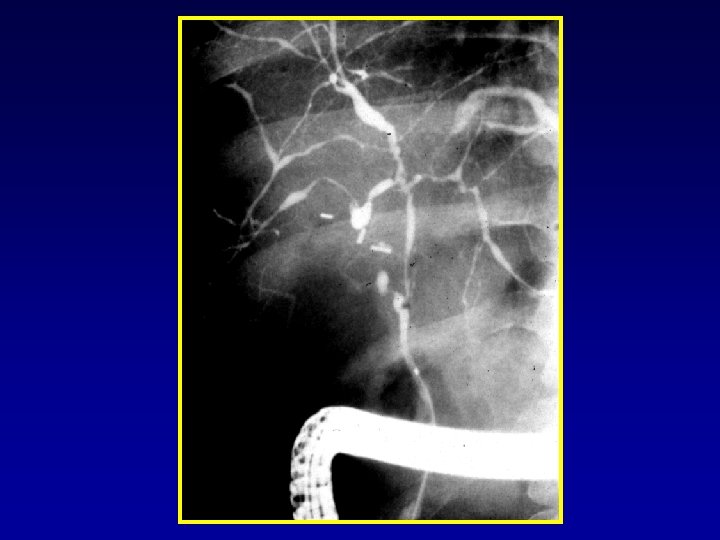

HIV Cholangiopathy • • Seen in advanced AIDS – CD 4 <50 High ALP, mildly elevated bilirubin Significant RUQ pain Survival is 6 -9 months – due to other infections, wasting…
Case 3 35 year old woman Mild fatigue No significant PMH No meds Exam - cervical LAN 0. 5 cm, nontender Liver 3 cm below RCM

Elevated ALP Biliary obstruction Tumor masses - primary or metastatic Drug Effect
Elevated ALP Biliary obstruction Tumor masses - primary or metastatic Drug Effect PBC, PSC Infiltrative disease - amyloid Granulomatous diseases – sarcoid, TB, fungi Autoimmune variants
Workup of ALP Elevation 1) Confirm liver origin with 5’-NT or GGT 2) Take a thorough drug history 3) U/S or CT to R/O mass and dilated ducts Mass -- biopsy Dilated ducts -- MRCP/ERCP 4) Neither -- check AMA, then biopsy liver.

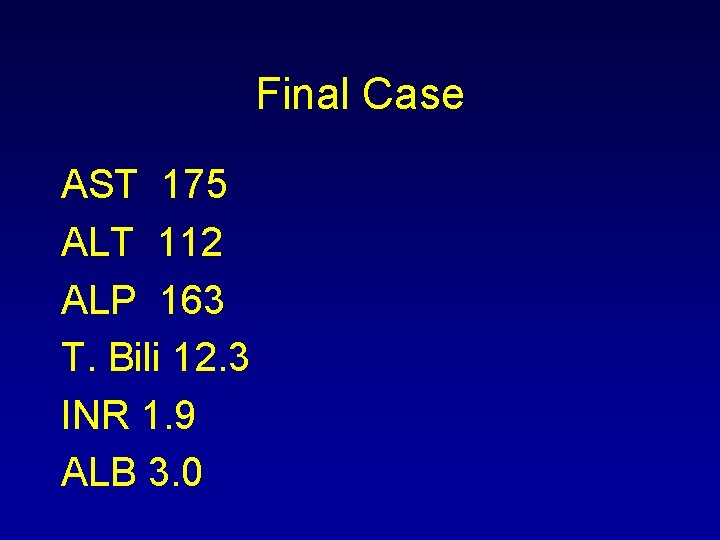
Final Case AST 175 ALT 112 ALP 163 T. Bili 12. 3 INR 1. 9 ALB 3. 0

An Approach to Abnormal LFTs Part 2 Robert C. Lowe, M. D. Boston Medical Center July 25, 2013
- Slides: 104