
Alterations in Respiratory Function Ball and Bindler Spring

Alterations in Respiratory Function Ball and Bindler Spring 2007 Donna Hills Ed. D APN

Developmental Alterations in the Respiratory System of the infant and child. • Critical anatomical differences between the infant/child/adult – smaller diameter and shorter – faster respir rate – narrower airway – infants up to 1 -2 mo of age are obligate nose breathers – tongue is larger in proportion to the oral cavity – larger lymphoid tissue until about age 6 yr.
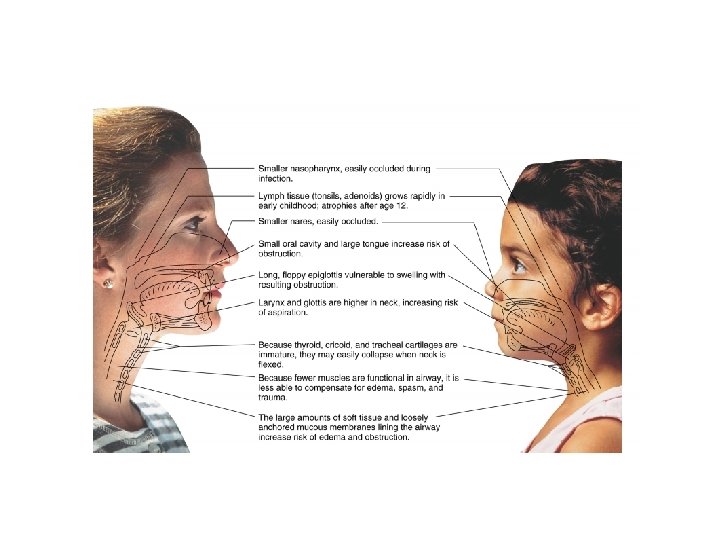

Critical anatomical differences between the infant/child/adult • Lower airway – children up to 6 yr are primarily diaphragmatic breathers – intercostal muscles are immature and less effective in aiding respir before age 6. – Chest wall is flexible due to ribs being primarily cartilage; more prone to movement

FIGURE 25– 2 In children, the trachea is shorter and the angle of the right bronchus at bifurcation is more acute than in the adult. Where is an aspirated foreign body likely to land? When you are resuscitating or suctioning, you must allow for the differences in the length of the trachea as it is easier to slip into the right bronchus with an endotracheal tube or suction catheter. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

Assessment Guidelines for a Child in Respiratory Distress • • Ball & Bindler: Box 25 -1, p. 825 Quality of respirations Quality of pulses Color Cough Behavior changes Signs of dehydration
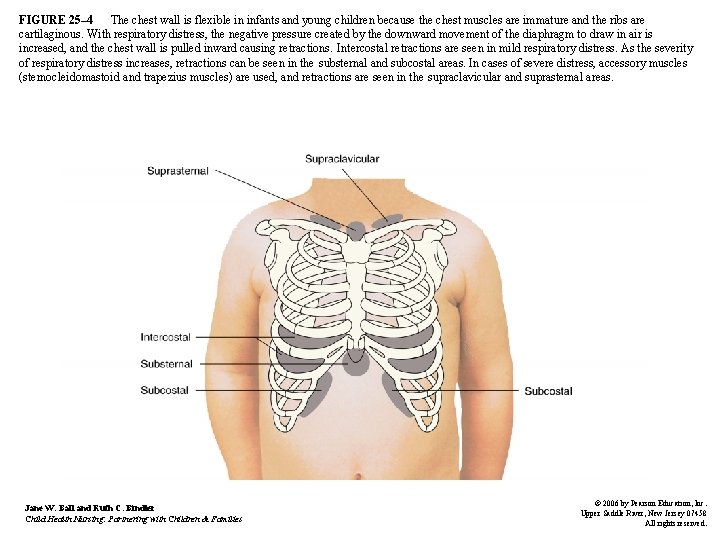
FIGURE 25– 4 The chest wall is flexible in infants and young children because the chest muscles are immature and the ribs are cartilaginous. With respiratory distress, the negative pressure created by the downward movement of the diaphragm to draw in air is increased, and the chest wall is pulled inward causing retractions. Intercostal retractions are seen in mild respiratory distress. As the severity of respiratory distress increases, retractions can be seen in the substernal and subcostal areas. In cases of severe distress, accessory muscles (sternocleidomastoid and trapezius muscles) are used, and retractions are seen in the supraclavicular and suprasternal areas. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

Abnormal Alterations in the Respiratory System of the infant and child. • Apnea: cessation of respir >20 sec. – May or may not be accompanied by cyanosis, pallor, hypotonia, bradycardia. – Apnea may be the first sign of distress in the infant; respir dysfunction, , sepsis, meningitis/encephalitis. – Apnea of prematurity: occurs in preterm infants due to lack of maturity of the neuro/respiratory systems.

Apparent Life Threatening Event • episode of apnea accompanied by color change, hypotonia, choking, gagging, occuring in a near term infant (>37 wks). • May occur during sleep or wakefulness, or feeding. • Child is usually admitted for monitoring

Sudden Infant Death Syndrome: SIDS • sudden death of an infant <1 yr of age that remains unexplained after a complete autopsy, death scene investigation and review of the history. • Leading cause of death in infants (1 mo-1 yr), with 90% occurring before 6 mo. . • Rarely occurs in infants <2 wks. • Unpredictable and unpreventable. • First sign is cardiopulmonary arrest.

Signs of Respiratory Distress • hypoxemia; low O 2 level in the blood; assessed by O 2 saturation or ABG/VBG. • Hypercapnia: high CO 2 level in the blood: ABG/VBG • irritability, lethargy, cyanosis, dyspnea (flaring, grunting, retracting), tachypnea. • Any of the above signs needs action and needs to be reported immediately to the Instr, RN or MD.

Nursing Management of Respiratory Distress • If O 2 sats are less than 95%, confirm that the tracing is believable; (sine wave form and correlates with heart rate). • At the same time, raise the HOB or sit child up if able. • Determine O 2 sat probe is functioning • open airway • administer O 2 by blow-by first, then face mask, then bag/valve if sats <90.

Nsg. Management Resp Dist. (cont) • assess the child for changes in: – vital signs, esp. HR, RR and BP. – mentation/responsiveness – tone, – color • alert the appropriate person to communicate changes in O 2 sat and responses to treatment; obtain order for O 2 or any other actions. Transfer child if required.

Reactive Airway Disorders • occur as a response to invasion by a virus, bacterium, allergen or irritant. • Response includes inflammation, edema, increased mucous production and bronchospasms – AKA the 3 S’s: secretions, swelling, spasm. • Can involve both the upper and lower airways • include croup, asthma and bronchiolitis

Croup Syndromes • classified as upper airway syndrome • can have swelling of : epiglottis, larynx, trachea, and/or bronchi. • 3 viral syndromes: – acute spasmodic laryngitis (spasmodic croup) – laryngotracheitis – laryngotracheobronchitis (LTB) • 2 bacterial syndromes: – bacterial tracheitis and epiglottitis

Summary of Croup Syndromes • • • Ball and Bindler, p. 838 Acute spasmodic laryngitis Laryngotracheo-bronchitis Bacterial tracheitis Epiglottitis

Classic parameters that distinguish each condition: • Acute spasmodic croup peaks at night, resolves by morning but reoccurs • High fevers are associated with the bacterial syndromes: Bacterial Tracheitis and Epiglottitis, which are treated with antibiotics • The child with LTB sounds worse than they look: the child with Epiglottitis is worse than they sound.

LTB: Laryngotracheobronchitis • most common: 3 mo-8 yrs • potential for airway obstruction esp in younger age group • Influenza, Parainfluenza types I and II, RSV; esp seen in winter. • barking cough, inspiratory stridor, retractions.

Epiglottitis: Supraglottitis • inflammation and subsequent edema of the epiglottis causing airway obstruction within minutes to hours. • Causes: HIB, staphylococcus and streptococcus • Recent decreased incidence with increased immunization rates of HIB vaccine. • Avoid making the child cry to avoid desat and increased laryngospasm.

Epiglottitis: Special Considerations • life threatening with rapid progression • drooling, incr HR/RR, prefer sitting upright, with chin thrust • avoid throat culture, tongue depressor or palpation of the tonsillar fossa, as this manipulation could produce severe laryngospasm • if suspected, keep pt calm, transport in sitting position with O 2: alert ENT.
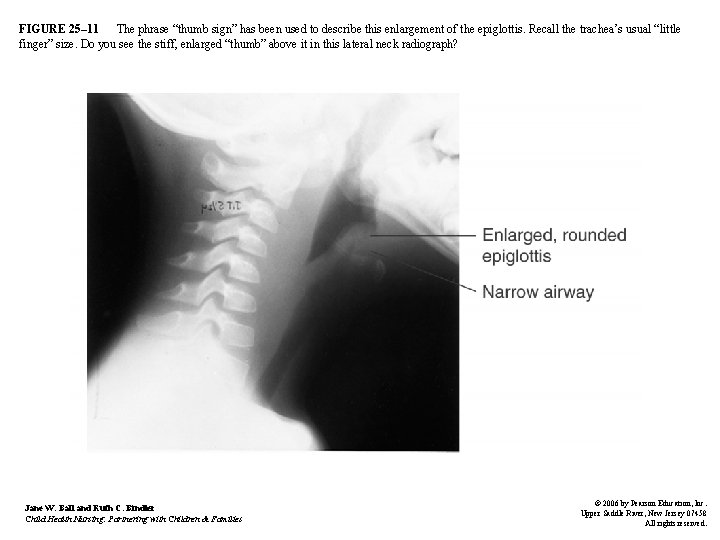
FIGURE 25– 11 The phrase “thumb sign” has been used to describe this enlargement of the epiglottis. Recall the trachea’s usual “little finger” size. Do you see the stiff, enlarged “thumb” above it in this lateral neck radiograph? Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

Case Presentation • Three yr old presents with a few days of URI symptoms with low grade fever (<102), now develops hoarseness and barking cough. Appetite less than usual but still drinking clear liquids and voiding 5 x/day. Clear nasal discharge which he clears with his sleeve; wakes up at night coughing. Is cranky but consolable. Temp 100 ax, HR 130, RR 28, sat 95% RA in no distress. Color good. Chest coarse; no retr.

Assessment of Case Presentation • What other questions would you like to ask the parent to determine data needed? • Any further assessment or tests needed? • What behaviors in the child might signal that the child was experiencing increased airway distress? • What do you think the child has and why?

Management for Case Presentation • Might give a trial neb of Albuterol 2. 5 mg in 2 cc NS over 5 -10 min. Reassess response. • Monitor for signs of stridor, F/G/R, activity, ability to take fluids, breath sound quality. • If sats are > or = 95% on RA even with activity, there is no suspicion of epiglottitis or air way narrowing on lateral neck xray (steeple sign), and good aeration, would give parameters for home management.

Parameters for Home Management • Assess parents ability to assess child, and obtain emergency help if needed • If child awakes with barking cough and stridor, and/or has coughing with increased work of breathing, either bring into the bathroom with shower on and door closed (fan off) or bring outside in cool night air (wrap in a coat or blanket) for a few minutes. Distress usually subsides.

Home Management continued • If coughing subsides with this cool humidification treatment, offer clear liguids and settle back to sleep. Can give a home neb of Albuterol or even just mist. Episode my reoccur. • If respiratory distress continues despite these efforts, bring to the nearest ER or call 911 if color poor, child is limp or lethargic, child drooling, quiet and wants to sit up.

Asthma • chronic inflammatory disorder with acute exacerbations or persistent symptoms • effects the large and small airways with increased mucous production, swelling and bronchospasm • triggers: exercise, infection, allergies and environmental irritants (second-hand smoke abrupt change in weather).

Pathophysiology • Multiple allergic pathways may be stimulated: Ig. E, Leukotrienes, Compliment. • Airway swelling and spasm results in airway narrowing, particularly significant in children with smaller airways. • Air trapping occurs distal to mucus plugs • Bronchospasm/coughing can feed into the cycle of anxiety which further increases the bronchospasm.

Acute Care Management • Assess for degree of respiratory distress: RR, HR, color/O 2 sat, F/G/R, cap refill. • Breath sounds, air movement, I/E ratio, peak flow (if able). • Nebulizer with O 2 via mask of Albuterol/Atrovent, (or Xopenex); use Epinephrine if respiratory distress is severe. • Start steroids at 1 -2 mg/Kg/day divided BID.
Acute Care Management( cont): • assess fluid status; increased RR leads to increased insensible loss of water, dries out mucous airways and risk of aspiration. • Monitor output: number of wet diapers/day, number of voids or actual measurement • provide emotional support for child and parents. • promote rest to conserve energy, decrease O 2 need and decrease bronchospasm

FIGURE 25– 17 Acute exacerbations of asthma may require management in the emergency department. The child is placed in a semisitting position to facilitate respiratory effort. Providing support to both the child and parent is an important part of nursing care during these acute episodes. The mother is exhausted after a sleepless night of caring for her son. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.
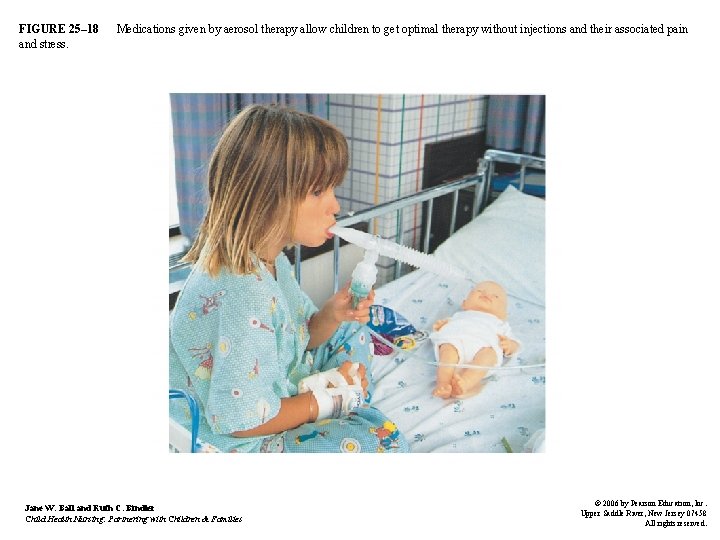
FIGURE 25– 18 and stress. Medications given by aerosol therapy allow children to get optimal therapy without injections and their associated pain Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

Management at Home • Primary goal is prevention • use peak flow meter to monitor degree of obstruction; divided into zones • avoid triggers: – refer to allergist to determine if candidate for desensitization (shots) – maintenance meds to avoid histamine and/or leukotriene stimulation • rescue agent for acute symptoms: Albuterol

Home management cont. • Determine need for a home nebulizer vs spacer used with an MDI (metered dose inhaler). • Keep a home log of need for treatment and adjustments in the environment, activity, diet, etc. • Determine need for steroids for maintenance and prevention • Determine a clear follow-up plan.

Revised Asthma Severity Classification • 2002 National Asthma Education and Prevention Program Classification System of Asthma Severity

Mild Intermittent • • brief exacerbations < 2 x/wk night time symptoms < 2 x/month PEFR > or = 80% quick relief with bronchodilators PRN, but if needed > 2 x/wk then moves to the next level.

Mild Persistent • • • exacerbations > 2 x/wk but < 1 x/day. Night time sx > 2 x/month May affect activity PEFR > or = 80% daily anti-inflammatory med. Quick relief bronchodilator PRN
Moderate Persistent • • daily symptoms daily short-acting beta-agonist exacerbations >2 x/wk; lasts for days night time sx > 1 x/wk affects activity PEFR >60% but <80% daily anti-inflammatory meds; medium dose bronchodilator up to 3 x/day

Severe Persistent • • continuous symptoms limited physical activity frequent exacerbations frequent night time sx PEFR , 60% but >30% daily anti-inflammatory; high dose bronchodilator up to 3 x/day

Status Asthmaticus • severe, unrelenting respiratory distress with bronchospasm • persists despite medication and supportive interventions • medical emergency requiring endotracheal intubation with assisted ventilation

Lower Airway Disorders • • • Bronchopulmonary Dysplasia Bronchiolitis Pneumonia Cystic Fibrosis Foreign body aspiration

Bronchopulmonary Dysplasia: Patho • acute lung injury with abnormal xray findings and persistent oxygen need beyond 36 wks gestational age. • Seen more often in preterms and those treated with long term ventilatory support • results in fibrosis and edema of the bronchioles with smooth muscle hypertrophy

BPD: clinical manifestations • sx resp distress: tachypnea, wheezing, crackles/rales, irritability, F/G/R, pulmonary edema, FTT, barrel chest. • Cyanosis if severe or accompanied by cardiac anomalies • Normal activities such as feeding, playing or a mild URI, increases oxygen demands and therefore can precipitate respiratory distress

BPD: medical management • symptomatic treatment and support • humidified 02 to keep sats 90 -92% even during feeding and sleeping • CPT 3 -4 x/day or as needed, preceeded by bronchodilator nebs (Albuterol, Xopenex), diuretics (Lasix, Aldactone), Antiinflammatories(steroids: Dexamethasone, Me thylprednisolone, Prednisone/Prednisolone), inhaled steroids (Pulmocort, Flovent).

FIGURE 25– 14 Many children with BPD are cared for at home, with the support of a home care program to monitor the family’s ability to provide airway management, oxygen, and support. This premature infant girl, who is now 4 months old but weighs only about 5 pounds, requires respiratory support with oxygen. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

BPD: nursing management • promote respiratory function, nl G+D. • preparing the family for home care needs • close monitoring of RR, HR, color, behavior changes, and how the family unit is coping with caring for this child with special needs. • Clear parameters for follow up in an acute exacerbation: readmission to the hosp is common and become ill very quickly.

Bronchitis • inflammation of the trachea and bronchi • usually follows a URI esp in children <4 yr. • Usually viral but can be bacterial: xray may be indicated • treatment usually supportive with close monitoring for worsening of symptoms. • Coarse breath sounds, wheezing, hacking cough, worse at night, fatigue, decreased appetite and interest in play.

Bronchiolitis • variation of severity of respir distress • <2 mo hospitalized; , 6 mo more severe disease than older infant • inflammation and destruction of smaller airways • caused by viruses: Influenza type A & B, Parainfluenza, RSV. • Can also be caused by bacteria or mycoplasma (but less likely).

Respiratory Syncytial Virus: RSV • transmitted through close or direct contact • viruses act like parasites and invade the mucosal cells • cells die, bursts and the resultant debris clogs and obstructs the bronchioles • in response, airways swell, produce excess secretions causing obstruction and bronchospasm. • Apnea and pulmonary edema may occur

RSV: clinical manifestations • URI, fever, clear rhinitis progressing to wheezing/coarse breath sounds, increased work of breathing, F/G/R. • Appear progressively more ill as sx of resp distress develop • less po intake, less energy/activity, incr sleepiness or irritability.

RSV: clinical therapy • chest xrays are not specific unless the child has a pneumonia as well • viral cultures are done on the nasal secretions and child is put on contact precautions until cultures come back neg (if positive, precautions continue) • respirations are supported with humidified 02 to keep sats by oxymetry >93% • CPT, sx VS, contact prec, hand washing.

RSV: medical management • Ribavirin: only antiviral drug available. Questionable effectiveness; reserved for severe, life-threatening cases. • Evidence that RSV in early childhood increases the risk of asthma in later childhood and COPD later in life. • Recomm premies and children with underlying medical conditions during their first RSV season (Oct-Mar) with Synagis.

Synagis for children at risk • passive immunity with monoclonal antibody specific to RSV • IM inj given 1 x/mo Oct-April to those born <37 wks, and/or have cong heart disease, asthma, BPD, or immunosuppression (and other chronic diseases). • Day care, shelters, high density group living and older siblings also increase the risk of the child contracting RSV.

Pneumonia • inflammation or infection of the bronchioles and alveolar spaces of the lungs • viral, bacterial or mycoplasma in origin(latter two are treated with A/B) • end result from all causes is exudate that fills alveolar spaces, creating areas of plugging and consolidation that can interfere with gas exchange.

Pneumonia: clinical manifestations and nursing management • similar to bronchiolitis • in addition, use of Tylenol or Ibuprofen for fever and pain control • frequent persistent coughing can cause muscle strain and interrupted sleep for both child and parent. • Cough suppressants are not routinely advised for young children • supportive therapy: fluids/nutr/02 if indic.

Cystic Fibrosis • common inherited autosomal recessive disorder • involves the exocrine glands which excrete a thick fluid that affects functioning of the respiratory, GI, endocrine, skin and reproductive systems. • Predominantly seen in the white population • equal distribution among gender • median life span is 30 yrs.

FIGURE 25– 20 Cystic fibrosis is an inherited autosomal recessive disorder of the exocrine glands, so it is not uncommon to see siblings with it such as this brother and sister. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

CF: clinical manifestations • 600 mutations with variation of severity • all types affect multiorgan systems: • lungs become plugged with thick mucous that can not be expectorated, causing atelectasis and air trapping. Secondary infections are common and are combatted by scheduled hosp. admissions for “clean outs”

CF: clinical manifestations • pancreatic ducts become blocked: enzymes can’t adequately digest food – poor absorption of nutrients; weight loss, FTT, resulting in foul smelling, frothy, floating and fat containing stools. – Insulin dependent diabetes is not uncommon as the child ages (adolescence). • Sterility or decreased fertility is common due to increased mucous secretions

CF: Primary presentation and diagnosis • • • meconium ileus in the new born small bowel obstruction as a young infant fecal impaction and/or intussusception steatorrhea (fatty stools) productive cough, frequent URI’s, weight loss • elevated Chloride on a Sweat Test (>50 -60)
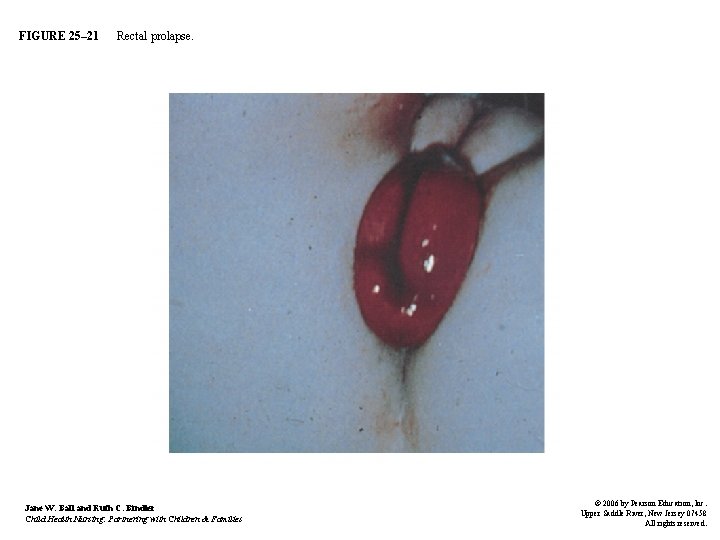
FIGURE 25– 21 Rectal prolapse. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

FIGURE 25– 22 Digital clubbing. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.
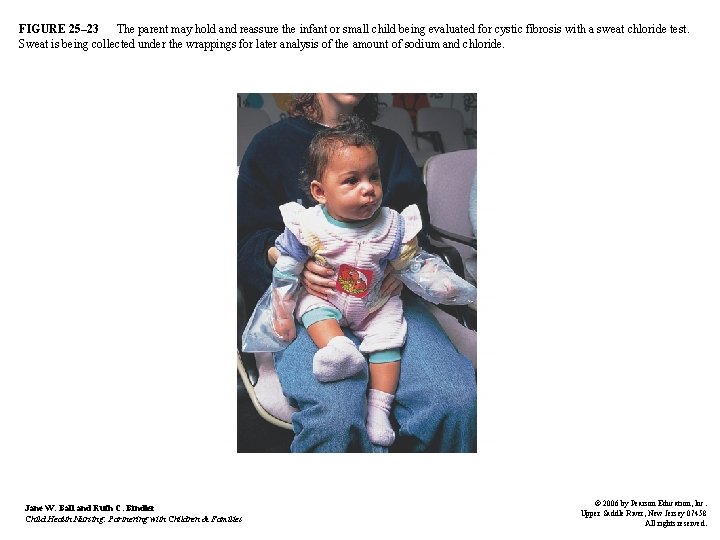
FIGURE 25– 23 The parent may hold and reassure the infant or small child being evaluated for cystic fibrosis with a sweat chloride test. Sweat is being collected under the wrappings for later analysis of the amount of sodium and chloride. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

CF: Clinical Therapy • maintaining respiratory function: nebs/CPT TID/PD/vibration/expectoration • supportive 02 as needed • managing infection: maintenance A/B, then clean outs and high dose antibiotics when hospitalized. • Avoid colonization and cross contamination with other Cystic Fibrosis kids. • Optimal GI absorp and avoid obstruction
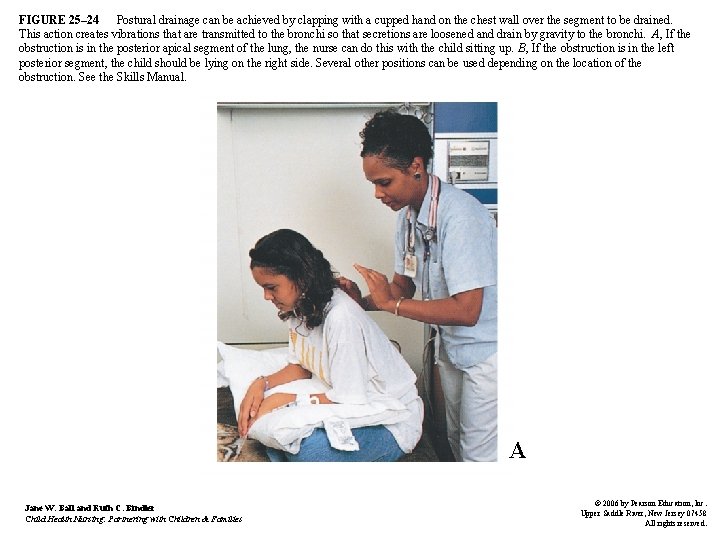
FIGURE 25– 24 Postural drainage can be achieved by clapping with a cupped hand on the chest wall over the segment to be drained. This action creates vibrations that are transmitted to the bronchi so that secretions are loosened and drain by gravity to the bronchi. A, If the obstruction is in the posterior apical segment of the lung, the nurse can do this with the child sitting up. B, If the obstruction is in the left posterior segment, the child should be lying on the right side. Several other positions can be used depending on the location of the obstruction. See the Skills Manual. A Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

Foreign Body Aspiration • at risk: infants>6 mo, toddlers, preschoolers during exploration and experimentation • schoolage and teens d/t activity while eating, too much in the mouth or eating too fast.
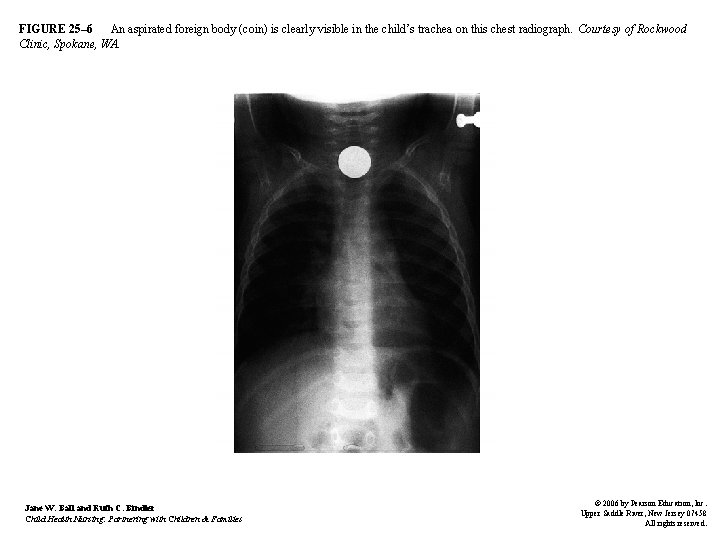
FIGURE 25– 6 An aspirated foreign body (coin) is clearly visible in the child’s trachea on this chest radiograph. Courtesy of Rockwood Clinic, Spokane, WA. Jane W. Ball and Ruth C. Bindler Child Health Nursing: Partnering with Children & Families © 2006 by Pearson Education, Inc. Upper Saddle River, New Jersey 07458 All rights reserved.

FBA: clinical manifestations • coughing, choking, gagging, dyphonia and wheezing; decreased breath sounds on one side, stridor and possible respiratory distress. • FB in bronchus is better tolerated; in trachea is life threatening • can migrate to R main stem bronchus to R lung d/t anatomical slope.

FBA: clinical management • in air way obstruction: chest thrusts and back blows in the infant. • Abdominal thrusts in the child over 8 yrs. • if partially obstructed: xray indic of chest (A/P & lateral) and lateral film of the neck. • Bronchoscopy under sedation may be necessary to remove object or sometimes, surgery. • Best therapy is prevention.
- Slides: 69