
Advice for Primary Care Referrers to ENT Mr

















- Slides: 20
Advice for Primary Care Referrers to ENT Mr. Mark Draper
Nasal Blockage • Initial Rx with ≥ 4/52 topical nasal steroid • Any patient on regular decongestants needs to stop for ≥ 2/52 – Rx TNS e. g. Flixonase during this 2/52 period • (slightly reduces rebound effect) • Reassess. If still symptomatic consider GPw. SI referral • If obvious DNS or severe external deformity – refer 2 o care
Nasal Fracture • Wait 5 days for swelling to subside slightly • If deviation and wants realignment, refer to 2 o care via Emergency ENT clinic – (contact on-call SHO during office hours)
Nasal Fracture • Wait 5 days for swelling to subside slightly • If deviation and wants realignment, refer to 2 o care via Emergency ENT clinic – (contact on-call SHO during office hours)
Rhinorrhoea • Initial treatment with ≥ 4/52 topical nasal steroid spray +/oral antihistamine • If coloured discharge then use saline/bicarbonate douching plus 2 weeks oral ABs (Co. Amoxiclav or Clarithromycin) • Referral suitable for GPw. SI
Douching
Hyposmia/Anosmia • Initial Rx with ≥ 4/52 topical nasal steroid • Referral suitable for GPw. SI
Rhinitis • Large variability of response to differing TNS sprays. – Trial ≥ 2 different sprays + oral AH prior to considering referral – Flixonase, Nasonex & Avamys tend to be more successful than Beconase • Consider Dymista spray as 2 nd line treatment • Referral suitable for GPw. SI
Epistaxis
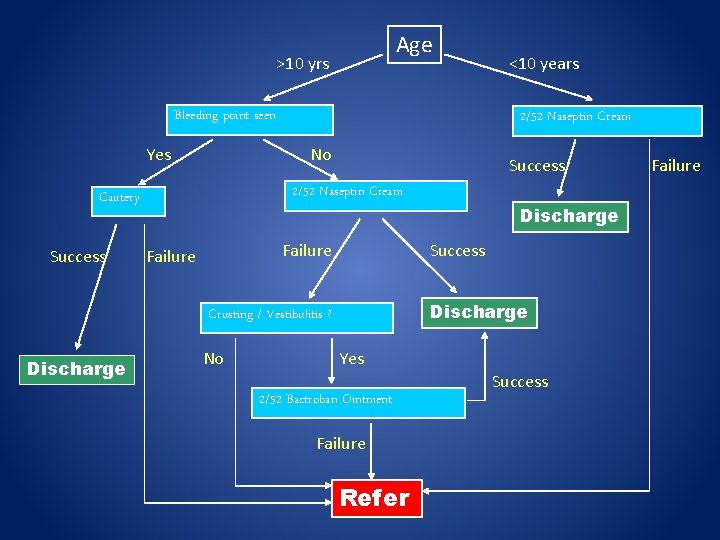
Age >10 yrs Bleeding point seen Yes Success 2/52 Naseptin Cream No Success 2/52 Naseptin Cream Cautery Failure No Discharge Success Discharge Crusting / Vestibulitis ? Discharge <10 years Yes 2/52 Bactroban Ointment Failure Refer Success Failure
• Cautery Tips – Lignocaine/Phenylephrine spray – Cotton wool soaked into nostril – Leave for 15 minutes – Fresh Ag. NO 3 stick for each application – May take 48 -36 hrs for full effect
Facial Pain • If no nasal blockage or rhinorrhoea, then extremely unlikely to be sinus/nose related
(European Position Paper on Rhinosinusitis and Nasal Polyps 2007) – Inflammation of nose + sinuses characterised by ≥ 2 symptoms, one of which should be either nasal blockage/ obstruction/ congestion or nasal discharge (anterior/ posterior nasal drip): • ± Facial pain or pressure, • ± Hypo / anosmia; – AND EITHER signs of: • Polyps and/or; • Mucopus primarily from middle meatus and/or; • Oedema/mucosal obstruction primarily in middle meatus, – AND / OR CT changes: • Mucosal changes within OMC and / or sinuses
Facial Pain • If no nasal blockage or rhinorrhoea, then extremely unlikely to be sinus/nose related • Consider myofascial syndrome / tension-related disorders • Referral suitable for GPw. SI
Hoarseness • Intermittent – Consider voice care advice +/- PPI / Reflux advice www. britishvoiceassociation. org. uk • Referral suitable for GPw. SI / 2 o care • Constant – Refer via 2 WW pathway
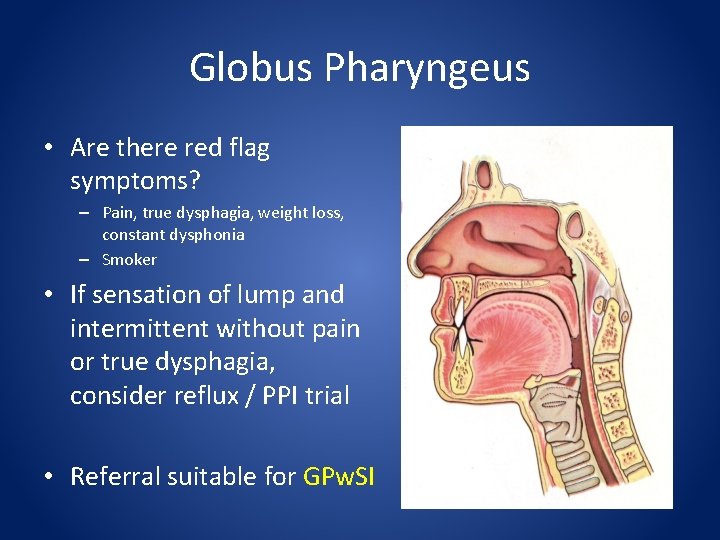
Globus Pharyngeus • Are there red flag symptoms? – Pain, true dysphagia, weight loss, constant dysphonia – Smoker • If sensation of lump and intermittent without pain or true dysphagia, consider reflux / PPI trial • Referral suitable for GPw. SI
‘Catarrh’ / ‘Post nasal drip’
‘Catarrh’ / ‘Post nasal drip’ • Most likely globus-type diagnosis • If no nasal symptoms, extremely unlikely to be related to nose/sinus. • Psychogenic viscious circle • Advise re Voice care / Stop Throat Clearing / Reflux advice / PPI trial • Referral suitable for GPw. SI
Snoring • If unconnected to nasal blockage – Do not refer to ENT • ‘Simple’ snoring – Wt loss, alcohol, mandibular advancement splint www. britishsnoring. co. uk • Suspected OSA – Respiratory Department referral