
ADRENAL DISORDERS Introduction Dr Atallah AlRuhaily Consultant Endocrinologist




































- Slides: 64
ADRENAL DISORDERS - Introduction Dr. Atallah Al-Ruhaily Consultant Endocrinologist
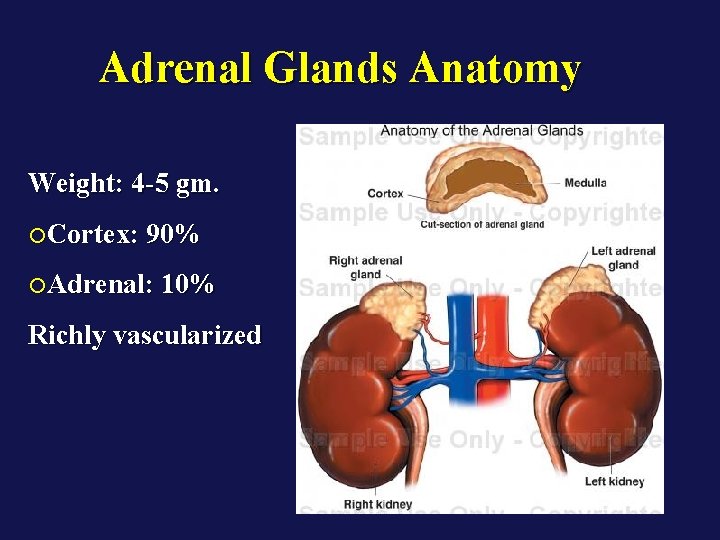
Adult Adrenal Glands n Each gland weighs 4 -5 g. n Location: in the retroperitoneum above or medial to the upper poles of the kidneys. n Surrounded by a fibrous capsule. n The yellowish outer cortex comprises 90% of adrenal weight. n The inner medulla 10% of adrenal weight.
Adrenal Glands Anatomy Weight: 4 -5 gm. Cortex: 90% Adrenal: 10% Richly vascularized
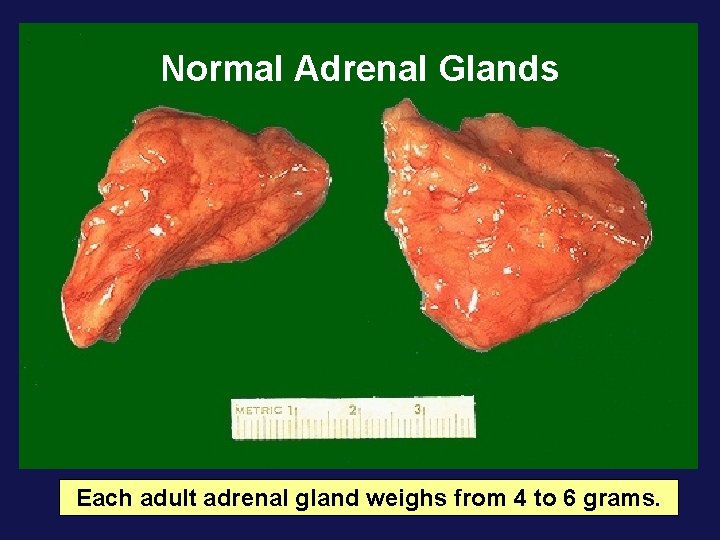
Normal Adrenal Glands Each adult adrenal gland weighs from 4 to 6 grams.
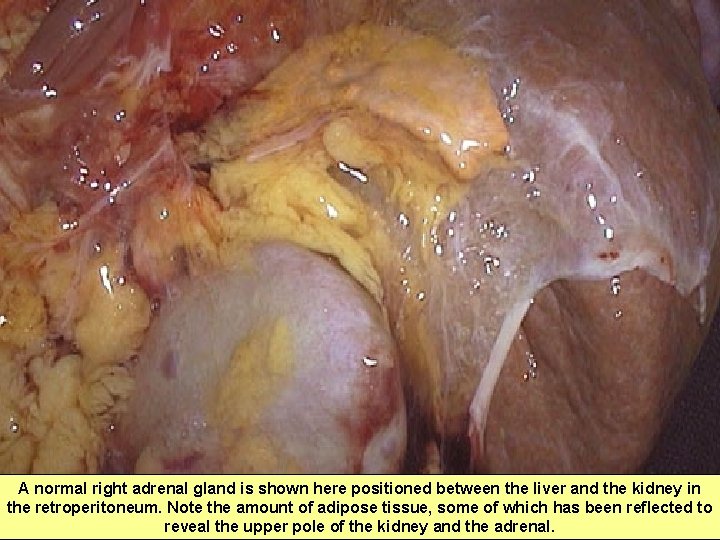
A normal right adrenal gland is shown here positioned between the liver and the kidney in the retroperitoneum. Note the amount of adipose tissue, some of which has been reflected to reveal the upper pole of the kidney and the adrenal.
Embryology of Adrenal Cortex is of mesodermal origin. Identifiable as a separate organ at the 2 month-old -fetus. At this stage, composed of: § Fetal zone o additional zone in fetus o makes up the main bulk of weight at this time. o lost in the 1 st year (usually within 3 months after birth). § Definitive zone o The origin of the adrenal cortex.
Embryology of Adrenal Cortex Fetal adrenal increases rapidly in size (Larger than the kidney at mid-gestation & much larger than adult gland in relation to total body mass). Fetal adrenal produces mainly DHEA & DHEA-S (precursors of maternal-placental estrogen). Definitive zone synthesizes various steroids mainly cortisol.
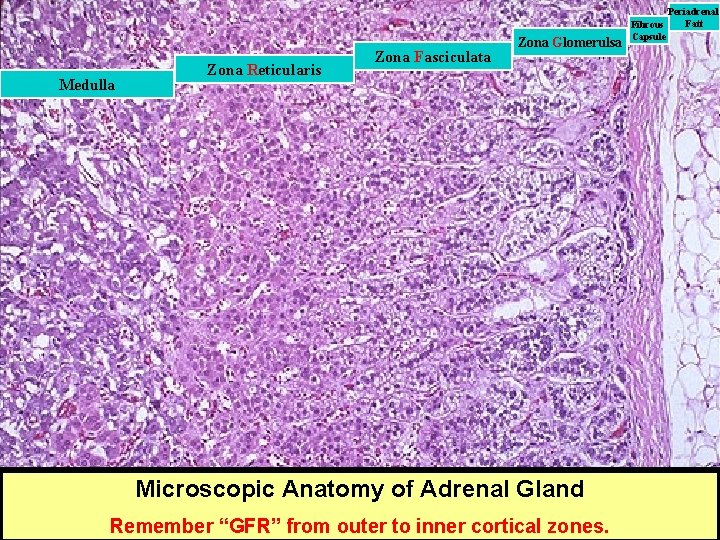
Embryology of Adrenal Cortex The anatomic relationship of fetal and definitive zones is maintained until birth. Adrenocortical weight decreases gradually until the fetal zone disappears 3 months after delivery. During the first 3 years, the adult adrenal cortex develops and differentiates into 3 adult zones: • Zona Glomerulosa • Zona Fasciculata • Zona Reticularis
Embryology of Adrenal Medulla ØMedullary chromaffin cells (the principal cells of adrenal medulla) develop from the neural crest. ØDuring development the medullary cells migrate and lie surrounded by the cortex.
Adrenal gland is composed of 2 distinct compartments Adrenal Cortex Produces many steroid hormones; the most important of which are: § Cortisol § Aldosterone § Adrenal Androgens Adrenal Medulla Produces Catecholamines: § Adrenaline (Epinephrine) § Noradrenaline (Norepinephrine)
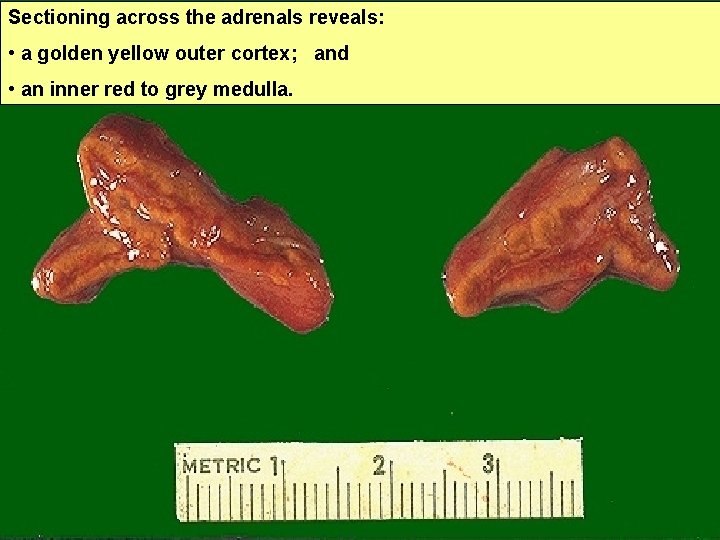
Sectioning across the adrenals reveals: • a golden yellow outer cortex; and • an inner red to grey medulla.
Medulla Zona Reticularis Zona Fasciculata Zona Glomerulsa Microscopic Anatomy of Adrenal Gland Remember “GFR” from outer to inner cortical zones. Fibrous Capsule Periadrenal Fatt
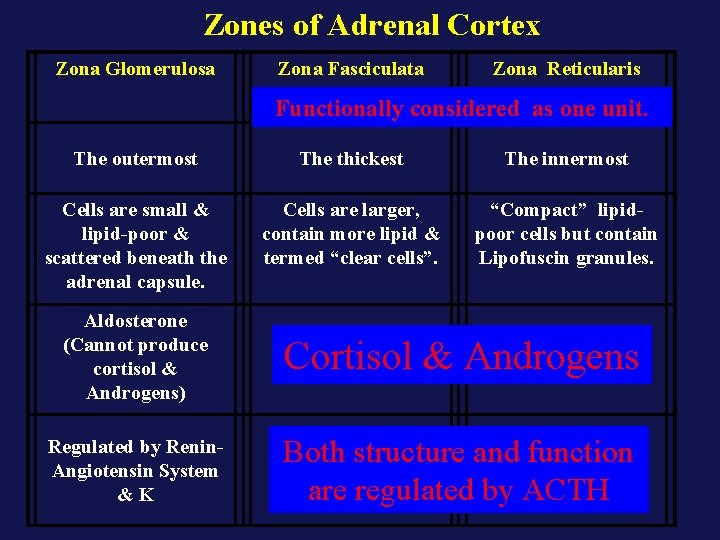
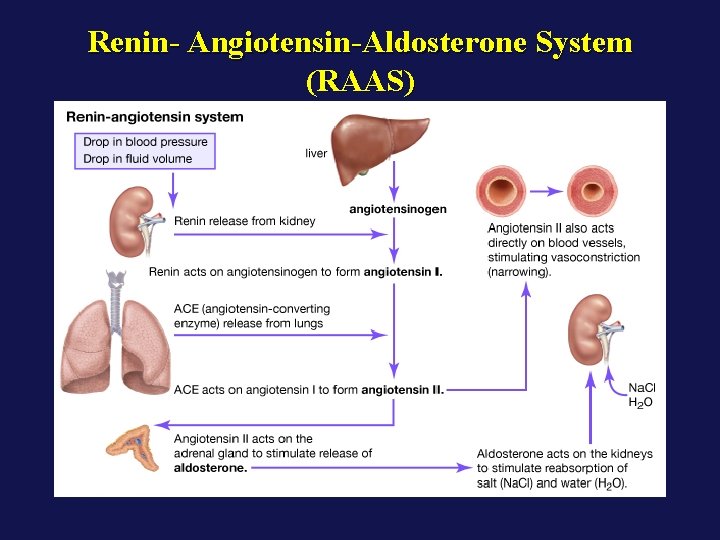
Zones of Adrenal Cortex Zona Glomerulosa Zona Fasciculata Zona Reticularis Functionally considered as one unit. The outermost The thickest The innermost Cells are small & lipid-poor & scattered beneath the adrenal capsule. Cells are larger, contain more lipid & termed “clear cells”. “Compact” lipidpoor cells but contain Lipofuscin granules. Aldosterone (Cannot produce cortisol & Androgens) Cortisol & Androgens Regulated by Renin. Angiotensin System & K Both structure and function are regulated by ACTH
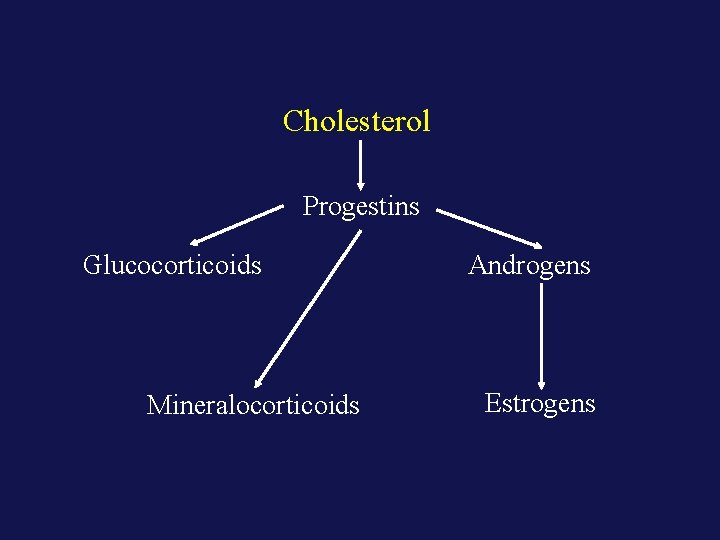
Classification of Adrenal Steroids Three groups (based on their predominant functions): 1. Glucocorticoids 2. Mineralocorticoids 3. Androgens
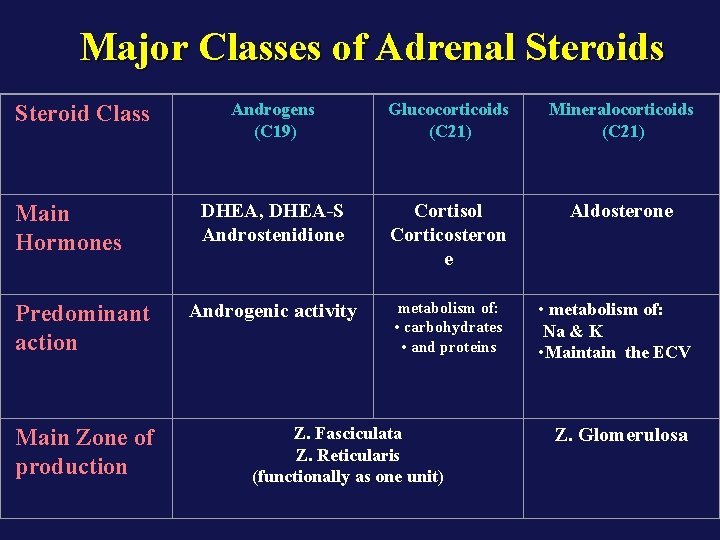
Major Classes of Adrenal Steroids Steroid Class Main Hormones Predominant action Main Zone of production Androgens (C 19) Glucocorticoids (C 21) Mineralocorticoids (C 21) DHEA, DHEA-S Androstenidione Cortisol Corticosteron e Aldosterone Androgenic activity metabolism of: • carbohydrates • and proteins Z. Fasciculata Z. Reticularis (functionally as one unit) • metabolism of: Na & K • Maintain the ECV Z. Glomerulosa
Cholesterol Progestins Glucocorticoids Mineralocorticoids Androgens Estrogens
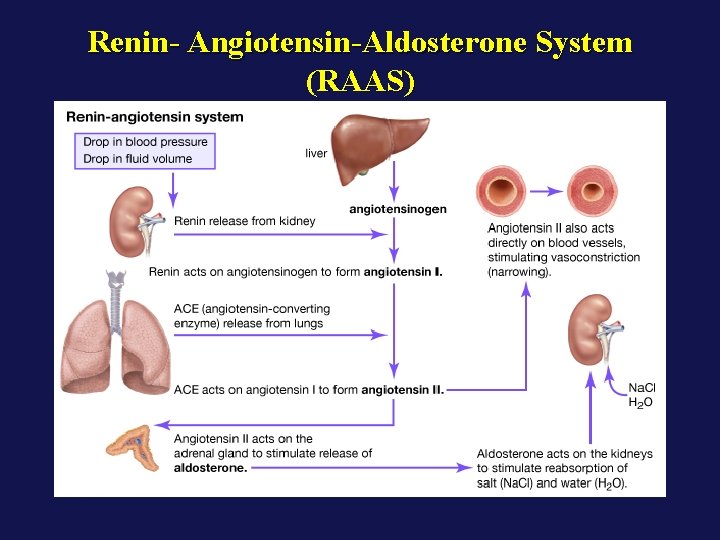
Renin- Angiotensin-Aldosterone System (RAAS)
Disorders of Adrenal Glands Adrenal Cortex • Addison’s disease • Cushing’s syndrome • Hyperaldoteronism • Congenital Adrenal Hyperplasia (CAH) • Hirsutism • Virilization Adrenal Medulla • Pheochromocytoma
Adrenal Insufficiency Adrenocortical insufficiency (hypofunction of the adrenal cortex) includes all conditions in which there is deficient production of: • Adrenal glucocorticoids • Mineralocorticoids hormones.
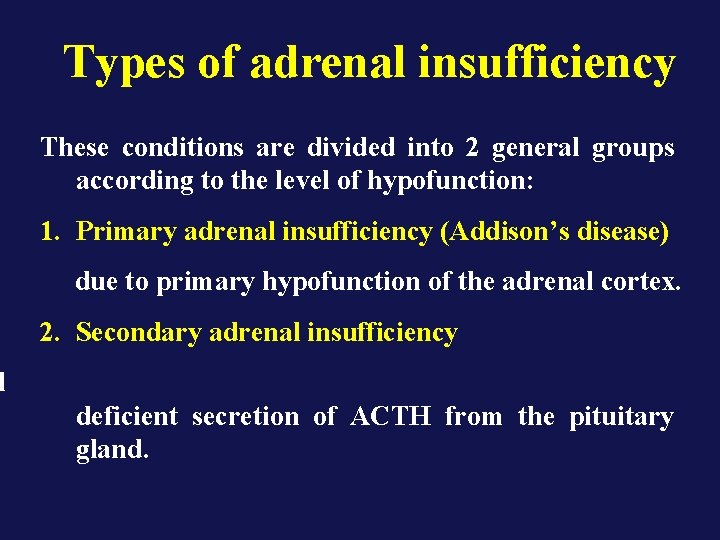
Types of adrenal insufficiency These conditions are divided into 2 general groups according to the level of hypofunction: 1. Primary adrenal insufficiency (Addison’s disease) due to primary hypofunction of the adrenal cortex. 2. Secondary adrenal insufficiency l deficient secretion of ACTH from the pituitary gland.
Etiology of Primary Adrenal Insufficiency A. Anatomic destruction of gland (chronic & acute) 1. “Idiopathic” atrophy (autoimmune) 2. Surgical removal 3. Infection (Tb. , fungal, viral-esp. AIDS) 4. Adrenal Hemorrhage 5. Invasion: metastases, amyloidosis, sarcoidosis B. Metabolic failure in hormone production 1. Congenital adrenal hyperplasia (CAH) 2. Enzyme inhibitors: (Metyrapone, Ketoconazole, Aminoglutethemide) 3. Cytotoxic agents: (Mitotane) C. ACTH-blocking Antibodies
Etiology of Secondary Adrenal Insufficiency 1. Hypopituitarism due to hypothalamicpituitary disease. 2. Suppression of hypothalamic-pituitary axis. • Exogenous steroids (Iatrogenic) • Endogenous steroids (from tumors)
Incidence Primary Adrenal Insufficiency: Relatively rare. Occurs at any age. affects both sexes equally. Secondary Adrenal Insufficiency: Relatively common (because of common therapeutic use of steroids).
Addison’s Disease: Etiology and Pathogenesis Addison’s disease results from progressive destruction of adrenal cortex. At least 90% of gland is destroyed before signs of insufficiency appear.
Addison’s Disease: Etiology and Pathogenesis 50% of patients have +ve circulating adrenal Abs. Some Abs destroy the adrenal glands, others block the binding of ACTH to its receptors. In addition, some patients have +ve Abs to thyroid, parathyroid and/or gonadal tissues. Polyglandular syndromes Autoimmune (PGA)
Associated Autoimmune Disorders Endocrine Disorders: • • • Chronic lymphocytic thyroiditis Premature ovarian failure DM type 1 Primary hypothyroidism Hyperthyroidism Nonendocrine Disorders: • • • Pernicious anemia Vitiligo Alopecia Chronic active hepatitis Nontropical sprue Myasthenia gravis
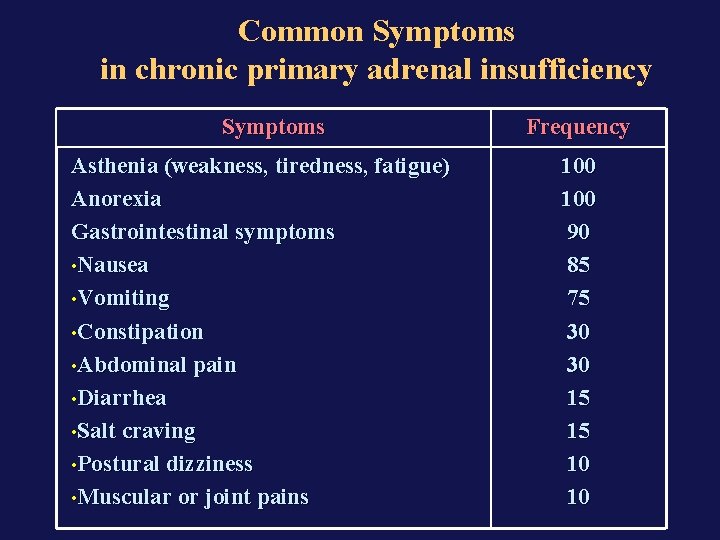
Common Symptoms in chronic primary adrenal insufficiency Symptoms Asthenia (weakness, tiredness, fatigue) Anorexia Gastrointestinal symptoms • Nausea • Vomiting • Constipation • Abdominal pain • Diarrhea • Salt craving • Postural dizziness • Muscular or joint pains Frequency 100 90 85 75 30 30 15 15 10 10
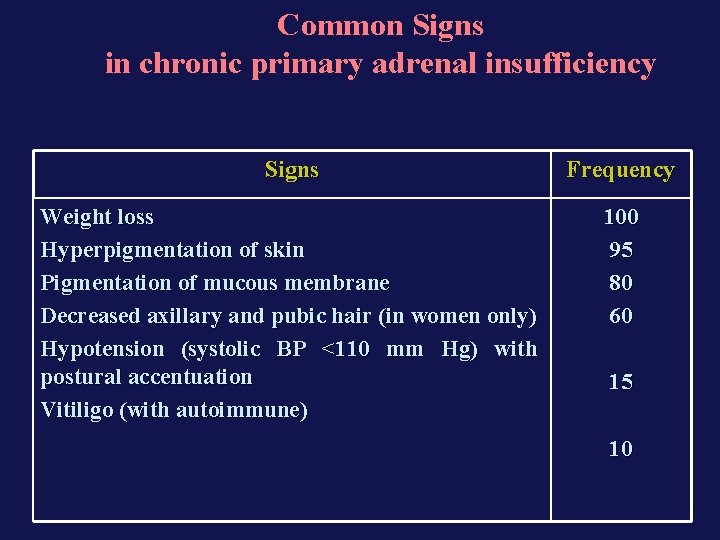
Common Signs in chronic primary adrenal insufficiency Signs Frequency Weight loss Hyperpigmentation of skin Pigmentation of mucous membrane Decreased axillary and pubic hair (in women only) Hypotension (systolic BP <110 mm Hg) with postural accentuation Vitiligo (with autoimmune) 100 95 80 60 15 10
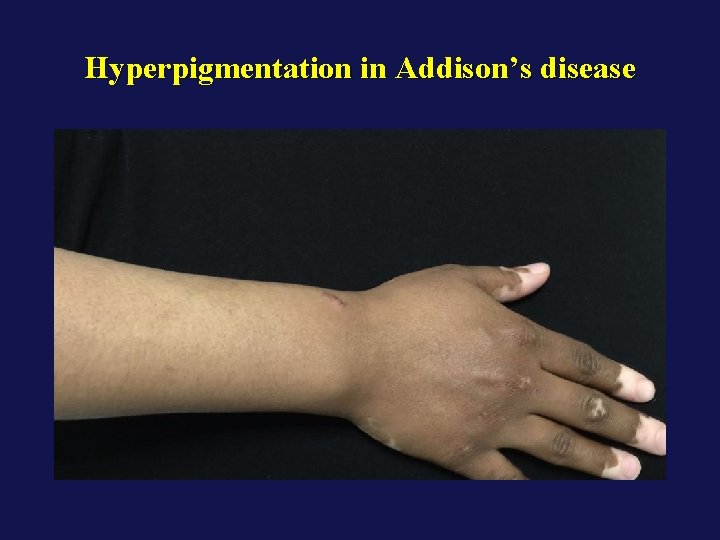
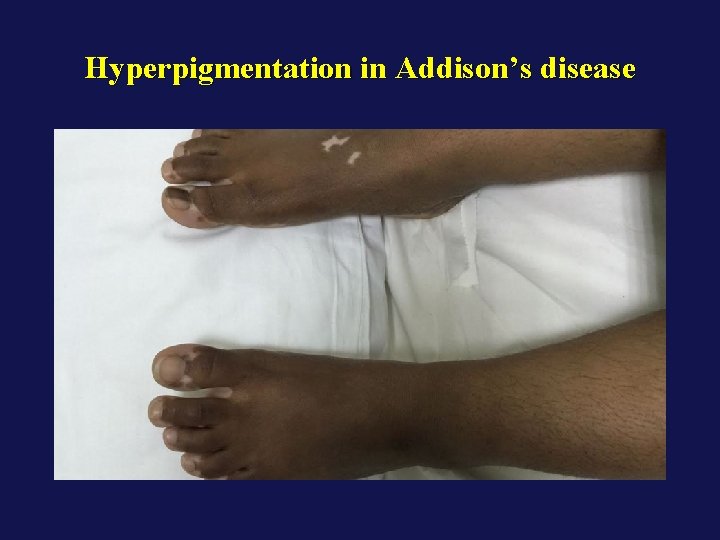
Hyperpigmentation n Generalized hyperpigmentation of skin & mucous membrane (the classical physical finding). n Along with other features, suggests primary adrenocortical insufficiency. n One of earliest manifestations of Addison’s disease.
Hyperpigmentation n Increased at exposed areas and accentuated at pressure areas (knuckles, toes, elbows, knees) n Associated with black or dark brown freckles. n Hperpigmentation of buccal mucosa & gum is preceded by generalized hyperpigmentation of skin. n Other areas: palmar creases, nail beds, nipples, areolae, perivaginal, perianal mucosa & scars that formed after onset of ACTH excess (but not older scars).
Hyperpigmentation in Addison’s disease
Hyperpigmentation in Addison’s disease
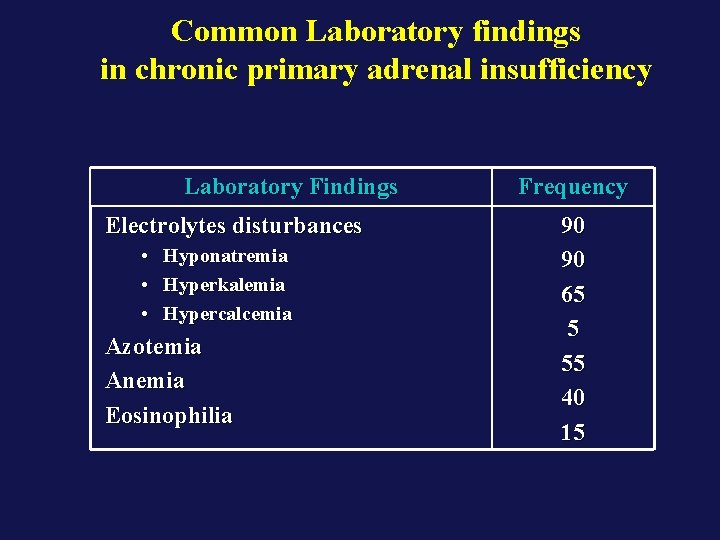
Common Laboratory findings in chronic primary adrenal insufficiency Laboratory Findings Electrolytes disturbances • Hyponatremia • Hyperkalemia • Hypercalcemia Azotemia Anemia Eosinophilia Frequency 90 90 65 5 55 40 15
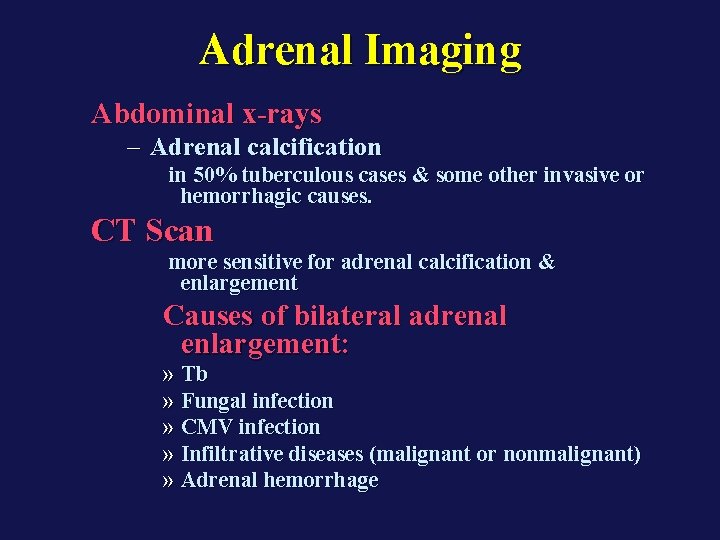
Adrenal Imaging Abdominal x-rays – Adrenal calcification in 50% tuberculous cases & some other invasive or hemorrhagic causes. CT Scan more sensitive for adrenal calcification & enlargement Causes of bilateral adrenal enlargement: » Tb » Fungal infection » CMV infection » Infiltrative diseases (malignant or nonmalignant) » Adrenal hemorrhage
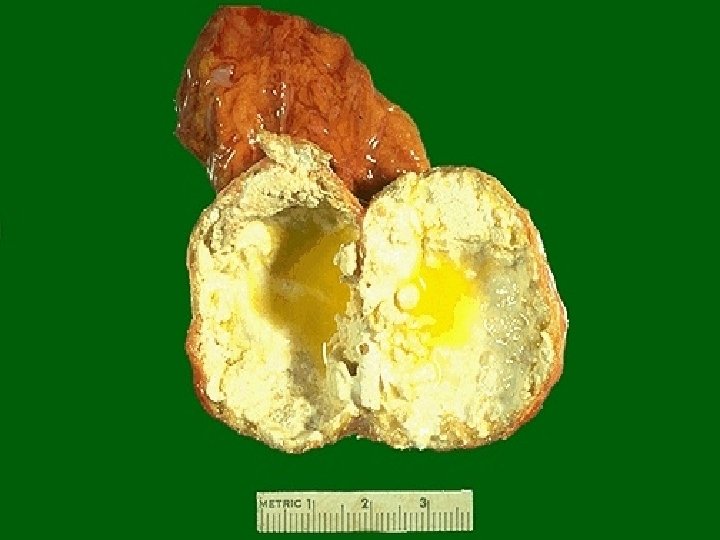
Rt Adrenal mass
Acute Adrenal Crisis A state of acute adrenal insufficiency occurring in patients with Addison’s disease who are exposed to any form of stress. Precipitating stress factors: 1. Infection 2. Trauma 3. Surgery 4. Dehydration (Salt deprivation, vomiting, diarrhea) 5. Discontinuation of steroids replacement therapy
Acute Adrenal Crisis: Clinical Features Common Clinical Features • Hypotension & shock • Fever (due to infection or hypoadrenalism per se) • Dehydration, volume depletion • Nausea, vomiting, anorexia • Abdominal pain (may mimic acute abdomen) • Weakness, apathy, depressed mentation • Hypoglycemia (more in children) Shock and coma may rapidly lead to death in untreated patients.
Acute Adrenal Crisis Laboratory Findings Suggestive of Diagnosis • Hyponatremia & Hyperkalemia (In a small number of acute cases). • Azotemia (usual) • Lymphocytosis • Eosinophilia • Hypoglycemia
Acute Adrenal Hemorrhage A progressively deteriorating condition resulting from bilateral adrenal hemorrhage and acute adrenal destruction in an already compromised patient with major illness.
Acute Adrenal Hemorrhage Manifestations • Abdominal, flank or back pain & abdominal tenderness (Less frequently, abdominal distention, rigidity & rebound tenderness). • Hypotension & shock • Fever • Nausea & Vomiting • Confusion & disorientation • Tachycardia
Acute Adrenal Hemorrhage With progression, the following manifestations may ensue: • Severe hypotension • Volume depletion • Dehydration • Hyperpyrexia • Cyanosis • Hypoglycemia • Coma • Death
Secondary Adrenal Insufficiency Causes n ACTH deficiency most commonly due to exogenous glucocorticoid therapy. n Pituitary & Hypothalamus tumors the most common causes of naturally occurring pituitary ACTH hyposecretion.
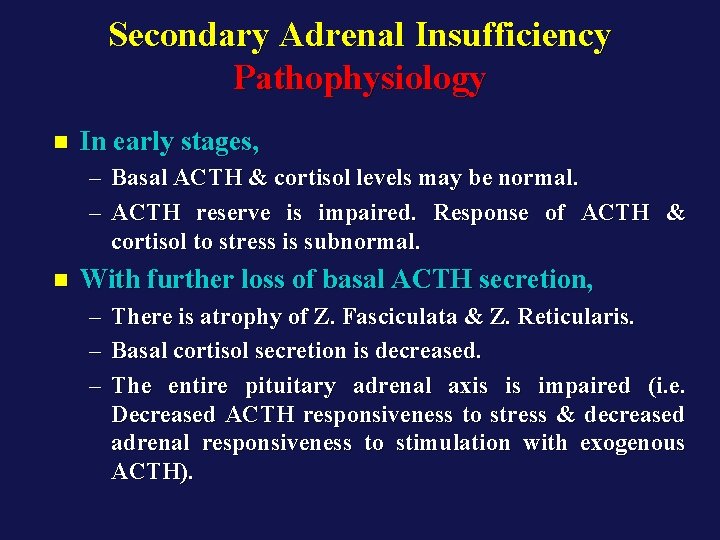
Secondary Adrenal Insufficiency Pathophysiology n ACTH deficiency is the primary event. n This leads to: – Decreased Cortisol & Androgen secretion. – But Aldosterone secretion remains normal except in few cases.
Secondary Adrenal Insufficiency Pathophysiology n In early stages, – Basal ACTH & cortisol levels may be normal. – ACTH reserve is impaired. Response of ACTH & cortisol to stress is subnormal. n With further loss of basal ACTH secretion, – – – There is atrophy of Z. Fasciculata & Z. Reticularis. Basal cortisol secretion is decreased. The entire pituitary adrenal axis is impaired (i. e. Decreased ACTH responsiveness to stress & decreased adrenal responsiveness to stimulation with exogenous ACTH).
Secondary Adrenal Insufficiency Clinical Features n Usually chronic nonspecific manifestations. n Acute crisis occurs in: – Undiagnosed patients – Patients who do not receive increased steroid dosage during periods of stress.
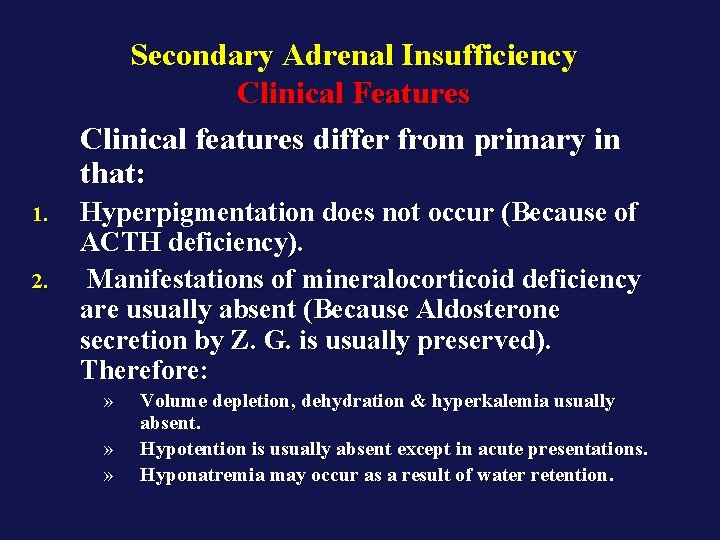
Secondary Adrenal Insufficiency Clinical Features Clinical features differ from primary in that: 1. 2. Hyperpigmentation does not occur (Because of ACTH deficiency). Manifestations of mineralocorticoid deficiency are usually absent (Because Aldosterone secretion by Z. G. is usually preserved). Therefore: » » » Volume depletion, dehydration & hyperkalemia usually absent. Hypotention is usually absent except in acute presentations. Hyponatremia may occur as a result of water retention.
Secondary Adrenal Insufficiency Clinical Features Prominent features (due to glucocorticoid deficiency) are nonspecific & include: – Weakness, lethargy & easy fatigability – anorexia, nausea & occasionally vomiting – Arthralgias & myalgias – Hypoglycemia – Acute decompensation with severe hypotension or shock unresponsive to vasopressors.
Secondary Adrenal Insufficiency Associated Features n The following additional features may be present: – History of glucocorticoid therapy or Cushingoid features. – Features of loss of other pituitary hormones (hypogonadism & hypothyroidism). – Features of hypersecretion of GH or PRL from pituitary adenoma. – Pressure symptoms from pituitary tumors.
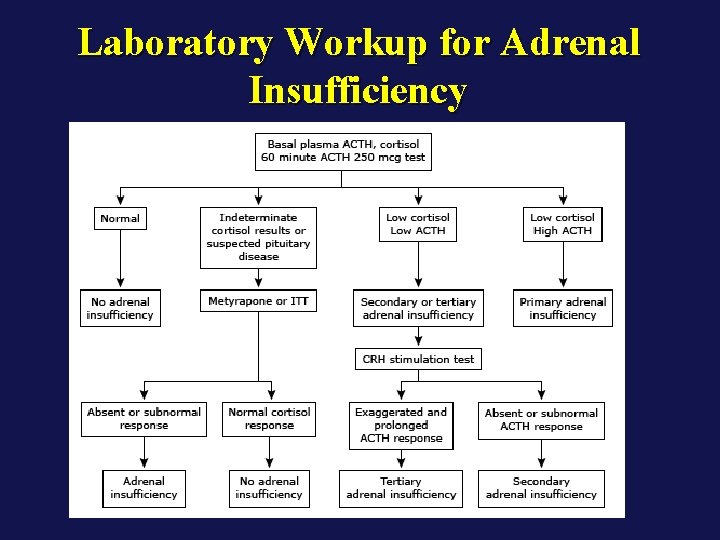
Laboratory Workup for Adrenal Insufficiency
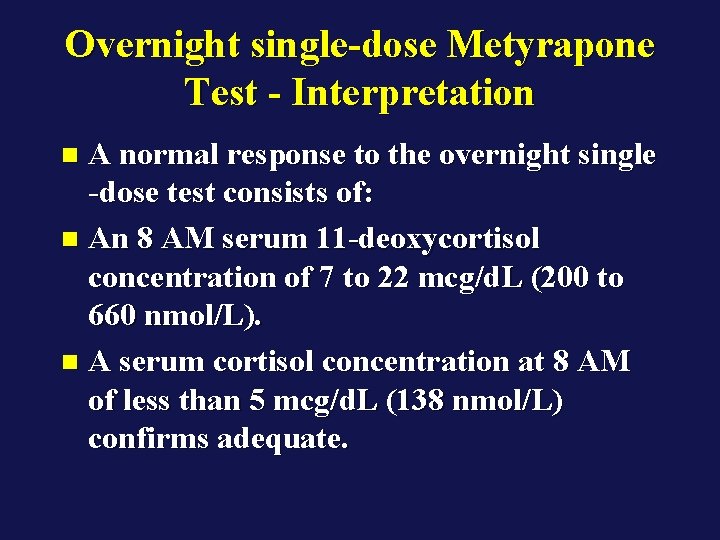
Overnight single-dose Metyrapone Test - Procedure Metayrapone : 30 mg/kg oral administration of Metyrapone at midnight with milk or snack. n Serum 11 -Deoxycortisol & Cortisol measurement (and ACTH level) 7: 30 9: 30 AM next morning. n
Overnight single-dose Metyrapone Test - Interpretation A normal response to the overnight single -dose test consists of: n An 8 AM serum 11 -deoxycortisol concentration of 7 to 22 mcg/d. L (200 to 660 nmol/L). n A serum cortisol concentration at 8 AM of less than 5 mcg/d. L (138 nmol/L) confirms adequate. n
Renin- Angiotensin-Aldosterone System (RAAS)
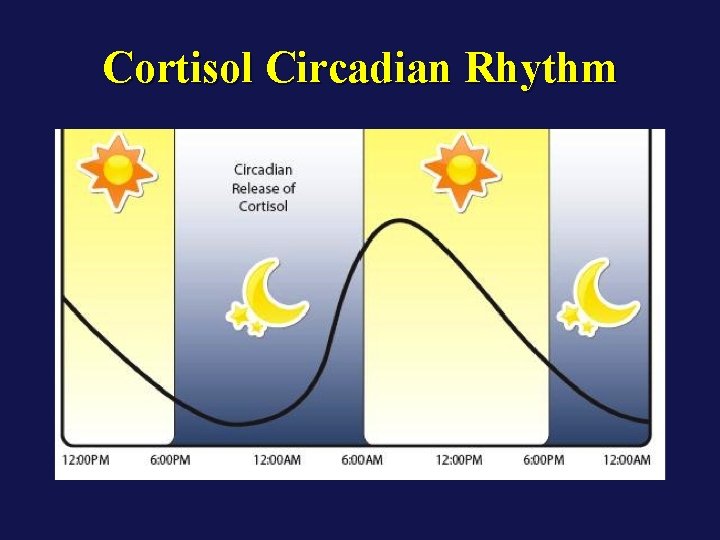
Cortisol Circadian Rhythm
Diagnosis of Adrenal Insufficiency 3 Stages of diagnosis confirmation: 1. Inappropriately low cortisol secretion? 2. . . A. Is cortisol deficiency dependent on or independent of corticotropin (ACTH) deficiency B. Evaluating mineralocorticoid secretion in patients without ACTH deficiency. 3. Is there a treatable cause of the primary disorder?
Diagnosis of Adrenal Insufficiency n Measuring non-specific anti-adrenal antibodies in serum by indirect immunofluorescence is not useful for establishing the diagnosis. n Antibodies directed to 21 -hydroxylase (P 450 c 21) identify nearly all patients with autoimmune adrenal insufficiency and is not positive in any patient with adrenoleukodystrophy-associated adrenal insufficiency.
Diagnosis of Adrenal Insufficiency Basal levels of adrenocortical steroids in plasma or urine may be normal in partial adrenal insufficiency. n Tests for adrenocortical reserve are necessary to establish the diagnosis. – Rapid ACTH Stimulation Test – Plasma ACTH Levels – Metyrapone Test – Insulin-induced Hypoglycemia – CRH Stimulation n
Diagnosis of Adrenal Insufficiency n Other indirect clues: § Features of hypersecretion of GH or PRL from pituitary adenoma. § Pressure symptoms from pituitary tumors.
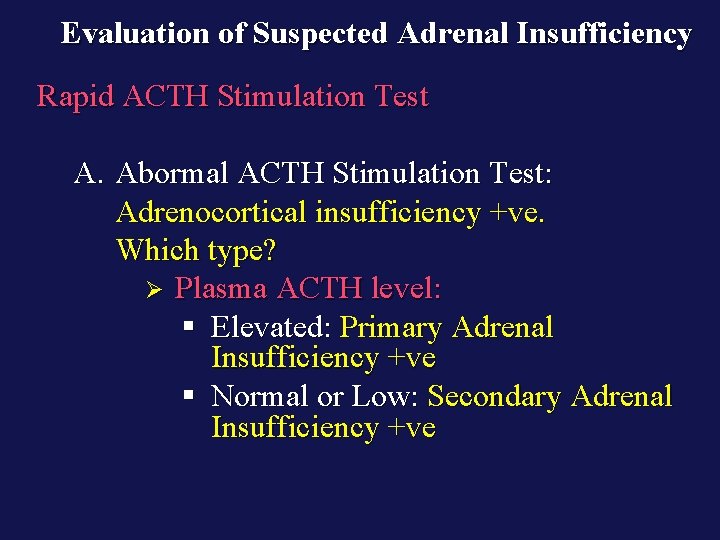
Evaluation of Suspected Adrenal Insufficiency Rapid ACTH Stimulation Test A. Abormal ACTH Stimulation Test: Adrenocortical insufficiency +ve. Which type? Ø Plasma ACTH level: § Elevated: Primary Adrenal Insufficiency +ve § Normal or Low: Secondary Adrenal Insufficiency +ve
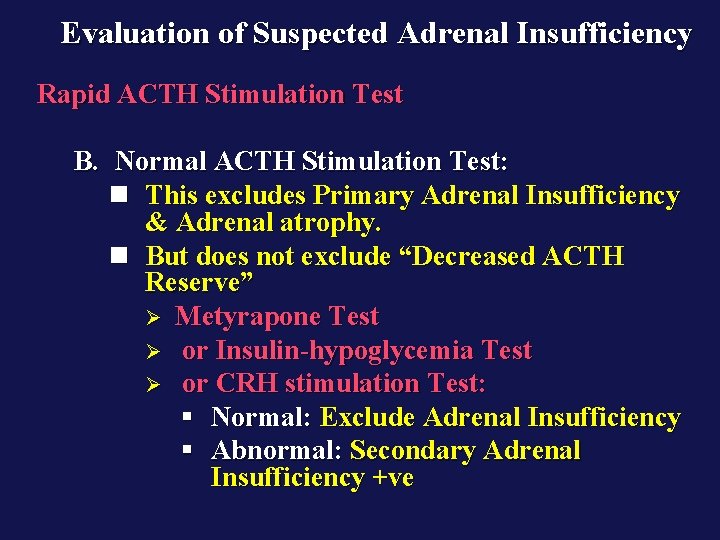
Evaluation of Suspected Adrenal Insufficiency Rapid ACTH Stimulation Test B. Normal ACTH Stimulation Test: n This excludes Primary Adrenal Insufficiency & Adrenal atrophy. n But does not exclude “Decreased ACTH Reserve” Ø Metyrapone Test Ø or Insulin-hypoglycemia Test Ø or CRH stimulation Test: § Normal: Exclude Adrenal Insufficiency § Abnormal: Secondary Adrenal Insufficiency +ve
Treatment of Adrenal Insufficiency Acute Addisonian Crisis n Glucocorticoid Replacement – Cortisol (Hyrdocortisone succinate or phosphate) 100 mg every 6 hrs. for 24 hrs. – When stable, reduce to 50 mg 6 hrs. – Taper to maintenance therapy by day 4 or 5 & add mineralocorticoid as required. – If complications persist or occur, maintain or increase the dose to 200 -400 mg/d. n General or Supportive Measures – Correct volume depletion, dehydration, & hypoglycemia with I. V. saline and glucose. – Evaluate and treat infection or other precipitating factors.
Treatment of Adrenal Insufficiency Maintenance Therapy n n Life-long replacement therapy glucocorticoid and mineralocorticoid. Preparations: – Cortisol (hydrocortisone) tablets » First choice » Maintenance dose: 15 -30 mg/d. » Usually, divided into 2 doses (2/3 AM & 1/3 PM) – Cortisone acetate (37. 5 mg/d) » Absorbed rapidly from GIT » converted in the liver to cortisol. with
Treatment of Adrenal Insufficiency Maintenance Therapy Synthetic Steroids: - Prednisone or Prednisolone 5 mg of prednisone tab is equivalent to 20 mg of hydrocortisone. - Fludrocortisone (9 -alpha fludrocortisol) » Used for mineralocorticoid therapy » Usual dose: 0. 05 -0. 1 mg/d PO AM
Treatment of Primary Adrenal Insufficiency Regimen Therapy Cortisol 15 -20 mg AM & 10 mg at 4 -5 pm n Or prednisone 5. 0 -7. 5 mg AM n Fludrocortisone (Fluranif) 0. 05 0. 1 mg PO AM. n Clinical Follow up: n – Maintenance of normal body weight, BP & electrolytes – Regression of clinical features Patient education & identification card or bracelet n Increased cortisol dosage during stress. n