
Acute Pancreatitis Umit Akyuz MD Gastroenterology Department Yeditepe




















































- Slides: 68
Acute Pancreatitis Umit Akyuz, MD Gastroenterology Department, Yeditepe University Istanbul
Acute Pancreatitis - Objectives Discuss basic physiology Etiology Clinical Presentation Diagnosis Prognosis Management Complications
Pancreatic Physiology (1) Production of bicarbonate-rich fluid to neutralize gastric fluid in the duodenum – duct cells primarily (CFTR gene = chloride / bicarbonate channel) (2) Synthesis of digestive enzymes – acinar cells (3) Insulin production = islet cells
Pancreatic Physiology Most of the pancreas is made of acinar cells The duct cells connect the acinar cells to the duodenum and as noted produces a bicarbonate rich fluid to “wash” the enzymes into the duodenum (3000 cc/day) The islet cells function independently but need remain in close proximity to the acinar cells to maintain normal gene expression
Pancreatic Physiology Acinar enzymes are produced as zymogens Zymogens are proenzymes that require cleavage of a peptide by trypsin to become active Trypsinogen (zymogen of trypsin) is activated by the intestinal brush boarder enzyme enterokinase or by another trypsin molecule
Acute Pancreatitis
Acute Pancreatitis – Epidemiology >200, 000 Hospital Admissions / Year 20% have a severe course – 10 -30% mortality for this group, which has not significantly changed during the past few decades despite improvement in critical care and other interventions
Acute Pancreatitis – Pathophysiology An acute inflammatory process within the pancreas with variable involvement of localized tissues and remote organ systems It can range from Mild Severe with MOSF, necrosis, abscess, or a myriad of other complications Vigorous immune response – By the time pancreatitis is recognized clinically the inflammatory consequences dominate the clinical picture
Acute Pancreatitis The vast majority of protection centers on trypsin activation (or lack thereof) – (1) preventing trypsinogen activation (2) inactivating trypsin (3) “sweeping” trypsin out of the pancreas
Acute Pancreatitis Etiology
Etiology Alcohol (40%) – Mechanism not fully understood – Not all alcoholics get pancreatitis (only about 15%) – This suggests a subset of the population predisposed to pancreatitis, with alcohol acting more as a co-precipitant
Alcohol related pancreatitis CASE 26 M presents for pseudocyst drainage – four weeks after severe pancreatitis Has had “abdominal symptoms” since childhood Does admit to heavy alcohol use as young adult – Strong family history of alcoholism and pancreatitis – Family history reveals a possible autosomal dominant abnormality ERCP reveals chronic pancreatitis
Alcohol related pancreatitis CASE Answer: – A mutation (PRSS 1) was found that alters the protein structure of trypsin producing a constant ON trypsin (auto-activation within the pancreas), resulting in frequent bouts of pancreatitis.
Etiology Gallstones (35%) – Gallstone pancreatitis risk is highest among patients with small GS < 5 mm and with microlithiasis – GS pancreatitis risk is also increased in white women > 60 yrs
Etiology – Drugs and Toxins (5%) Azathioprine Cimetidine Estrogens Enalapril Erythromycin Furosemide Multiple HIV medications Scorpion Bites Sulfonamides Thiazides TMP/SMX
Etiology – Trauma Blunt Trauma – Automobile – Bicycle handlebar injuries – Abuse Iatrogenic – ERCP (1 -7%) – Likely secondary to contrast but also very operator dependant – Risk is also increased with Sphincter of Oddi manometry
Etiology – Multi-System Disease Diabetic Ketoacidosis (10 -15%) Hemochromatosis HUS Hypercalcemia Hyperparathyroidism Hypertriglyceridemia IBD Malnutrition Severe PUD Renal Failure SIRS SLE and other connective tissue dissorders Status-Post solid organ and BM transplant Vasculitis
Etiology – Multi-System Disease Cystic Fibrosis – 2 -15% of patients – Ductal obstruction from thickened secetions
Etiology – Multi-System Disease Malnutrition and Re-feeding Anorexia Nervosa – Pancreatic acinar cells atrophy but true cause of pancreatitis unknown
Etiology – Infection Ascaris Campylobacter CMV Coxsackie B EBV Enterovirus HIV/AIDS Influenza MAC Measles Mumps Rubella Mycoplasma Rubeola Viral Hepatitis Varicella
Etiology – Anatomical Anomalies Pancreas Divisum – Failure of dorsal and ventral fusion (5 -15% of population) Annular Pancreas Any Ductal Anomalies Sphincter of Oddi dysfunction Always consider a primary malignancy as a possible cause of new onset pancreatitis in older patients without other obvious risk factors
Etiology – Genetic CFTR heterozygote – “atypical” CF Other CFTR mutations – found in many adult patients with more severe forms of pancreatitis (we can test for a few hundred of the more than 1200 different mutations) SPINK 1 mutations – most common cause of familial pancreatitis; causes a predisposition for pancreatitis (other trigger is usually present) PRSS 1 gene – Self-activating trypsin
Etiology - Autoimmune Primarily a pancreatic disorder but. . . Can be associated with other diseases of presumed autoimmune etiology including sclerosing cholangitis, primary biliary cirrhosis, retroperitoneal fibrosis, rheumatoid arthritis, sarcoidosis, and Sjögren's syndrome - some authors have proposed that AIP represents a systemic autoimmune disease
Etiology - Autoimmune (1) Diagnostic histology - dense lymphoplasmacytic infiltrate of the pancreatic parenchyma with secondary fibrosis (2) Characteristic imaging with elevated Ig. G 4 – focal or diffuse enlargement of the pancreas that is often sausage-shaped – minimal pancreatic stranding – calcifications or peripancreatic fluid – uniform narrowing of the main pancreatic duct – rim-like enhancement of the pancreatic head (3) Response to steroid therapy
Etiology – Idiopathic Still accounts for ~20% of cases
Etiology – Idiopathic Experts suggest that idiopathic pancreatitis should account for no more than 5 -10% of the total cases, yet the broadly quoted percentage in the literature at this time in the US is currently 20 -25%.
Acute Pancreatitis Clinical Presentation
Clinical Presentation Clinical – Continuous mid-epigastric / peri-umbilical abdominal pain Radiating to back, lower abdomen or chest – Emesis – Fever – Aggravated by eating – Progressive – Restless and uncomfortable
Clinical Presentation More severe cases – Jaundice – Ascites – Pleural effusions – generally left-sided – Cullen’s sign – bluish peri-umbilical discoloration – Grey Turner’s sign – bluish discoloration of the flanks
Diagnosis – Initial work-up GS history Drug intake Family History Alcohol intake Viral exposures Lipase LFTs GB US
Diagnosis – Follow up investigations Fasting liver profile Fasting plasma calcium – when well Viral titers as indicated by clinical presentation GB US – consider repeating MRCP CT pancreas (pancreas protocol)
Diagnosis – Further investigations Appropriate for recurrent idiopathic acute pancreatitis – GB US – EUS / ERCP – biliary and pancreatic cytology – Autoimmune markers – Sphincter of Oddi manometry – Functional testing / History to screen for sequela of chronic pancreatitis
Diagnosis – Amylase Elevates within HOURS and can remain elevated for 4 -5 days High specificity when using levels >3 x normal Many false positives (see next slide) Most specific = pancreatic isoamylase (fractionated amylase)
Diagnosis – Amylase Elevation Pancreatic Source – – – Biliary obstruction Bowel obstruction Perforated ulcer Appendicitis Mesenteric ischemia Peritonitis Salivary – – Parotitis DKA Anorexia Fallopian tube Unknown Source – – Renal failure Head trauma Burns Postoperative
Diagnosis – Lipase The preferred test for diagnosis Begins to increase 4 -8 H after onset of symptoms and peaks at 24 H Remains elevated for days Sensitivity 86 -100% and Specificity 6099% >3 X normal S&S ~100%
Diagnosis Elevated ALT > 3 x normal (in a nonalcoholic) has a positive predictive value of 95% for GS pancreatitis
Diagnosis – Imaging CT – Excellent pancreas imaging – Recommended in all patients with persisting organ failure, sepsis or deterioration in clinical status (6 -10 days after admission) – Search for necrosis – will be present at least 4 days after onset of symptoms; if ordered too early it will underestimate severity – Follow-up months after presentation as clinically warranted for CT severity index of >3
Diagnosis - Imaging ERCP / EUS – Diagnostic and Therapeutic – Can see and treat: Ductal dilatation Strictures Filling defects / GS Masses / Biopsy
Diagnosis – Imaging ERCP indications (should be done in the first 72 hr) – GS etiology with severe pancreatitis – needs sphincterotomy – Cholangitis – Jaundice – Dilated CBD – If no GS found sphincterotomy is indicated anyway – Poor surgical candidate for laparoscopic cholecystectomy – Clinical course not improving sufficiently to allow timely laparoscopic cholecystectomy and intraoperative cholangiogram – Pregnant patient – Uncertainty regarding biliary etiology of pancreatitis
Acute Pancreatitis Prognosis
Prognosis – Ranson’s (Severe > 3) Ranson’s Score – 5 on Admission Age > 55 y Glucose >200 WBC > 16000 LDH > 350 ALT > 250 – 6 after 48 hours from presentation Hct > 10% decrease Calcium < 8 Base Deficit > 4 BUN > 5 Fluid Sequestration > 6 L Pa. O 2 < 60
Prognosis – Atlanta Criteria Severe Acute Pancreatitis – Early Prognostic Signs Ranson signs ≥ 3 APACHE-II score ≥ 8 Organ Failure and/or Local Complications (persist >48 hr after admission) Necrosis Abscess Pseudocyst Organ Failure as Defined by Atlanta Symposium – Shock–systolic pressure <90 mm. H – Pa. O 2 ≤ 60 mm. Hg – Creatinine >2. 0 mg/L after rehydration – Gastrointestinal bleeding >500 cc/24 h
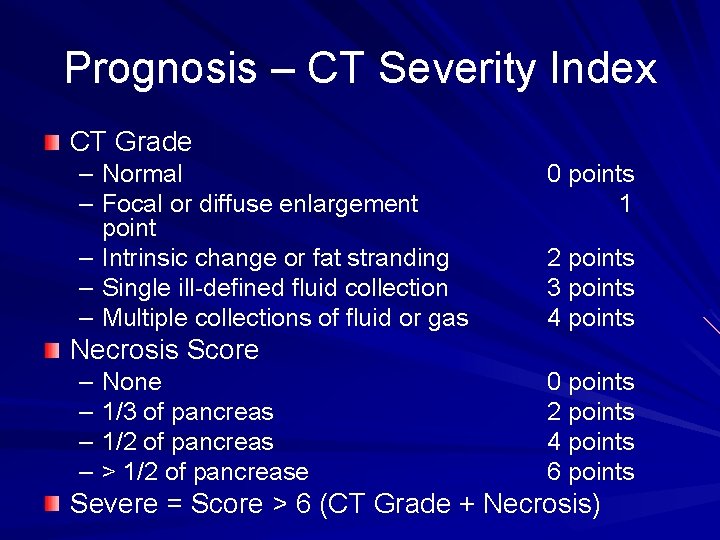
Prognosis – CT Severity Index CT Grade – Normal – Focal or diffuse enlargement point – Intrinsic change or fat stranding – Single ill-defined fluid collection – Multiple collections of fluid or gas 0 points 1 2 points 3 points 4 points Necrosis Score – None – 1/3 of pancreas – 1/2 of pancreas – > 1/2 of pancrease 0 points 2 points 4 points 6 points Severe = Score > 6 (CT Grade + Necrosis)
Prognosis – CRP Santorini consensus and the World Association guidelines recommend a cut off of 10 - 15 mg/dl – This is checked 48 hours after admission
Management All patients with biliary pancreatitis should undergo definitive treatment of gallstones during the same hospital admission, unless a clear plan has been made for definitive treatment within the next two weeks Delay exposes the patient to the risk of potentially fatal recurrent acute pancreatitis Surgery should be delayed in severe pancreatitis and ERCP is preferred
Management Mainly supportive – Hydration, pain relief, and pancreatic rest – NPO – to decrease pancreatic secretion – Remember stress ulcer prophylaxis always – Look for complications!!! – No magic bullet – antiproteases, octreotide (antisecretory) or lexiafant (anti-inflammatory) have all been disappointing in large trials
Management - Antibiotics Infected necrosis has significant mortality (40%) No consensus at this time for prophylactic antibiotics but the literature leans toward using them in severe pancreatitis with necrosis – Imipenum, cefuroxime, ceftazidime + amikacin + metro, Ofloxacin + metro, cipro + metro your choice If used, it should be given no longer than 7 to 14 days Gut decontamination is not recommended
Management - Feedings Enteral nutrition is preferred There is a push for nasojejunal feeds however nasogastric feeds have been shown to be effective in 80% of cases¶ NGTs should be used with caution in patients with AMS however More risk with TPN / IL but if cannot feed enterally >5 days may be needed ¶ Eatock FC. Nasogastric feeding in severe acute pancreatitis. Radiology 1994: 193, 297 -306.
Management – Necrosis All severe pancreatitis should be managed in the ICU or Stepdown Unit FNA recommended when >30% necrosis or clinical suspicion of sepsis for a culture 7 -14 days after onset, if gas present assume infected necrosis and treat Infection generally requires debridement (surgical or IR)
Management – Pain Morphine not ideal but can still be used – it can theoretically worsen symptoms by increasing spasm of the Sphincter of Oddi Demerol is a good opiate agonist Hydromorphone is also an excellent option PCA is generally preferred in the beginning Always use the gut if you can to transition off IV pain meds Don’t forget aggressive bowel care
Infliximab in Acute Pancreatitis Ø Infliximab, a monoclonal TNF antibody, was tested in 100 rats randomly assigned to 10 groups Ø In acute edematous pancreatitis and in severe necrotizing pancreatitis, the drug significantly decreased serum amylase activity and the histopathologic score Ø In severe necrotizing pancreatitis, it ameliorated both parenchymal and fatty tissue necrosis of the pancreas Ø It also alleviated alveolar edema and ARDS-like pulmonary complications, but this difference was not significant Oruc N, et al. Pancreas 2004; 28: E 1 -8. [26]
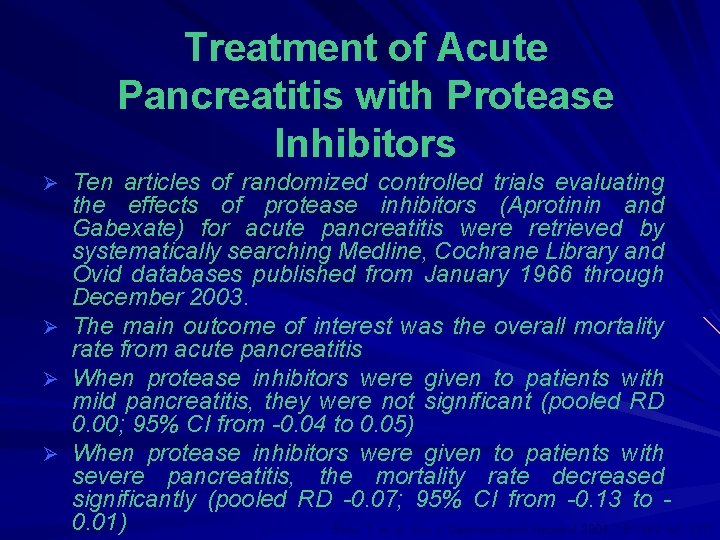
Treatment of Acute Pancreatitis with Protease Inhibitors Ten articles of randomized controlled trials evaluating the effects of protease inhibitors (Aprotinin and Gabexate) for acute pancreatitis were retrieved by systematically searching Medline, Cochrane Library and Ovid databases published from January 1966 through December 2003. Ø The main outcome of interest was the overall mortality rate from acute pancreatitis Ø When protease inhibitors were given to patients with mild pancreatitis, they were not significant (pooled RD 0. 00; 95% CI from -0. 04 to 0. 05) Ø When protease inhibitors were given to patients with severe pancreatitis, the mortality rate decreased significantly (pooled RD -0. 07; 95% CI from -0. 13 to 0. 01) Seta T, et al. Eur J Gastroenterol Hepatol 2004; 16: 1287 -93. [37] Ø
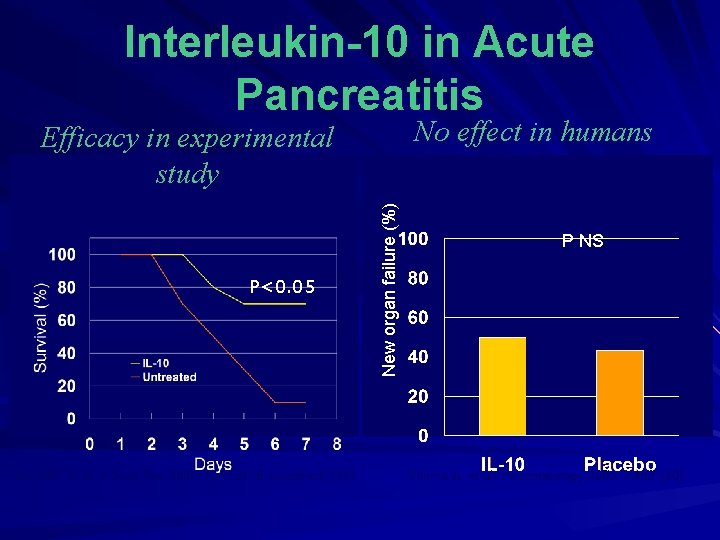
Interleukin-10 in Acute Pancreatitis No effect in humans P<0. 05 Zou WG, et al. J Surg Res 2002; 103: 121 -6. (modified) [29] New organ failure (%) Efficacy in experimental study P NS Villoria A, et al. Pancreatology 2003; 3: 466. [30]
Limitations of Experimental Models for the Treatment of Acute Pancreatitis The utility of such experimental models might have limitation, and a full extrapolation of experimental data from laboratory animals to Pastorwith CM, Frossard JL. FASEB J 2001; 15: 893 -7. [28] humans must be done caution
Complications – Local Necrosis – Sterile – Infected - abscess Pseudocyst Ascites Intraperitoneal hemorrhage Thrombosis Bowel infarction Obstructive jaundice
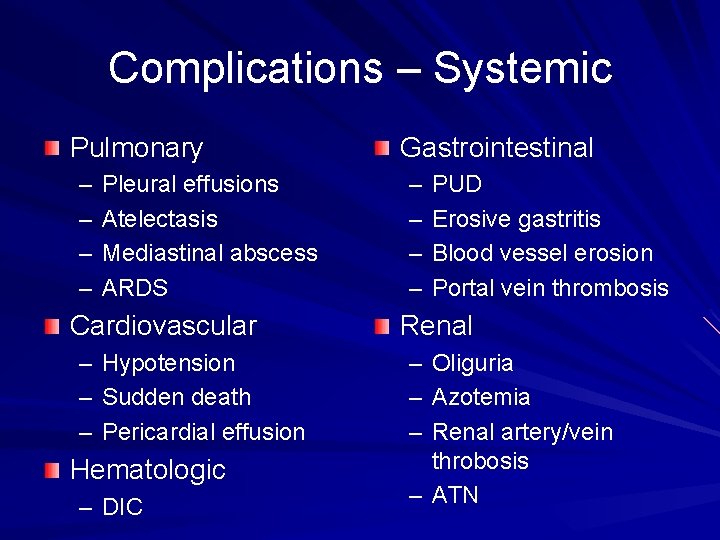
Complications – Systemic Pulmonary – – Pleural effusions Atelectasis Mediastinal abscess ARDS Cardiovascular – – – Hypotension Sudden death Pericardial effusion Hematologic – DIC Gastrointestinal – – PUD Erosive gastritis Blood vessel erosion Portal vein thrombosis Renal – – – Oliguria Azotemia Renal artery/vein throbosis – ATN
Complications – Long Term Chronic Pancreatitis – Abdominal Pain – Steatorrhea – Exocrine insufficiency (pancreas has a 90% reserve for the secretion of digestive enzymes) – Endocrine Insufficiency – less common – Pseudocyst
Conclusions Do not assume alcohol is the primary cause of pancreatitis Always consider further work-up for “idiopathic” pancreatitis Severe acute pancreatitis should be managed in ICU/SD Infected necrosis carries a high mortality Antibiotics for suspected infected necrosis Tube feedings preferred Always look for the myriad of complications
CHRONIC PANCREATITIS Progressive – Destructive Inflammation Permanent parenchymal loss Pancreatic endo + exo insufficiency
Causes • Alcohol 80 % (Ten years 60 gd. L) • Idiopathic 10%-20% • Rare biliary, p. HTP
Chronic Pancreatitis Classic triad Steatorrhea Calcification Diabetes
Symptoms + Signs Abdominal Pain Malabsorption Diabetes Jaundice
Pain Mid-epigastrium; Upperquadrant periumbilical Steady, boring, achy, radiating to the back. Better! When Sitting.
Diagnostic Laboratory Amylase Slightly Lipase Liver Fu. Tests Glucose AP Protrombin time
Diagnostic Imaging CT: Ductal dilatation Calcification Pseudocysts ERCP
Diagnostic Tests Pancreolauryl-Test Secretin – Pancreocymin Test
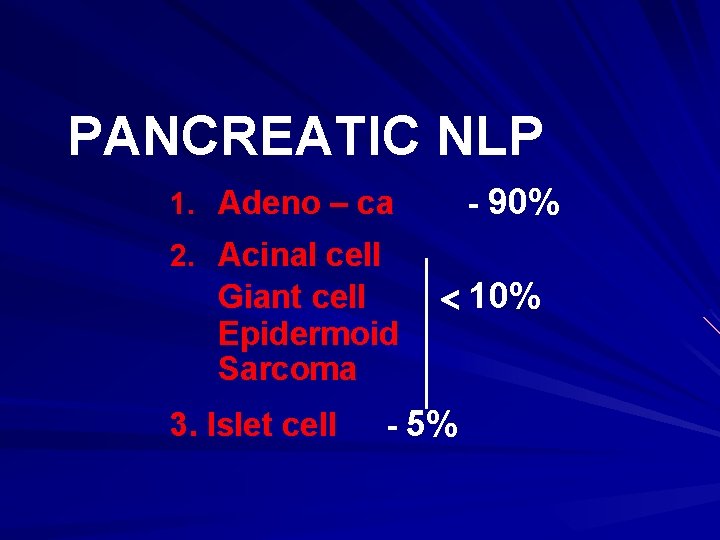
PANCREATIC NLP - 90% 1. Adeno – ca 2. Acinal cell Giant cell Epidermoid Sarcoma 3. Islet cell 10% - 5%