
Acute and Chronic Pancreatitis a need for close


































- Slides: 92
Acute (and Chronic) Pancreatitis: a need for close assessment Pat Hagan MN, M. Ed. , RN CCRN, CEN
Statistics Incidence in the United States ranges from 54 -234 cases per million people per year! 5 -15% of patients have a fulminant course 20 -60% of patients face death or potentially lethal complications Overall mortality rates are between 10 -20%
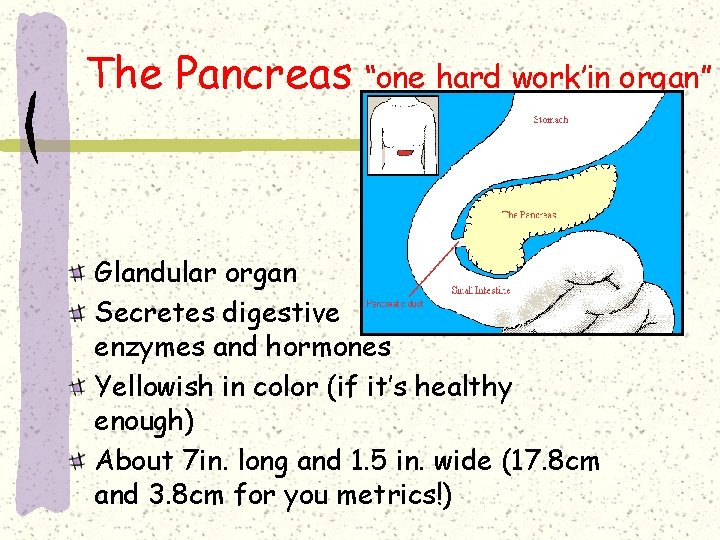
The Pancreas “one hard work’in organ” Glandular organ Secretes digestive enzymes and hormones Yellowish in color (if it’s healthy enough) About 7 in. long and 1. 5 in. wide (17. 8 cm and 3. 8 cm for you metrics!)
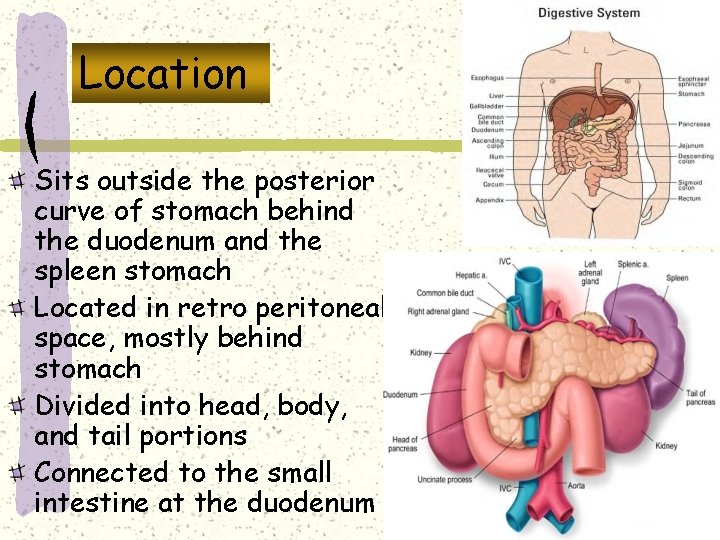
Location Sits outside the posterior curve of stomach behind the duodenum and the spleen stomach Located in retro peritoneal space, mostly behind stomach Divided into head, body, and tail portions Connected to the small intestine at the duodenum
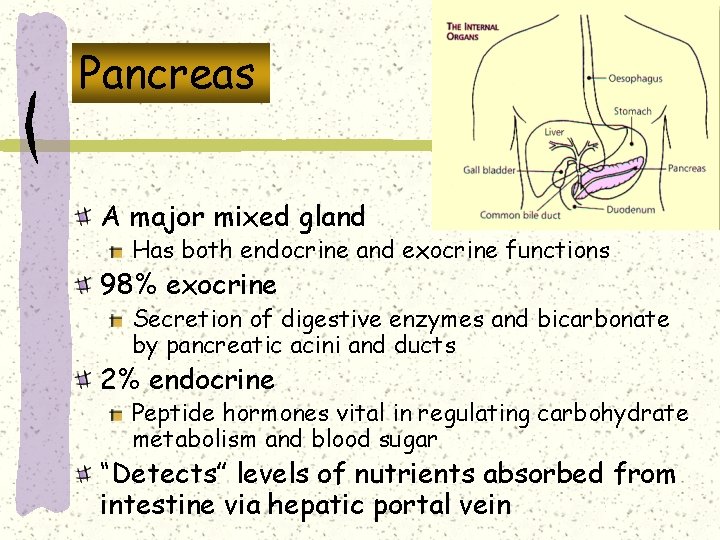
Pancreas A major mixed gland Has both endocrine and exocrine functions 98% exocrine Secretion of digestive enzymes and bicarbonate by pancreatic acini and ducts 2% endocrine Peptide hormones vital in regulating carbohydrate metabolism and blood sugar “Detects” levels of nutrients absorbed from intestine via hepatic portal vein
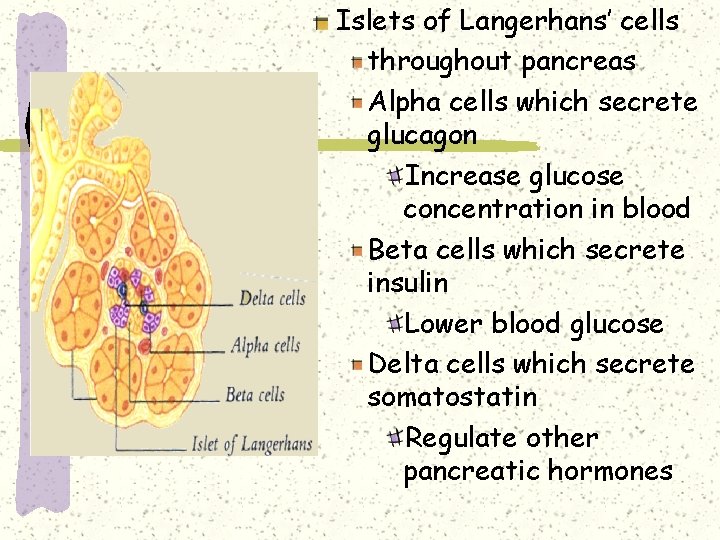
Islets of Langerhans’ cells throughout pancreas Alpha cells which secrete glucagon Increase glucose concentration in blood Beta cells which secrete insulin Lower blood glucose Delta cells which secrete somatostatin Regulate other pancreatic hormones
Somatostatin Facts 3 rd peptide secreted from pancreas Tends to dampen rise in both insulin and glucagon, preventing roller-coaster rides with the blood sugar! May inhibit GH secretion from pituitary, since GH has anti-insulin effects
So, what are those enzymes? Pancreatic Acinar cells secrete pancreatic enzymes Produce digestive enzymes and bicarbonate. Secretes about 1, 500 -2, 000 cc of digestive solution per day Lipase Amylase Main Trypsin ones Phospholipase (PLA 2)
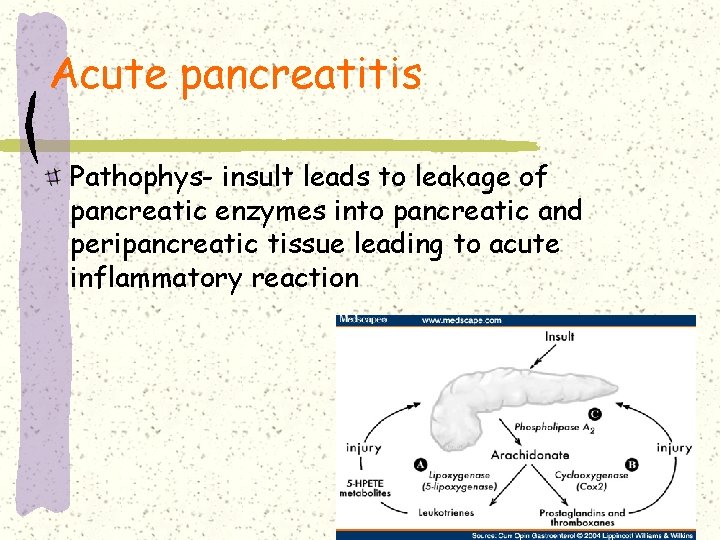
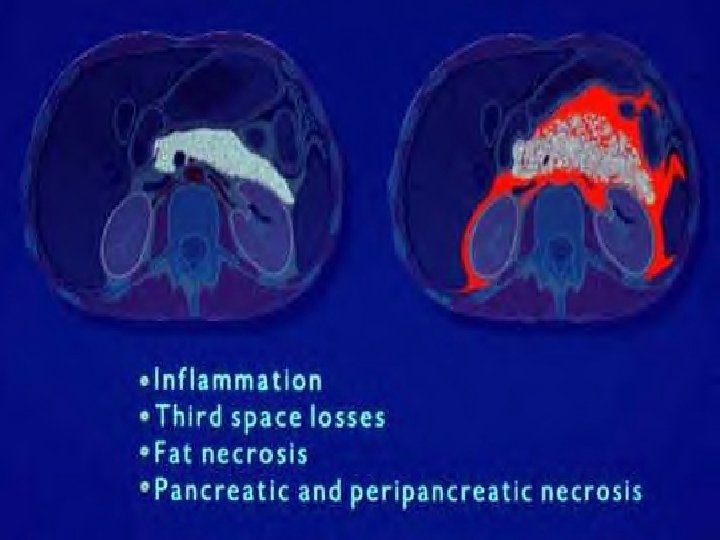
Acute pancreatitis Pathophys- insult leads to leakage of pancreatic enzymes into pancreatic and peripancreatic tissue leading to acute inflammatory reaction
Acute pancreatitis Inflammation of the pancreas Pancreatic enzymes activated prematurely (before reaching intestines) Activates inflammatory mediators to area Increasing vascular permeability Leads to edema and fluid shifts from intravascular spaces to the interstitum
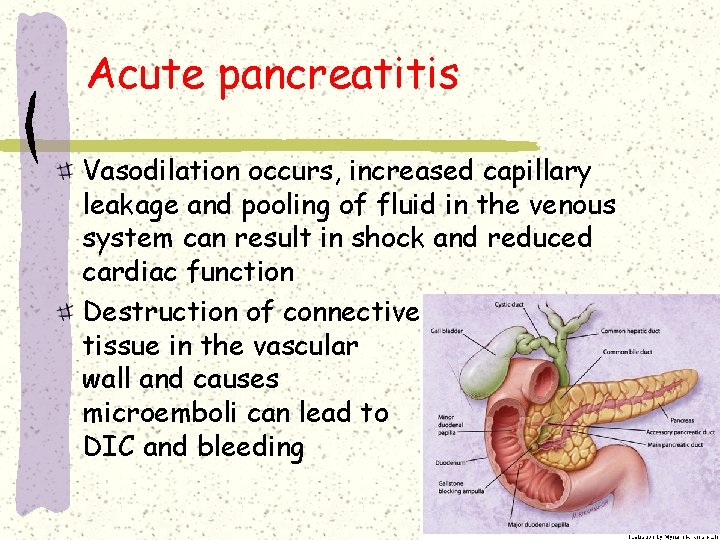
Acute pancreatitis Vasodilation occurs, increased capillary leakage and pooling of fluid in the venous system can result in shock and reduced cardiac function Destruction of connective tissue in the vascular wall and causes microemboli can lead to DIC and bleeding
Acute pancreatitis Phospholipase A irritates pancreatic tissue and causes tissue necrosis Lipase overflowing into the tissues and systemic circulation leads to fat necrosis of the pancreas and surrounding areas Risk of mortality increases with development of infection or pulmonary, cardiac, and renal complications
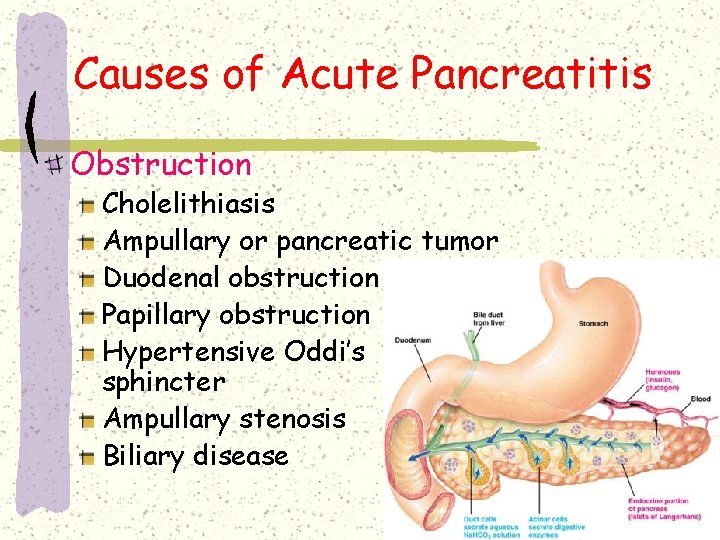
Causes of Acute Pancreatitis Obstruction Cholelithiasis Ampullary or pancreatic tumor Duodenal obstruction Papillary obstruction Hypertensive Oddi’s sphincter Ampullary stenosis Biliary disease
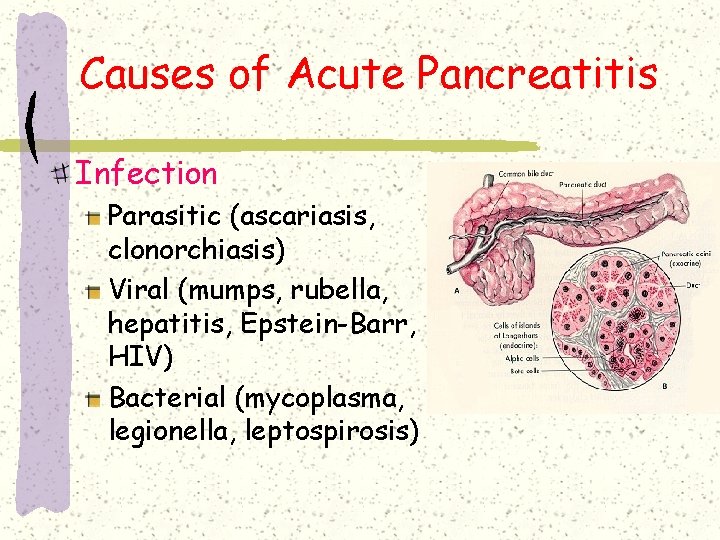
Causes of Acute Pancreatitis Infection Parasitic (ascariasis, clonorchiasis) Viral (mumps, rubella, hepatitis, Epstein-Barr, HIV) Bacterial (mycoplasma, legionella, leptospirosis)
Trivia What is the name of the scorpion that causes pancreatitis? Hint: you won’t find it in the USA Tityus Trinitatis (Found in Central/ South America and the Caribbean)
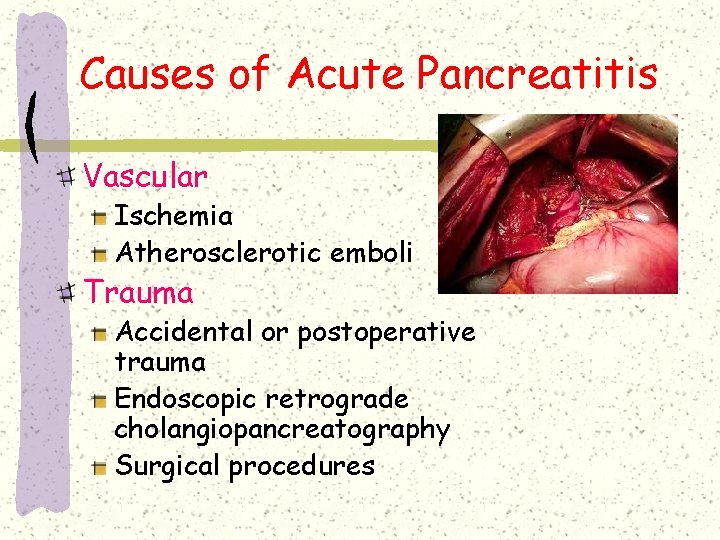
Causes of Acute Pancreatitis Vascular Ischemia Atherosclerotic emboli Trauma Accidental or postoperative trauma Endoscopic retrograde cholangiopancreatography Surgical procedures
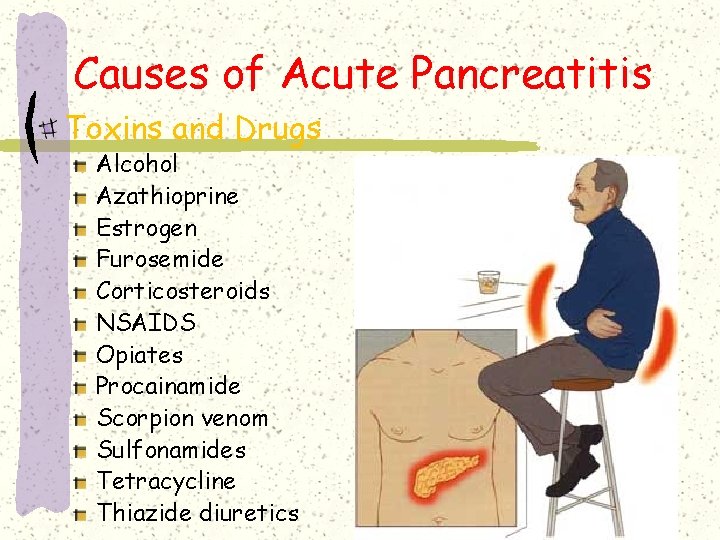
Causes of Acute Pancreatitis Toxins and Drugs Alcohol Azathioprine Estrogen Furosemide Corticosteroids NSAIDS Opiates Procainamide Scorpion venom Sulfonamides Tetracycline Thiazide diuretics
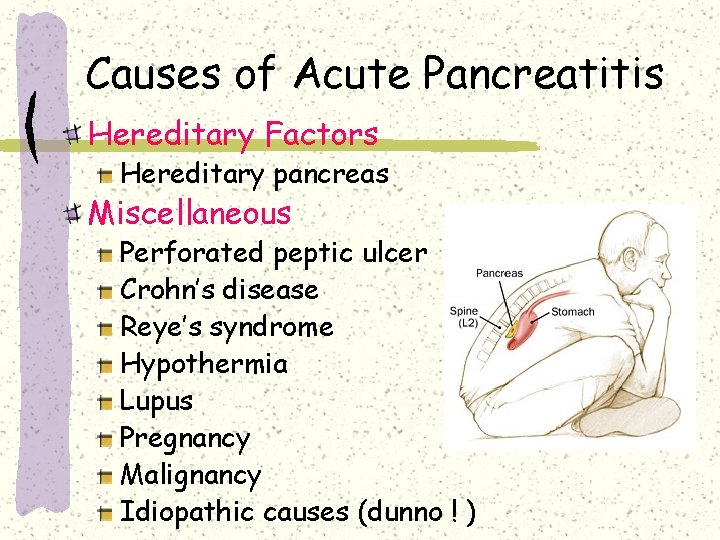
Causes of Acute Pancreatitis Hereditary Factors Hereditary pancreas Miscellaneous Perforated peptic ulcer Crohn’s disease Reye’s syndrome Hypothermia Lupus Pregnancy Malignancy Idiopathic causes (dunno ! )
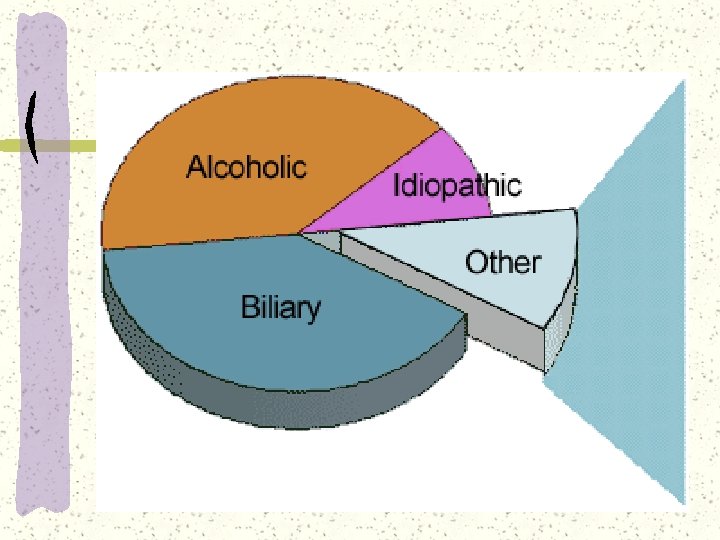
More Statistics Cholelithiasis most common cause in the U. S. , Western Europe, and Asia (45% of cases) Chronic alcohol ingestion is second leading cause (35%) Pseudocytes and abscesses account for 70 to 80% of mortality
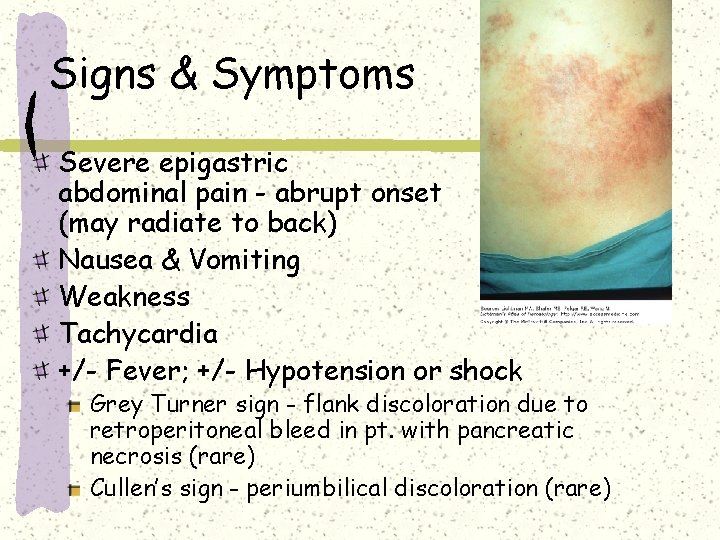
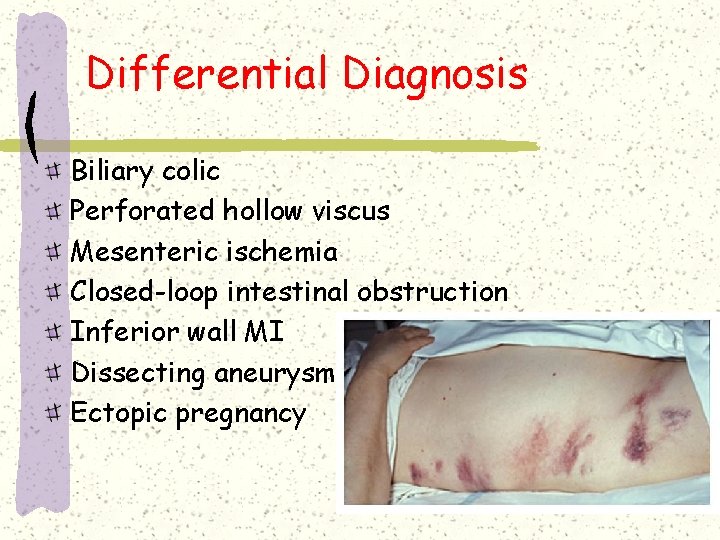
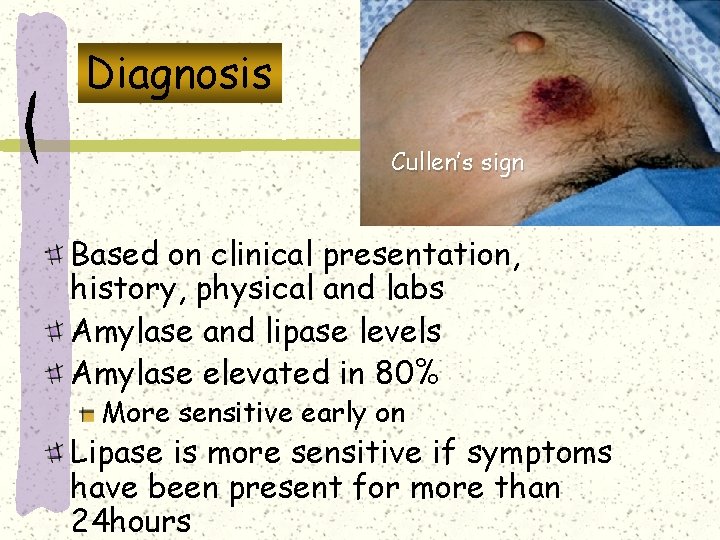
Signs & Symptoms Severe epigastric abdominal pain - abrupt onset (may radiate to back) Nausea & Vomiting Weakness Tachycardia +/- Fever; +/- Hypotension or shock Grey Turner sign - flank discoloration due to retroperitoneal bleed in pt. with pancreatic necrosis (rare) Cullen’s sign - periumbilical discoloration (rare)
Acute Pancreatitis Clinical Manifestations Epigastric or midabdominal pain May radiate to back Fever, leukocytosis Nausea and vomiting Abdominal distention Hypotension and shock, DIC ATN, ARDS Formation of pancreatic fluid collections (pseudocytes and abscesses)
Clinical Manifestations (continued) Atelectasis, Pneumonia, Pleural Effusions, Pulmonary edema, Tetany may develop as a result of deposition of calcium in areas of fat necrosis or decreased parathorome Transient hyperglycemia Lleus, colonic obstruction CNS hypoperfusion with confusion
Differential Diagnosis Biliary colic Perforated hollow viscus Mesenteric ischemia Closed-loop intestinal obstruction Inferior wall MI Dissecting aneurysm Ectopic pregnancy
Diagnosis Cullen’s sign Based on clinical presentation, history, physical and labs Amylase and lipase levels Amylase elevated in 80% More sensitive early on Lipase is more sensitive if symptoms have been present for more than 24 hours
Diagnosis Both amylase and lipase levels may be normal with CT proved pancreatitis Ultrasonography or CT is definitive Radiography may reveal a “sentinel loop” Localized ileus in midepigastric region Pleural effusions may also be present MRI, abdominal plain films, Upright Chest X-ray
Acute Pancreatitis Lab studies CBC, electrolytes, liver enzymes, calcium, magnesium, PT/PTT May have hemoconcentration due to third spacing of fluid May have hypocalcemia caused by “soap” formation Saponification of triglycerides and calcium Frequently have hypomagnesemia WBC usually elevated Liver enzymes may be elevated from biliary obstruction
Evaluation amylase…Nonspecific !!! Amylase levels > 3 x normal very suggestive of pancreatitis May be normal in chronic pancreatitis!!! Enzyme level severity False (-): acute on chronic (Et. OH); Hyper. TG False (+): renal failure, other abdominal or salivary gland process, acidemia lipase More sensitive & specific than amylase
Lab studies (continued) Elevated Serum Amylase Rises rapidly, usually within hours after attack Remains elevated for about 4 days Reference range in adults 0 -140 U/dl Elevated Urine Amylase Rises in a few hours after the rise in serum amylase and lipase Remains elevated for about 7 to 10 days The rise in urine amylase is secondary to an increase in the renal clearance of amylase
Lab studies (continued) Elevated Serum Lipase Also rapidly rises within hours after attack Remains elevated for about 4 days Reference range in adults 130 U/L Elevated C-reactive protein measures severity Amylase clearance to Creatinine clearance by the kidney (increases significantly compared with Creatinine clearance) Normal ratio for amylase clearance is between 2 -5% In pancreatitis, the ratio is increased
Danger Signals: First Few Hours Encephalopathy Hypoxemia Tachycardia > 130/min Hypotension < 90 mm. Hg Hct > 50 Oliguria < ml/hr Azotemia
Radiographic Evaluation AXR - “sentinel loop” or small bowel ileus US or CT may show enlarged pancreas with stranding, abscess, fluid collections, hemorrhage, necrosis or pseudocyst MRI/MRCP newest “fad” Decreased nephrotoxicity from gadolinium Better visualization of fluid collections MRCP allows visualization of bile ducts for stones Does not allow stone extraction or stent insertion Endoscopic US (even newer but used less) Useful in obese patients
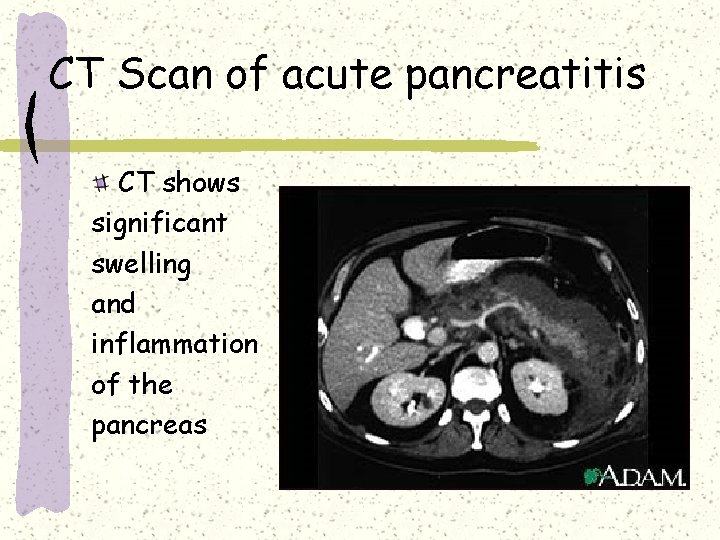
CT Scan of acute pancreatitis CT shows significant swelling and inflammation of the pancreas
CT Criteria of Severity a. Normal b. Enlargement c. Peripancreatic inflammation d. Single fluid collection e. Multiple fluid collections ACUTE PANCREATITIS, X-RAY Acute pancreatitis. Abdominal x-ray in front view.
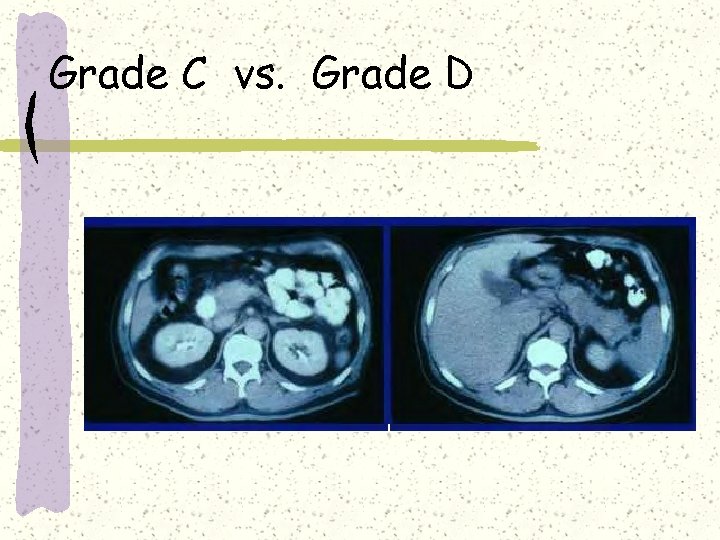
Grade C vs. Grade D
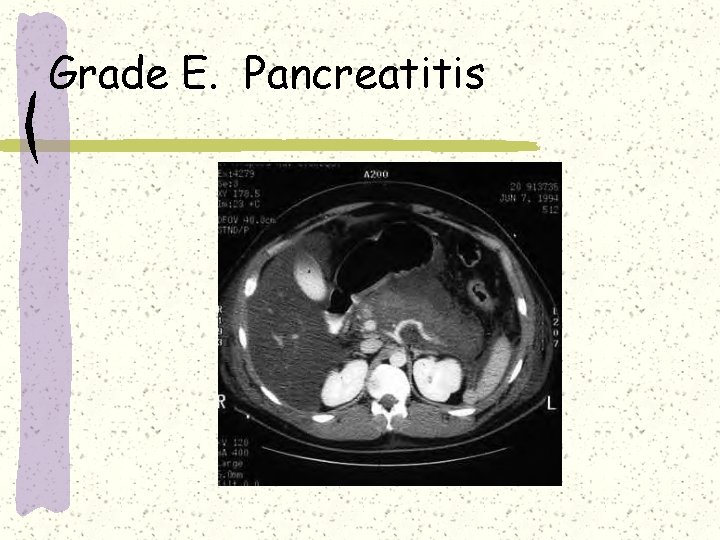
Grade E. Pancreatitis
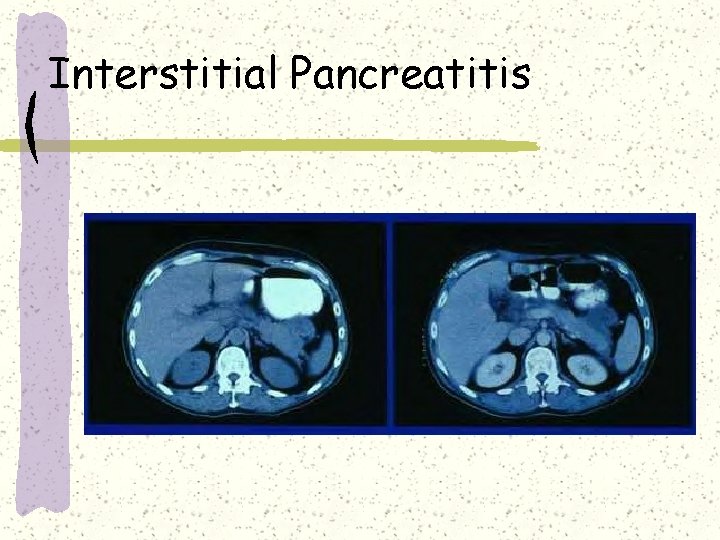
Interstitial Pancreatitis
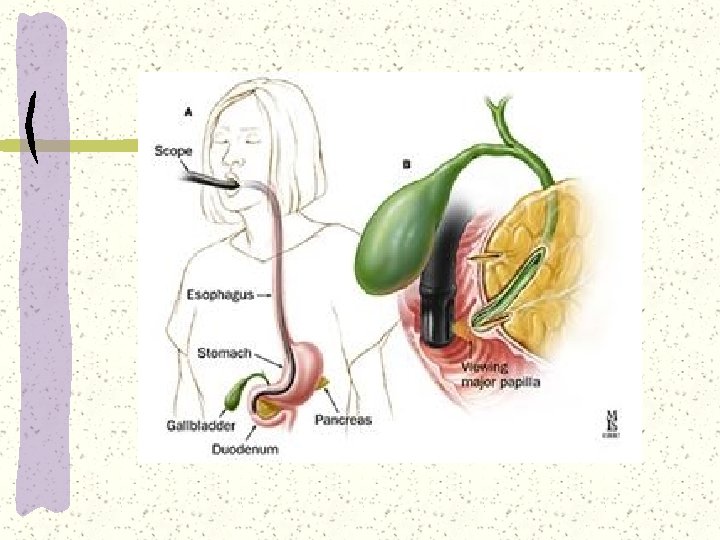
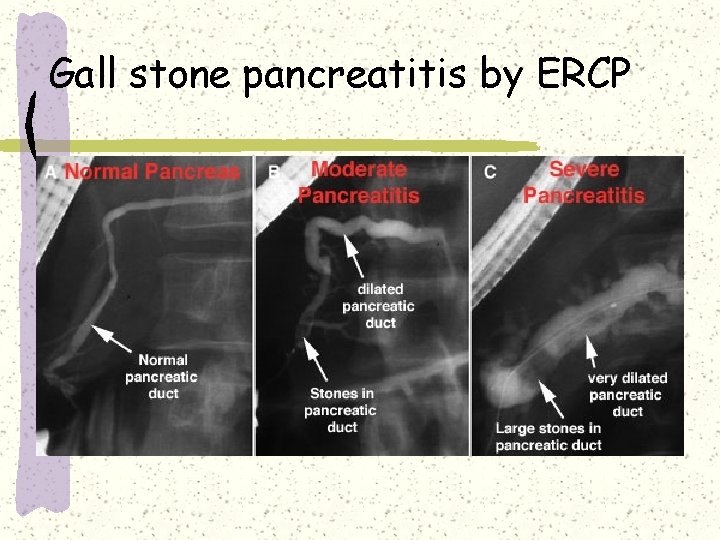
Gall stone pancreatitis by ERCP
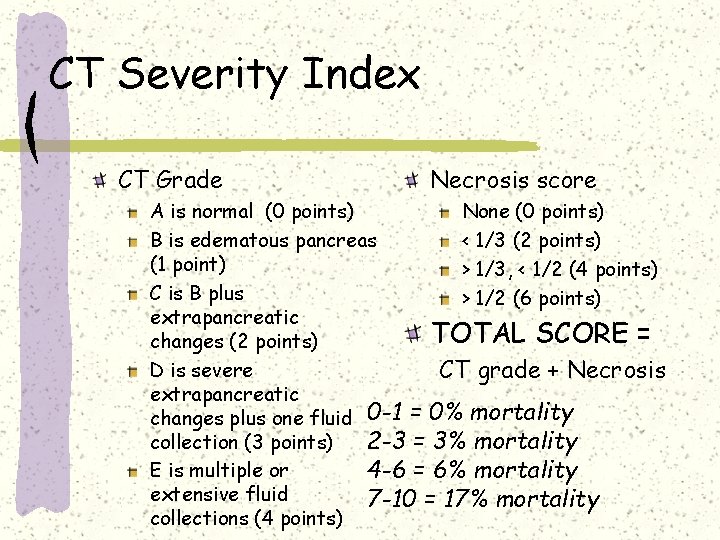
CT Severity Index CT Grade Necrosis score A is normal (0 points) None (0 points) B is edematous pancreas < 1/3 (2 points) (1 point) > 1/3, < 1/2 (4 points) C is B plus > 1/2 (6 points) extrapancreatic TOTAL SCORE = changes (2 points) D is severe CT grade + Necrosis extrapancreatic changes plus one fluid 0 -1 = 0% mortality collection (3 points) 2 -3 = 3% mortality E is multiple or 4 -6 = 6% mortality extensive fluid 7 -10 = 17% mortality collections (4 points)
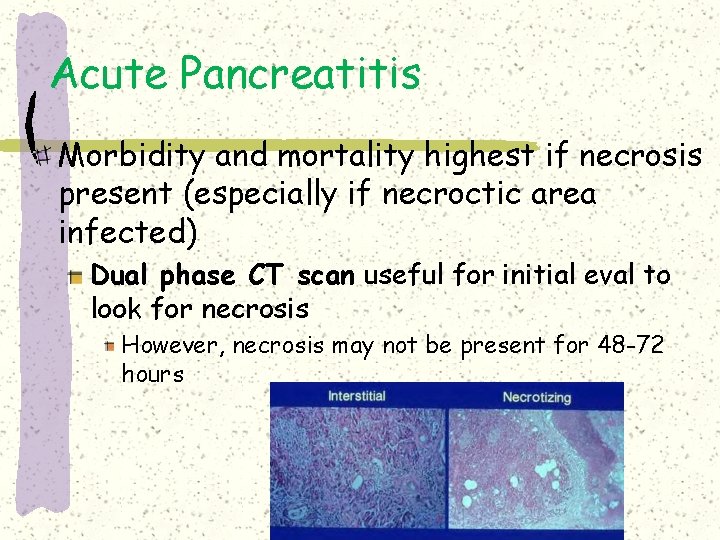
Acute Pancreatitis Morbidity and mortality highest if necrosis present (especially if necroctic area infected) Dual phase CT scan useful for initial eval to look for necrosis However, necrosis may not be present for 48 -72 hours
Prognosis Many different scoring systems Ranson (most popular & always taught in medschool) No association found with score, and mortality or length of hospitalization APACHE II CT severity Index Recent studies show this to be most predictive of adverse outcomes CT score > 5 associated with 15 x mortality rate Problem is 1 CT study showing this was conducted 72 hours after admission (Ranson/Apache are 24 & 48 hours) Imrie Score Atlanta Classification used to help compare various scores (clinical research trials)
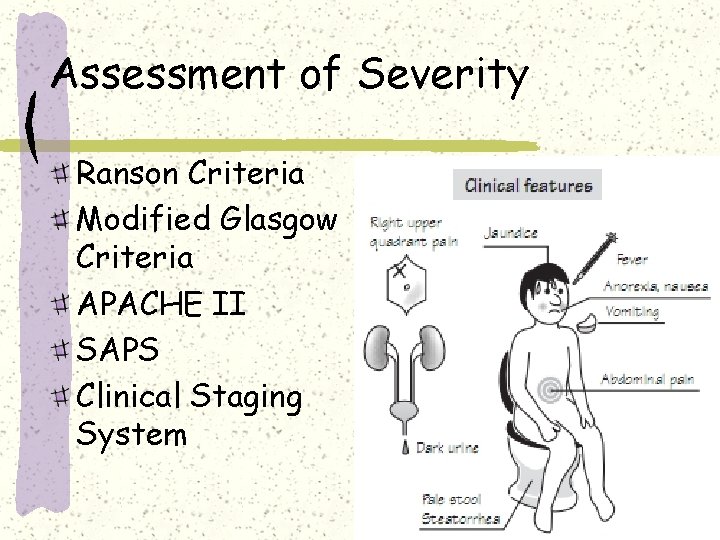
Assessment of Severity Ranson Criteria Modified Glasgow Criteria APACHE II SAPS Clinical Staging System
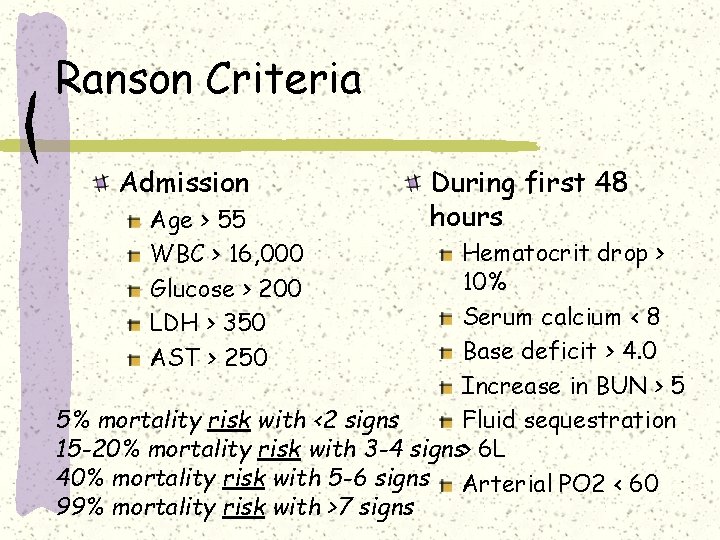
Ranson Criteria Admission Age > 55 WBC > 16, 000 Glucose > 200 LDH > 350 AST > 250 During first 48 hours Hematocrit drop > 10% Serum calcium < 8 Base deficit > 4. 0 Increase in BUN > 5 Fluid sequestration 5% mortality risk with <2 signs 15 -20% mortality risk with 3 -4 signs> 6 L 40% mortality risk with 5 -6 signs Arterial PO 2 < 60 99% mortality risk with >7 signs
Ranson’s Criteria During 1 st 48 hours: fall in HCT > 5 mg% BUN rise> 5 mg% Serum Calcium < 8 mg% Base deficit > 4 meq/L Estimated fluid sequestration > 6 L Arterial PO 2 < 60 mm Hg
How Sick Are You? Using Ranson’s Criteria will predict the severity of the nonalcoholic acute pancreatitis (possible score of 11) Age>55 years WBC > 16, 000/mm 3 Serum glucose > 200 mg/dl SGOT > 300 IU/L
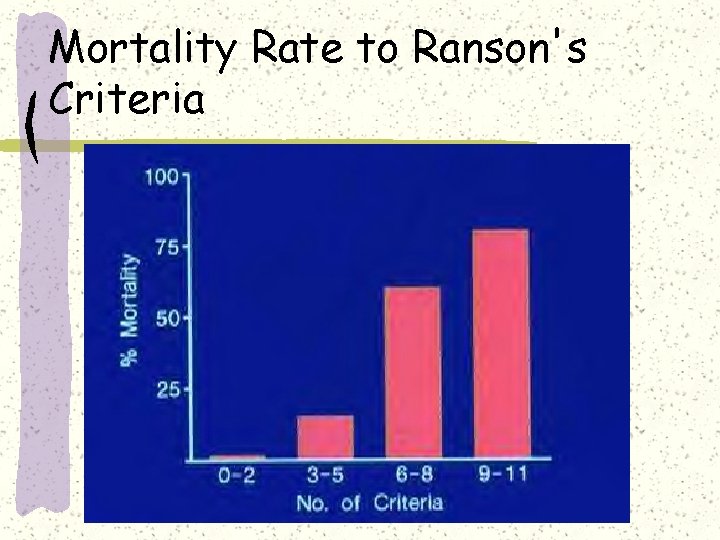
Ranson’s Criteria Relation to morbidity/mortality 2 or fewer signs: 1% mortality 3 signs: severe pancreatitis 3 -4 signs: 15% mortality 5 -6 signs: 40% mortality More than 6 signs: better ask for the priest for fire proofing!!
Mortality Rate to Ranson's Criteria
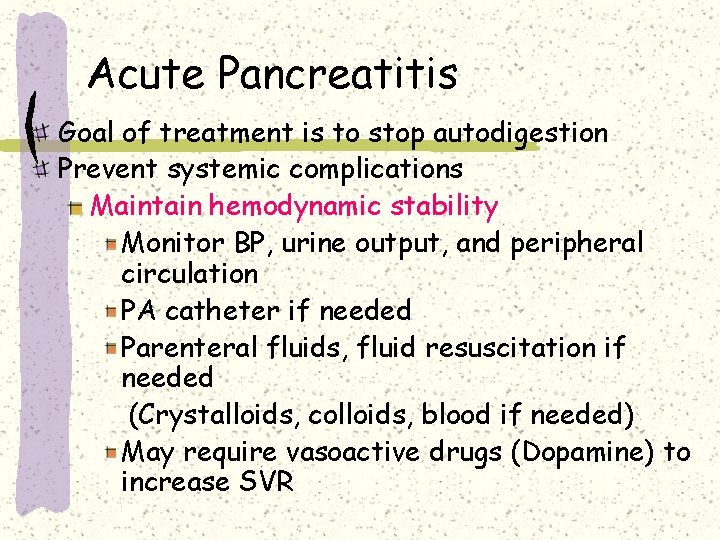
Acute Pancreatitis Goal of treatment is to stop autodigestion Prevent systemic complications Maintain hemodynamic stability Monitor BP, urine output, and peripheral circulation PA catheter if needed Parenteral fluids, fluid resuscitation if needed (Crystalloids, colloids, blood if needed) May require vasoactive drugs (Dopamine) to increase SVR
Therapy Remove offending agent (if possible) Supportive !!! #1 - NPO (until pain free) NG suction for patients with ileus or emesis TPN may be needed #2 - Aggressive volume repletion with IVF Keep an eye on fluid balance/sequestration and electrolyte disturbances
Therapy continued #3 - Narcotic analgesics usually necessary for pain relief…textbooks say Meperidine… NO conclusive evidence that morphine has deleterious effect on sphincter of Oddi pressure #4 - Urgent ERCP and biliary sphincterotomy within 72 hours improves outcome of severe gallstone pancreatitis Reduced biliary sepsis, not actual improvement of pancreatic inflammation #5 - Don’t forget PPI to prevent stress ulcer
Acute Pancreatitis Improve oxygenation Supplemental oxygen May need mechanical ventilation (ARDS) Monitor Sp. O 2 via pulse ox
Acute Pancreatitis Improve oxygenation (continued) Monitor lung sounds Suction if rhonchi present Assume Fowler’s position if in compromise Promotes maximum lung expansion Watch for atelectasis or hypoxia Encourage cough and deep breath, walk to maintain lung function
Acute Pancreatitis Maintain metabolic balance Monitor for electrolyte imbalances such as hypokalemia and hypocalcemia (assess for Chvostek’s and Trousseau’s sign) Watch for arrhythmias Watch glucose, may need insulin Monitor BUN and Creatinine Follow amylase and lipase levels Obtain daily albumin levels
Acute Pancreatitis Pain management Narcotics to relieve pain around the clock Demerol not MSO 4, but morphine lasts longer so. .
Pancreatitis Nursing Interventions Administer analgesics, antacids, anticholinergics as ordered, monitor effects Withhold food/fluid and eliminate odor and sight of food from environment to decrease pancreatic stimulations Maintain NG tube and assess for drainage
Pancreatitis Nursing Interventions (continued) Institute nonpharmacologic measures to decrease pain Assist patient to position of comfort (kneechest; fetal position) Teach relaxation techniques and provide a quiet, restful environment
Patient and Family Teaching Talk about conditions which caused illness Importance to sticking to a bland, low-fat, high carbohydrate diet avoiding large meals and caffeine Make sure they know the symptoms of acute pancreatitis
Pancreatitis Nursing Interventions (continued) Provide patient teaching and discharge planning concerning Dietary regimen when oral intake permitted High-carbohydrate, high-protein, low-fat diet Eating small, frequent meals instead of 3 large ones Avoid caffeine products Eliminate alcohol Maintain relaxed atmosphere after meals
Pancreatitis Nursing Interventions (continued) Recognition and reporting of signs of complications Continued nausea and vomiting Abdominal distention with increased fullness Persistent weight loss Severe epigastric or back pain Frothy/foul-smelling bowel movements Irritability, confusion, persistent elevation of temperature (2 days)
Acute Pancreatitis Measure all Intake and Output Vomit, blood loss, etc. Auscultate bowel sounds Initially will diminish or absent Weigh daily Measure abdominal girth if ascites is suspected Check oral and nasal mucosa for signs of dryness and cracking
Acute Pancreatitis Electrolyte replacement Reduction of pancreatic secretions “resting the pancreas” NPO halts pancreatic enzymes NG tube reduces HCL in stomach Administer histamine 2 blockers to further reduce acid Nutritional support via TPN Renal support Surgical therapies Complications prevention (pulmonary, cardiac, and renal
After the acute phase Once subsided, BS will resume, abdominal pain will diminish, and patient should report feeling hungry May resume eating Clear liquids Small carbs No spicy foods or caffeinated beverages No fat or high protein May need antispasmotics, anticholinergics and antacids to reduce gastric and pancreatic juices
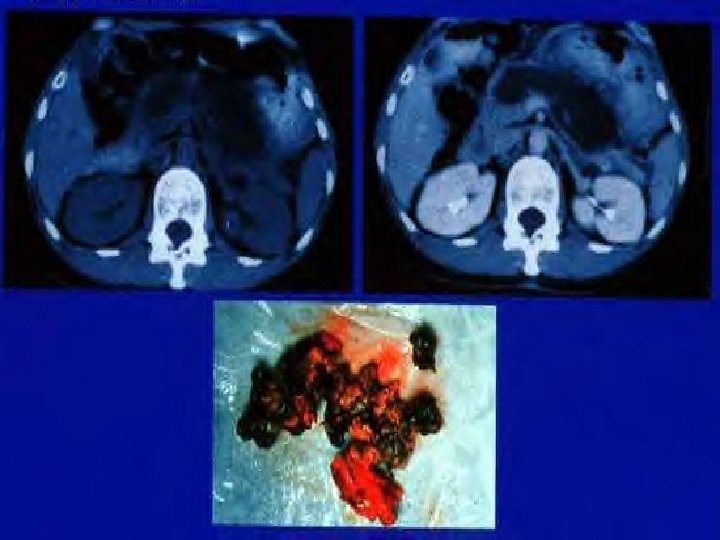
Complications Necrotizing pancreatitis Significantly increases morbidity & mortality Usually found on CT with IV contrast Pseudocysts Suggested by persistent pain or continued high amylase levels (may be present for 4 -6 wks afterward) Cyst may become infected, rupture, hemorrhage or obstruct adjacent structures Asymptomatic, non-enlarging pseudocysts can be watched and followed with imaging Symptomatic, rapidly enlarging or complicated pseudocysts need to be decompressed
Complications continued #2 Infection Many areas for concern: abscess, pancreatic necrosis, infected pseudocyst, cholangitis, and aspiration pneumonia -> SEPSIS may occur If concerned, obtain cultures and start broadspectrum antimicrobials (appropriate for bowel flora) In the absence of fever or other clinical evidence for infection, prophylactic antibiotics is not indicated Renal failure Severe intravascular volume depletion or acute tubular necrosis may lead to ARF
Complications continued #3 Pulmonary Atelectasis, pleural effusion, pneumonia and ARDS can develop in severe cases Other Metabolic disturbances hypocalcemia, hypomagnesemia, hyperglycemia GI bleeds Stress gastritis Fistula formation
Long-term Sequelae Chronic Pancreatitis Characterized by chronic and progressive loss of pancreatic parenchyma Both endocrine (DM) and exocrine (steatorrhea, azotorrhea) insufficiency develop when 80% to 90% of gland is destroyed Pancreatic calcification (from intraductal calcium carbonate deposits) may be apparent on plain abdominal x-ray Patients may require insulin, pancreatic enzyme replacement (Creon), and medium-chain triglycerides
Long-term Sequelae Pseudocyst Formation Collection of enzyme-rich pancreatic fluid and tissue debris arising within areas of necrosis Result from the formation of granulation tissue within the pancreas May be asymptomatic and resolve spontaneously Treatment Drainage Resection Indicated if they persist for more than 6 weeks, are enlarging, or are symptomatic
Prognosis 85 -90% mild, self-limited Usually resolves in 3 -7 days 10 -15% severe requiring ICU admission Mortality may approach 50% in severe cases
Long-term Sequelae Pleural Fistulas and Pancreatic Ascities Result from pancreatic fluid entering pleural space or abdomen Treatment includes: Repeated aspiration Diuretics Carbonic anhydrase inhibitors Surgical resection
Chronic pancreatitis Pathophys - irreversible parenchymal destruction leading to pancreatic dysfunction Persistent, recurrent episodes of severe pain Anorexia, nausea Constipation, flatulence Steatorrhea Diabetes
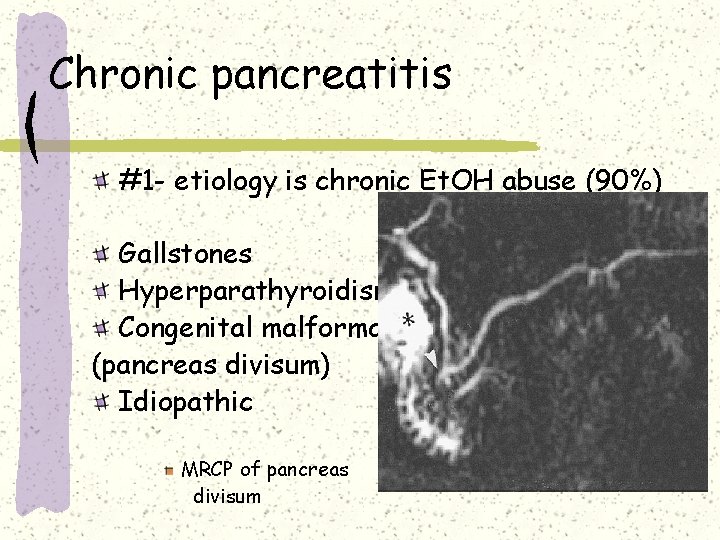
Chronic pancreatitis #1 - etiology is chronic Et. OH abuse (90%) Gallstones Hyperparathyroidism Congenital malformation (pancreas divisum) Idiopathic MRCP of pancreas divisum
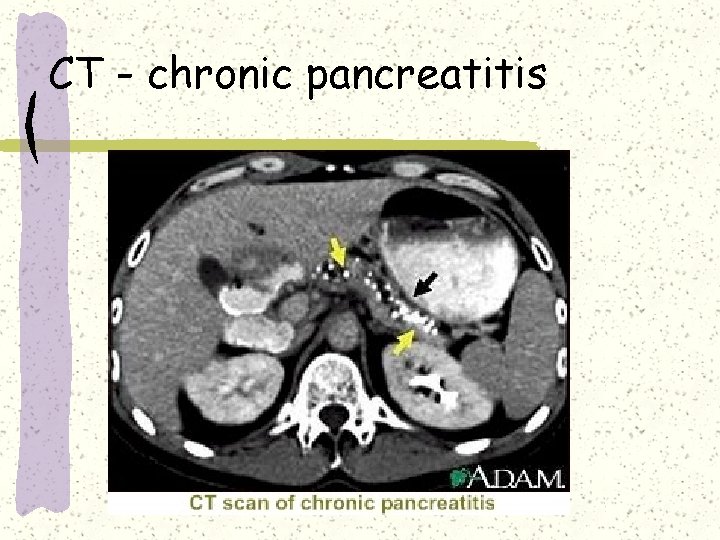
Evaluation or normal amylase and lipase Plain AXR / CT may show calcified pancreas Pain management critical Et. OH cessation may improve pain Narcotic dependency is common
CT - chronic pancreatitis
Complications Exocrine insufficiency typically manifests as weight loss and steatorrhea If steatorrhea present, a trypsinogen level < 10 is diagnostic for chronic pancreatitis Manage with low-fat diet and pancreatic enzyme supplements (Pancrease, Creon) Endocrine insufficiency may result from islet cell destruction which leads to diabetes
Conclusion Pancreatitis is common YOU WILL SEE IT!!! 10 -15% are severe = ICU admission Mortality may approach 50% in severe cases These are the cases where knowing future complications would be great (ie finding a marker that correlates with severity…and that’s what the clinical researchers are attempting to do)
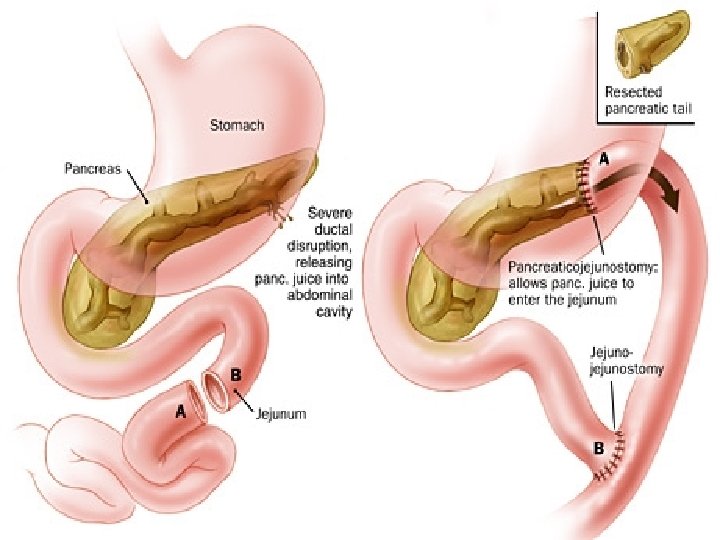
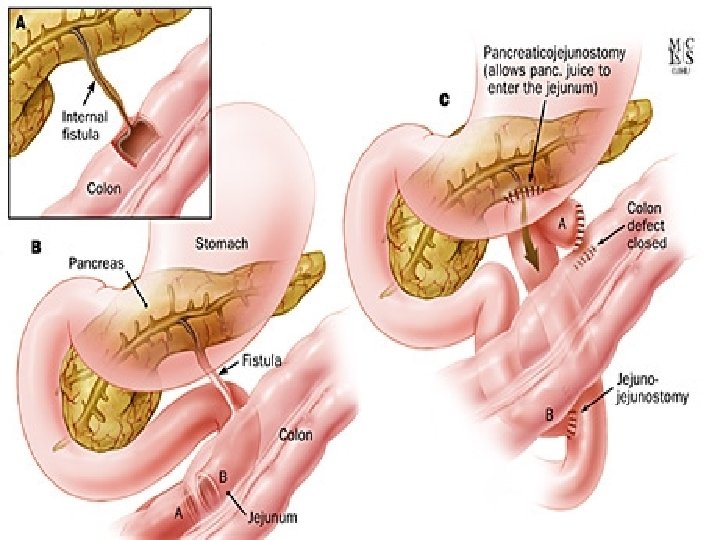
Management of the Patient with Pancreatic Dysfunction Cancers of the pancreas Hyperinsulinemia Zollinger-Ellison Syndrome Surgical management of Pancreatic Disorders Pancreaticojejunostomy Whipple Procedure Pancreatectomy
Cancer of the Pancreas Most pancreatic tumors are adenocarcinomas and half occur in the head of the pancreas TUMOR GROWTH RESULTS IN COMMON BILE DUCT OBSTRUCTION WITH JAUNDICE Men (more common in Black / Jewish) 45 -65 Contributing factors: Chemical carcinogens Cigarette smoking High-fat diet Diabetes Mellitus Prognosis generally poor
Smoking !!!!!! Who is this big smoker? ?
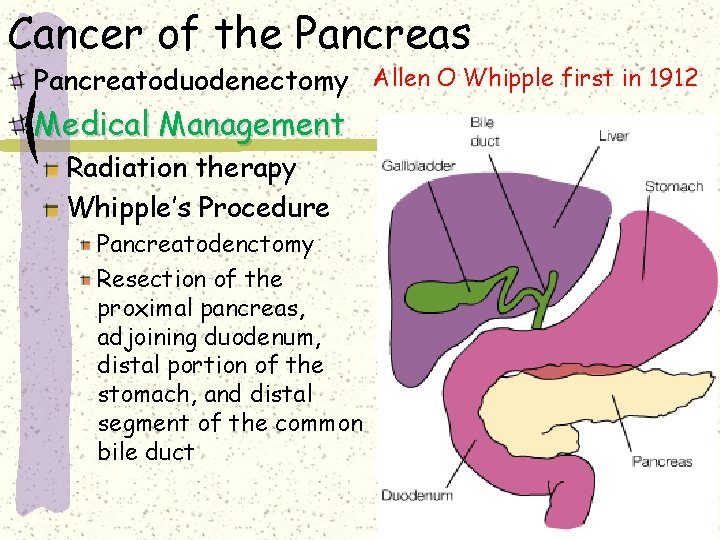
Cancer of the Pancreas Pancreatoduodenectomy Allen O Whipple first in 1912 Medical Management Radiation therapy Whipple’s Procedure Pancreatodenctomy Resection of the proximal pancreas, adjoining duodenum, distal portion of the stomach, and distal segment of the common bile duct
Cancer of the Pancreas Drug Therapy necessary after surgery Pancreatic enzymes Oral hypoglycemic agents or insulin Bile salts Chemotherapy
Cancer of the Pancreas Assessment Findings Anorexia Rapid , progressive weight loss Dull abdominal pain located in upper abdomen or left hypochondrial region with radiation to the back Related to eating Jaundice
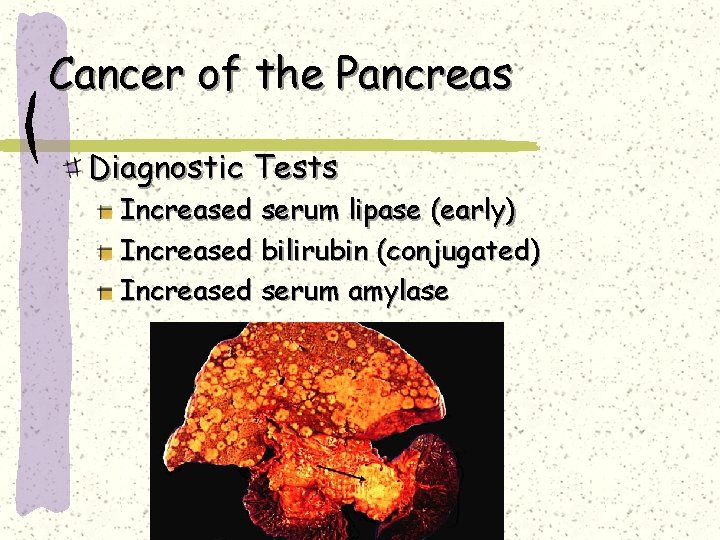
Cancer of the Pancreas Diagnostic Tests Increased serum lipase (early) Increased bilirubin (conjugated) Increased serum amylase
Cancer of the Pancreas Nursing Interventions Same as Pancreatitis Provide care for the patient receiving radiation therapy or chemotherapy Routine pre- and post-op care (for patients undergoing Whipple’s procedure) Provide emotional supports to patient / family Provide patient teaching and discharge planning concerning Need to eat small frequent meals of a low-fat, highcalorie diet with vitamin supplements Importance of adhering to medication regimen after surgery
Hyperinsulinism Overproduction of insulin by pancreatic islets (hyperplasia) or ectopic insulin-like material Symptoms Those of excessive doses of insulin Abnormal reduction in blood glucose levels Episodes of unusual hunger, nervousness, sweating, headache, and faintness Seizures and unconsciousness Treatment Glucose Surgical removal of tissue 15% will go on to develop DM
Zollinger-Ellison Syndrome Ulcerogenic tumors Tumor of the islets of Langerhans causes hypersecretion of gastric acid that produces ulcers in stomach, duodenum, jejunum Gastrinomas may occur as single tumors or as multiple, small tumors. About one-half to twothirds of single gastrinomas are malignant tumors that most commonly spread to the liver and lymph nodes near the pancreas and small bowel.
The End. . . .