
ACO 101 Overview of DartmouthHitchcock Health Pioneer ACO












- Slides: 37
ACO 101: Overview of Dartmouth-Hitchcock Health Pioneer ACO Model and One. Care Vermont ACO Models Lynn Guillette, CPA, MBA May 3, 2014
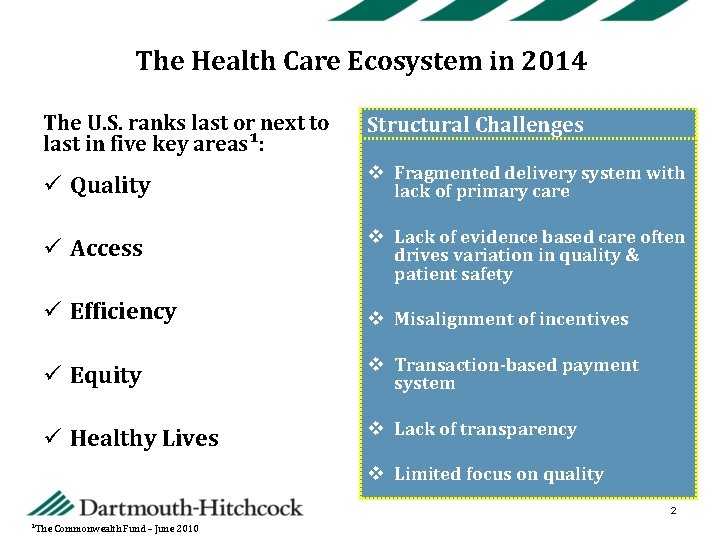
The Health Care Ecosystem in 2014 The U. S. ranks last or next to last in five key areas¹: Structural Challenges ü Quality v Fragmented delivery system with lack of primary care ü Access v Lack of evidence based care often drives variation in quality & patient safety ü Efficiency v Misalignment of incentives ü Equity v Transaction-based payment system ü Healthy Lives v Lack of transparency v Limited focus on quality 2 ¹The Commonwealth Fund – June 2010
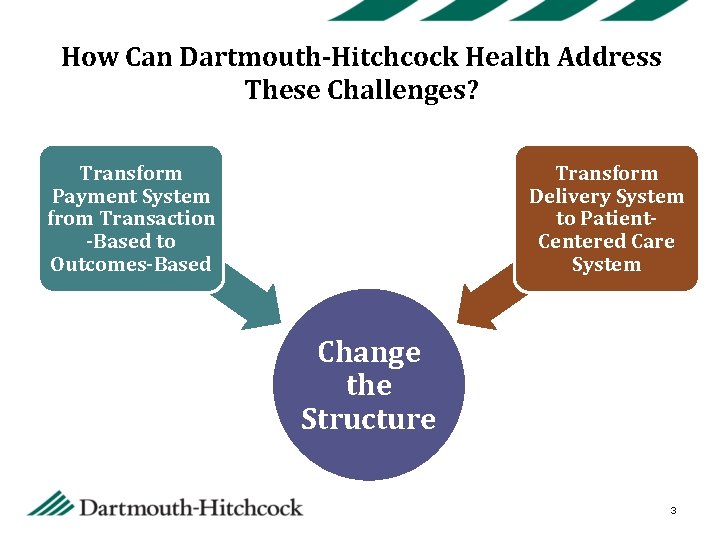
How Can Dartmouth-Hitchcock Health Address These Challenges? Transform Payment System from Transaction -Based to Outcomes-Based Transform Delivery System to Patient. Centered Care System Change the Structure 3
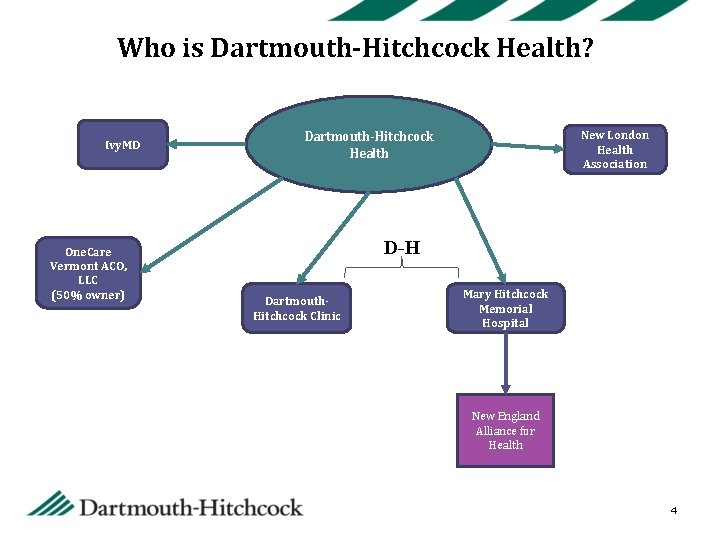
Who is Dartmouth-Hitchcock Health? Ivy. MD One. Care Vermont ACO, LLC (50% owner) Dartmouth-Hitchcock Health New London Health Association D-H Dartmouth. Hitchcock Clinic Mary Hitchcock Memorial Hospital New England Alliance for Health 4
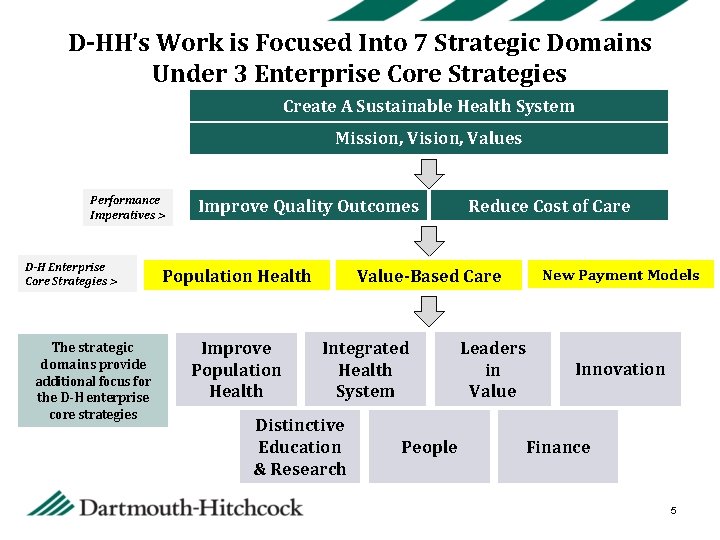
D-HH’s Work is Focused Into 7 Strategic Domains Under 3 Enterprise Core Strategies Create A Sustainable Health System Mission, Vision, Values Performance Imperatives > D-H Enterprise Core Strategies > The strategic domains provide additional focus for the D-H enterprise core strategies Improve Quality Outcomes Population Health Improve Population Health Reduce Cost of Care New Payment Models Value-Based Care Integrated Health System Distinctive Education & Research People Leaders in Value Innovation Finance 5
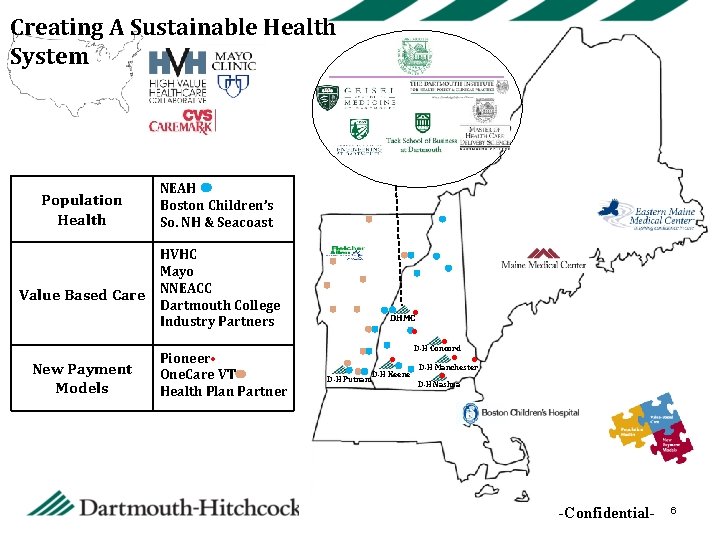
Creating A Sustainable Health System Population Health NEAH Boston Children’s So. NH & Seacoast Value Based Care HVHC Mayo NNEACC Dartmouth College Industry Partners New Payment Models Pioneer • One. Care VT Health Plan Partner ME NH VT • • DHMC • D-H Keene D-H Putnam • D-H Concord • • D-H Manchester • D-H Nashua MA -Confidential- 6
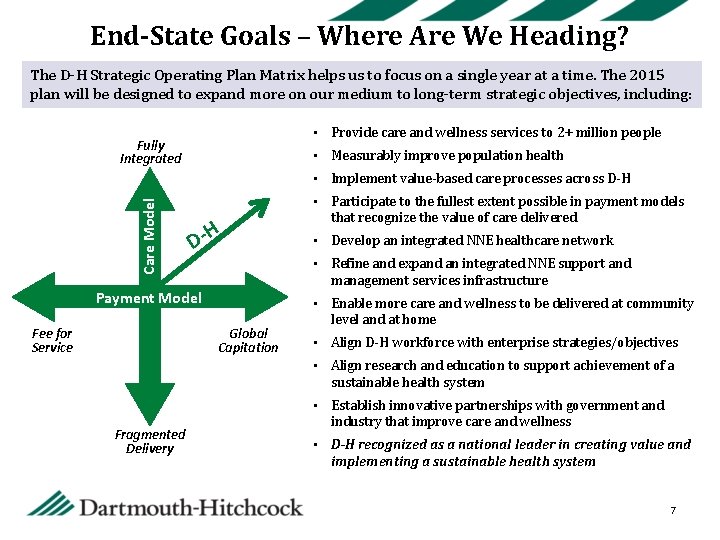
End-State Goals – Where Are We Heading? The D-H Strategic Operating Plan Matrix helps us to focus on a single year at a time. The 2015 plan will be designed to expand more on our medium to long-term strategic objectives, including: • Provide care and wellness services to 2+ million people Fully Integrated • Measurably improve population health Care Model • Implement value-based care processes across D-H H D- • Develop an integrated NNE healthcare network • Refine and expand an integrated NNE support and management services infrastructure Payment Model Fee for Service • Participate to the fullest extent possible in payment models that recognize the value of care delivered Global Capitation • Enable more care and wellness to be delivered at community level and at home • Align D-H workforce with enterprise strategies/objectives • Align research and education to support achievement of a sustainable health system Fragmented Delivery • Establish innovative partnerships with government and industry that improve care and wellness • D-H recognized as a national leader in creating value and implementing a sustainable health system 7
To Transform the Payment System, We Need to Learn a New Language Fee For Service Global Budget Accountable Care Organization Pay for Performance Shared Risk 8
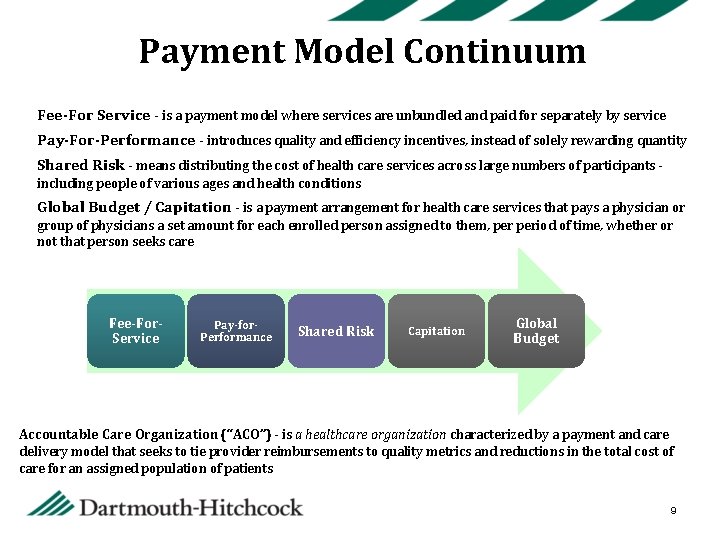
Payment Model Continuum Fee-For Service - is a payment model where services are unbundled and paid for separately by service Pay-For-Performance - introduces quality and efficiency incentives, instead of solely rewarding quantity Shared Risk - means distributing the cost of health care services across large numbers of participants including people of various ages and health conditions Global Budget / Capitation - is a payment arrangement for health care services that pays a physician or group of physicians a set amount for each enrolled person assigned to them, period of time, whether or not that person seeks care Fee-For. Service Volume Focused Pay-for. Performance Shared Risk Capitation Global Budget Value Focused Accountable Care Organization (“ACO”) - is a healthcare organization characterized by a payment and care delivery model that seeks to tie provider reimbursements to quality metrics and reductions in the total cost of care for an assigned population of patients 9
More about ACOs ü Providers in an ACO may all belong to the same health system, or may include multiple health systems, independent hospitals, physician groups/practices, and other types of healthcare providers üProviders work together with a payor to provide high quality coordinated care for patients Doctors, Hospitals, Other Healthcare Providers üMay include one or more payors üMay include any one (or more) of the four payment methodologies outlined on slide 9 üQuality performance is measured at the aggregate ACO level Accountable Care Organization (“ACO”) Payor(s) üThe ACO would be rewarded for providing the ACO’s patients with a positive patient experience, better health outcomes, and reduction in the growth of total cost of care for the ACO patient population 10
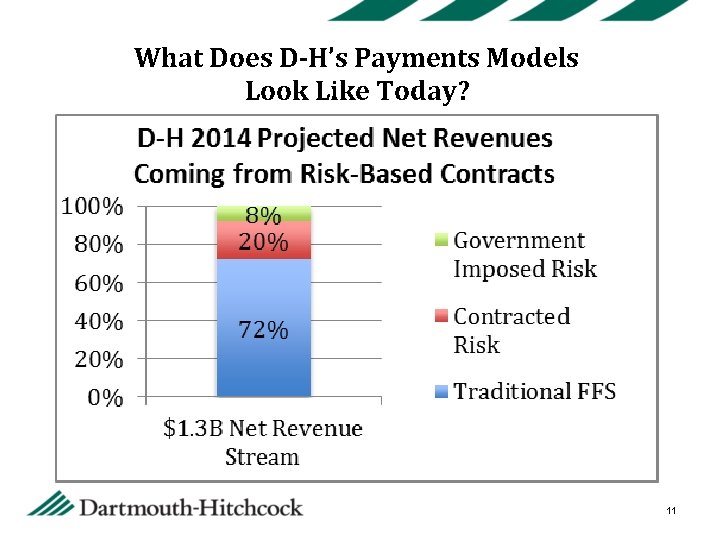
What Does D-H’s Payments Models Look Like Today? 11
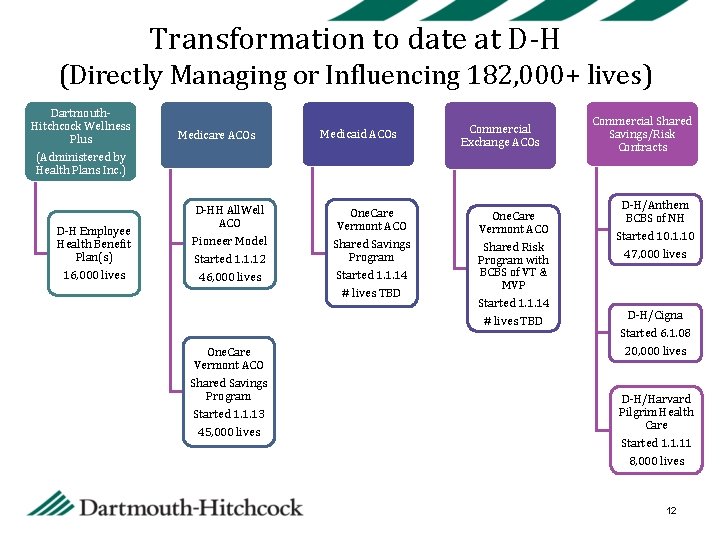
Transformation to date at D-H (Directly Managing or Influencing 182, 000+ lives) Dartmouth. Hitchcock Wellness Plus Medicare ACOs Medicaid ACOs Commercial Exchange ACOs (Administered by Health Plans Inc. ) D-H Employee Health Benefit Plan(s) 16, 000 lives D-HH All. Well ACO Pioneer Model Started 1. 1. 12 46, 000 lives One. Care Vermont ACO Shared Savings Program Started 1. 1. 13 45, 000 lives One. Care Vermont ACO Shared Savings Program Started 1. 1. 14 # lives TBD One. Care Vermont ACO Shared Risk Program with BCBS of VT & MVP Started 1. 1. 14 # lives TBD Commercial Shared Savings/Risk Contracts D-H/Anthem BCBS of NH Started 10. 1. 10 47, 000 lives D-H/Cigna Started 6. 1. 08 20, 000 lives D-H/Harvard Pilgrim Health Care Started 1. 1. 11 8, 000 lives 12
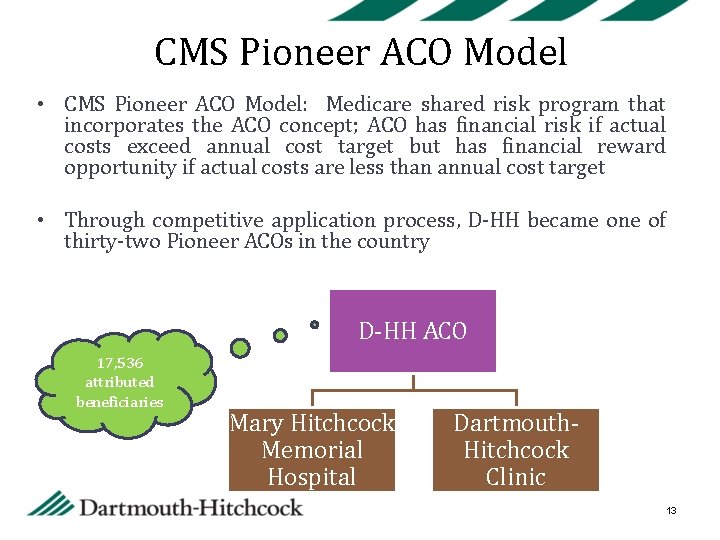
CMS Pioneer ACO Model • CMS Pioneer ACO Model: Medicare shared risk program that incorporates the ACO concept; ACO has financial risk if actual costs exceed annual cost target but has financial reward opportunity if actual costs are less than annual cost target • Through competitive application process, D-HH became one of thirty-two Pioneer ACOs in the country D-HH ACO 17, 536 attributed beneficiaries Mary Hitchcock Memorial Hospital Dartmouth. Hitchcock Clinic 13
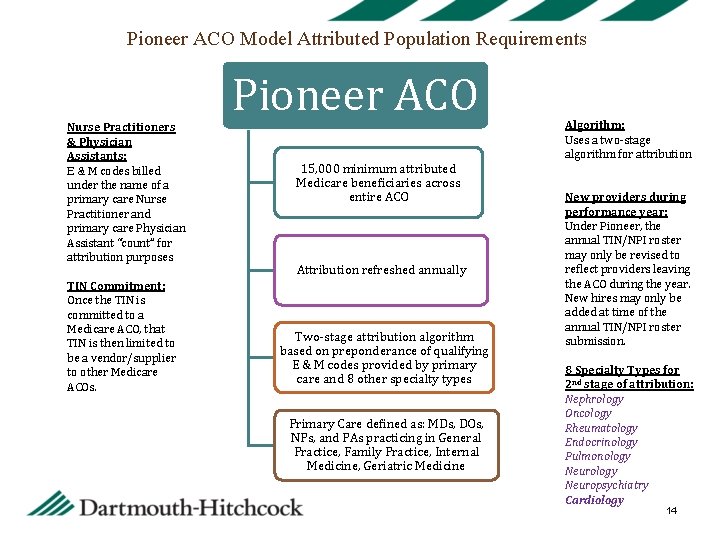
Pioneer ACO Model Attributed Population Requirements Nurse Practitioners & Physician Assistants: E & M codes billed under the name of a primary care Nurse Practitioner and primary care Physician Assistant “count” for attribution purposes TIN Commitment: Once the TIN is committed to a Medicare ACO, that TIN is then limited to be a vendor/supplier to other Medicare ACOs. Pioneer ACO 15, 000 minimum attributed Medicare beneficiaries across entire ACO Attribution refreshed annually Two-stage attribution algorithm based on preponderance of qualifying E & M codes provided by primary care and 8 other specialty types Primary Care defined as: MDs, DOs, NPs, and PAs practicing in General Practice, Family Practice, Internal Medicine, Geriatric Medicine Algorithm: Uses a two-stage algorithm for attribution New providers during performance year: Under Pioneer, the annual TIN/NPI roster may only be revised to reflect providers leaving the ACO during the year. New hires may only be added at time of the annual TIN/NPI roster submission. 8 Specialty Types for 2 nd stage of attribution: Nephrology Oncology Rheumatology Endocrinology Pulmonology Neuropsychiatry Cardiology 14
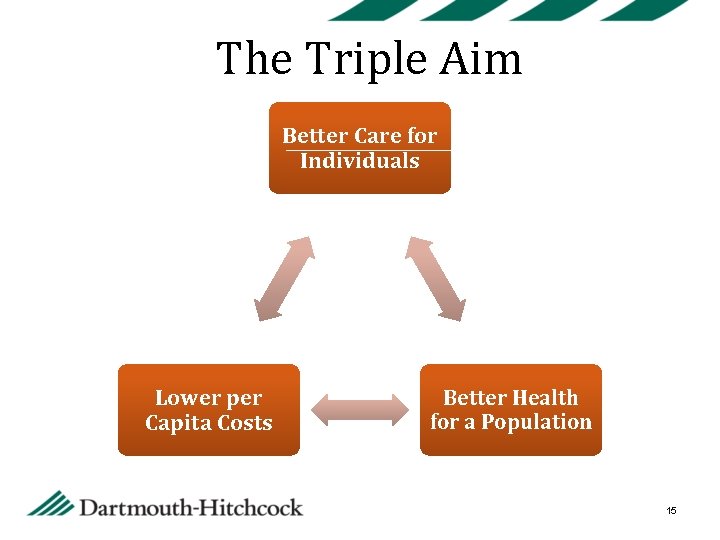
The Triple Aim Better Care for Individuals Lower per Capita Costs Better Health for a Population 15
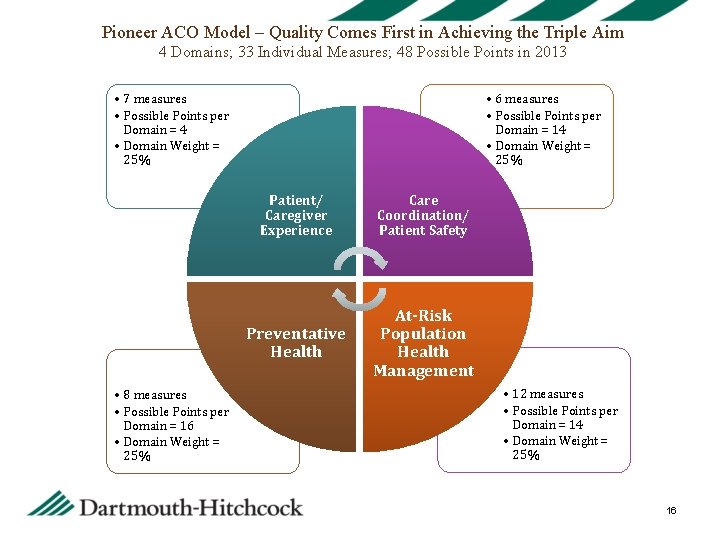
Pioneer ACO Model – Quality Comes First in Achieving the Triple Aim 4 Domains; 33 Individual Measures; 48 Possible Points in 2013 • 7 measures • Possible Points per Domain = 4 • Domain Weight = 25% • 8 measures • Possible Points per Domain = 16 • Domain Weight = 25% • 6 measures • Possible Points per Domain = 14 • Domain Weight = 25% Patient/ Caregiver Experience Care Coordination/ Patient Safety Preventative Health At-Risk Population Health Management • 12 measures • Possible Points per Domain = 14 • Domain Weight = 25% 16
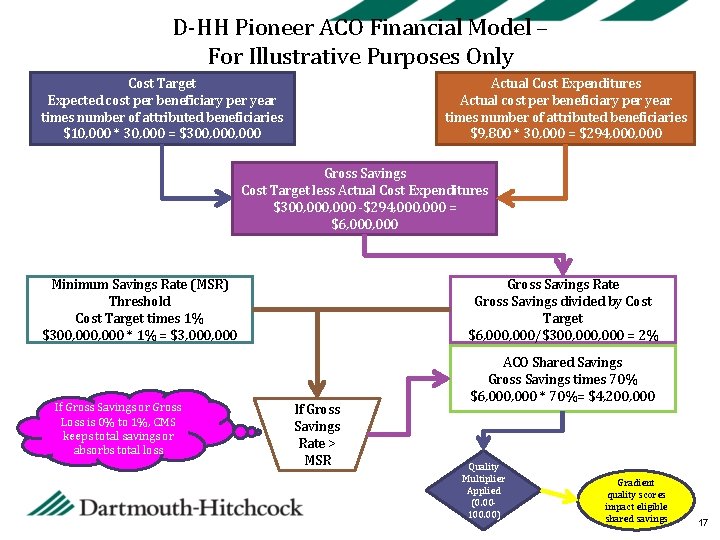
D-HH Pioneer ACO Financial Model – For Illustrative Purposes Only Cost Target Expected cost per beneficiary per year times number of attributed beneficiaries $10, 000 * 30, 000 = $300, 000 Actual Cost Expenditures Actual cost per beneficiary per year times number of attributed beneficiaries $9, 800 * 30, 000 = $294, 000 Gross Savings Cost Target less Actual Cost Expenditures $300, 000 -$294, 000 = $6, 000 Minimum Savings Rate (MSR) Threshold Cost Target times 1% $300, 000 * 1% = $3, 000 If Gross Savings or Gross Loss is 0% to 1%, CMS keeps total savings or absorbs total loss Gross Savings Rate Gross Savings divided by Cost Target $6, 000/$300, 000 = 2% If Gross Savings Rate > MSR ACO Shared Savings Gross Savings times 70% $6, 000 * 70%= $4, 200, 000 Quality Multiplier Applied (0. 00100. 00) Gradient quality scores impact eligible shared savings 17
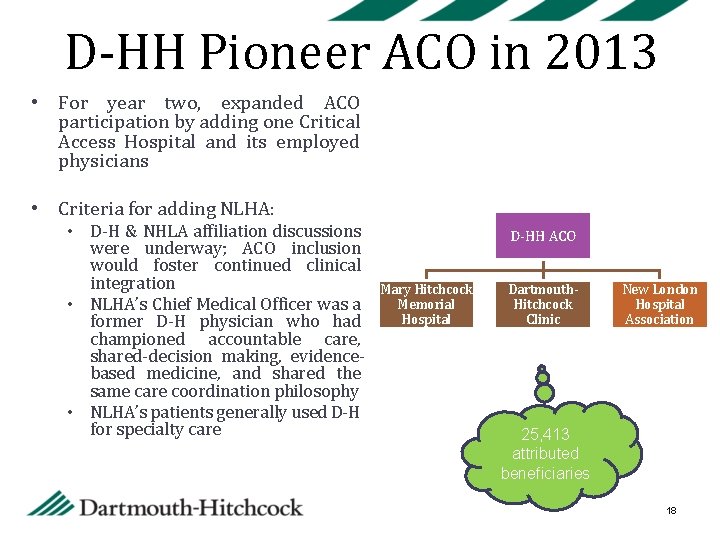
D-HH Pioneer ACO in 2013 • For year two, expanded ACO participation by adding one Critical Access Hospital and its employed physicians • Criteria for adding NLHA: • D-H & NHLA affiliation discussions were underway; ACO inclusion would foster continued clinical integration • NLHA’s Chief Medical Officer was a former D-H physician who had championed accountable care, shared-decision making, evidencebased medicine, and shared the same care coordination philosophy • NLHA’s patients generally used D-H for specialty care D-HH ACO Mary Hitchcock Memorial Hospital Dartmouth. Hitchcock Clinic New London Hospital Association 25, 413 attributed beneficiaries 18
D-HH Pioneer Expansion in Year 3 • D-H determined that it needed to expand Pioneer ACO participants beyond D-H and NLHA • Why? • To move closer to achieving our vision of creating a sustainable health system with the healthiest population possible • To lead the transformation of health care in our region and to set the standard for the nation • How? • Create rigor and structure to the expansion identification, selection, and implementation process • Adequately assess business risk to D-H and its ACO because of changes in composition of ACO provider participation 19
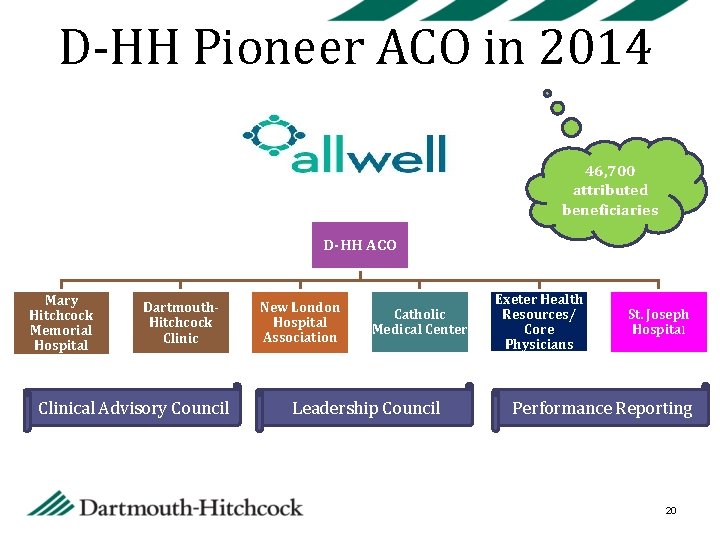
D-HH Pioneer ACO in 2014 46, 700 attributed beneficiaries D-HH ACO Mary Hitchcock Memorial Hospital Dartmouth. Hitchcock Clinical Advisory Council New London Hospital Association Catholic Medical Center Leadership Council Exeter Health Resources/ Core Physicians St. Joseph Hospital Performance Reporting 20
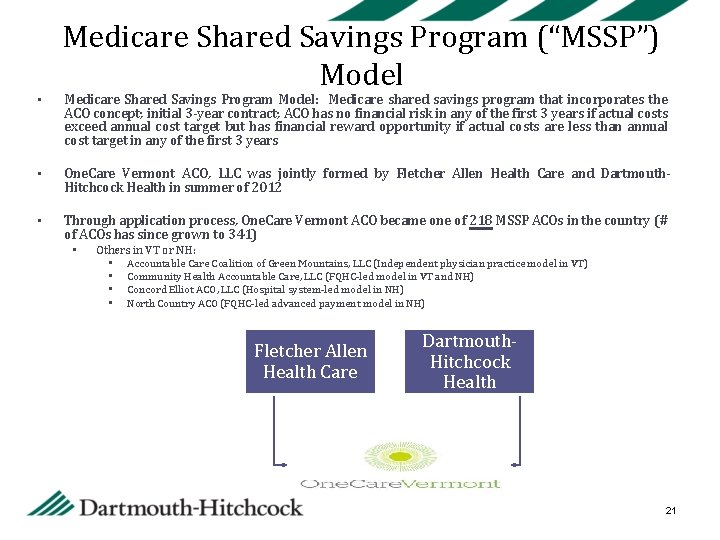
• Medicare Shared Savings Program (“MSSP”) Model Medicare Shared Savings Program Model: Medicare shared savings program that incorporates the ACO concept; initial 3 -year contract; ACO has no financial risk in any of the first 3 years if actual costs exceed annual cost target but has financial reward opportunity if actual costs are less than annual cost target in any of the first 3 years • One. Care Vermont ACO, LLC was jointly formed by Fletcher Allen Health Care and Dartmouth. Hitchcock Health in summer of 2012 • Through application process, One. Care Vermont ACO became one of 218 MSSP ACOs in the country (# of ACOs has since grown to 341) • Others in VT or NH: • Accountable Care Coalition of Green Mountains, LLC (Independent physician practice model in VT) • Community Health Accountable Care, LLC (FQHC-led model in VT and NH) • Concord Elliot ACO, LLC (Hospital system-led model in NH) • North Country ACO (FQHC-led advanced payment model in NH) Fletcher Allen Health Care Dartmouth. Hitchcock Health 21
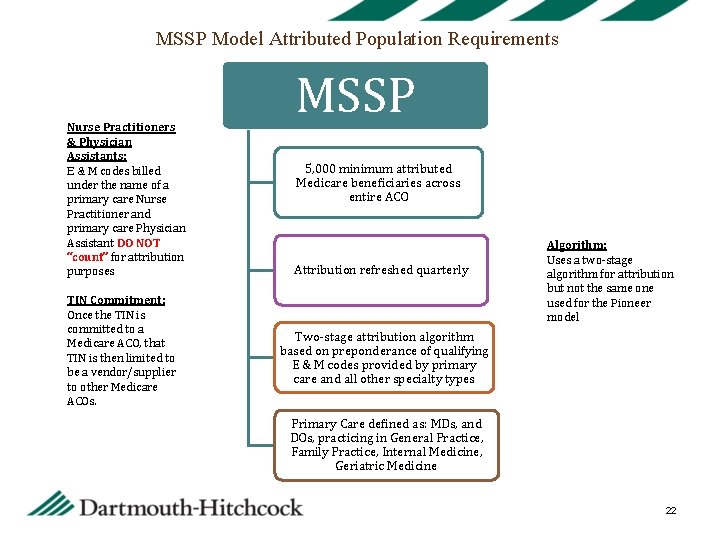
MSSP Model Attributed Population Requirements Nurse Practitioners & Physician Assistants: E & M codes billed under the name of a primary care Nurse Practitioner and primary care Physician Assistant DO NOT “count” for attribution purposes TIN Commitment: Once the TIN is committed to a Medicare ACO, that TIN is then limited to be a vendor/supplier to other Medicare ACOs. MSSP 5, 000 minimum attributed Medicare beneficiaries across entire ACO Attribution refreshed quarterly Algorithm: Uses a two-stage algorithm for attribution but not the same one used for the Pioneer model Two-stage attribution algorithm based on preponderance of qualifying E & M codes provided by primary care and all other specialty types Primary Care defined as: MDs, and DOs, practicing in General Practice, Family Practice, Internal Medicine, Geriatric Medicine 22
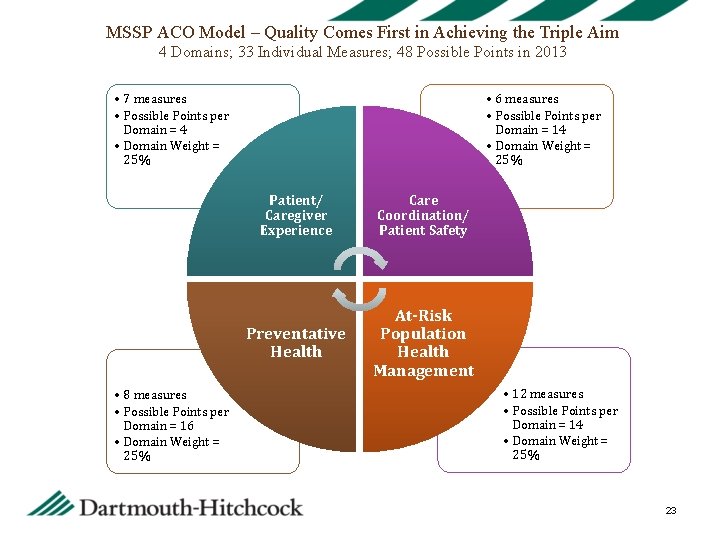
MSSP ACO Model – Quality Comes First in Achieving the Triple Aim 4 Domains; 33 Individual Measures; 48 Possible Points in 2013 • 7 measures • Possible Points per Domain = 4 • Domain Weight = 25% • 8 measures • Possible Points per Domain = 16 • Domain Weight = 25% • 6 measures • Possible Points per Domain = 14 • Domain Weight = 25% Patient/ Caregiver Experience Care Coordination/ Patient Safety Preventative Health At-Risk Population Health Management • 12 measures • Possible Points per Domain = 14 • Domain Weight = 25% 23
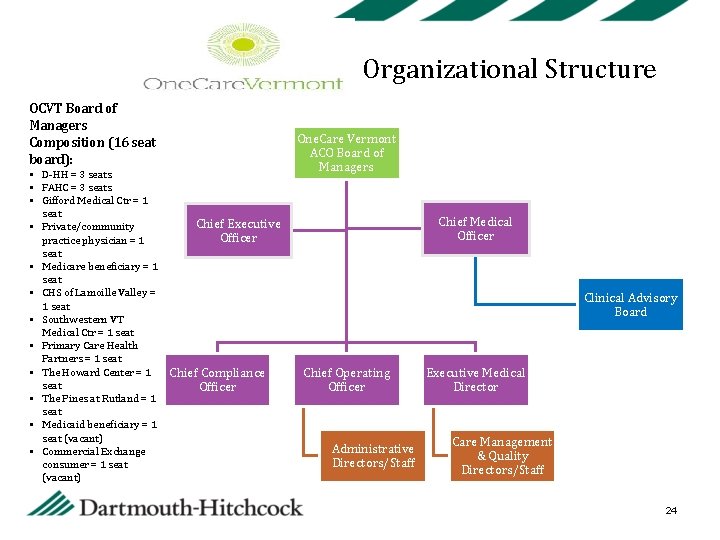
Organizational Structure OCVT Board of Managers Composition (16 seat board): § D-HH = 3 seats § FAHC = 3 seats § Gifford Medical Ctr = 1 seat § Private/community practice physician = 1 seat § Medicare beneficiary = 1 seat § CHS of Lamoille Valley = 1 seat § Southwestern VT Medical Ctr = 1 seat § Primary Care Health Partners = 1 seat § The Howard Center = 1 seat § The Pines at Rutland = 1 seat § Medicaid beneficiary = 1 seat (vacant) § Commercial Exchange consumer = 1 seat (vacant) One. Care Vermont ACO Board of Managers Chief Medical Officer Chief Executive Officer Clinical Advisory Board Chief Compliance Officer Chief Operating Officer Administrative Directors/Staff Executive Medical Director Care Management & Quality Directors/Staff 24
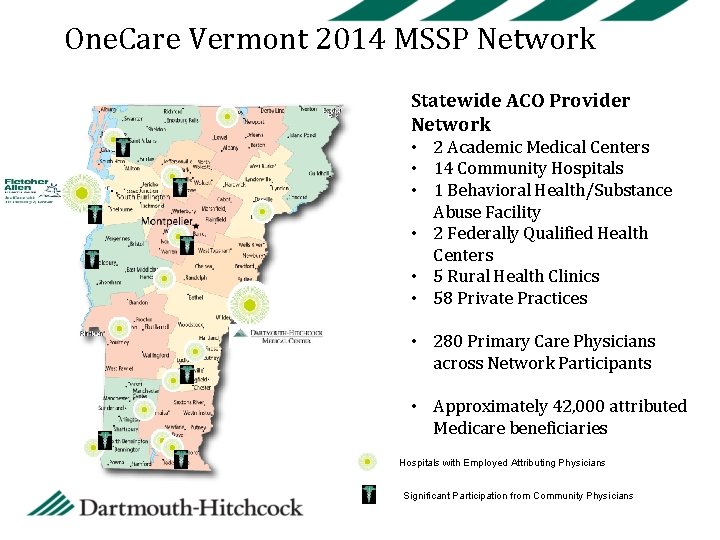
One. Care Vermont 2014 MSSP Network Statewide ACO Provider Network • 2 Academic Medical Centers • 14 Community Hospitals • 1 Behavioral Health/Substance Abuse Facility • 2 Federally Qualified Health Centers • 5 Rural Health Clinics • 58 Private Practices • 280 Primary Care Physicians across Network Participants • Approximately 42, 000 attributed Medicare beneficiaries Hospitals with Employed Attributing Physicians Significant Participation from Community Physicians
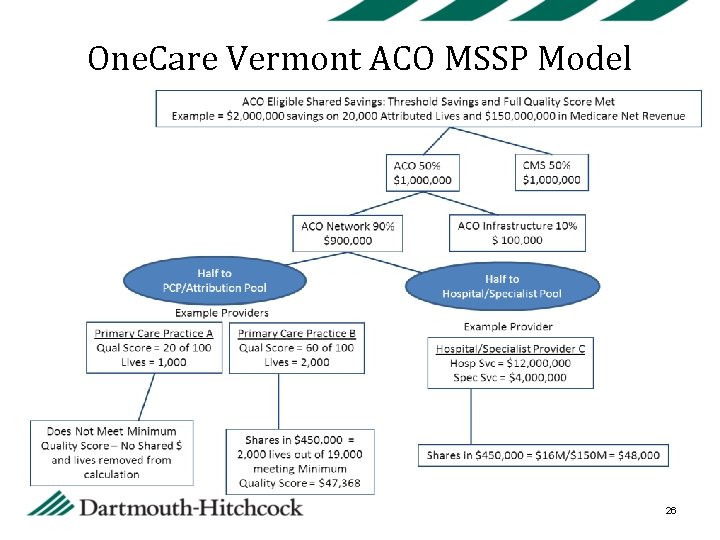
One. Care Vermont ACO MSSP Model 26
NNEACC • NNEACC: Northern New England Accountable Care Collaborative • Data Trust owned by Dartmouth College, Dartmouth. Hitchcock, Eastern Maine Health, Fletcher Allen Health Care, and Maine. Health • Used by both D-HH Pioneer ACO and One. Care Vermont • Proprietary software tools for: • • Care Coordination/Management Quality Management Physician/Practice Administrator Management User Help Desks 27
Beneficiaries Don’t Join the ACO? ü Providers and provider organizations join an ACO, not Medicare beneficiaries ü Medicare Beneficiaries assigned to a Pioneer ACO or MSSP ACO: Still have traditional FFS Medicare as primary payor Can’t be in a Medicare Advantage Plan Must have Part A and Part B Medicare coverage Can choose any provider organization that accepts Medicare – are not locked into seeing only ACO participating providers q Medicare beneficiary ID card does not indicate or reference ACO assignment q q 28
Do the Beneficiaries Know They’ve Been Assigned to the ACO? ü Beneficiaries get a one-time notice in the year that they are first assigned to a Pioneer or MSSP ACO NOTICE TO BENEFICIARIES LETTER: Your Doctor is Participating in an Accountable Care Organization Excerpt of notice <BENEFICIARY FULL NAME> <ADDRESS> <CITY STATE ZIP> <file creation date> ACOs: A Way to Better Coordinate Your Health Care Your doctor or primary care provider has chosen to participate in Dartmouth-Hitchcock Health, our Medicare Accountable Care Organization (ACO). An ACO is a group of doctors, hospitals, and health care providers working together with Medicare to give you more coordinated service and care. We’re Working to Improve Your Care The goal of an ACO is for your doctors or primary care providers to communicate closely with your other health care providers, so they can deliver high-quality care that meets your individual needs and preferences. ACOs may be rewarded for providing you with high quality, more coordinated care. 29
Can the Beneficiaries Opt-Out of ACO Assignment? ü Beneficiaries cannot opt-out of being assigned to a Pioneer ACO or MSSP ACO, but they can opt-out of allowing CMS to share their personal health information with us ü ü ü Decline to Consent to Share Information “opt-out” forms mailed out with the Notice to Beneficiaries Letter If they opt-out, they are still assigned to ACO but ACO will not receive any claims or clinical data from CMS for services provided to these beneficiaries All Medicare Beneficiaries are automatically opted-out of sharing alcohol & substance abuse data Date: January 28, 2013 Declining to Share Personal Health Information Excerpt of form Please sign this form if you do NOT want Medicare to share information about care you have received from other healthcare providers with the Dartmouth-Hitchcock Health ACO for use in coordinating your care. You can also call 1 -800 MEDICARE (1 -800 -633 -4227) instead of completing this form. TTY users should call 1 -877 -486 -2048. Your decision not to share this personal health information with the Dartmouth-Hitchcock Health ACO will remain in effect until you tell us that you have changed your preference. You may change your decision not to share your personal information at any time. Your request will take effect in approximately 60 business days. Note: Even if you don’t want to share your personal information with the Dartmouth-Hitchcock Health ACO for use in coordinating your care, Medicare will still need to use your information for some purposes, including certain financial calculations and determining the quality of care provided by the Dartmouth-Hitchcock Health ACO. Also, Medicare may share some of your personal health information with the Dartmouth-Hitchcock Health ACO as part of assessing the quality of care your healthcare providers at the Dartmouth-Hitchcock ACO are providing. 30
What can Specialists do to impact ACO models? • Development of “Anchor Specialists” and “Medical Neighbors” • • Need for rapid consult access • • Are case start times inconsistent? Are block times altered for low volume days? Are surgeons returning to office on low case OR days? Are supplies and high-cost implants standardized? Do current clinical “standard protocols” need to be revised to be more attractive in ACO environment? • • Special clinics for commonly encountered problems Special focus on fragile patients at risk for hospital care Are bookable office hours per week available to meet this demand? Assess OR Efficiency in order to support ACO Hospital • • • Special expertise/focus to support PCP ‘s management of chronic care conditions (e. g. heart failure “expert” within cardiology; Vascular support from Surgery) Diagnostic work-ups Use of shared-decision making Location of surgery (inpatient, hospital outpatient, ASC, other? ) Greater emphasis/involvement in post-acute care planning • • Use of SNFs/rehab facilities vs. home health services Encouraging “pre-hab” prior to surgery to potentially reduce post-acute care recovery times and increase patient functional restoration 31
What can Specialists do to impact ACO models? • Coordinate care with primary care providers • Encourage beneficiaries to see their primary care provider for annual Medicare Wellness preventative care visit • Collaboration between primary care coordinators and specialty care staff/nurses/care coordinators for complex patients (e. g. chronic kidney disease, oncology) and those with rare diseases (e. g. hemophilia) • Enhance patient satisfaction; what patients think about their specialty care visits matter • Assist in closing gaps in care • Emphasis on more precise coding and medical record documentation • Focus on quality performance measures that could be applicable to specialists 32
APPENDIX – Pioneer ACO’s 33 Quality Measures 33
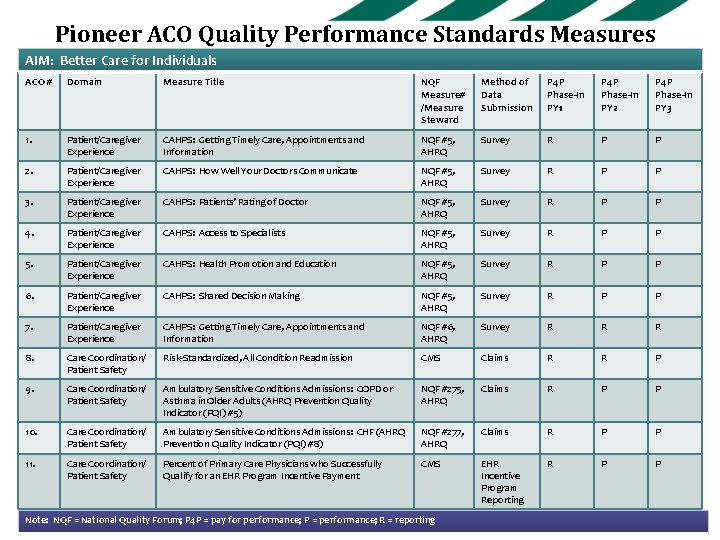
Pioneer ACO Quality Performance Standards Measures AIM: Better Care for Individuals ACO # Domain Measure Title NQF Measure# /Measure Steward Method of Data Submission P 4 P Phase-In PY 1 P 4 P Phase-In PY 2 P 4 P Phase-In PY 3 1. Patient/Caregiver Experience CAHPS: Getting Timely Care, Appointments and Information NQF #5, AHRQ Survey R P P 2. Patient/Caregiver Experience CAHPS: How Well Your Doctors Communicate NQF #5, AHRQ Survey R P P 3. Patient/Caregiver Experience CAHPS: Patients’ Rating of Doctor NQF #5, AHRQ Survey R P P 4. Patient/Caregiver Experience CAHPS: Access to Specialists NQF #5, AHRQ Survey R P P 5. Patient/Caregiver Experience CAHPS: Health Promotion and Education NQF #5, AHRQ Survey R P P 6. Patient/Caregiver Experience CAHPS: Shared Decision Making NQF #5, AHRQ Survey R P P 7. Patient/Caregiver Experience CAHPS: Getting Timely Care, Appointments and Information NQF #6, AHRQ Survey R R R 8. Care Coordination/ Patient Safety Risk-Standardized, All Condition Readmission CMS Claims R R P 9. Care Coordination/ Patient Safety Ambulatory Sensitive Conditions Admissions: COPD or Asthma in Older Adults (AHRQ Prevention Quality Indicator (PQI) #5) NQF #275, AHRQ Claims R P P 10. Care Coordination/ Patient Safety Ambulatory Sensitive Conditions Admissions: CHF (AHRQ Prevention Quality Indicator (PQI) #8) NQF #277, AHRQ Claims R P P 11. Care Coordination/ Patient Safety Percent of Primary Care Physicians who Successfully Qualify for an EHR Program Incentive Payment CMS EHR Incentive Program Reporting R P P Note: NQF = National Quality Forum; P 4 P = pay for performance; P = performance; R = reporting
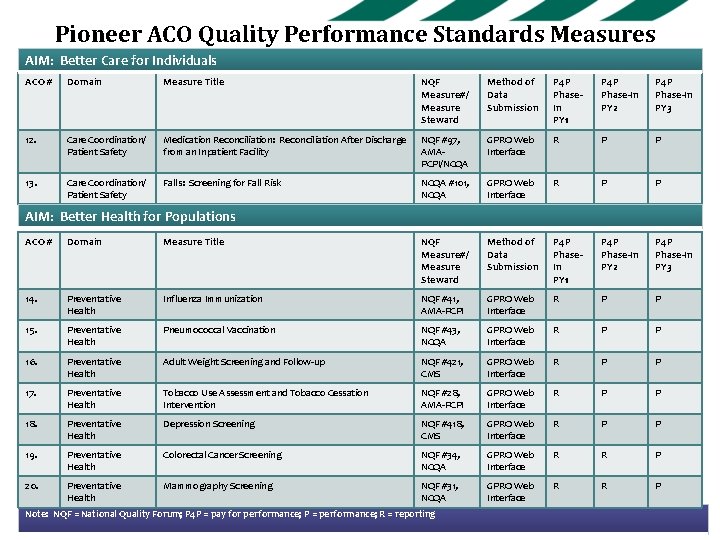
Pioneer ACO Quality Performance Standards Measures AIM: Better Care for Individuals ACO # Domain Measure Title NQF Measure#/ Measure Steward Method of Data Submission P 4 P Phase. In PY 1 P 4 P Phase-In PY 2 P 4 P Phase-In PY 3 12. Care Coordination/ Patient Safety Medication Reconciliation: Reconciliation After Discharge from an Inpatient Facility NQF #97, AMAPCPI/NCQA GPRO Web Interface R P P 13. Care Coordination/ Patient Safety Falls: Screening for Fall Risk NCQA #101, NCQA GPRO Web Interface R P P AIM: Better Health for Populations ACO # Domain Measure Title NQF Measure#/ Measure Steward Method of Data Submission P 4 P Phase. In PY 1 P 4 P Phase-In PY 2 P 4 P Phase-In PY 3 14. Preventative Health Influenza Immunization NQF #41, AMA-PCPI GPRO Web Interface R P P 15. Preventative Health Pneumococcal Vaccination NQF #43, NCQA GPRO Web Interface R P P 16. Preventative Health Adult Weight Screening and Follow-up NQF #421, CMS GPRO Web Interface R P P 17. Preventative Health Tobacco Use Assessment and Tobacco Cessation Intervention NQF #28, AMA-PCPI GPRO Web Interface R P P 18. Preventative Health Depression Screening NQF #418, CMS GPRO Web Interface R P P 19. Preventative Health Colorectal Cancer Screening NQF #34, NCQA GPRO Web Interface R R P 20. Preventative Health Mammography Screening NQF #31, NCQA GPRO Web Interface R R P Note: NQF = National Quality Forum; P 4 P = pay for performance; P = performance; R = reporting
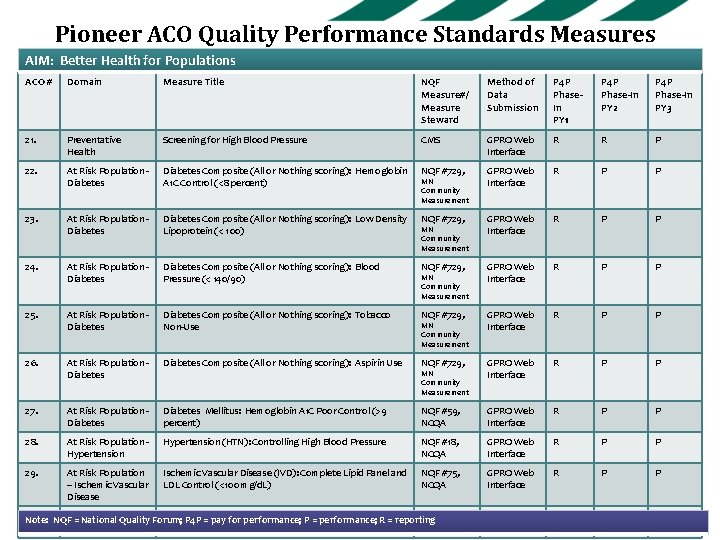
Pioneer ACO Quality Performance Standards Measures AIM: Better Health for Populations ACO # Domain Measure Title NQF Measure#/ Measure Steward Method of Data Submission P 4 P Phase. In PY 1 P 4 P Phase-In PY 2 P 4 P Phase-In PY 3 21. Preventative Health Screening for High Blood Pressure CMS GPRO Web Interface R R P 22. At Risk Population Diabetes Composite (All or Nothing scoring): Hemoglobin A 1 C Control (<8 percent) NQF #729, GPRO Web Interface R P P 23. At Risk Population Diabetes Composite (All or Nothing scoring): Low Density Lipoprotein (< 100) NQF #729, GPRO Web Interface R P P 24. At Risk Population Diabetes Composite (All or Nothing scoring): Blood Pressure (< 140/90) NQF #729, GPRO Web Interface R P P 25. At Risk Population Diabetes Composite (All or Nothing scoring): Tobacco Non-Use NQF #729, GPRO Web Interface R P P 26. At Risk Population Diabetes Composite (All or Nothing scoring): Aspirin Use NQF #729, GPRO Web Interface R P P 27. At Risk Population Diabetes Mellitus: Hemoglobin A 1 C Poor Control (>9 percent) NQF #59, NCQA GPRO Web Interface R P P 28. At Risk Population Hypertension (HTN): Controlling High Blood Pressure NQF #18, NCQA GPRO Web Interface R P P 29. At Risk Population – Ischemic Vascular Disease (IVD): Complete Lipid Panel and LDL Control (<100 mg/d. L) NQF #75, NCQA GPRO Web Interface R P P MN Community Measurement MN Community Measurement 10. Coordination/ Ambulatory Sensitive Conditions Admissions: CHF (AHRQ NQF #277, Note: NQFCare = National Quality Forum; P 4 P = pay for performance; P = performance; R = reporting Patient Safety Prevention Quality Indicator (PQI) #8) AHRQ
Pioneer ACO Quality Performance Standards Measures AIM: Better Health for Populations ACO # Domain Measure Title NQF Measure#/ Measure Steward Method of Data Submission P 4 P Phase. In PY 1 P 4 P Phase-In PY 2 P 4 P Phase-In PY 3 30. At Risk Population – Ischemic Vascular Disease (IVD): Use of Aspirin or Another Antithrombotic NQF #68, NCQA GPRO Web Interface R P P 31. At Risk Population – Heart Failure: Beta-Blocker Therapy for Left Ventricular Systolic Dysfunction (LVSD) NQF #83, AMI-PCPI GPRO Web Interface R R P 32. At Risk Population – Coronary Artery Disease (CAD) Composite: All or Nothing Scoring: Drug Therapy for Lowering LDL-Cholesterol NQF #74, GPRO Web Interface R R P 33. At Risk Population – Coronary Artery Disease (CAD) Composite: All or Nothing Scoring: Angiotensin-Converting Enzyme (ACE) Inhibitor or Angiotensin Receptor Blocker (ARB) Therapy for Patients with CAD and Diabetes and/or Left Ventricular Systolic Dysfunction (LVSD) NQF #66, GPRO Web Interface R R P CMS (Composite) /AMA-PCPI (individual component) Note: NQF = National Quality Forum; P 4 P = pay for performance; P = performance; R = reporting